Measuring Height in Inches: What Actually Works
Most people don't think about how much error they're introducing when they measure their own height. They grab a tape measure, stand against a wall, mark the top, and call it a day. The result is usually off by an inch or two, sometimes more. That margin of error matters if you're filling out a medical form, buying clothes from an international retailer, or just trying to track growth in a kid over time. Small inaccuracies add up. I ran into this a few years ago when I was helping a friend track his daughter's height progress for a pediatric visit. She was right in between chart values, and our at-home measurements were landing her in two different percentile bands depending on who measured her. We brought her back to the clinic and got a stadiometer reading that differed from our best home attempt by nearly an inch and a half. That single discrepancy could have changed a doctor's assessment. After that, I became annoyingly particular about how height gets measured and recorded.
The Ultimate Guide To Height Measurement Understanding Height By Inches Chart
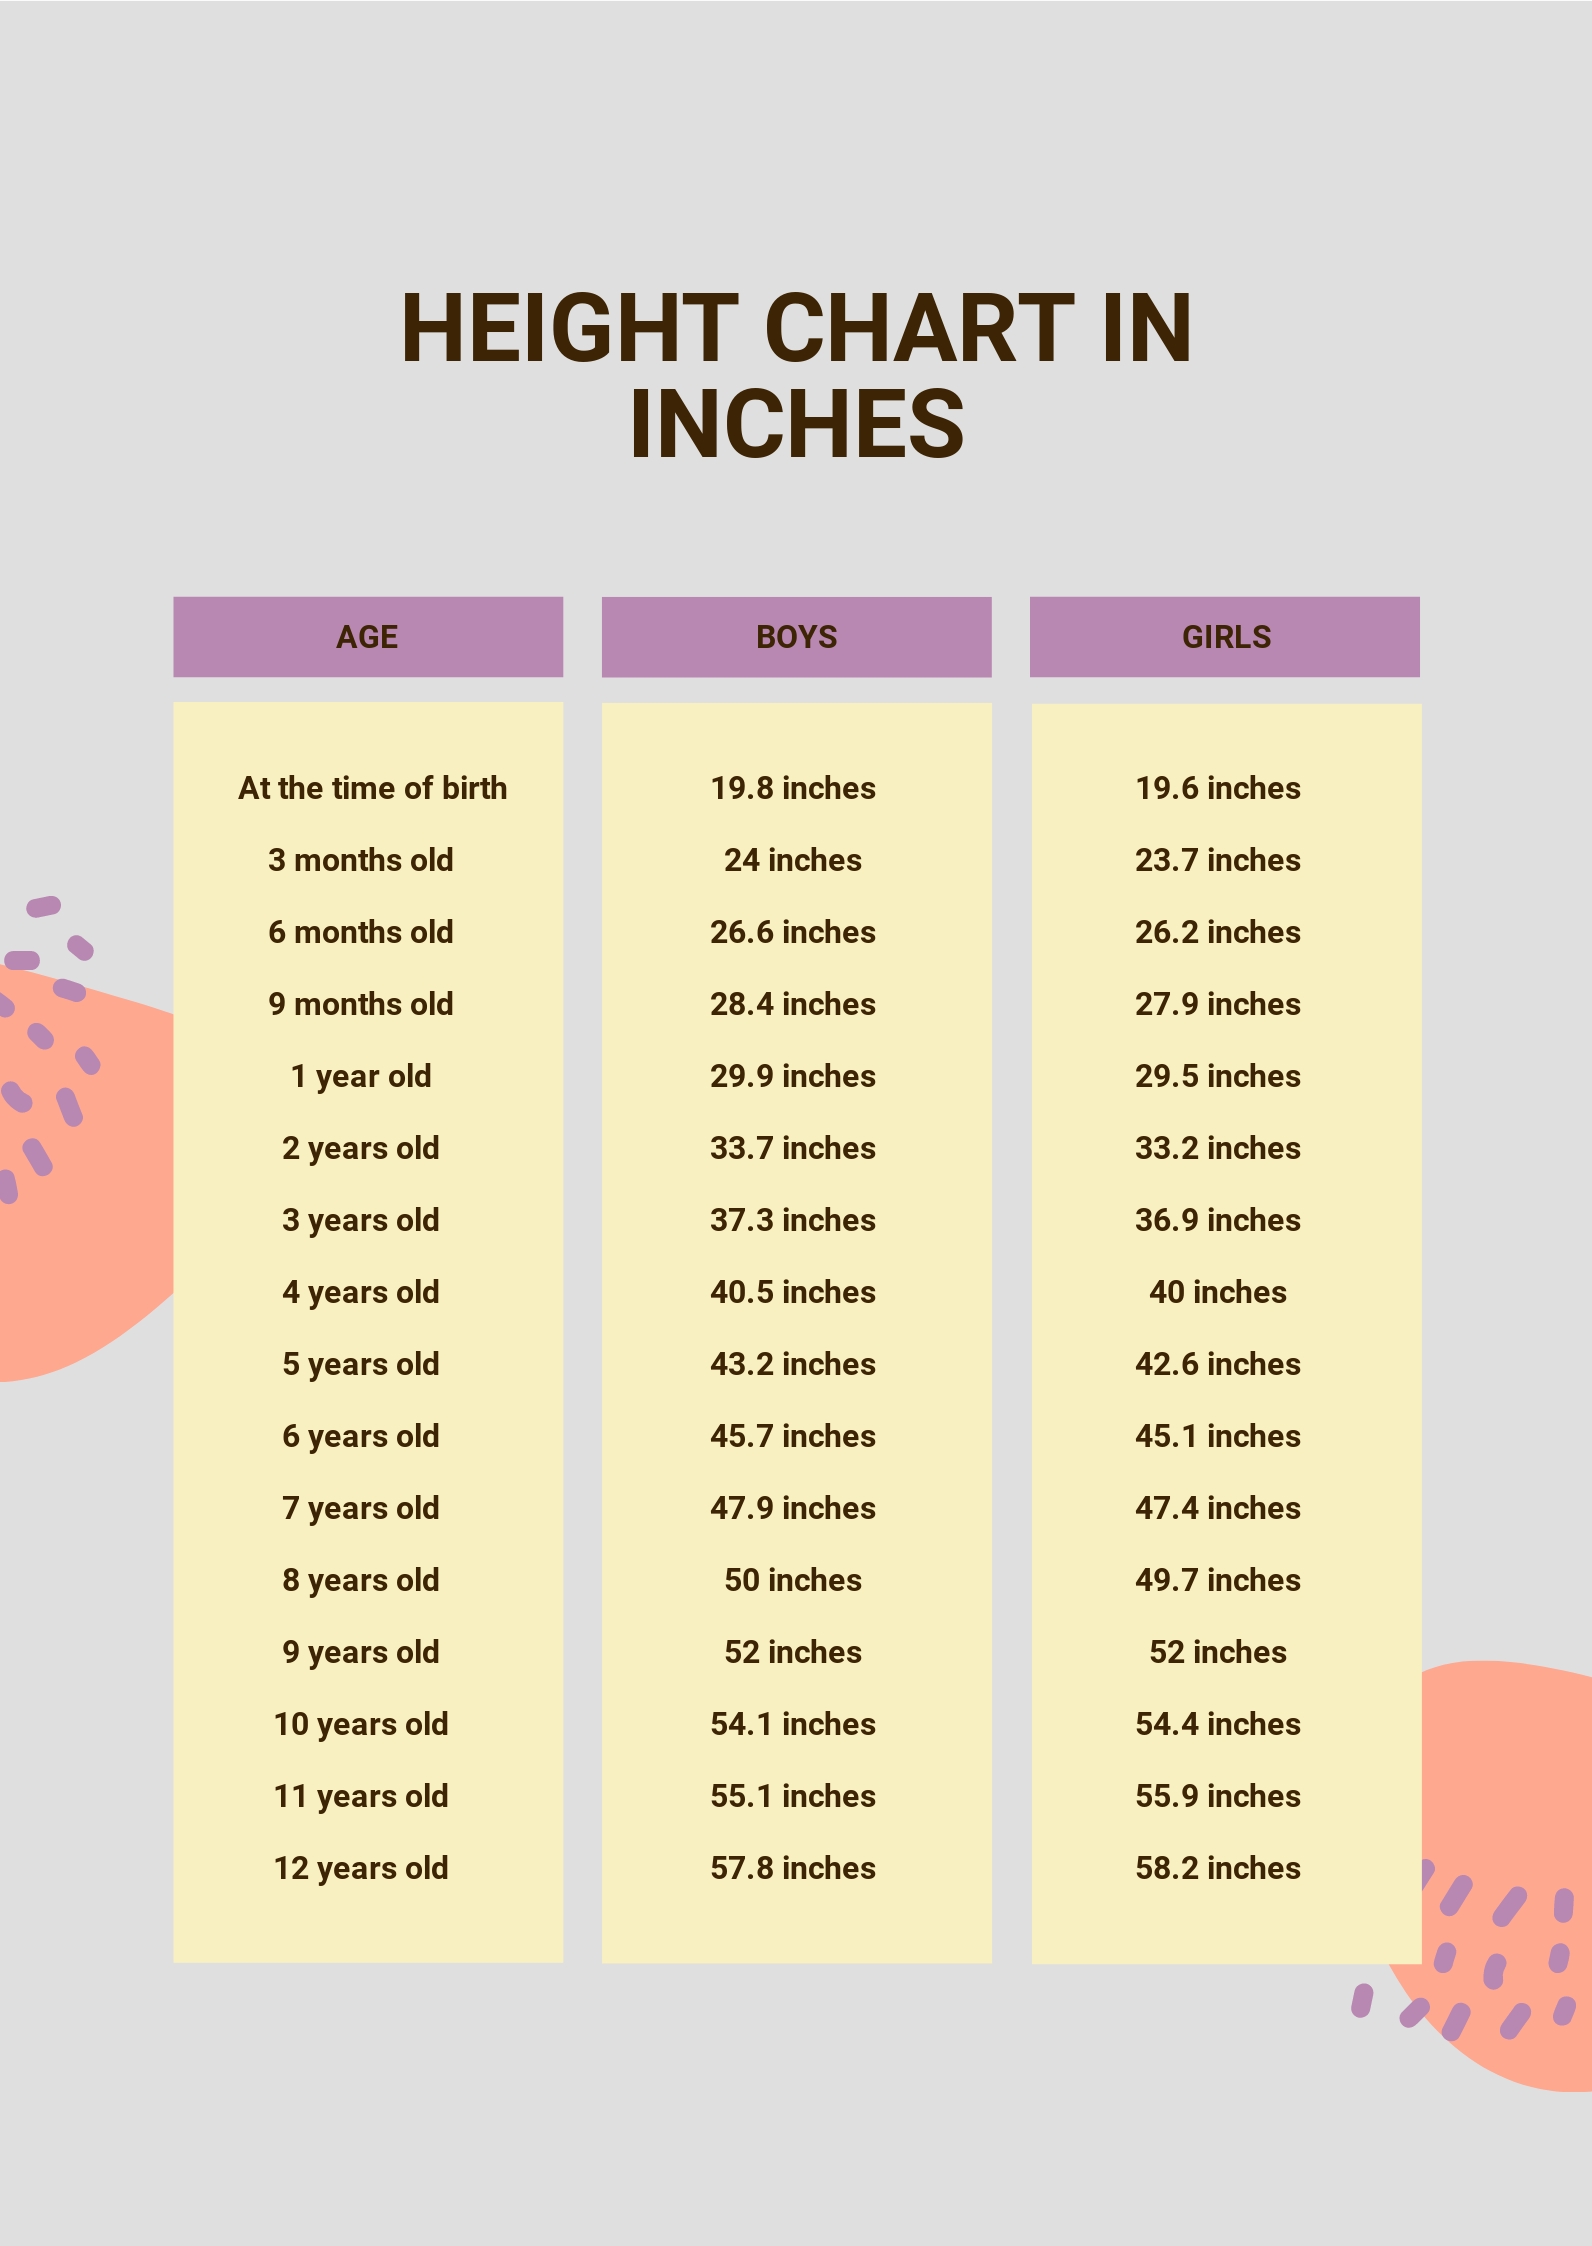
Before you get into any charts or conversions, you need a proper measuring setup. A flat, hard surface. A rigid object with a sharp, straight edge — a book works, a clipboard works better. A steel tape measure, not those floppy fiberglass ones you use for home renovation. Mark the wall where the top of the head touches the object. Stand barefoot. Don't slouch. Don't stand on your tiptoes. Look straight ahead. Measure from the floor to the mark. The numbers on a height chart mean something specific. A standard inches chart for adults typically ranges from about 54 inches (4'6") to 84 inches (7'), though pediatric charts go higher. Each increment represents one inch, and the percentile lines between them show how a given height compares to a reference population. CDC growth charts use WHO standards for children under two and CDC reference data for older kids. These aren't suggestions. They're statistical distributions based on tens of thousands of measurements taken under standardized conditions. Here's where people mess up. They look at a height in inches and try to match it to a percentile without accounting for age and sex. A 60-inch girl at age 10 and a 60-inch boy at age 12 are in completely different percentiles. The chart is useless if you're pulling the wrong reference column. Always verify you're reading the correct gender and age row. This seems obvious until you've been doing this for a while and your eyes just skip to the nearest line.
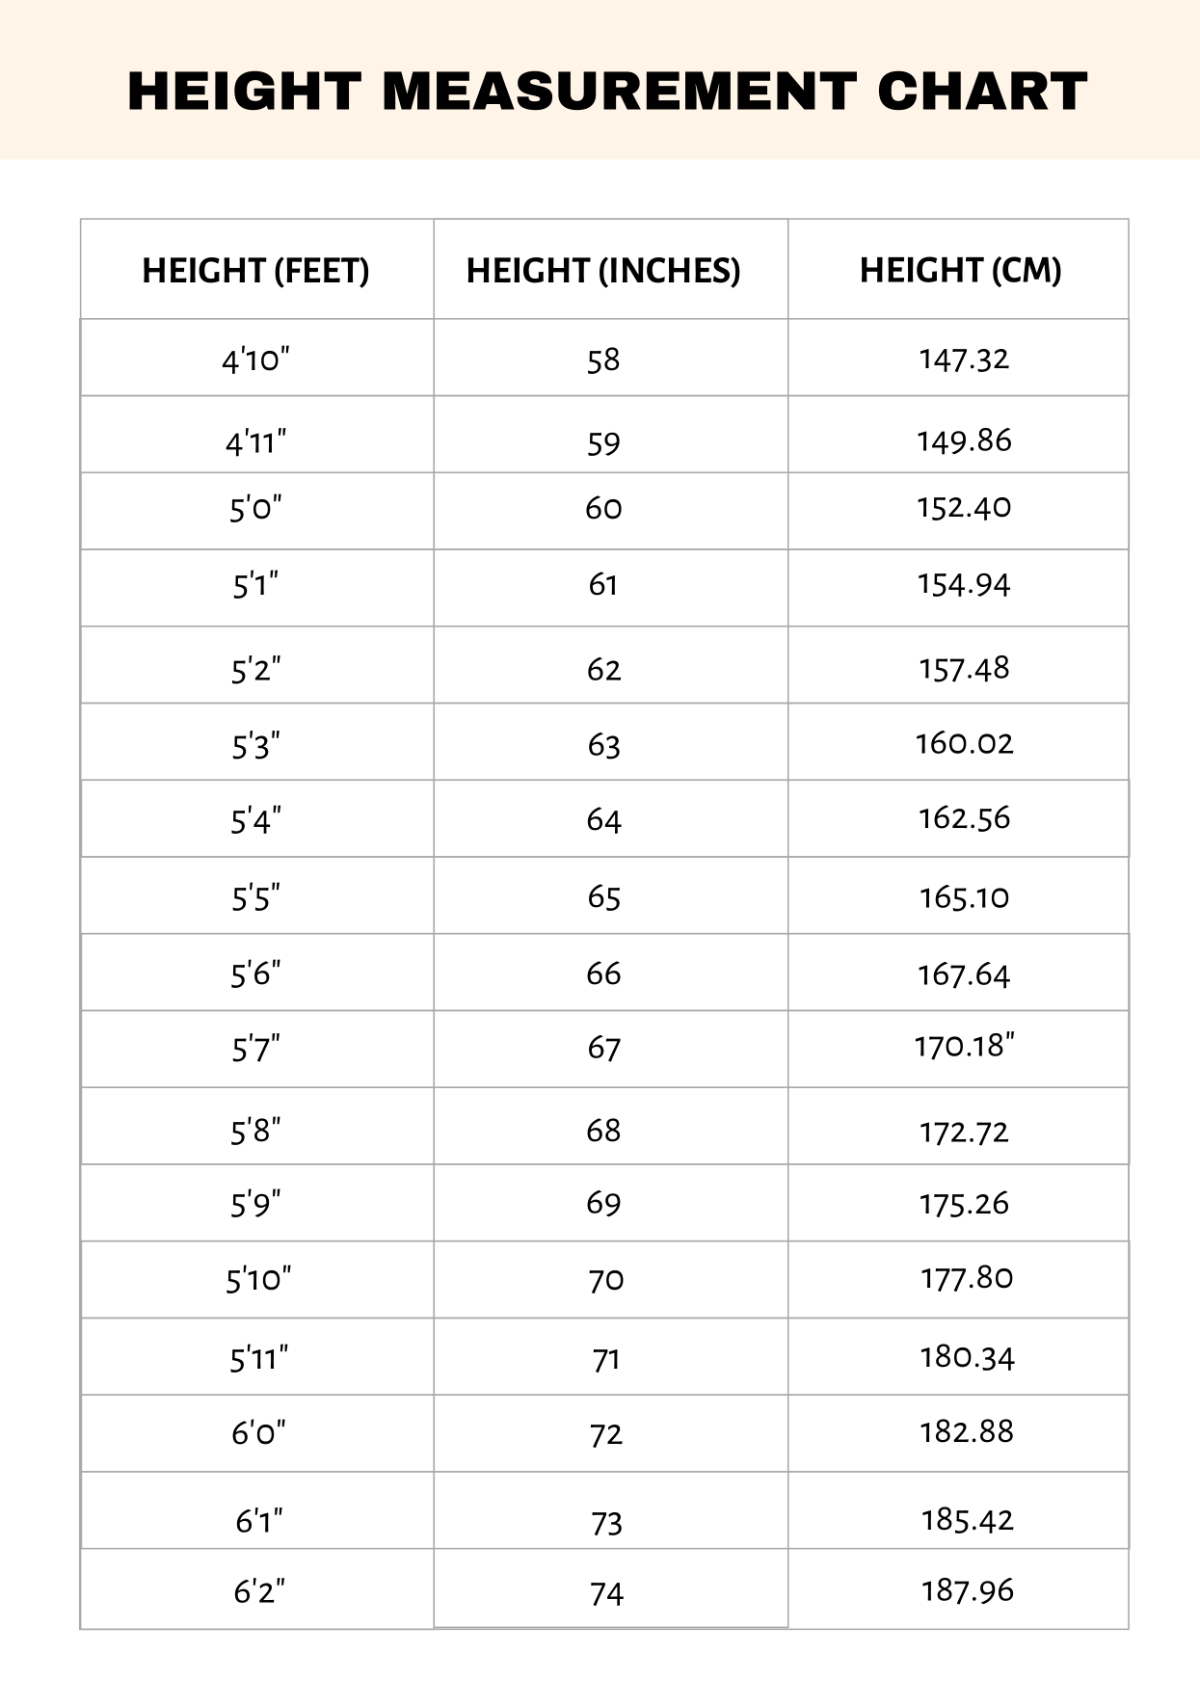
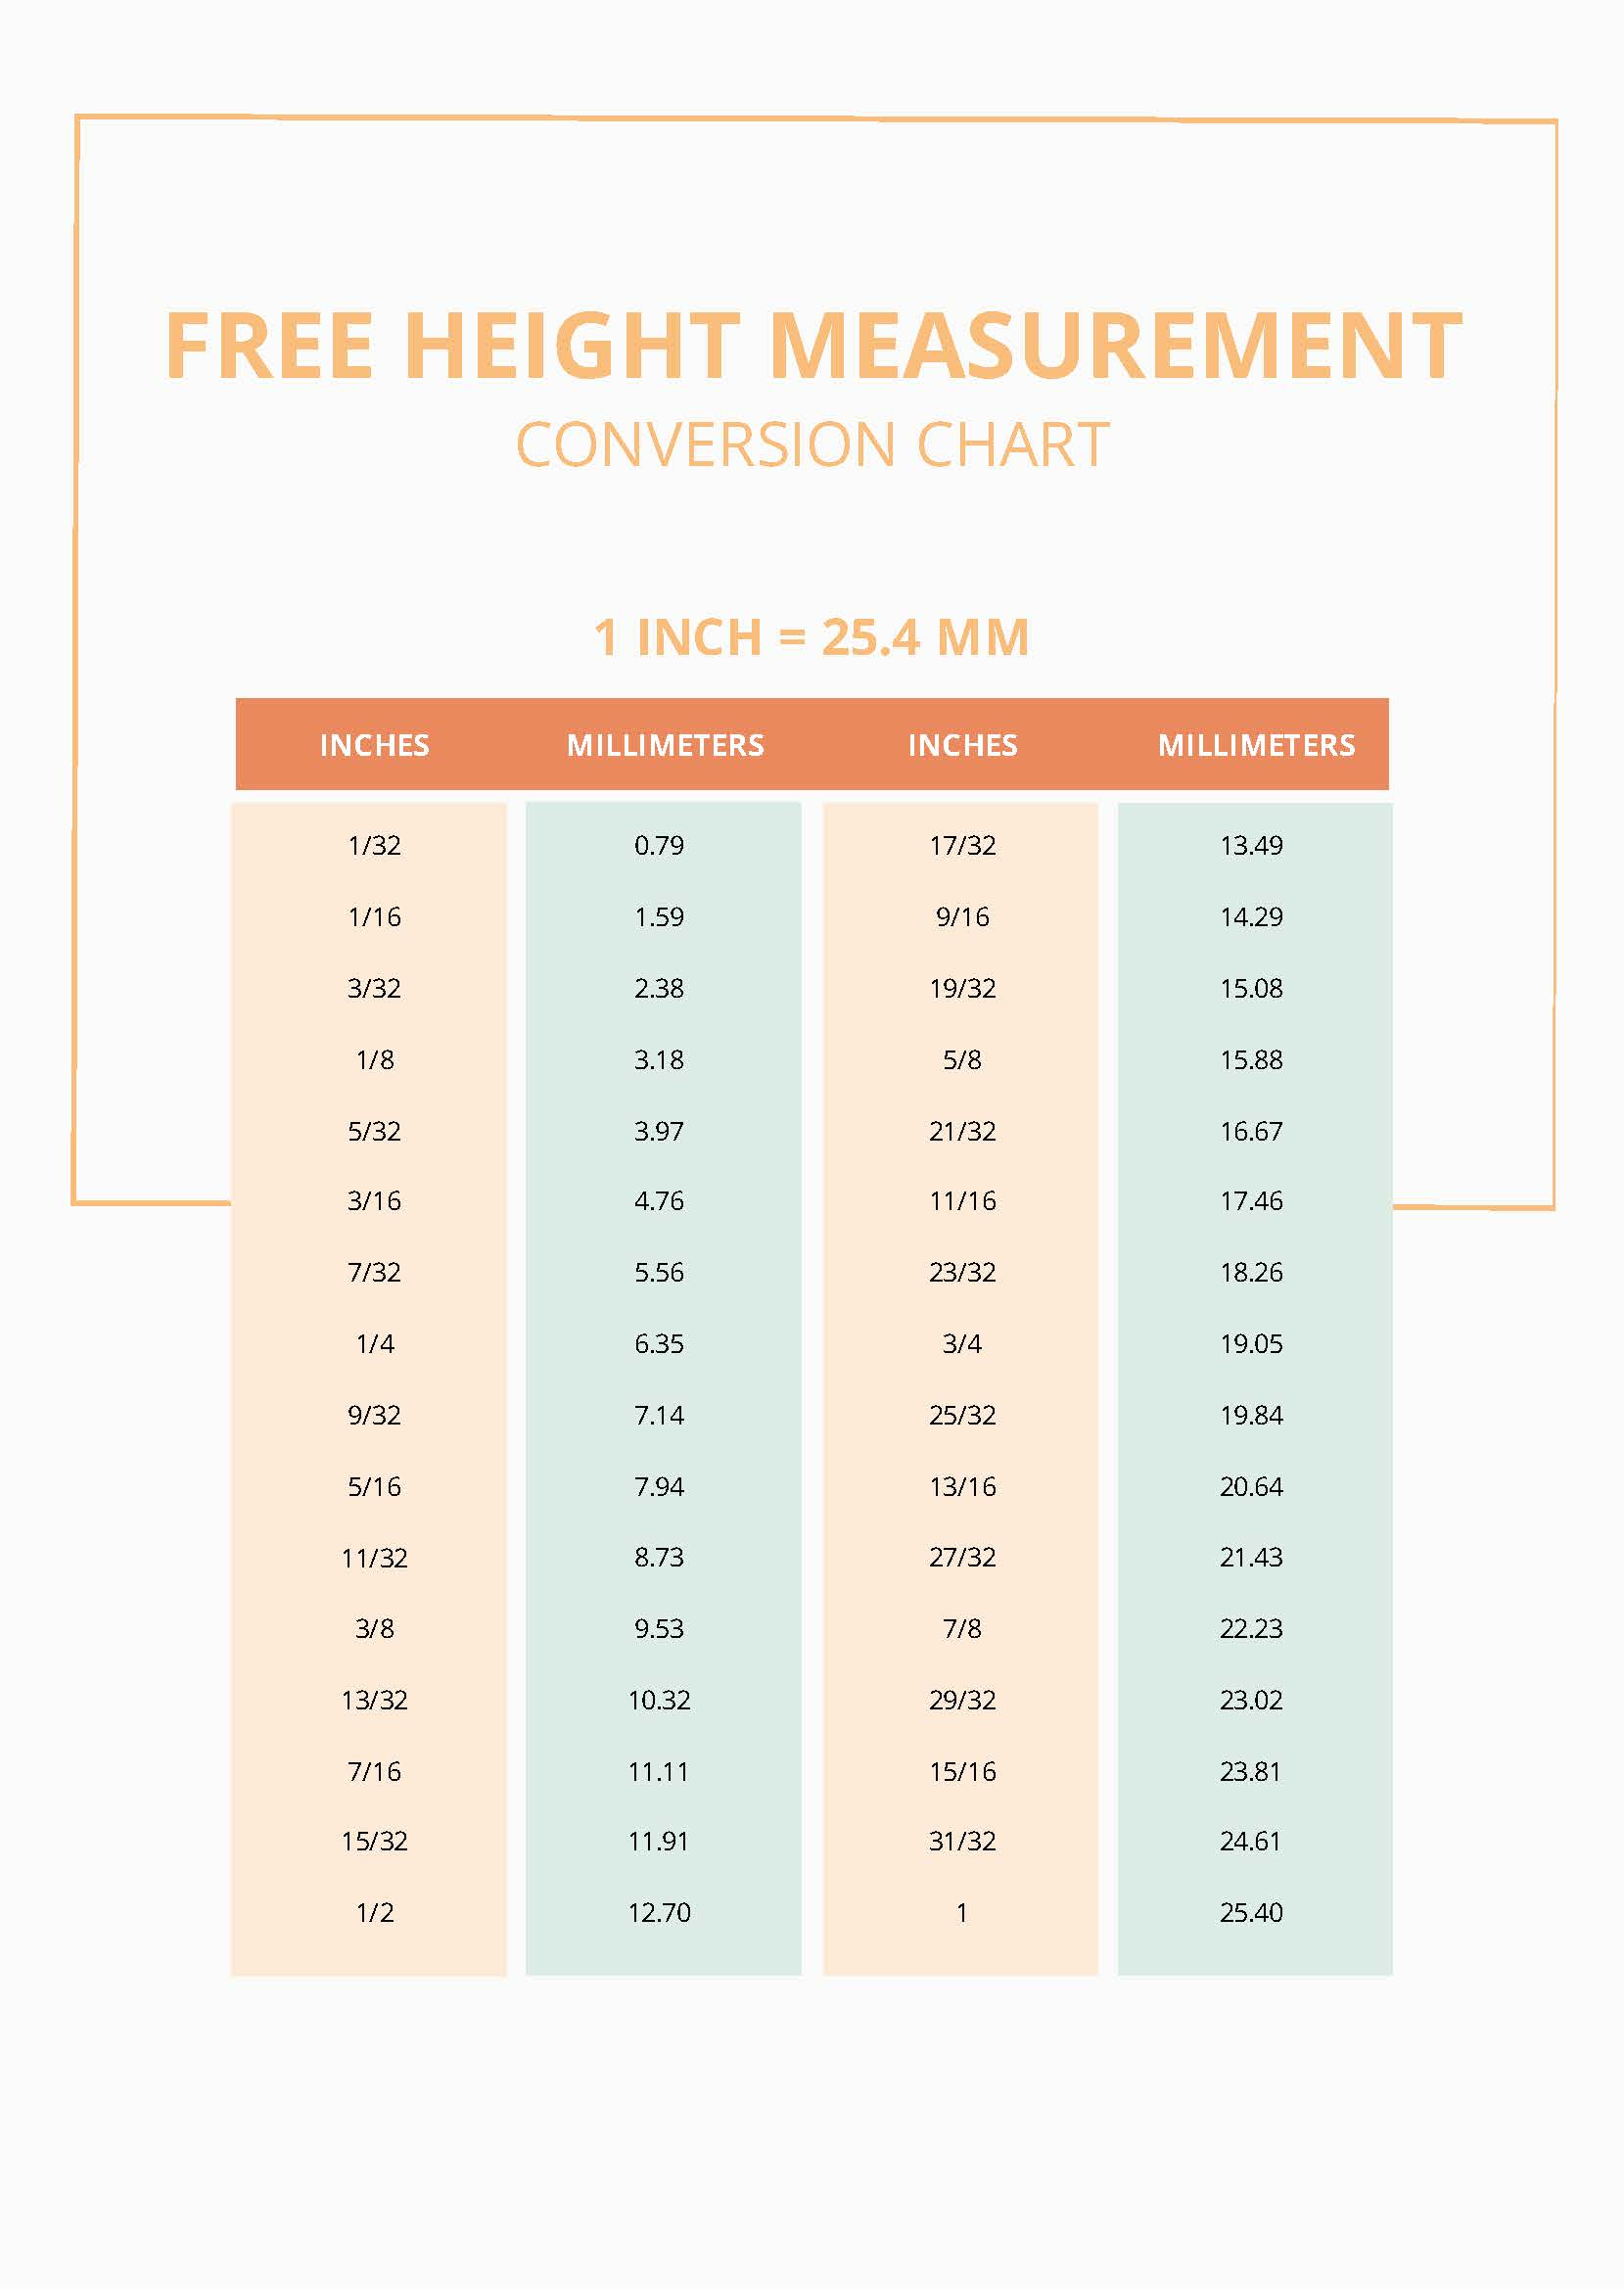
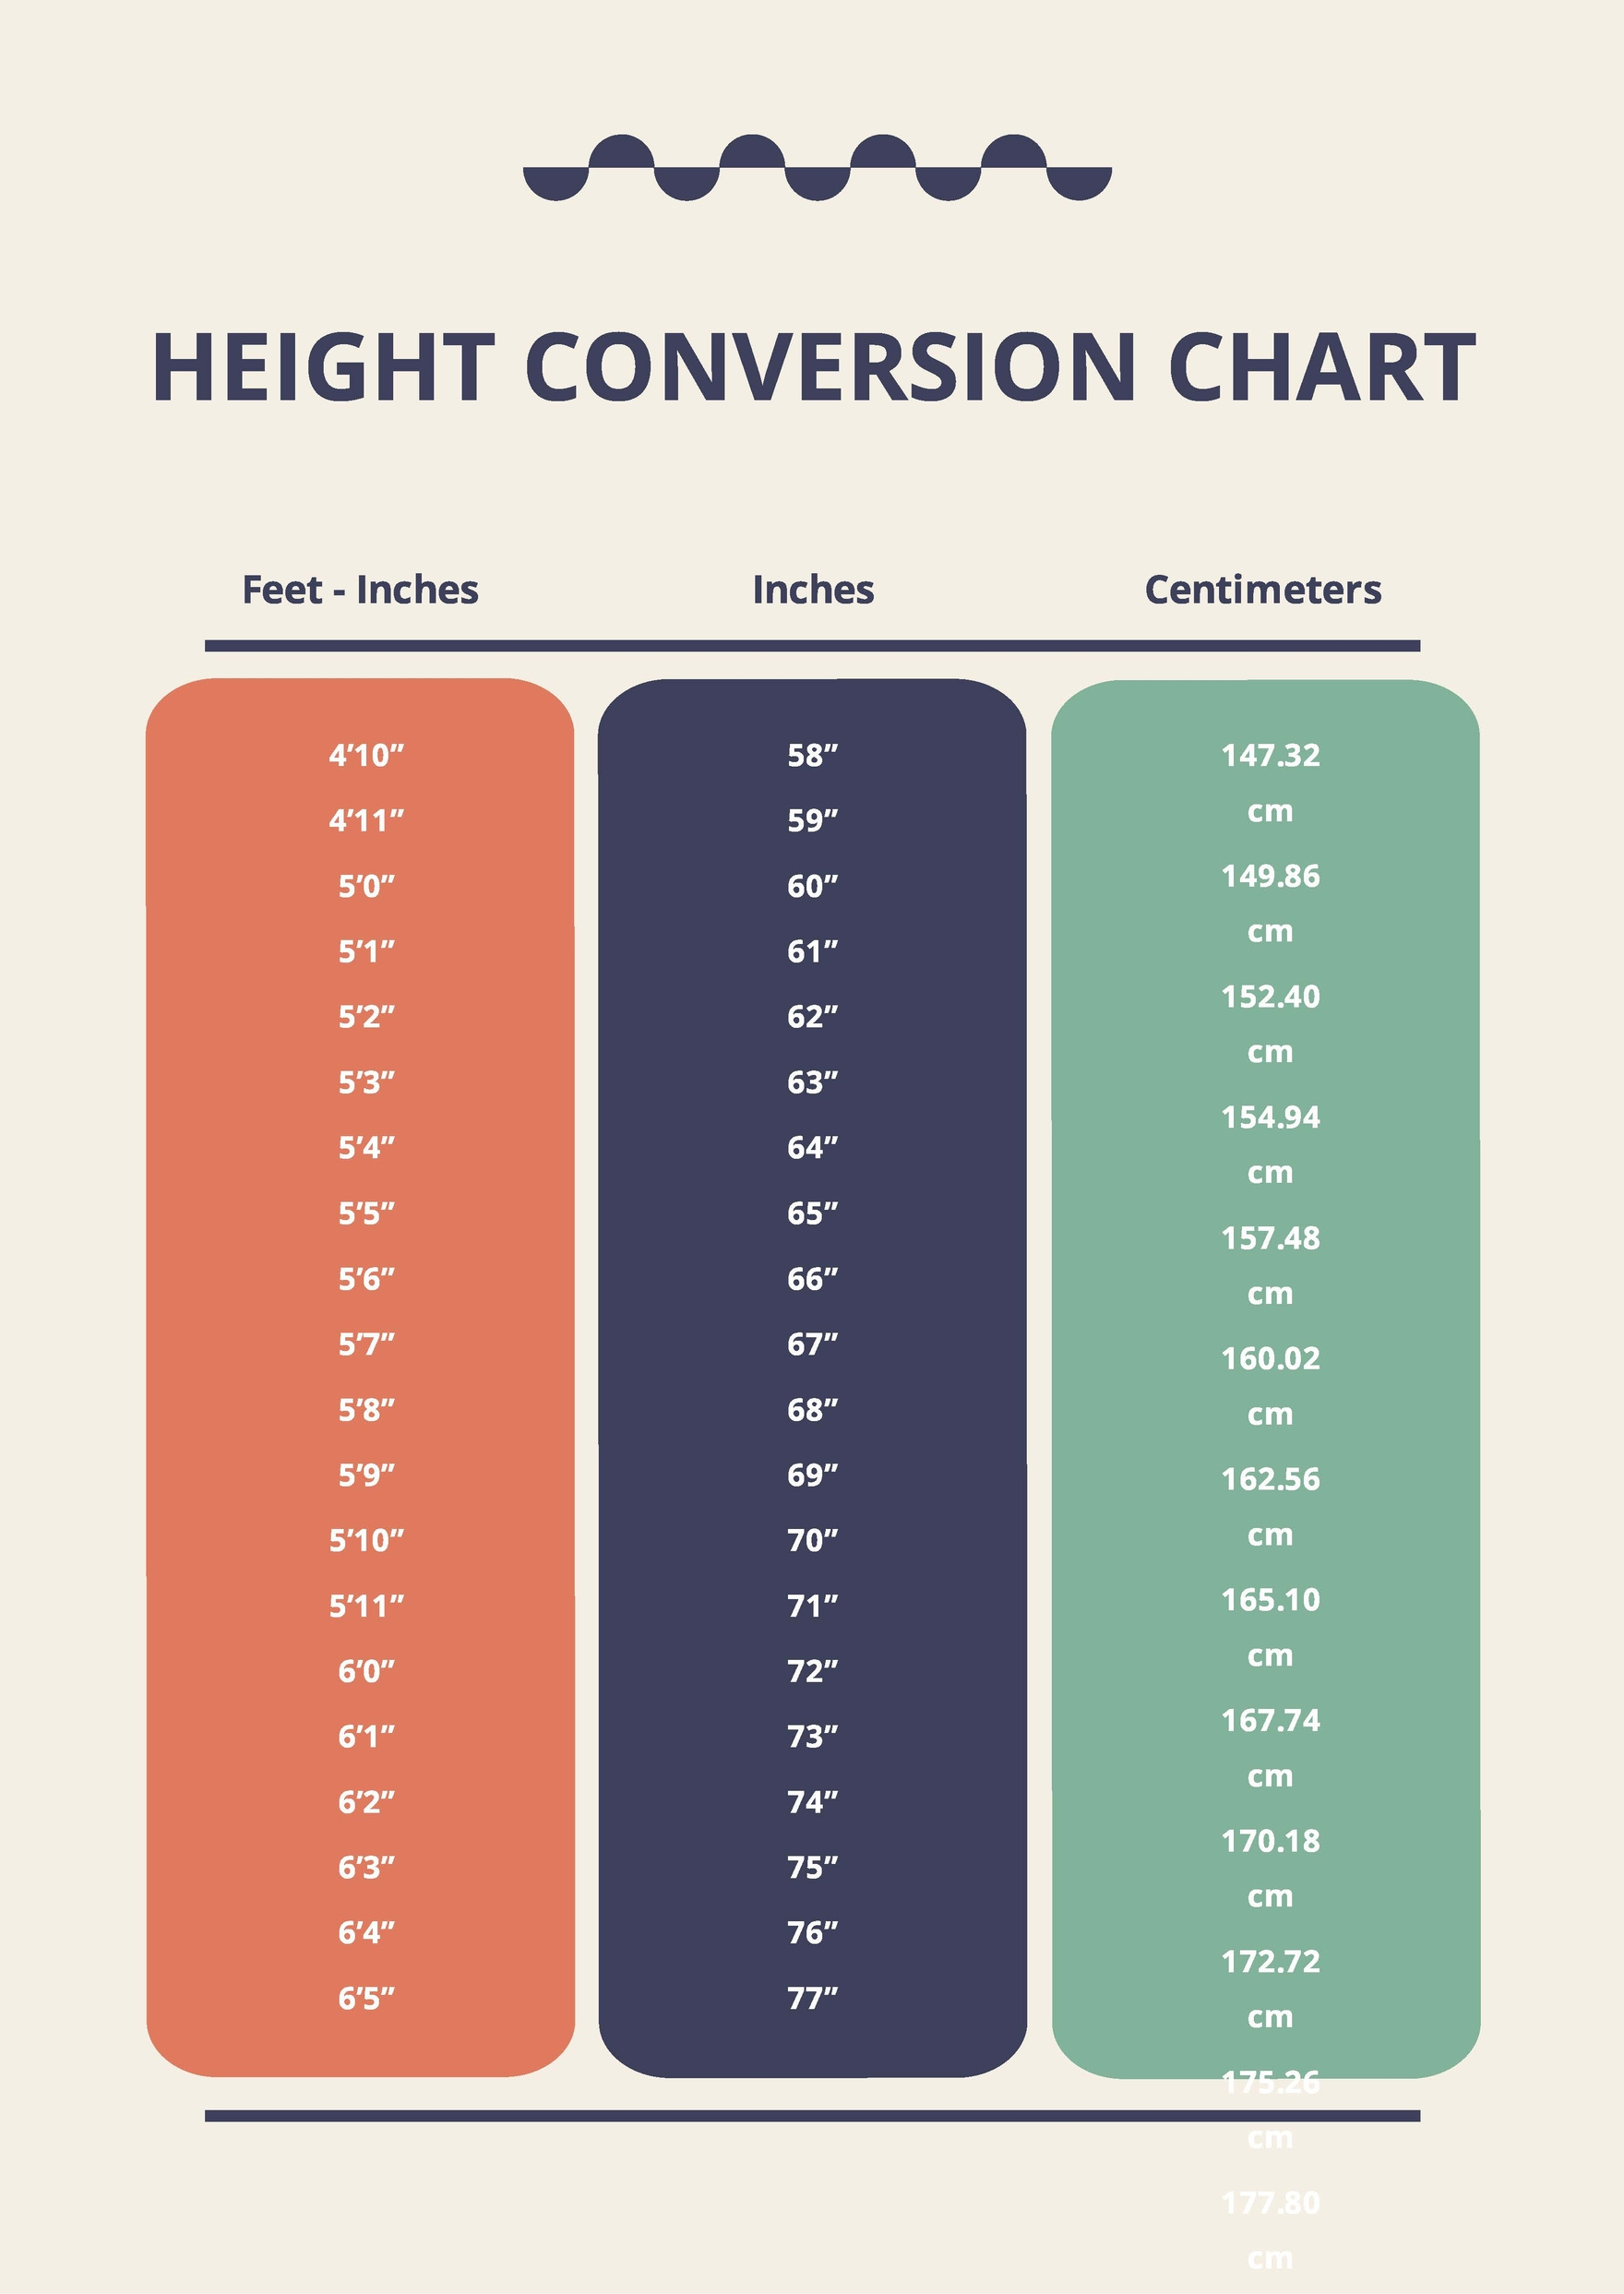
I learned the hard way that wall markers lie. When you press a book against someone's head and leave a pencil mark, the graphite smears. The line gets thick. You end up measuring to the top of the smudge or the bottom, and suddenly your measurement is inconsistent from day to day. The workaround is to use a small piece of masking tape on the wall first, make the mark on the tape, and then re-measure by holding the tape against the same point each time. It sounds trivial but it cut my measurement variance from about three-quarters of an inch down to roughly a quarter inch. Converting centimeters to inches is straightforward math but easy to botch under pressure. One inch equals exactly 2.54 centimeters. So if a chart lists 170 cm, divide by 2.54 to get approximately 66.93 inches. Don't round prematurely. Keep the decimal during the conversion, then round at the end. Rounding 170 cm up to 67 inches before converting versus rounding after gives you a slightly different result, and in medical contexts that tiny difference can shift a classification. Common pitfalls that nobody warns you about:
Get the Full Details

Shoes with thick soles are the most obvious culprit. Mountain boots can add an inch or more. People forget about this when they self-report height for insurance forms or job applications. Hair volume is another one. Long, hair compresses differently depending on how hard the measuring object presses down. Two measurements on the same person five minutes apart can vary because of hair compaction. Take two readings and average them. That's the standard approach used in clinical settings. Morning versus evening height difference is real. Intervertebral discs compress throughout the day under gravity. An adult can lose up to half an inch between waking up and going to bed. If you're tracking growth over weeks or months, always measure at the same time of day. Preferably in the morning, right after getting out of bed, before any significant activity. This is why pediatricians measure kids in the morning when possible. Chart accuracy has limits. Most published height charts are based on population averages from specific countries and time periods. A CDC chart reflects US children. European charts differ slightly. African pediatric standards differ again. If you're using a chart designed for one population to assess someone from a different background, the percentile assignments may not be accurate for that individual. There's no perfect universal chart. The best you can do is use the chart that most closely matches the population you're working with and acknowledge the uncertainty.
Self-measurement is inherently less reliable than professional measurement. Even with good technique, the person doing the marking and the person being measured are usually the same person, which introduces leverage and angle errors. If you need precision — and most people don't, but some do — get measured by someone else with a proper stadiometer. A wall-mounted one, not a freestanding portable unit. Portable stadiometers drift over time. The base plate shifts. The headpiece loosens. I once had a portable unit that gave readings varying by up to a full inch depending on which technician was using it and how hard they seated the headpiece. The bottom line is that height measurement is simple in theory and annoying in practice. Get a rigid tape measure. Use masking tape for your marks. Measure barefoot at the same time of day. Read the correct percentile column. Account for the difference between centimeter and inch systems without rounding early. And don't trust your own measurements more than you should. Most people's self-reported height is about half an inch taller than their actual height. The psychological bias toward reporting a more favorable number is well-documented and almost universal.