Breaking Down The Bones That Make Your Hand Work
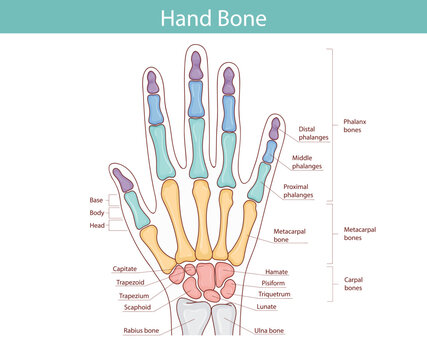
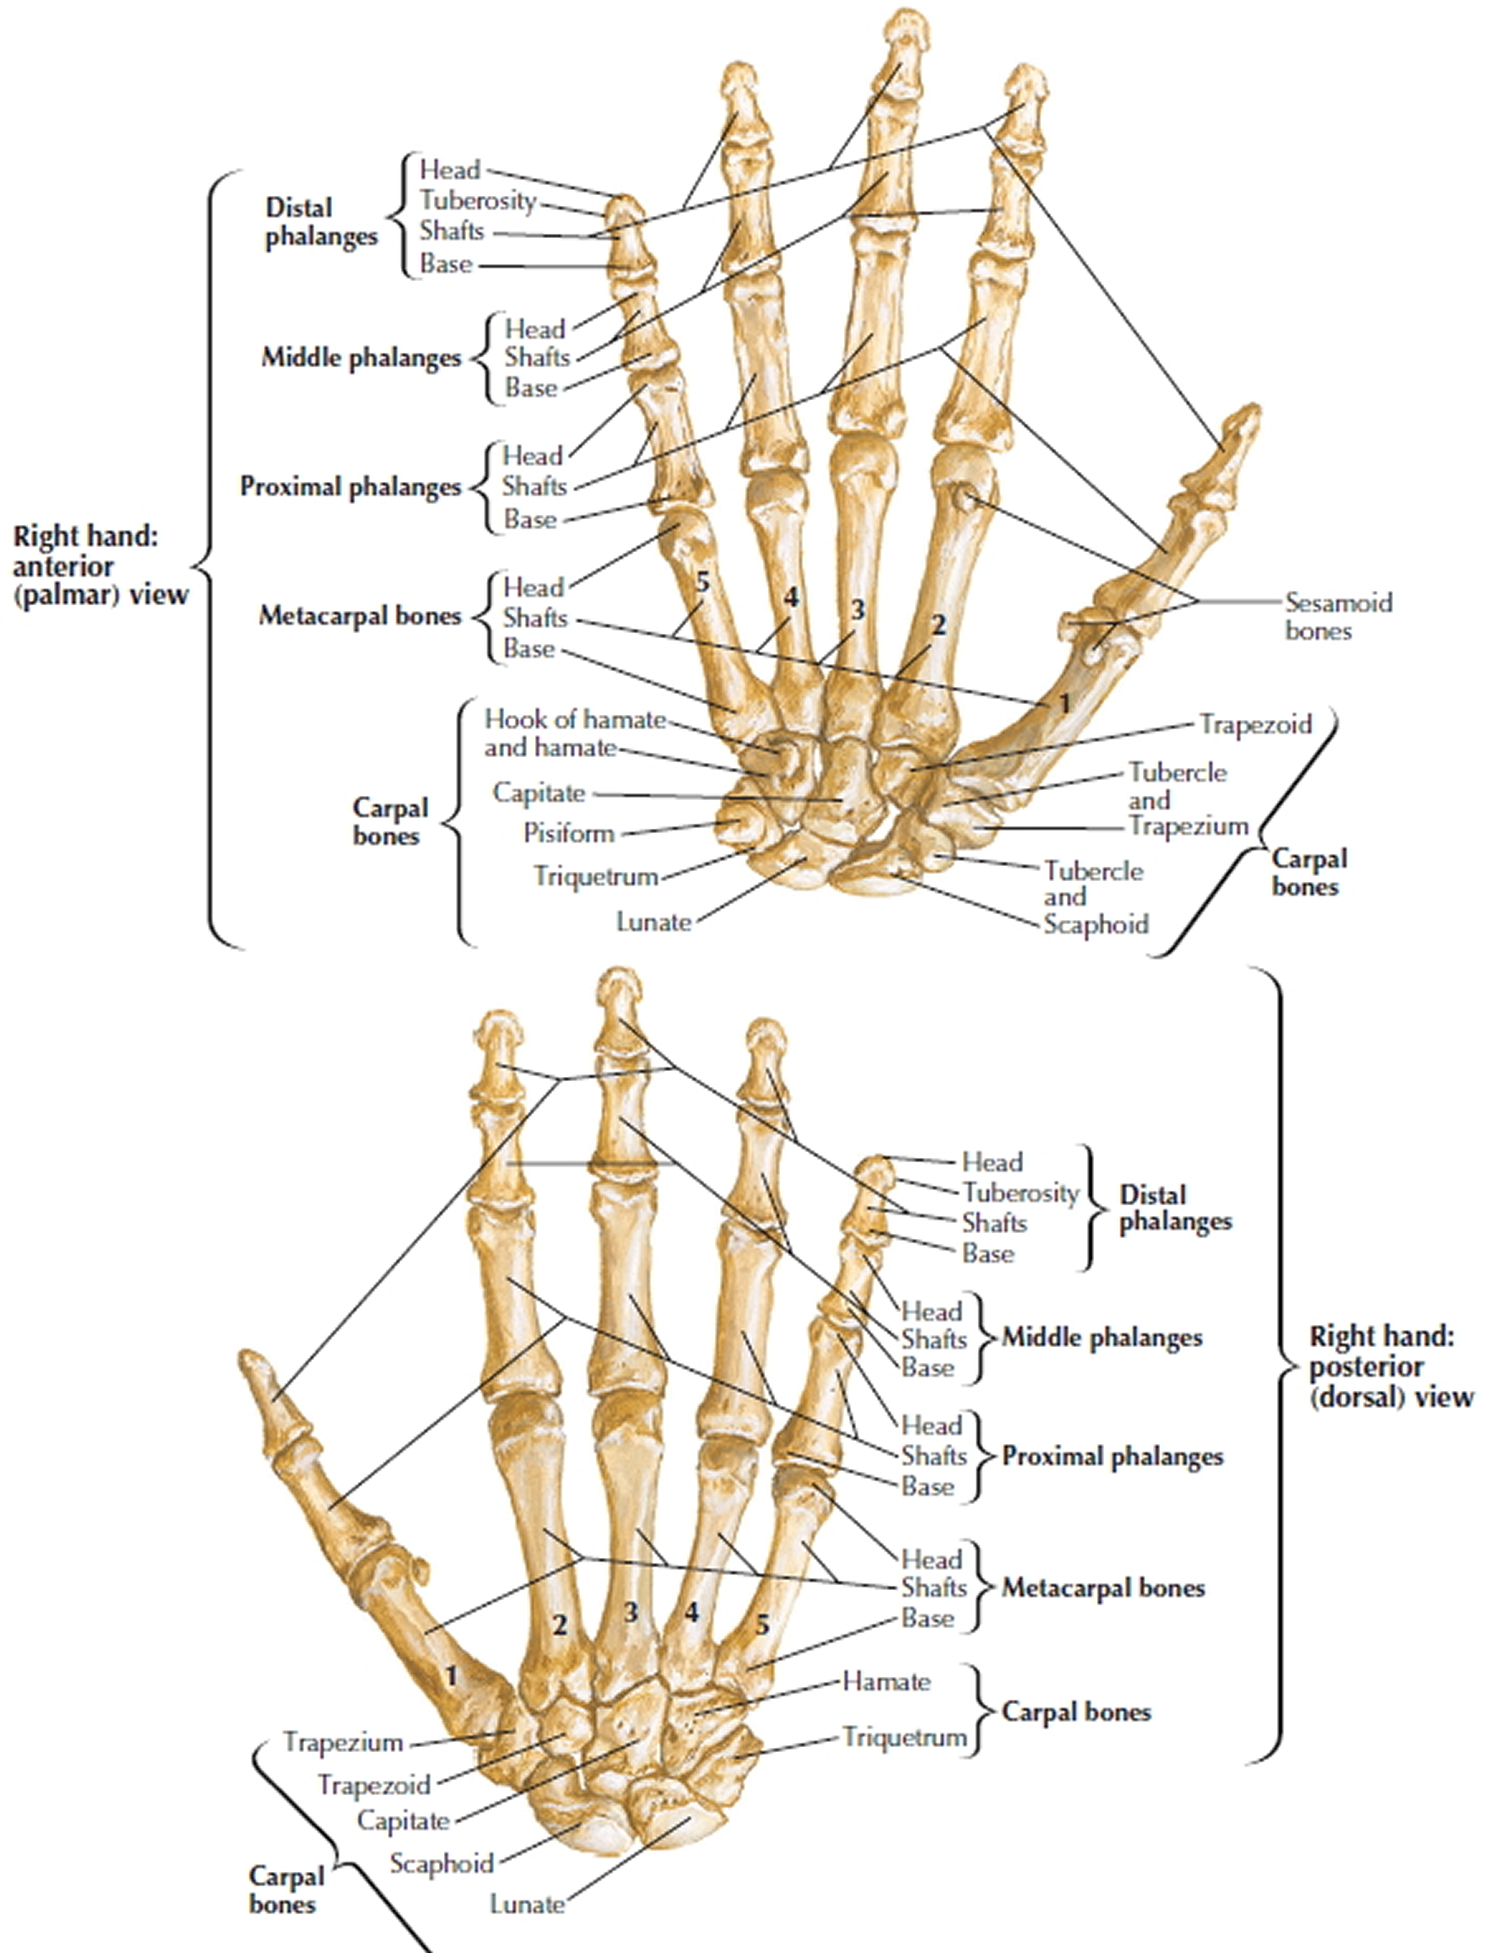
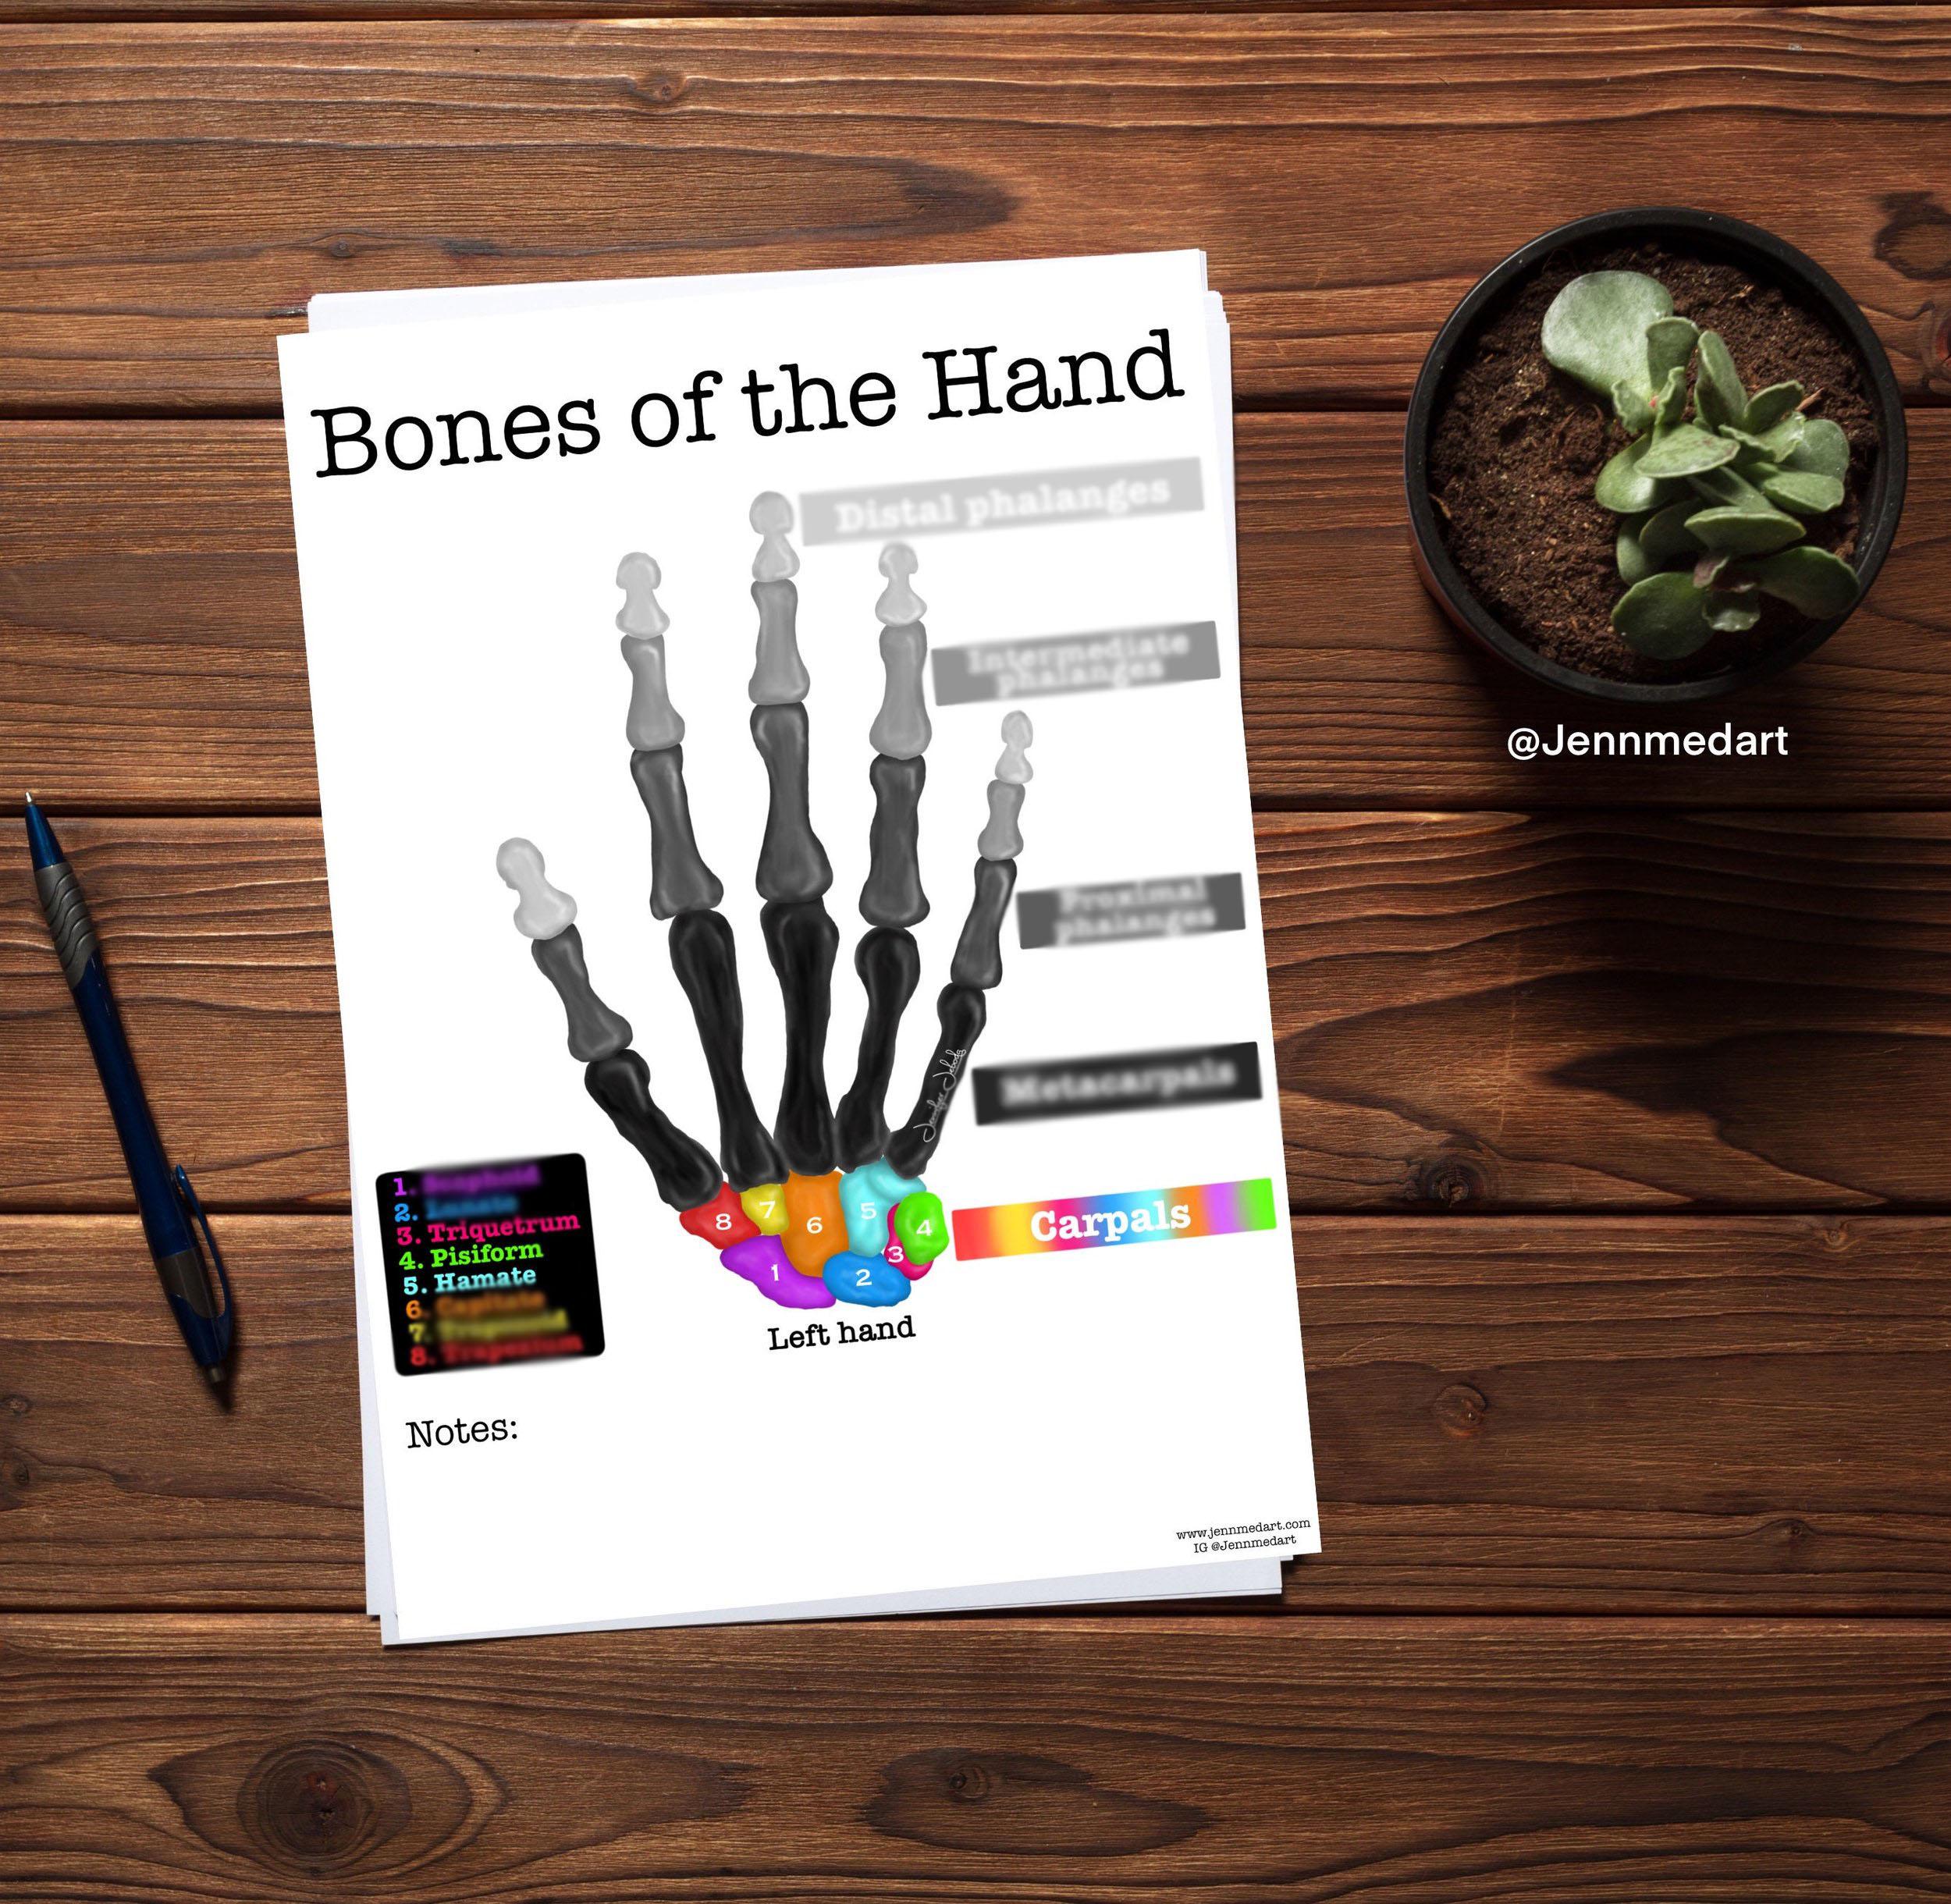
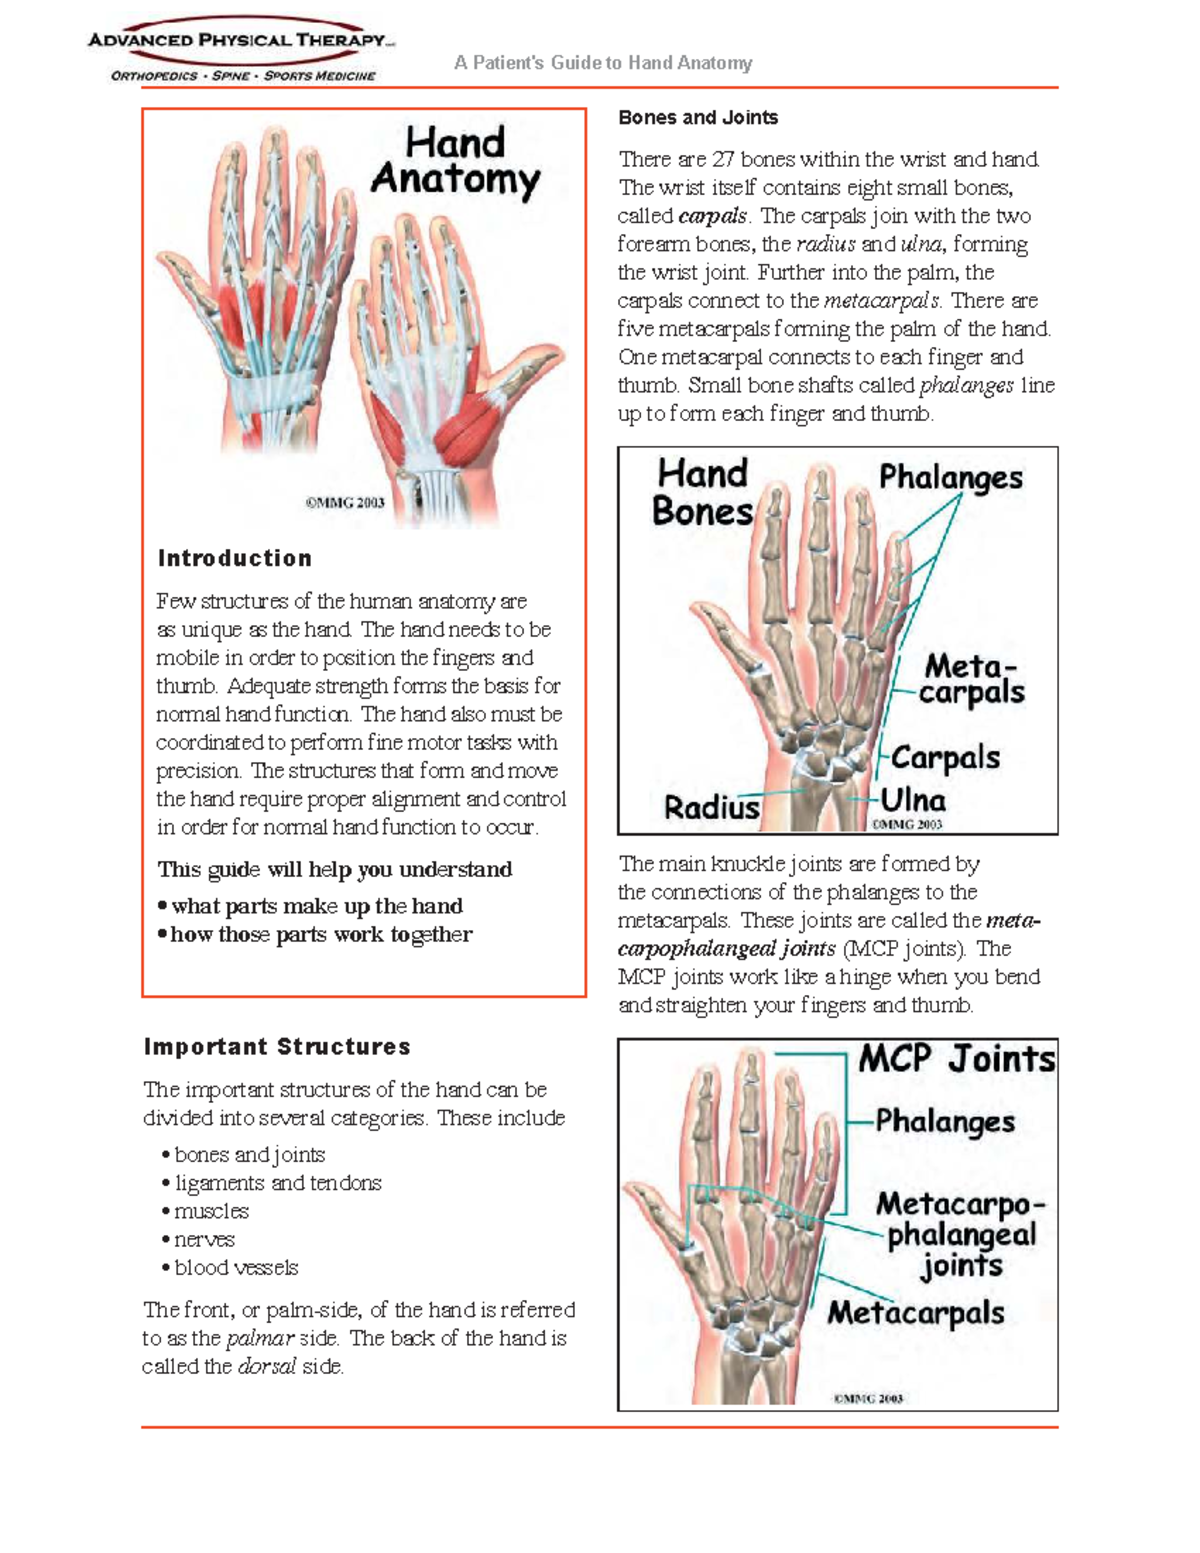
The human hand contains 27 individual bones, arranged in three groups. Most people only recognize fingers. They do not realize the wrist alone has eight carpal bones packed into two rows, each with names that look like medical Latin. That is because it is medical Latin. The scaphoid, lunate, triquetrum, pisiform, trapezium, trapezoid, capitate, and hamate. Those are the proximal row, reading from thumb side to pinky side, followed by the distal row with the same names in the same order. I still have to double-check the spelling of hamate versus hamatum on cold mornings.The metacarpals make up the palm. Five of them, numbered one through five from the thumb outward. The first metacarpal is the odd one out. It has a saddle joint at its base, which gives the thumb its opposition. The other four attach to the carpal row with slightly different angles, which is why your hand can pronate and supinate while maintaining grip strength. A fractured scaphoid will sit out for weeks before showing on an X-ray. I learned this the hard way after a snowboard impact and a negative initial scan that missed the stress fracture entirely. One thing most guides miss is the sesamoid bones. Two small pea-shaped bones sit at the base of the thumb under the first metacarpophalangeal joint. They are embedded in the flexor pollicis brevis tendon. They protect the tendon during heavy pinch grip. I once worked with a pianist who had ossification of those sesamoids after years of aggressive Chopin etudes. The pain was localized exactly under the thumb pad, and MRI only picked it up after the third scan. A CT scan confirmed the calcification. You have to know they exist before you think to look for them. The interphalangeal joints are hinge joints with a single plane of motion. The metacarpophalangeal joints allow flexion, extension, abduction, adduction, and circumduction. That is five degrees of freedom per joint, compared to two for the IP joints. The ligamentous architecture changes between those joints. The collateral ligaments of the MCP joints are loose in extension and tight in flexion. The opposite is true for the IP joints. This is why a jammed finger feels completely different depending on whether the force came at the tip or the middle knuckle. I have seen emergency room misdiagnoses from exactly this confusion.
Blood supply to the hand comes primarily from the radial and ulnar arteries, forming the superficial and deep palmar arches. The proximal carpal row gets blood from dorsal and volar branches. The scaphoid receives its blood supply retrograde, entering at the distal pole and flowing backward. A fracture through the waist can cut off blood to the proximal fragment, leading to avascular necrosis. This is not rare. It happens in approximately 15 percent of scaphoid waist fractures, and it is almost entirely preventable if the fracture is immobilized early enough. Early is the key word. Delayed casting is what causes the worst outcomes. Nerve supply follows the same pattern. The median nerve controls sensation in the lateral three and a half digits and powers most of the thenar muscles. The ulnar nerve covers the medial one and a half digits and handles the interossei plus the hypothenar group. The radial nerve provides dorsal sensation but does not control intrinsic hand muscles. When someone loses fine motor control in the fingers, the first question is whether the nerve damage is proximal or at the wrist. A wrist laceration at the level of the flexor retinaculum will spare the forearm muscles but wreck intrinsic function. That is the hand claw deformity you see in untreated cases. Here is a practical note about labeling anatomical diagrams. Many resources flip left and right hands without warning. In anatomical position, the palms face forward. If a diagram shows a right hand with the palm facing you, it is actually showing the dorsal surface. I spent two weeks teaching from a textbook that had the carpals mirrored. A student caught it. She pointed out that the hook of the hamate was on the wrong side. The caption said "left hand" but the image was a flipped right hand. It took me six minutes to verify by holding my own hand up to the diagram. Something as basic as that is more common than you would expect.
Another edge case that people run into involves the bifid median nerve. About 7 percent of the population has a median nerve that splits around the flexor pollicis longus tendon before entering the carpal tunnel. Standard carpal tunnel release surgery will miss a bifid nerve if the surgeon does not identify it preoperatively. The patient comes back months later with persistent numbness. Preoperative ultrasound or MRI can catch this, but most ERs do not order that for typical carpal tunnel presentations. It is worth mentioning if you work in hand surgery or physical therapy. The incidence is high enough to matter. The proximal phalanx is the longest bone in each finger. A fracture here is common in boxing and climbing falls. The extensor mechanism runs along the dorsal surface and attaches to the middle and distal phalanges. Disruption of the central slip at the base of the proximal phalanx causes a boutonniere deformity. The proximal interphalangeal joint hyperextends while the distal joint flexes. This is a clinical diagnosis. You do not always need an X-ray to see it. Bending the PIP joint passively and watching the DIP fail to extend is enough to make the call. Casting in proper position within the first week prevents permanent contracture. After three weeks, surgical correction becomes necessary. Metacarpal shaft fractures, particularly of the fourth and fifth metacarpals, are frequently called boxer's fractures. The deformity angle matters more than the bone displacement. A metacarpal head that is rotated even 10 degrees will cause the finger to cross over its neighbor when making a fist. The aesthetic and functional result is worse than the X-ray suggests. Reduction should be checked dynamically, not just with static imaging. I have seen acceptable-looking reductions on film that were grossly malrotated when the patient tried to grip a pen. The correction is usually a simple rotation under fluoroscopy. It takes about five minutes and saves the patient from secondary surgery.
Get the Full Details
The pisiform is a sesamoid bone within the flexor carpi ulnaris tendon. It sits on the volar aspect of the triquetrum and is not part of the true carpal chain that transmits force from the forearm to the hand. It is a separate articulation. Fractures here are rare but often misidentified as osteophytes on plain films. A dedicated pisiform view is necessary for confirmation. The treatment is conservative in most cases. Rest, ice, and avoiding volar pressure for six weeks resolves the symptoms. Some athletes in cycling and weightlifting develop chronic pisiform pain from repetitive compression against the handlebars or barbell. Taping over the area with sports adhesive sometimes helps manage symptoms between rest periods. Capitate fractures are the most common carpal bone fractures after the scaphoid. The capitate is the keystone of the carpus. It articulates with three proximal carpal bones, all four distal carpal bones, and the third metacarpal. A displaced capitate fracture disrupts the entire carpal arch. Surgical fixation with screws is usually required. Non-operative treatment leads to post-traumatic arthritis in the majority of cases within five years. The prognosis depends on how much articular surface was involved at the time of injury. Even a clean fracture with perfect reduction carries a significant arthritis risk because the cartilage was damaged at the moment of impact. Understanding dexterity requires connecting bone structure to tendon and ligament function. The lumbricals and interossei originate from the flexor digitorum profundus tendons and insert into the extensor hood. This arrangement allows simultaneous flexion at the MCP joints and extension at the IP joints. When those small muscles weaken from disuse or nerve damage, the hand loses fine pinch and precision grip. A stroke patient recovering hand function will work on regaining independent finger movement because the default pattern is gripping with all fingers together. Isolating individual finger motion requires retraining the neuromuscular pathways, not just strengthening the muscles.
Osteoarthritis of the thumb base, specifically at the trapezium and first metacarpal joint, is extremely common in people over 50. It is not a wear-and-tear problem in the traditional sense. It is a ligamentous laxity issue. The volar beak ligament destabilizes, the metacarpal subluxates, and the joint surfaces grind. Early intervention with splinting and anti-inflammatory measures can delay surgery. Once the joint space is gone on imaging, no amount of therapy reverses it. Thumb CMC joint replacement or ligament reconstruction with tendon graft are the standard surgical options. Recovery takes approximately 12 weeks for full functional use. Some patients return to heavy labor, but the strength is never quite back to baseline. If you are building an educational resource or a reference chart, label each bone clearly with its Latin name and its common English equivalent where one exists. The scaphoid is the boat-shaped bone. The lunate is the moon-shaped one. The triquetrum is the three-cornered bone. The pisiform is the pea-shaped one. The trapezium and trapezoid are distinguished by their articular surfaces, not their names. The capitate is the largest carpal bone with the biggest head. The hamate has the distinctive hook that you can palpate on the volar wrist. Those descriptions help students who are struggling with the Latin terminology. I always include both on any reference sheet I produce. A common misconception is that the wrist has only two degrees of freedom. Flexion and extension are the obvious ones. The wrist also has radial deviation and ulnar deviation, plus a small amount of axial rotation when the hand is pronated and supinated with the wrist extended. That gives roughly four to five degrees of freedom at the radiocarpal and intercarpal joints combined. The fingers add more, especially the thumb with its six degrees of freedom at the trapeziometacarpal joint. The total dexterity of the human hand comes from this combination, not from any single bone or joint working alone.