Working with Electronic Health Records datasets
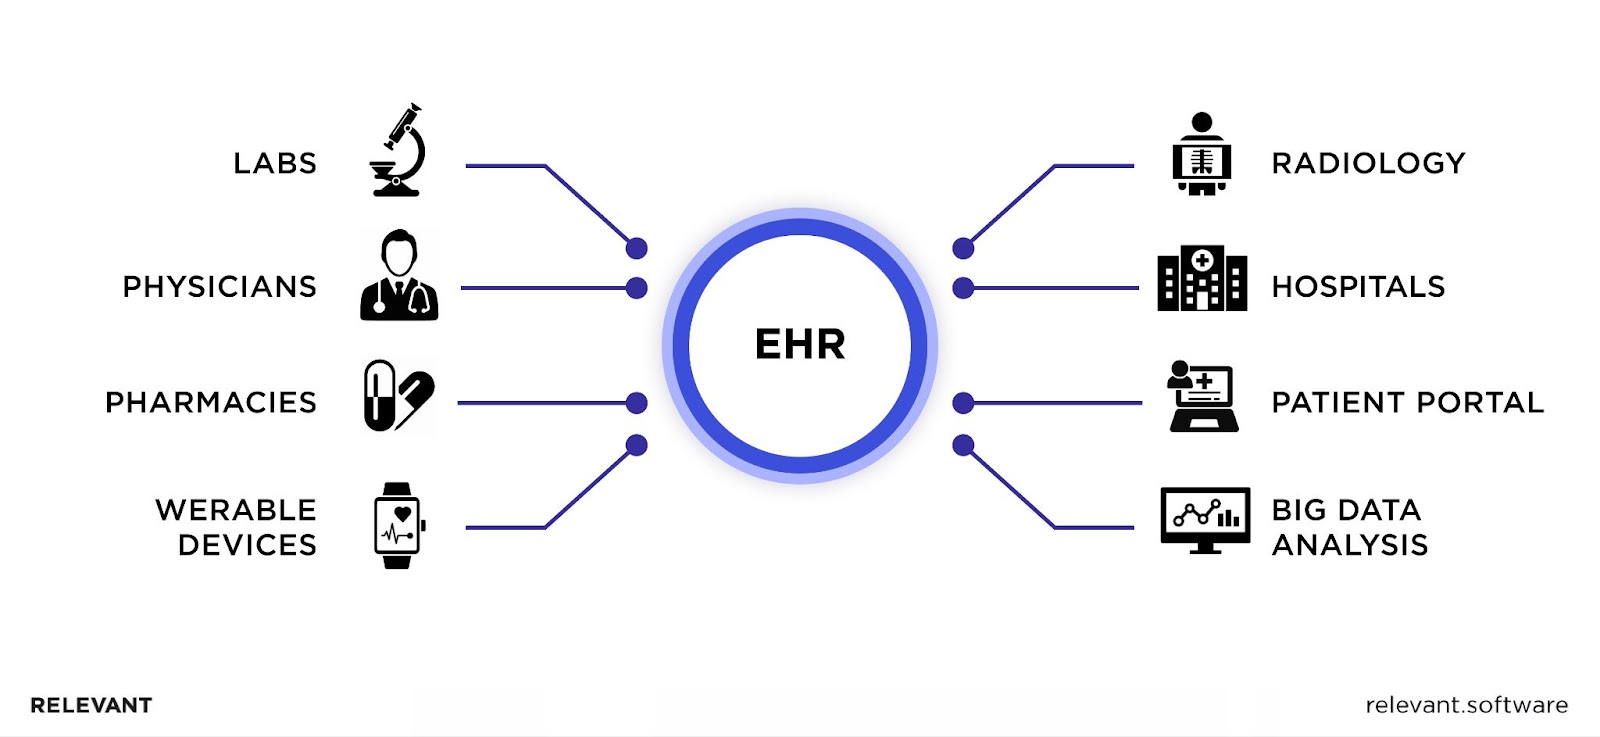
You open a raw EHR dump and immediately notice something is wrong. Patient records are interleaved, timestamps jump backward and forward, and the same person appears under three different IDs. This is not a bug in your code. This is just what clinical data looks like before anyone touches it. EHR datasets contain patient-level clinical information pulled from electronic health record systems used by hospitals and clinics. They typically include demographics, diagnostic codes, medication orders, lab results, vitals, and procedure logs. The structure depends entirely on the source system. Some datasets arrive as clean relational tables. Most do not. I work with these regularly, and the first thing I do is map the schema. Not the documentation. The actual data. Documentation is usually a week out of date. I wrote a quick script that scans every column for null distribution, distinct value counts, and date ranges. Takes about ten minutes on a standard dataset. This reveals more than any schema diagram ever will.
The two most common dataset formats you will encounter are MIMIC-IV and eICU-CRD. MIMIC-IV comes from Beth Israel Deaconess Medical Center. It contains over 350,000 admissions. eICU-CRD is a multi-hospital dataset with roughly 60,000 ICU stays. Both require CITI certification and a data use agreement before you can access them. The process takes between two and four weeks. Plan around that timeline if you have a deadline. Here is a practical example of the first pipeline I build for any new EHR dataset. I load all tables into DuckDB. Not pandas. DuckDB handles the nested JSON columns in medication and lab result tables without forcing me to write custom parsers. I run a quick query to identify primary_key versus encounter_id relationships across tables. Then I write out a cleaned Parquet file with a consistent row-per-event structure. This step usually cuts downstream processing time from hours to minutes. One thing beginners consistently get wrong is the treatment of time. EHR data is event-driven, not interval-driven. A lab result exists at a point in time. A medication order spans a period. If you aggregate by calendar day without understanding the event boundaries, your models will learn artifacts instead of signals. I learned this the hard way on a sepsis prediction project. The initial model showed 0.94 AUC. The validation set dropped to 0.61. The issue was temporal leakage. Lab values from the future were being used to predict outcomes that happened before those labs were ordered. Moving to a strict event-window approach fixed it. AUC went to 0.78 on validation, which is realistic for this type of data.
Another counter-intuitive point about EHR datasets that nobody mentions often enough. Missing values are not random. They carry information. A missing lactate level often means the patient did not appear critically ill. A missing medication record might mean the order was placed but not yet administered, or it might mean the pharmacy rejected it. When I impute, I usually create a missingness indicator flag alongside the imputed value. This single addition improved model calibration in multiple projects without changing the imputation method itself. Download locations are straightforward. MIMIC-IV is on PhysioNet. eICU-CRD is also on PhysioNet. You create an account, complete the ethics training, sign the data use agreement, and wait for approval. There is no way to skip this. Anyone offering pre-downloaded copies is distributing data they have no right to share. The dataset files themselves are large. MIMIC-IV decompressed is roughly 300 gigabytes. You need adequate storage before you start. There are honest limitations to working with these datasets. The data is observational. You cannot establish causality from it without specialized methods. Provider-level confounding is severe and rarely addressed in published work. Coding drift across institutions means a diagnosis code in one hospital does not carry the same meaning in another. And the biggest practical issue. EHR datasets capture what was documented, not what actually happened. A missed diagnosis will not appear in the data. A condition that was treated but never coded will be invisible.
Get the Full Details

If your goal is predictive modeling, consider supplementing the EHR data with claims data when available. Claims contain billing information that often corrects or completes diagnostic coding. If your goal is causal inference, EHR datasets alone are usually insufficient without a careful quasi-experimental design. For pure data exploration, start with a small subset. A single admission with all its linked tables. Get the relationships right before scaling up. The skill that matters most is not the machine learning part. It is understanding what each table represents clinically. I spend more time reading the data dictionary and talking to clinicians than I spend tuning models. The dataset will tell you what it can tell you. It will also tell you what it cannot. The trick is learning to read both signals.