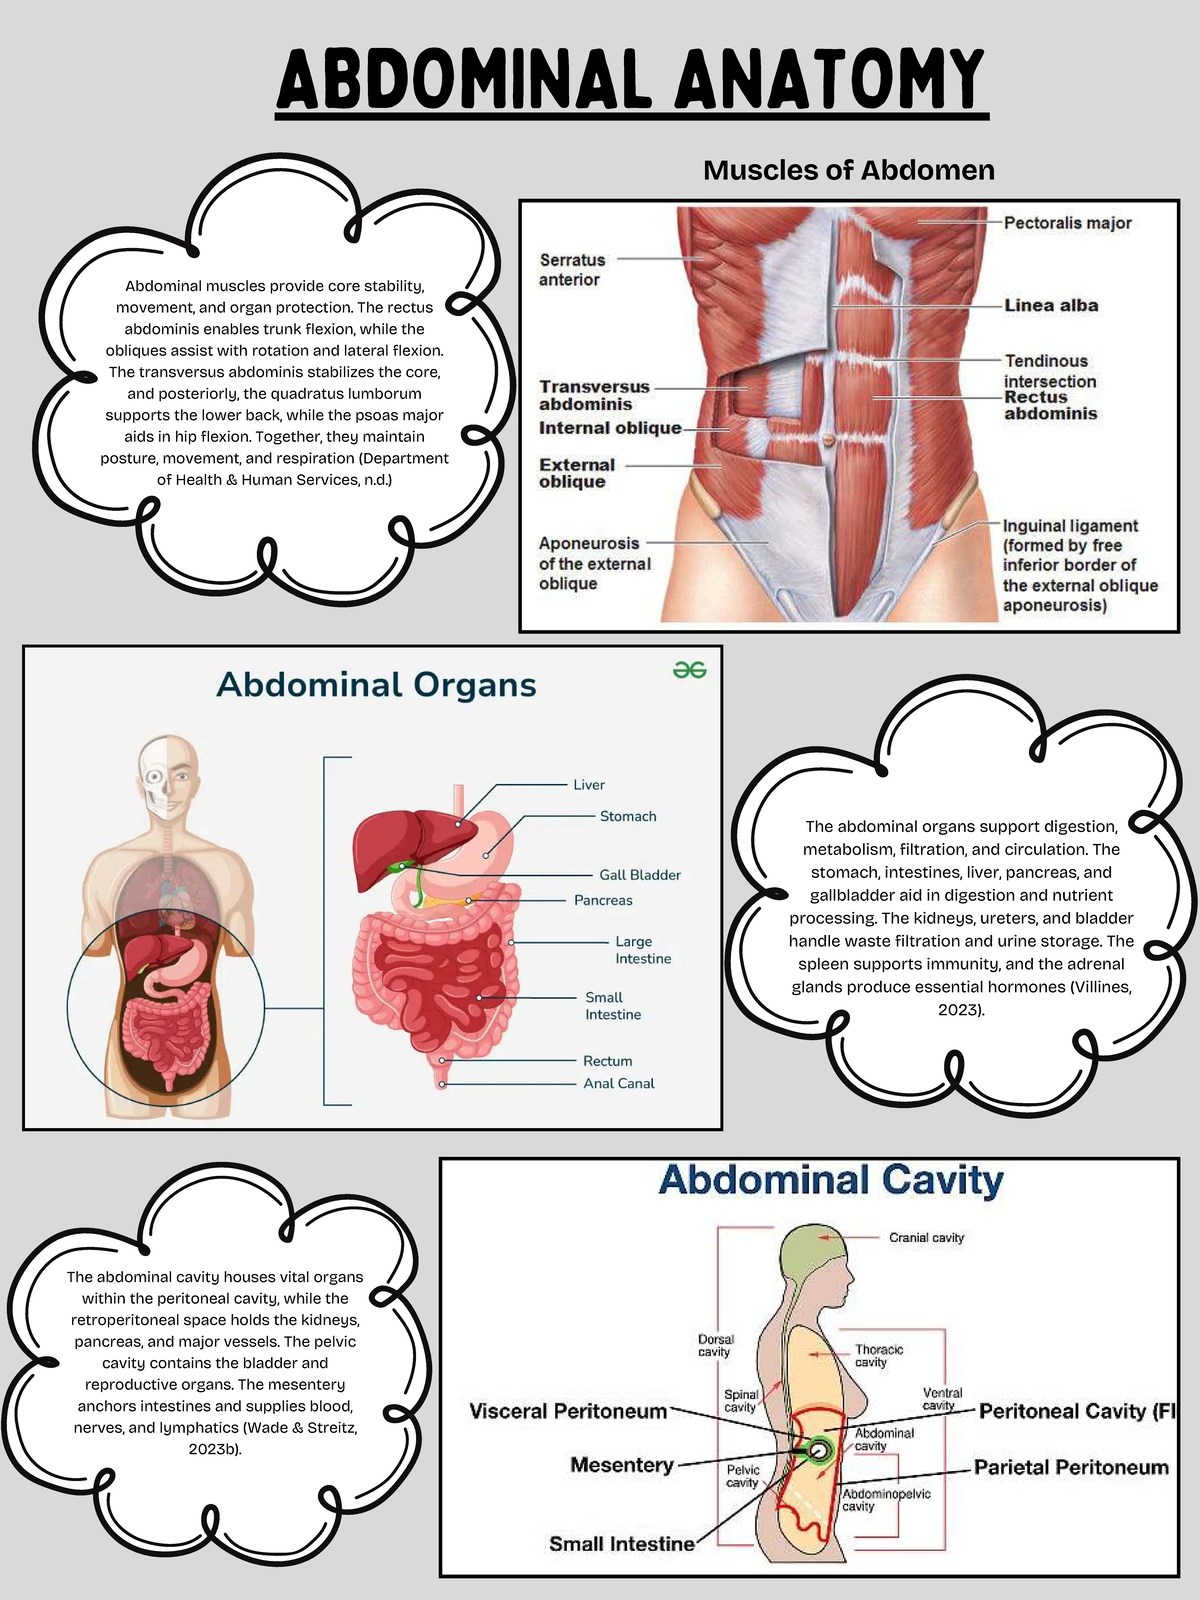
Abdominal Region Mapping: A Practical Reference
Most people learn about the nine-region and four-quadrant systems in anatomy class and never use them again. That's a mistake. When you're studying imaging, preparing for clinical work, or just trying to understand your own symptoms, having a clear mental map of where everything sits matters more than memorizing Latin names. The reason guides like this keep getting written and updated is that the traditional teaching doesn't match how things actually present in practice. Textbooks show you perfect diagrams with organs in ideal positions. Real bodies are not diagrams. The liver drags lower on the right side in some people. The spleen can extend further than expected. The stomach shifts after a meal. Understanding the variability is what separates someone who can read an exam from someone who can't. I've spent years going back to these maps during consultations, imaging reviews, and procedure planning. The one constant is that no two reference sheets are perfect, which is why I end up making my own version roughly every year or two and keeping it within reach.
The Nine-Region System
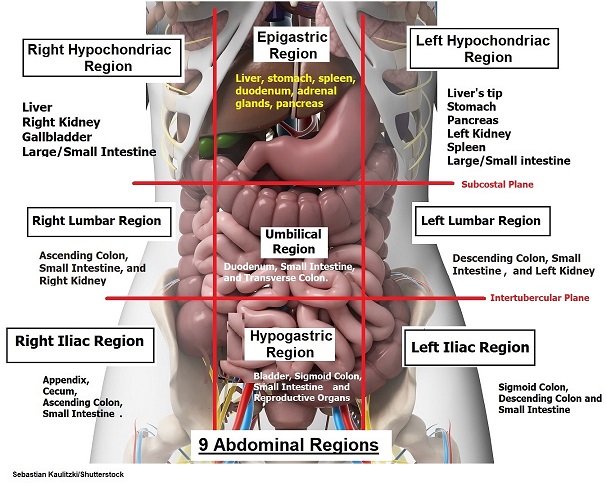
The abdomen gets divided by two horizontal planes and two vertical planes. The transumbilical plane passes through the umbilicus and the subcostal plane runs along the lower margin of the rib cage. The midclavicular lines drop down from the midpoint of each clavicle. That gives you nine regions: Right hypochondriac, epigastric, left hypochondriac, right lumbar, umbilical, left lumbar, right iliac, hypogastric, and left iliac. The right hypochondriac region houses the liver edge, gallbladder, hepatic flexure of the colon, and the right kidney posteriorly. The epigastric region contains the stomach, pancreas, liver dome, and aorta. The left hypochondriac region has the spleen, splenic flexure, stomach fundus, and left kidney. The right lumbar region is mostly colon with the ascending colon and right kidney sitting behind it. The umbilical region is deceptively empty-feeling but contains loops of small intestine, the inferior vena cava, and the origin of the superior mesenteric artery. The left lumbar region mirrors the right with the descending colon. The right and left iliac regions contain the cecum and appendix on the right, sigmoid colon on the left, and reproductive organs depending on sex. The hypogastric region holds the bladder, uterus, and rectosigmoid junction.
The Four-Quadrant System
Clinicians use the four-quadrant system more often because it's faster. A single vertical midline and a single transumbilical horizontal line create the right upper quadrant, left upper quadrant, right lower quadrant, and left lower quadrant. RUQ pain immediately narrows the differential toward liver, gallbladder, duodenum, right kidney, and the hepatic flexure. RLQ pain points toward the appendix, cecum, right ovary and fallopian tube, and right ureter. LUQ involves the spleen, stomach, pancreatic tail, left kidney, and splenic flexure. LLQ is mostly colon and reproductive structures. The four-quadrant system sacrifices precision for speed, which is usually what you need in an acute setting.
Get the Full Details

Something Most Guides Don't Warn You About
Organ position varies significantly with body habitus and even with respiration. In tall, thin individuals, the viscera sit lower. In shorter, broader builds, they're more elevated. I once spent twenty minutes trying to trace what I thought was a mass in the right lower quadrant on a CT scan, only to realize it was just the hepatic flexure of the colon positioned unusually low because the patient was emaciated from chemotherapy. The organ wasn't abnormal. It was just in a position I hadn't accounted for. That's the kind of thing that shows up when you stop treating the maps as rigid and start treating them as probabilistic. Another detail that's easy to miss: the peritoneal relationships matter more than the surface landmarks. A retroperitoneal organ like the kidney or pancreas will refer pain differently than a intraperitoneal one like the stomach or small bowel. Visceral pain is poorly localized. Somatic pain from the parietal peritoneum is sharp and precisely localizable. Knowing whether you're dealing with one or the other changes everything about how you interpret symptoms.
Common Pitfalls When Learning These Maps
The biggest mistake people make is memorizing the regions without understanding the borders. If you don't know exactly where the subcostal plane sits relative to the L3 vertebra, you'll misalign your mental grid every time. The subcostal plane is at L3. The transtubercular plane, which sometimes replaces the transumbilical plane in clinical practice, is at L5. Getting those vertebrae wrong throws off your entire orientation. A second issue is assuming static anatomy. The gallbladder isn't always under the right costal margin. During deep inspiration, the liver and everything attached to it drops about two to three centimeters. If you're palpating a patient who hasn't exhaled fully, you might miss a splenomegaly that would be obvious with proper technique, or you might mistake a normal liver edge for hepatomegaly. Depth of breathing changes the map in real time. The third pitfall is over-trusting surface landmarks in obese patients. The umbilicus is not a reliable landmark in someone with significant adiposity. It can shift position considerably. In those cases, relying on bony landmarks like the iliac crests and the xiphoid process gives you a more stable reference frame.
How to Actually Use This Information
The most practical approach is to build a personal reference sheet and keep it accessible. Write out the nine regions, list the key organs in each, note the common pathologies associated with each area, and include the vertebral level for each plane. Stick it somewhere you'll actually look at it. I keep mine taped to the inside of my cabinet next to the imaging workstation. It takes up about six by eight inches and saves me from having to reopen textbooks every time I need a quick reminder. When studying, don't just read the lists. Draw the grid yourself. Place the organs on a blank torso diagram. Do it from memory first, then check your work. The act of drawing forces you to confront gaps in your understanding that passive reading hides. I found this out the hard way when I could name every organ but couldn't reliably place the duodenum on a blank diagram. Turns out I'd never actually visualized its C-loop relationship to the head of the pancreas properly.
The Limitations You Need to Accept
No surface map will ever fully capture the complexity of the abdomen. These systems are teaching tools, not diagnostic instruments. They were designed for education and gross anatomical description, not for pinpointing pathology in living patients. Imaging technology has made them less critical for diagnosis, but they remain essential for communication. When a clinician says "tenderness in the right lower quadrant," everyone in the room knows exactly what anatomical area they're discussing. That shared language has value even if it doesn't replace an ultrasound. The maps also break down in emergency and surgical situations where organ displacement is common. Trauma, ascites, pregnancy, and large masses all shift structures from their textbook positions. In those scenarios, relying solely on surface anatomy without imaging is dangerous. The maps give you a starting point, not an answer.
A Note on Downloadable Resources
There are plenty of abdominal organ mapping guides available online, but quality varies enormously. Some are accurate but outdated. Others are visually appealing but contain errors in organ placement. When you find a resource worth keeping, check the publication date, verify the organ positions against a standard anatomical reference like Gray's Anatomy or Netter's, and look for author credentials. A guide written by someone with clinical or anatomical training will generally be more reliable than one compiled from secondary sources. I tend to favor resources that include both the nine-region and four-quadrant systems side by side, show cross-sectional anatomy references, and note the vertebral correlations. Those three elements together make a guide actually usable rather than just decorative.