Understanding the Ulna When It Stops Behaving
Most people never think about their ulna until it hurts. I spent a few years dealing with elbow issues that nobody could quite pin down, and eventually it came back to this bone being treated like some kind of afterthought compared to the radius. Let me break down what actually happens here, because clinical significance isn't something you find in a basic anatomy textbook.The Ulna Unraveling The Anatomy Function And Clinical Significance Of The Forgotten Bone
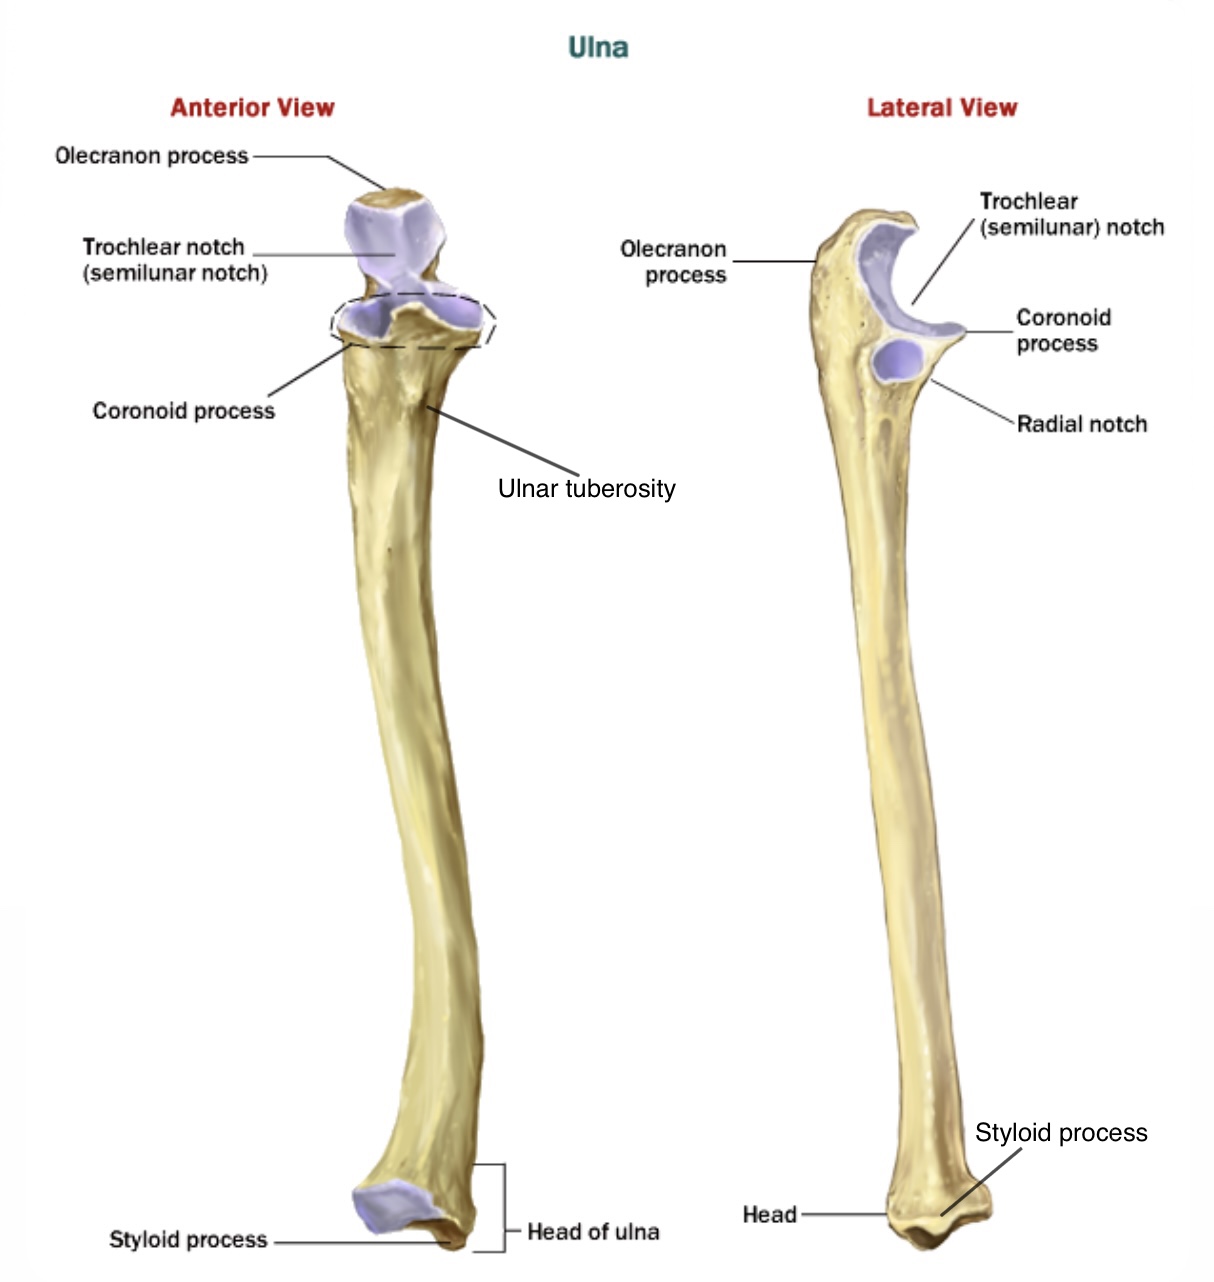
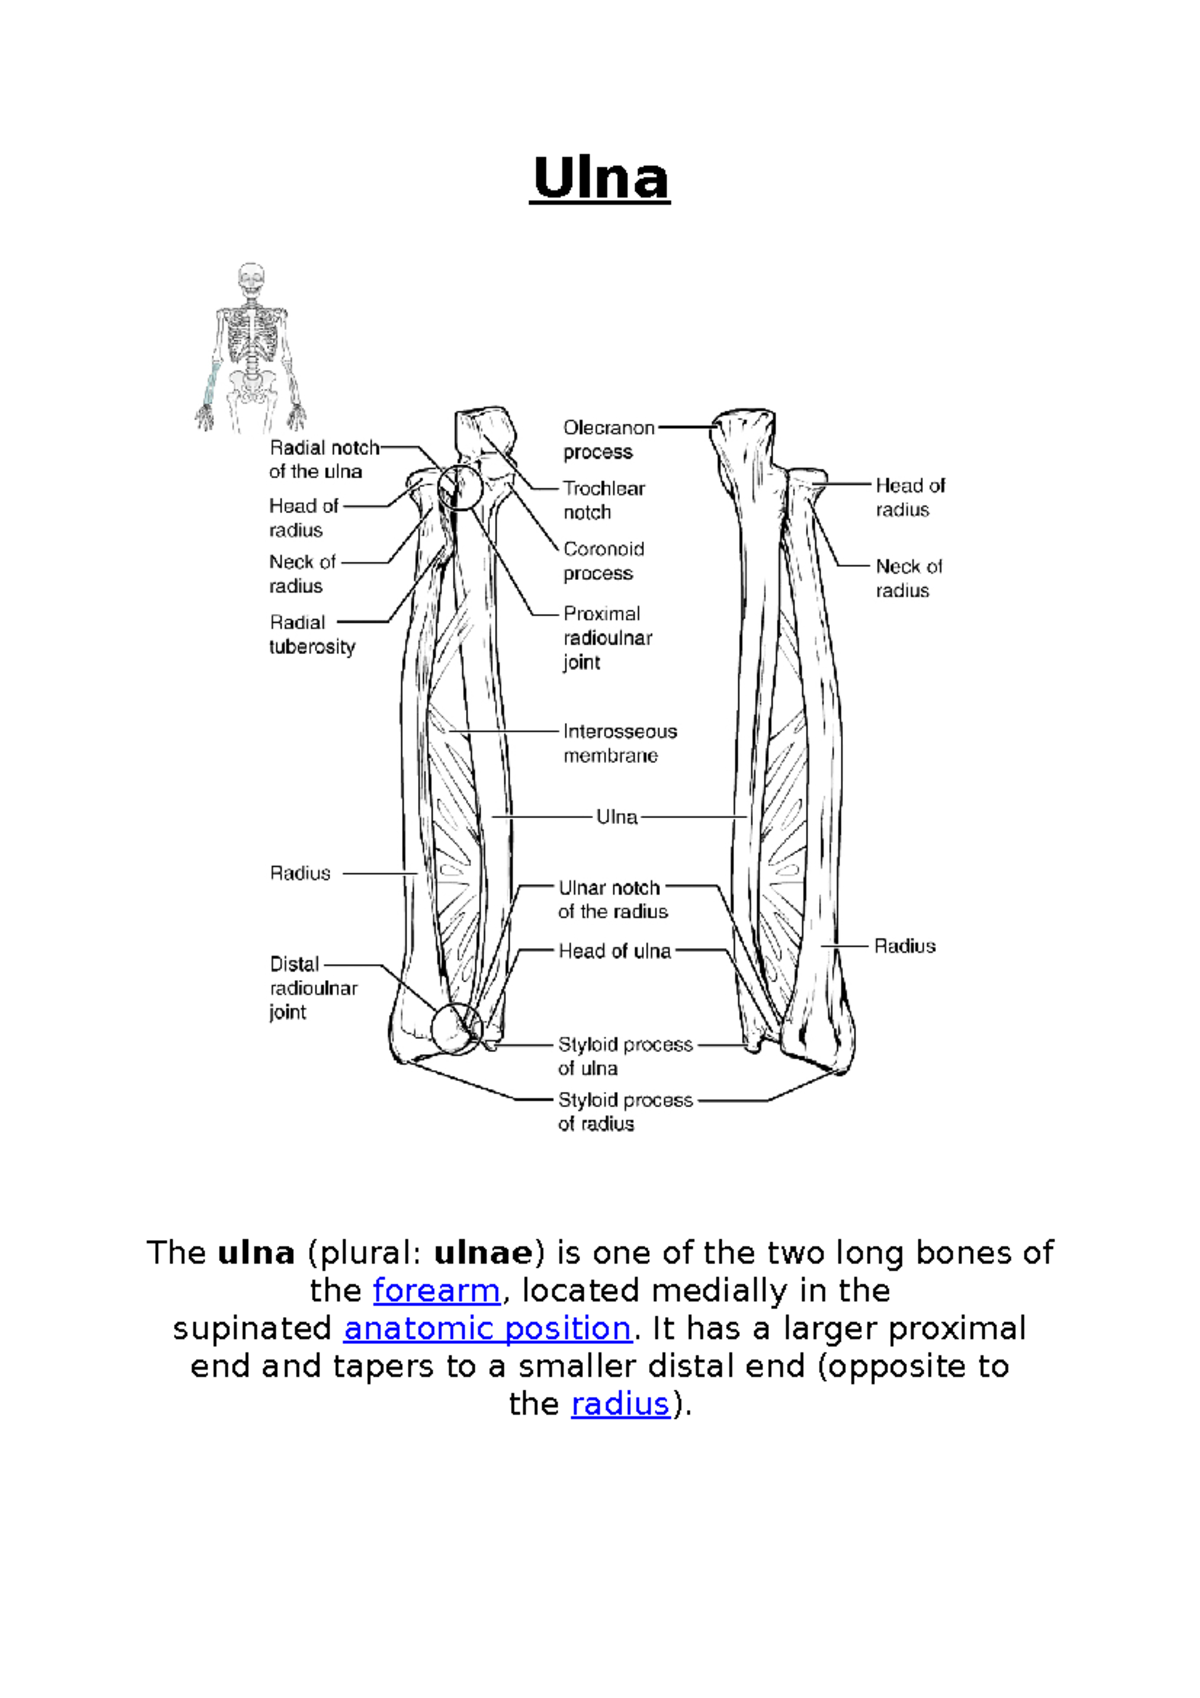
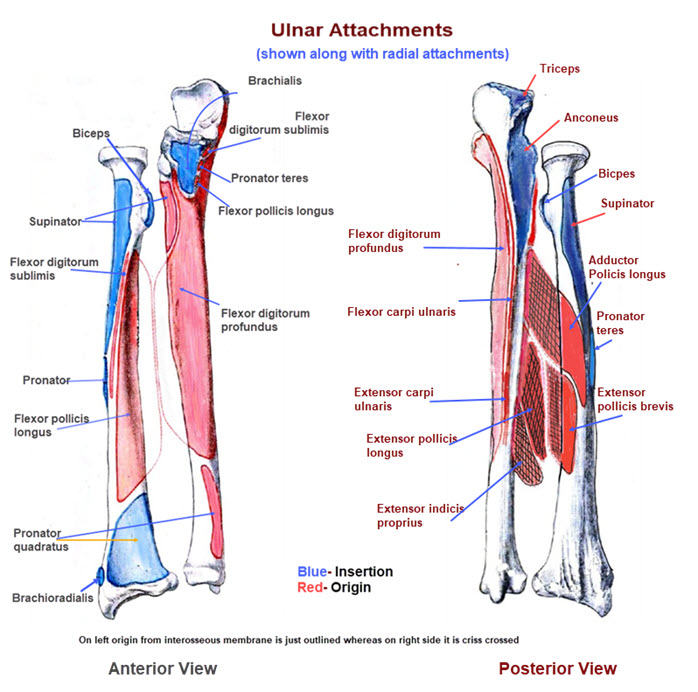
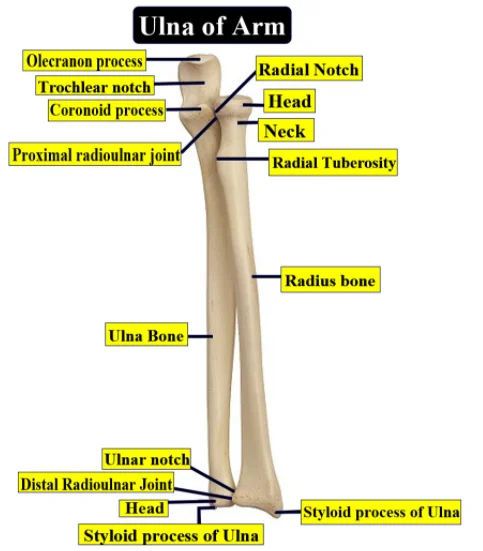
The ulna is one of two long bones in the forearm, running from the elbow down to the pinky side of the wrist. It's thicker at the top and tapers toward the bottom. The olecranon forms the bony point of your elbow - that's the part that takes the hit when you lean on concrete. The coronoid process sits just below it and helps stabilize the joint. Near the wrist you've got the ulnar head with the styloid process jutting off it. The trochlear notch wraps around the humerus like a C-clamp. That's the anatomy. Now let's talk about what it does. Functionally the ulna is primarily a stability structure. It bears roughly 60 percent of the axial load through the elbow and forearm. The radius does a lot of the rotation work during pronation and supination, but without the ulna holding things together that motion would be chaos. The interosseous membrane connects the two bones and distributes forces across the forearm. When that membrane gets compromised, things fall apart fast. I'm going to skip the basic stuff most articles cover and get into what actually matters clinically. The ulnar nerve courses right behind the medial epicondyle and then travels between the two heads of the flexor carpi ulnaris. Cubital tunnel syndrome - compression of that nerve at the elbow - is the most common ulnar-related complaint I see. It's not dramatic. It's numbness in the ring and little fingers, weakness when gripping, and eventually the hand starts looking sad from intrinsic muscle atrophy. People ignore it for months. By the time they come in, conservative treatment has about a 40 to 50 percent success rate instead of the 80 percent you'd get if caught early.
Elbow dislocations are another area where the ulna matters way more than people realize. Up to 80 percent of elbow dislocations involve some kind of ulnar fracture. The posterior olecranon can shear off, or you get a terrible triad injury where the radial head breaks, the coronoid fractures, and the ligaments blow out simultaneously. I've seen surgeons spend four hours on these. The approach matters enormously here. A triceps-splitting approach gives you visibility but weakens the extension mechanism. An olecranon osteotomy preserves the muscle but opens up a whole new healing variable. Pick wrong and you're dealing with nonunion or stiffness for the rest of the patient's life.
Ulnar Styloid Fractures and Where They Go Wrong
The ulnar styloid process gets fracture often enough that it should be a board question. It attaches the ulnar collateral ligament complex and the triangular fibrocartilage complex. When it breaks, you've potentially destabilized the entire distal radioulnar joint. Here's what most protocols miss: a base fracture of the styloid with DRUJ instability needs surgical fixation. A tip fracture without instability usually doesn't. The difference comes down to whether the ulnocarpal ligament insertion is involved. If you're treating a base fracture as if it's a tip fracture, you're asking for chronic wrist pain and grip weakness down the line. I ran into a case where a patient had a displaced ulnar styloid fracture that was initially treated conservatively. Six months later she still couldn't pronate or supinate without catching and pain. The fracture had united, but the DRUJ was subluxing with every forearm rotation. We ended up doing a screw fixation through the styloid base into the ulnar shaft. Recovery took about twelve weeks, but she got her motion back. The lesson was that imaging the DRUJ under stress with fluoroscopy during the initial evaluation would have caught the instability right away instead of waiting half a year.
Get the Full Details
Guyon's Canal and Distal Ulnar Pathology
Further down the line you've got Guyon's canal, the space between the pisiform and hamate where the ulnar nerve and artery pass through. Compression here causes hand-level ulnar neuropathy instead of the elbow-level version I mentioned earlier. Cyclists get this all the time from handlebar pressure. The presentation is almost identical to cubital tunnel syndrome but the treatment pathway diverges significantly because the lesion location changes the surgical approach entirely. Decompression at the wrist is a fifteen-minute procedure with a much better prognosis than elbow surgery in most cases. Repetitive stress fractures of the ulnar shaft are rare but devastating when they happen. I saw one in a thrower who kept pushing through the pain. The fracture line was through the mid-diaphysis, right where the bone gets its weakest blood supply. It didn't heal for eight months despite rest and bone stimulator use. Eventually required a compressive plate and autograft. Throwing athletes should be monitored closely for medial elbow pain that doesn't respond to standard rest. Early imaging with MRI picks up the stress reaction before it becomes a complete fracture.
When the Ulna Dictates the Surgical Plan
Forearm fracture management has shifted a lot over the years. Two-bone forearm fractures used to get casted routinely. Now we know that anything with significant angulation or shortening needs open reduction and internal fixation. The rule of thumb is less than ten degrees of angulation and less than three millimeters of shortening in the adult forearm. Beyond that you lose supination and pronation strength measurably. I've seen patients lose about fifteen to twenty percent of rotational range when those thresholds are exceeded and never fully recover it. The proximal ulna deserves special mention because of Monteggia fractures. A fracture of the proximal ulnar shaft with dislocation of the radial head. There are four types and they each get managed differently. Type 1 is anterior dislocation with a posterior apex fracture - most common in kids. Type 2 is the opposite direction and more common in adults. Type 3 involves lateral or anterior dislocation at the level of the radial head and is typical in pediatrics. Type 4 has both the ulnar fracture and a radial shaft fracture. The key point is that every single one of these requires anatomical reduction of the ulna first. Once the ulnar length and alignment are restored, the radial head usually reduces spontaneously. If it doesn't, then you're dealing with a more complex injury and possibly an associated ligamentous disruption that needs separate attention. I had a case where the ulnar fracture was reduced but not perfectly aligned - maybe five degrees of apex anterior angulation. The radial head reduced initially but then subluxed again with gentle range of motion. We thought we had a persistent dislocation problem until we went back and realized the ulnar shortening was subtly altering the tension on the interosseous membrane and the annular ligament. Revision fixation brought everything back into normal alignment and the radial head stayed put. Five degrees doesn't sound like much until you understand how tightly coupled the forearm mechanics are.
Practical Evaluation Steps
If you're evaluating ulnar pathology, start with the basics but don't rush past them. Elbow extension and flexion should be measured. Forearm pronation and supination need goniometric assessment - not eyeballing it. Grip strength comparison between sides matters. Then do the specific tests. Tinel's sign at the elbow for cubital tunnel. The elbow flexion test held for three minutes is actually more sensitive than Tinel's for that condition. At the wrist check for ulnar variance on a true PA radiograph with the arm in neutral position. Positive ulnar variance - where the ulna sits farther distal than the radius - loads the ulnocarpal joint and leads to impaction syndrome. Negative ulnar variance does the opposite and shifts load to the radial side. Ulnar variance changes with forearm rotation. Supination makes the ulna relatively more dorsal and can mask variance on a standard PA view. That's why getting a lateral view and comparing both wrists is important. I usually order a PA of both forearms and wrists in neutral rotation, plus a lateral of the symptomatic side. If the story suggests DRUJ involvement, I add a clenched-fist view which stresses the joint and reveals instability that doesn't show up on a relaxed film.
Where Conservative Care Fails
Most ulnar issues respond to conservative treatment if caught early. Rest, activity modification, NSAIDs, and physical therapy covering forearm flexor and extensor strengthening along with nerve gliding exercises. But there are clear indicators where that approach is wasting time. Acute complete ulnar nerve laceration needs repair within days for meaningful recovery. Displaced intra-articular fractures with joint incongruity need surgical fixation. Chronic DRUJ instability that fails six weeks of conservative care typically needs reconstruction. Persistent cubital tunnel syndrome with denervation on EMG and measurable muscle atrophy warrants surgical decompression rather than continued observation. The ulnar tunnel syndrome variant at the wrist is another one that gets missed repeatedly. People treat it as cervical radiculopathy or carpal tunnel when the distribution pattern is completely different. Ulnar tunnel symptoms respect the boundary of the canal - they don't cross into the median nerve territory. If a patient has isolated ring and little finger sensory changes with normal cervical spine imaging and normal median nerve studies, the lesion is either at the elbow or the wrist. Distinguishing between those two locations determines the entire treatment plan.
The Recovery Timeline Nobody Talks About
Ulnar nerve decompression at the elbow has a reputation for being finicky. Even with perfect surgical technique, return of sensation can take six to twelve months. Motor recovery is slower and sometimes incomplete if the compression was severe. I tell patients upfront that this isn't a quick fix. The nerve has to regenerate and reinnervate, and that process follows a predictable but slow biological timeline. Early surgery gives better outcomes but patients who present with mild symptoms still benefit from a structured conservative trial before considering operation. The sweet spot is moderate symptoms with positive electrodiagnostic findings and no significant atrophy yet. Fracture healing follows its own schedule. Proximal ulnar fractures typically unite in six to eight weeks in healthy adults. Mid-shaft fractures take eight to twelve weeks. Distal fractures with good blood supply heal faster but are more prone to nonunion if the fracture pattern is oblique or comminuted. The interosseous membrane attachment zone near the tuberosity is a particular weak point mechanically and biologically. Fractures through this area have a higher nonunion rate and sometimes require earlier surgical intervention rather than waiting to see if they'll heal on their own. The ulna gets dismissed as the boring partner bone in the forearm. That's a mistake. It carries the load, stabilizes the joints, and protects a major nerve. When it fails, the downstream effects ripple through the entire upper extremity. Understanding the anatomy beyond the textbook definitions and recognizing the patterns that don't fit the standard protocols is what separates adequate care from good care. Most of these problems are straightforward when you know what to look for. They become complicated when you're treating them as something they're not.