Where You Will Actually Find This Tissue
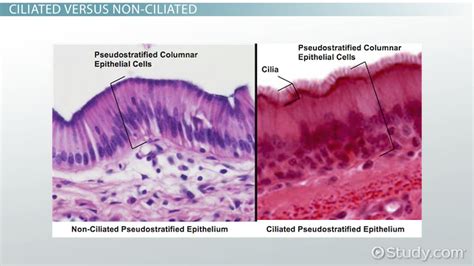
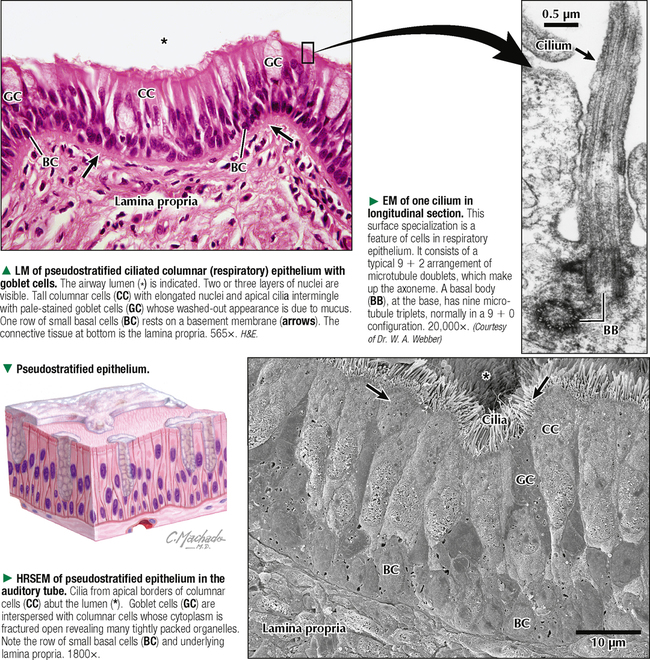
Pseudostratified columnar epithelium shows up in places that consistently trip people up on exams and in the lab. The most common textbook answer is the respiratory tract, but that is only part of the picture. The epithelium lines the trachea, bronchi, and the upper airways as respiratory epithelium with cilia and goblet cells. It also appears in the male reproductive system, specifically the epididymis and the vas deferens. The efferent ductules of the testis are another location, and they have a different appearance than the respiratory version because the cilia are longer and more pronounced while the microvilli do the real absorptive work there. I learned this the hard way during a histology practical where the slide was stained with H&E and the section was cut obliquely. The nuclei were all at different levels, which is the defining feature, but the oblique cut made it look almost stratified squamous at first glance. I almost picked the wrong answer. The trick is to look for the basal lamina. In true stratified epithelium, multiple cell layers sit on top of each other and the bottom layer attaches to the basement membrane. In pseudostratified, every single cell contacts the basement membrane, even if the nucleus is positioned higher up and you cannot see the apical surface of that particular cell. That is the single most reliable way to distinguish the two without switching to a different stain. The function follows directly from the location. In the respiratory tract, the ciliated cells move mucus produced by goblet cells upward toward the pharynx. This is the mucociliary escalator. It is not a subtle mechanism. Particulate matter, pathogens, and debris get trapped in the mucus layer and the coordinated beating of the cilia moves it along. The rate of transport depends on ciliary beat frequency, which drops significantly with chronic smoking or cold air exposure. In the male reproductive tract, the function shifts. The stereocilia on the epididymal epithelium are actually long microvilli that dramatically increase surface area for absorption and secretion. They reabsorb testicular fluid and secrete proteins that mature sperm need. Confusing the stereocilia of the epididymis with the true cilia of the respiratory tract is a common mistake because they look similar under low magnification.
One thing that always comes up in practice is the basal cell layer. Pseudostratified columnar epithelium contains reserve stem cells called basal cells that sit on the basement membrane but do not reach the lumen. These cells are responsible for regeneration after injury. In smokers, the epithelium can undergo metaplasia where the pseudostratified ciliated columnar epithelium is replaced by stratified squamous epithelium because the constant irritation makes the ciliated cells unsustainable. The basal cells are still there, but they differentiate into squamous cells instead. This is clinically significant because metaplasia in the bronchus is a precursor lesion and it is reversible if the irritant is removed early enough. When you are working with actual tissue samples, the biggest problem is fixation. Over-fixation in formalin for more than forty-eight hours makes the cilia brittle and they detach during processing. You end up with an epithelium that looks stripped and disorganized, and you might incorrectly conclude the tissue was diseased. I started cutting the fixation time down to twenty-four hours for respiratory samples, and the ciliary architecture came back cleanly every time. For the epididymis, the stereocilia are more resilient but they still benefit from shorter fixation periods. If you are doing immunohistochemistry, you need even shorter fixation or you will lose antigenicity in the ciliary proteins. Another practical issue is section thickness. Standard microtome sections at five micrometers work fine for identifying the tissue type, but if you want to see the cilia clearly or assess the density of goblet cells, you need thicker sections around eight to ten micrometers. Thinner sections compress the epithelium and make the pseudostratification harder to appreciate because the nuclei get pushed into a narrower vertical space. I usually cut a test section at five micrometers first to confirm orientation, then go to eight micrometers for the diagnostic cuts.
There is also a staining consideration. The PAS stain is useful for highlighting the goblet cell mucin in respiratory epithelium, but it does not work well for the epididymal stereocilia because those are lipid-rich microvilli, not mucin-producing structures. If you are trying to identify the tissue based on staining alone and you use PAS expecting a positive result in the apical borders, you will get confused when the epididymal sample comes out nearly negative. Oil Red O or Sudan Black can work for the lipid content in stereocilia, but those are fat-soluble dyes that require frozen sections, which adds a whole other layer of complexity to the workflow. The goblet cell density is another variable that people overlook. In healthy adult respiratory epithelium, goblet cells make up roughly five to ten percent of the epithelial surface. In chronic bronchitis, that number can jump to thirty percent or more due to goblet cell hyperplasia. Counting goblet cells is tedious but it is one of the few quantitative metrics that actually correlates with disease severity in research settings. I use a simple grid overlay on a digital microscope image and count positive cells per millimeter of basement membrane length. It takes about fifteen minutes per section and gives you a number you can track over time. If you are studying this for an exam, focus on the nuclear positioning pattern and the presence of a single basal lamina. Those two features will distinguish it from every other epithelial type you will encounter. Do not get distracted by the cilia versus stereocilia distinction unless the question specifically asks about the reproductive tract. The most frequently tested trap is describing this tissue as stratified because of the multi-layered nuclear appearance. It is not stratified. Every cell touches the basement membrane. Remember that and you will avoid the most common error.
Get the Full Details

For anyone working in a lab setting, the takeaway is straightforward. Shorter fixation preserves ciliary structure. Thicker sections reveal the pseudostratification more clearly. Different stains are needed for respiratory versus reproductive versions of this tissue. And metaplasia is a real possibility in chronically irritated epithelium, so do not assume normal architecture without checking the clinical context.