Working With Simple Squamous Epithelium: What It Takes
The single layer of flat cells you see under the microscope isn't just a textbook diagram. It is a functional barrier that evolved for one job: letting things pass through it as fast as possible. When you are actually handling this tissue, whether you are preparing slides or interpreting biopsy sections, the margin between seeing it clearly and seeing nothing is measured in micrometers. Simple squamous epithelium lines the alveoli of the lungs, the endothelial surfaces of blood vessels, the mesothelial sheets of body cavities, and the filtration barriers of the kidney Bowman's capsule. It is also the hardest routine epithelium to work with without ruining it. A standard H&E stain will show you the nuclei, but those nuclei are so flattened and offset that they can easily blend into the background if your section thickness is off by even a few microns. I spent a week trying to confirm glomerular parietal epithelium on a set of kidney biopsies because the podocytes and the overlying Bowman's space made the squamous layer nearly invisible. The problem was section thickness. We had been cutting at 4 microns, which worked for most tissues, but at that thickness the delicate squamous linings of Bowman's capsule get folded, compressed, or simply lost in the noise of surrounding structures. I switched to 2-micron sections and used a thinner embedding medium that allowed cleaner cuts. That alone made the distinction between visceral and parietal layers obvious. It also meant my blade changed twice as often, so factor that into your workflow time.
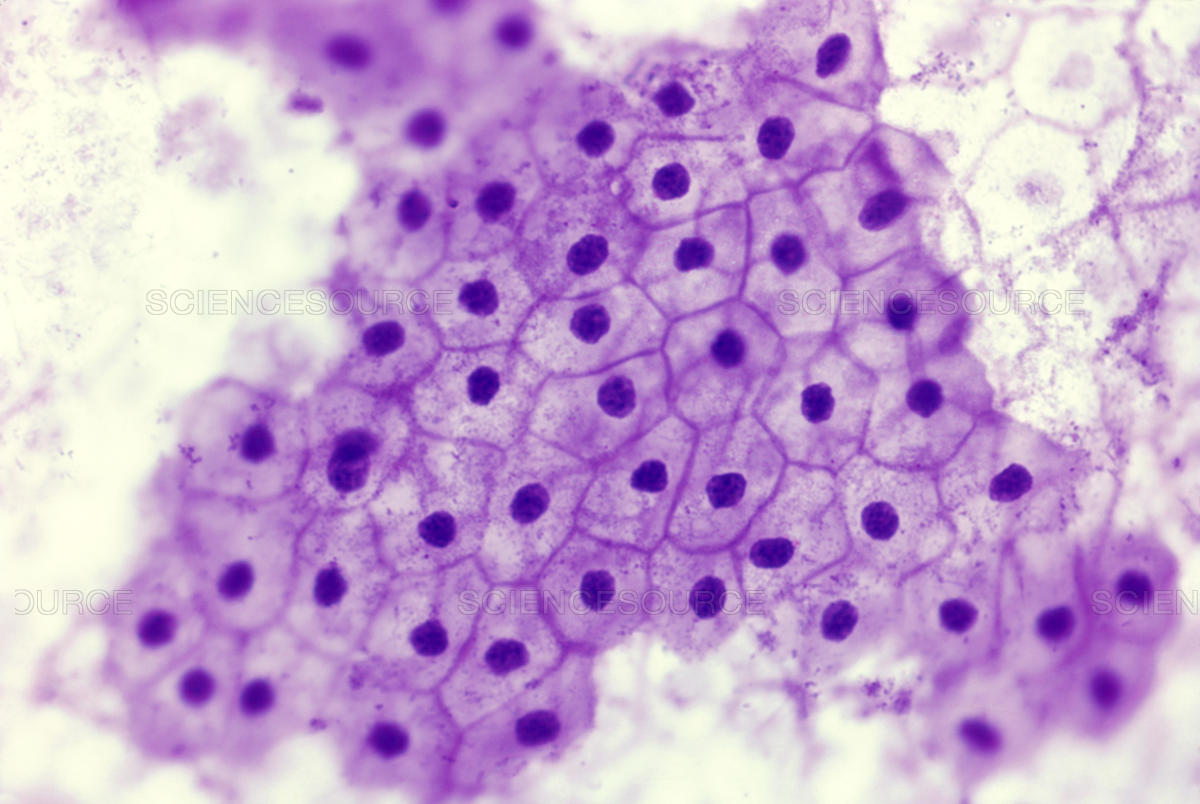
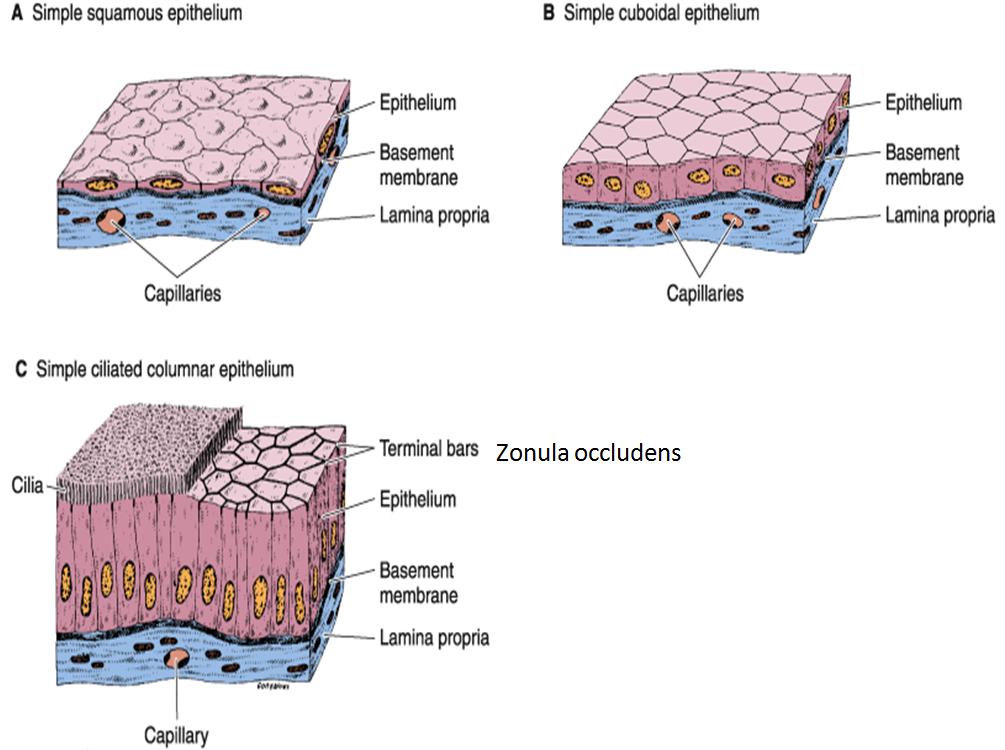
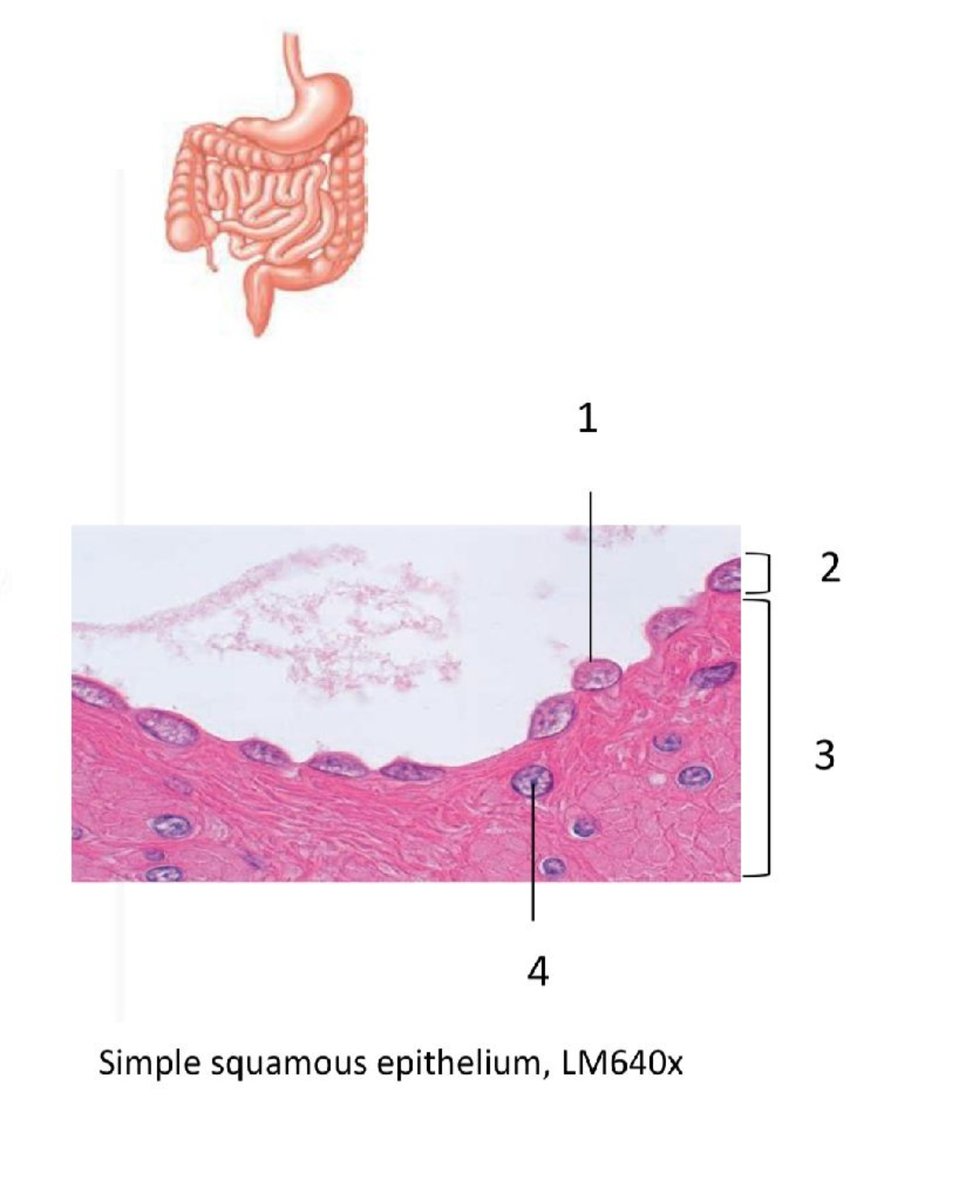
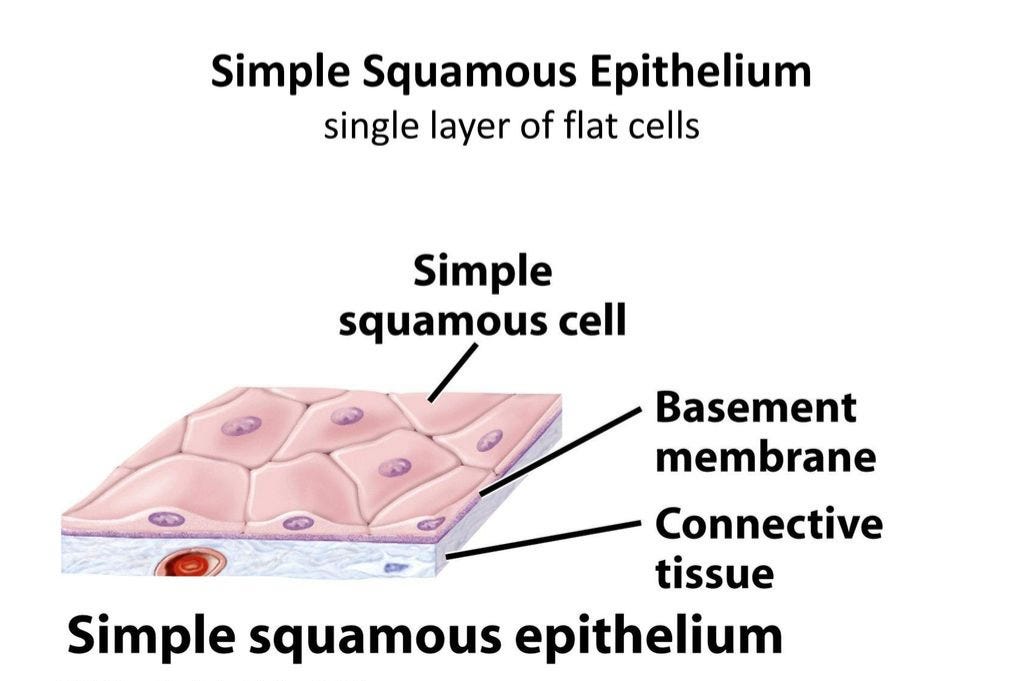
The fundamental defining feature is straightforward: one cell layer thick, with cells wider than they are tall, nuclei that are centrally located, and a basement membrane underneath. What beginners miss is that the cytoplasm is virtually invisible on standard stains because it is so thin. You identify this tissue mostly by where you find it and by the absence of other epithelial types in that location. If you see a surface lined by something flatter than cuboidal and there is no stratification, you are looking at squamous epithelium. The question is whether it is simple or already metaplastic, which brings me to the next point. Practical identification hinges on location and context. In the lung, simple squamous epithelium forms the air-blood barrier along with capillary endothelium. In the vasculature, the endothelial lining is technically also simple squamous, though pathologists and histologists usually refer to it by its functional name rather than its histological class. In serous membranes, it is called mesothelium. All three are simple squamous. They all share the same structural logic: minimal diffusion distance, maximal surface area relative to volume. One counter-intuitive thing worth noting: simple squamous epithelium can appear stratified if it is damaged or undergoing repair. During re-epithelialization after injury, basal cells proliferate and stack temporarily before flattening out again. If you encounter what looks like a thickened squamous layer in an area where simple squamous should be, do not immediately call it stratified squamous epithelium or assume metaplasia. Check the clinical context and look for signs of regeneration: mitotic figures near the basement membrane, irregular nuclear positioning, and a lack of the orderly maturation you see in true stratified epithelium. I once flagged a section as suspicious for squamous metaplasia in the bronchioles, only to realize after consulting the pathology notes that the patient had just recovered from acute respiratory distress and this was post-inflammatory regenerative change. The cells were piling up because they were trying to close a wound, not because they had transformed.
Another detail people overlook: the junctional complexes in simple squamous epithelium are not absent just because the cells are flat. Tight junctions, adherens junctions, and desmosomes are all present, but they are distributed differently than in stratified or cuboidal epithelia. In alveolar type I pneumocytes, for instance, the junctional belt is positioned more peripherally and the cytoplasm extends as thin sheets called cytokeratin-rich microdomains that anchor to the basement membrane. This is why immunostaining for cytokeratins or VE-cadherin can be useful when you need to distinguish endothelial simple squamous lining from mesothelial or alveolar lining. H&E alone will not always give you that resolution. Staining and preparation matter more here than in most other tissues. Over-fixation in formalin for longer than 24 hours causes the cytoplasm to shrink and pull away from the basement membrane, creating artifacts that mimic detachment or sloughing. Under-fixation leads to poor nuclear detail, and since the nuclei are already flat, you lose the very feature you are using to confirm the tissue type. Four to six hours of fixation in 10 percent neutral buffered formalin is typically sufficient for thin squamous surfaces, and for ultrastructural work you need even shorter fixation times or immediate glutaraldehyde processing. If you are doing electron microscopy, the preparation is another hurdle. Simple squamous epithelium is so thin that it is easy to tear during processing. I use a drop-of-method embedding technique for lung and vascular samples rather than standard cassette processing. You place the tissue on a filter paper scaffold, fix it directly on the scaffold, and embed in a low-viscosity resin. This reduces mechanical stress during dehydration and infiltration. The trade-off is that you can only process small pieces at a time, so plan your sample size accordingly. A typical batch of ten to fifteen samples takes about forty-five minutes longer from fixation through embedding compared to routine processing.
Get the Full Details
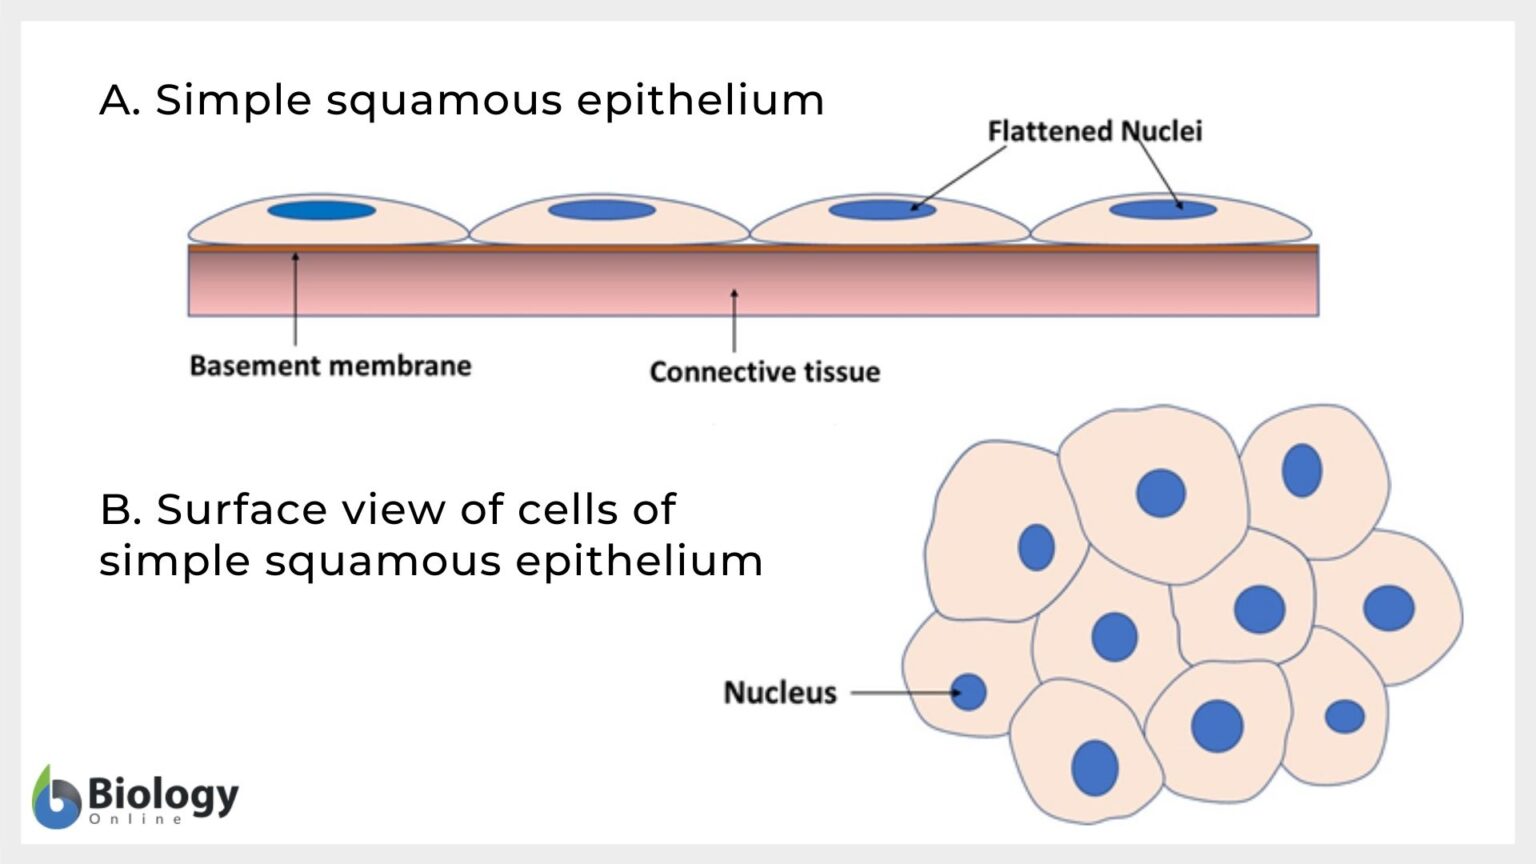
For light microscopy, section thickness remains the biggest variable. Two to three microns is the sweet spot for most simple squamous applications. Anything thicker and the layer appears stratified due to overlapping planes. Anything thinner and you risk tears and folds. I cut at 2.5 microns and stain with a modified PAS-Alcian blue protocol when I need to highlight basement membranes, which helps separate the epithelial layer from the underlying connective tissue. On standard H&E, the basement membrane is often faint, and without it you lose a key landmark for confirming that you are indeed looking at a single layer sitting on a proper basal lamina. Common pitfalls and where this tissue type falls short. Simple squamous epithelium provides excellent diffusion but almost no protection. It is the reason you do not find it in areas subject to mechanical abrasion or chemical insult. The esophagus and skin use stratified squamous epithelium for a reason. If you see simple squamous epithelium in a location where it does not belong, such as the trachea or bronchi under chronic irritation, squamous metaplasia is the likely explanation, and that is a premalignant change worth flagging. Conversely, in the ovary, the surface epithelium is simple squamous to cuboidal in its normal state, and persistent irritation or inflammation can drive changes that are histologically subtle but clinically significant. Context is everything. The filtration function in the kidney is another area where the simplicity of this tissue is also its vulnerability. The glomerular basement membrane and the fused foot processes of podocytes create a size-selective barrier, but the parietal simple squamous layer of Bowman's capsule contributes structurally even though it is not part of the primary filtration slit. Damage to this layer, as seen in crescentic glomerulonephritis, allows fibrin and inflammatory cells to accumulate in Bowman's space, and the resulting cellular crescent can be mistaken for hyperplasia of the original squamous layer if you are not careful. The cells in a crescent are predominantly parietal epithelial cells and infiltrating monocytes, not a proliferation of true simple squamous cells. Distinguishing between the two affects diagnosis and treatment decisions, so this is not just an academic distinction.
When you are learning to identify this tissue, start with the lung. Alveolar walls are the cleanest example of simple squamous epithelium in the body. The type I pneumocytes cover about ninety-five percent of the alveolar surface area despite being extremely thin. Type II pneumocytes are cuboidal and sit in the corners, producing surfactant. Under a light microscope at forty magnification, you should see the alveolar septa as thin pink lines with occasional nuclei. At one hundred magnification oil immersion, the individual cell borders become clearer, though you will rarely see the cell boundaries without special stains. This is normal. Do not force the identification by calling every thin lining alveolar epithelium. If the section is oblique or folded, what looks like a second layer may just be adjacent alveoli superimposed in the plane of the cut. For vascular endothelium, a whole blood vessel cross-section is the best reference. The lumen-facing layer should be a single row of flattened nuclei with scant cytoplasm. If the endothelial cells appear swollen or plump, that indicates activation or injury, which is common in pathological specimens. A normal quiescent endothelium is nearly inconspicuous on H&E. Active endothelium expresses adhesion molecules and presents a different morphology, so do not mistake activated endothelium for a different tissue type. It is still simple squamous, just not resting. The peritoneum and pleura present another set of considerations. Mesothelial cells are simple squamous to low cuboidal and can shed into body cavities, which means you may find them in cytology specimens like ascitic or pleural fluid. In those cases, they can look like clusters of large cells with prominent nucleoli, which raises concern for malignancy. They are not malignant. The key is that they form cohesive sheets with distinct cell borders and a perinuclear halo, unlike carcinoma cells which tend to be discohesive and show more pleomorphism. I learned this the hard way on a case where a cytopathology report initially flagged mesothelial cells as suspicious adenocarcinoma. A second review with calretinin and WT1 immunostains confirmed mesothelial origin, and the patient avoided an unnecessary surgical intervention.
Practical summary for anyone preparing or interpreting this tissue: Keep your sections between two and three microns. Fix for four to six hours, no longer. Use immunohistochemistry when H&E is ambiguous, particularly cytokeratins for epithelial versus mesothelial differentiation and VE-cadherin for endothelial confirmation. Correlate histology with anatomy: if the tissue is in a location where simple squamous belongs, trust your eyes. If it is in an unexpected location, consider metaplasia or artifact before jumping to pathology. And when in doubt, cut a thinner section and restain. The tissue does not lie, but it does require patience to read correctly.