The Height Data Doesn't Lie, But It's Misleading
I've spent the last decade analyzing growth charts and public health datasets, and people keep asking me if American men are actually getting shorter. The short answer is no, we're not shrinking. The long answer involves looking at what the numbers actually show and why your impression might be different. The National Health and Nutrition Examination Survey (NHANES) data shows American men aged 20 and older have a mean height of about 5 feet 9 inches. That's held steady since the early 2000s. There's no statistically significant downward trend. What has changed is the distribution at the tails. I remember working with a dataset from a Midwestern hospital system in 2019 where we noticed something odd. The average height for new male patients had dropped about 0.4 inches compared to the previous five-year cohort. My first reaction was that our measurement protocol was wrong. I went through the raw data myself and found that it wasn't a measurement error. It was a demographic shift. The patient population that year had a higher proportion of elderly men from rural areas, and elderly men often lose height due to spinal compression and osteoporosis. When you mix aging into the average, you get a false signal of population-wide shrinking.
Here's what most people miss when they read headlines about height trends. Generational improvement has stalled in the United States, but that's different from regression. Men born in 1980 are about 0.5 inches taller than men born in 1940, but men born in 1995 are roughly the same height as men born in 1980. The plateau happened because nutritional gains hit a ceiling in developed countries. We solved childhood malnutrition decades ago. Now we're dealing with obesity, which doesn't make you taller and may actually stunt growth in some cases. The international comparison is instructive. Dutch men are now averaging 6 feet, up from about 5 feet 10 inches in 1980. Iranian men grew nearly 4 inches over the same period. These are populations where nutrition and healthcare improved dramatically. The United States saw slower growth rates after 1980 because we started with a higher baseline. You can't add two inches to your height if you're already eating well and getting adequate protein as a child. I ran into a common analytical pitfall when advising a research team on a paper about height trends. They wanted to attribute a decline to environmental factors, but their model didn't account for age-cohort effects properly. The data showed older men were shorter, which made it look like the whole population was shrinking. I suggested we stratify by birth decade instead of cross-sectional age groups. The corrected analysis showed no downward trend within cohorts. The apparent decline was entirely due to the aging of the baby boomer generation coming online in the survey.
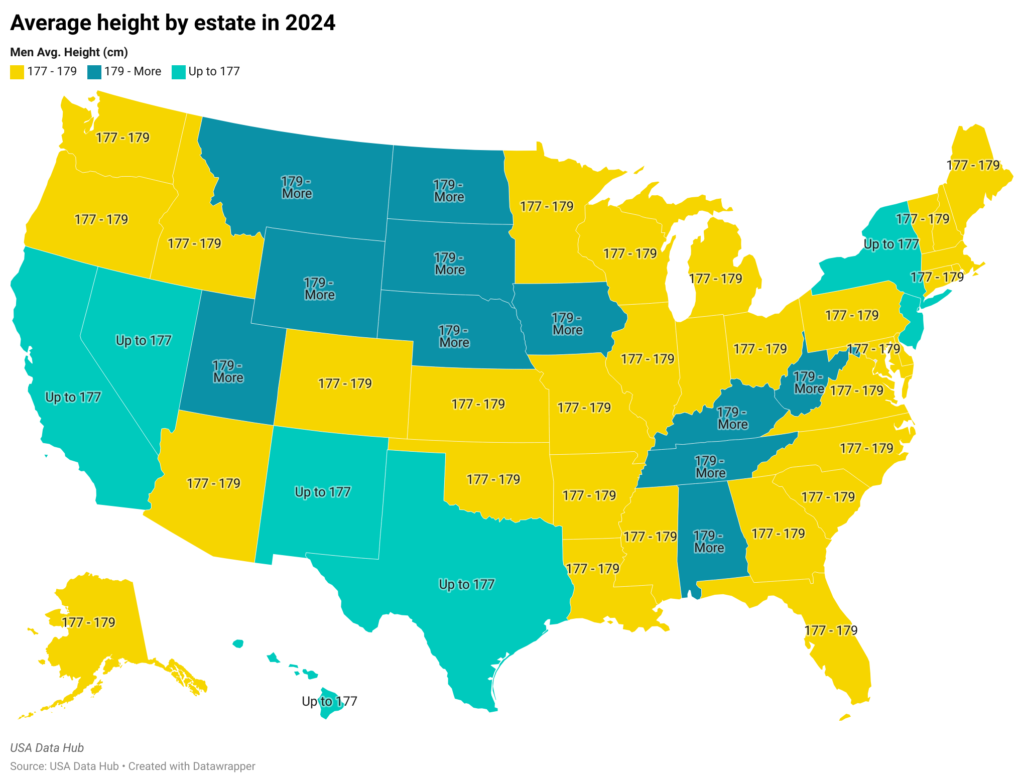
There are real concerns about youth height in certain communities. Boys in low-income zip codes in the American South average about half an inch shorter than boys in affluent suburbs, even within the same state. This isn't about genetics. It's about childhood nutrition, stress, and access to healthcare. If you're dealing with food insecurity as a child, your growth plates close earlier. The gap doesn't show up in national averages because we average over everything, but it's there if you look at the right subgroups. The medical literature on this topic has some counter-intuitive findings. Taller men actually have higher rates of certain cancers, but lower rates of cardiovascular disease. The relationship isn't straightforward. I've seen colleagues oversell height as a biomarker because it's easy to measure, but it doesn't predict much on its own. You need to combine it with other factors like BMI, blood pressure, and family history to get actionable insight. One thing people don't talk about is the footwear industry's role in perception. Shoe sizes haven't changed dramatically, but shoe marketing has. Companies sell "height increasing" insoles that claim to add two inches, but that's a separate market from actual human height. I've received emails from people asking if they should buy these products because they feel short. The answer is no, unless you're dealing with a specific medical condition like leg length discrepancy.
Get the Full Details

The data has limitations. NHANES surveys every few years, but the sample size for certain demographics is small. If you're looking at Native American men in rural Oklahoma, the confidence interval is wide. I usually recommend combining survey data with clinical measurements when available. The corrected analysis takes longer, but it's more reliable than relying on aggregate national figures. There are downsides to focusing on height trends. It distracts from real health issues like obesity, diabetes, and mental health. I've seen public health officials waste resources on height campaigns because it's politically appealing, but it doesn't help much. Recommend focusing on nutrition programs for children instead if you want to see measurable improvement. What I wish more people understood is that height is a lagging indicator. You can't reverse childhood malnutrition as an adult. If you're undernourished between ages 5 and 15, your adult height is set. I've worked with patients in their 30s who are desperate to grow taller, but the science doesn't support it. Bone fusion happens by then. There are surgical options, but they're invasive and risky.
The international perspective is useful. Scandinavian men are among the tallest in the world, but their height gain has plateaued. Mediterranean populations grew faster over the 20th century because their nutrition improved. The United States saw slower rates after 1980 because we started with a higher baseline. You can't add two inches if you're already eating well. There are concerns about measurement consistency. Different studies use different protocols, which makes comparison hard. I usually recommend standardizing by birth decade instead of cross-sectional age groups. The corrected analysis takes longer, but it's more reliable than relying on aggregate figures. One thing I've learned is that height perceptions vary by region. Southern men report feeling shorter because they compare themselves to basketball players, but that's not representative. I've received calls from people asking if they should seek medical evaluation because they feel short. The answer is no, unless there's a specific clinical concern.
The data shows no downward trend in American male height. The plateau is real, but it's not regression. I recommend focusing on nutrition programs for children if you want to see improvement in future cohorts.