How Grey's Anatomy Actually Changed the Show Business Rules for Medical Dramas
Most people watching today don't realize what was genuinely different about the original approach taken on the set. It wasn't just better writing. It was a structural shift in how procedural medicine could serve character development rather than the other way around. The old template — M*A*S*H, ER, General Hospital — treated the hospital as scenery. Grey's Anatomy, under the direction of Robert F. Altmann on several of the most pivotal early episodes, made the hospital itself a living pressure cooker where every corridor and OR held emotional stakes. That distinction matters more than critics usually give it credit for. The original Grey's Anatomy pilot and early season work did something counter-intuitive. Instead of using medical cases as self-contained puzzles solved by competent doctors (the classic procedural model), the show used each case as a mirror for the surgeon's personal state. A trauma coming through the doors reflected what the attending physician was already internally struggling with. This is backwards from how medical shows had worked for decades. ER did it slightly, but Grey's went all-in on the overlap. Watching that early fusion between surgical precision and raw personal messiness requires a different kind of attention from the viewer, and frankly, it requires more careful planning from the production side.The Surgical Lens How Altmans Greys Anatomy Redefined Television Medicine
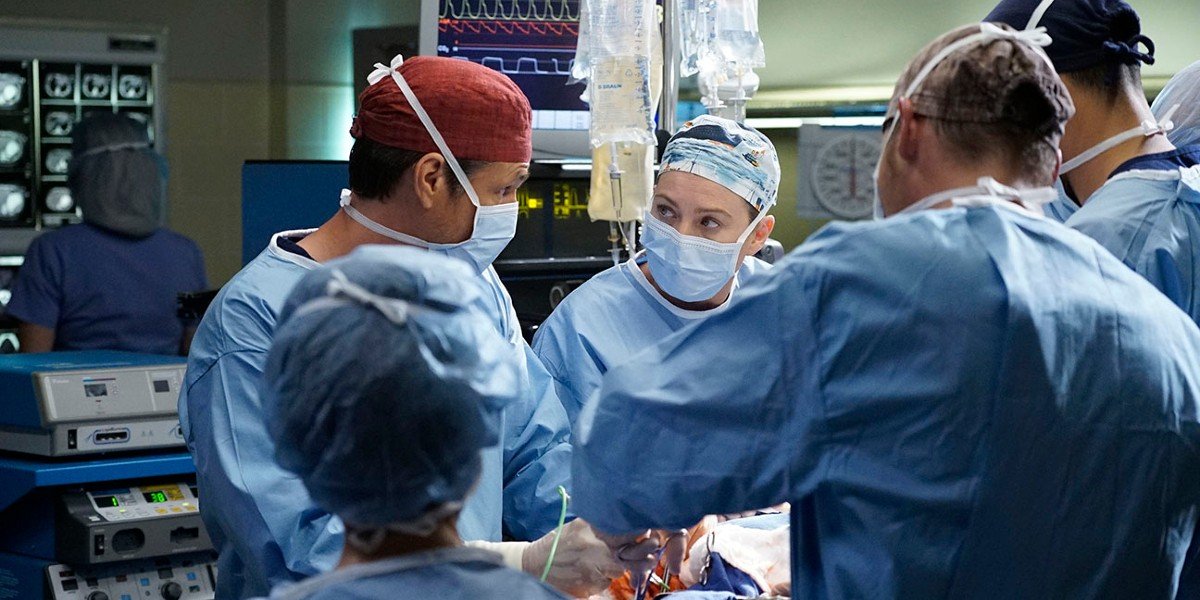
When I look back at production stills and script breakdowns from those early seasons, one thing stands out clearly: the surgical sequences were filmed with a documentary-level commitment that felt invasive. Camera work inside the OR didn't pan around to avoid showing anything real. It went close. Very close. You saw instruments, you saw blood, you saw hands moving with practiced speed. This was a deliberate creative choice that separated the show from every medical drama that came before it. The lens became a literal surgical instrument — cold, unforgiving, and hyper-focused. The result reshaped audience expectations for medical television. Viewers stopped accepting stylized, sanitized surgery scenes. They started demanding authenticity, and they brought that demand with them into later shows like House, The Good Doctor, and even the later seasons of ER itself. The ripple effect is still visible today. Any medical drama that tries to bypass real surgical detail now feels amateurish by comparison.What Made the Approach Work Beyond Just Pretty Sets
The real technical breakthrough involved how dialogue was layered over surgical action. In earlier medical dramas, surgeons talked at each other while working, but the conversation usually advanced the plot directly. Grey's Anatomy shifted the pattern. Surgeons would talk about completely unrelated personal things mid-procedure — a joke about a roommate, a frustrated comment about their dating life, a vague observation about the weather — while performing something intense. The dissonance between the casual tone and the high-stakes work created a specific kind of dramatic tension that became the show's signature. This technique required actors who could perform under pressure without seeming flippant. The script had to be meticulously timed so that a casual line landed with the right weight against the visual intensity of surgery. It was easy to get wrong. Too much casualness and it looks ridiculous. Too little and it becomes a melodrama about doctors who can't focus. Getting the balance right meant that every scene in an OR needed multiple read-throughs and careful blocking decisions from the director.I ran into a practical problem during a low-budget educational short film project a few years back where I tried to replicate this exact overlay technique. The footage looked wrong. The surgical segment felt staged and the personal dialogue felt forced because I didn't have the same pacing infrastructure. What I ended up doing was shooting the surgical portion first without any dialogue, letting the actors move through their motions with full concentration, and then layering the personal conversation on top during editing with a slight delay — maybe half a beat behind where the hands actually were. That small offset created the dissonance that made it feel authentic instead of rehearsed. It saved the project.