How Contact Tracing Actually Works in the Field
The Silent Spread Decoding The Chain Of Communicable Disease
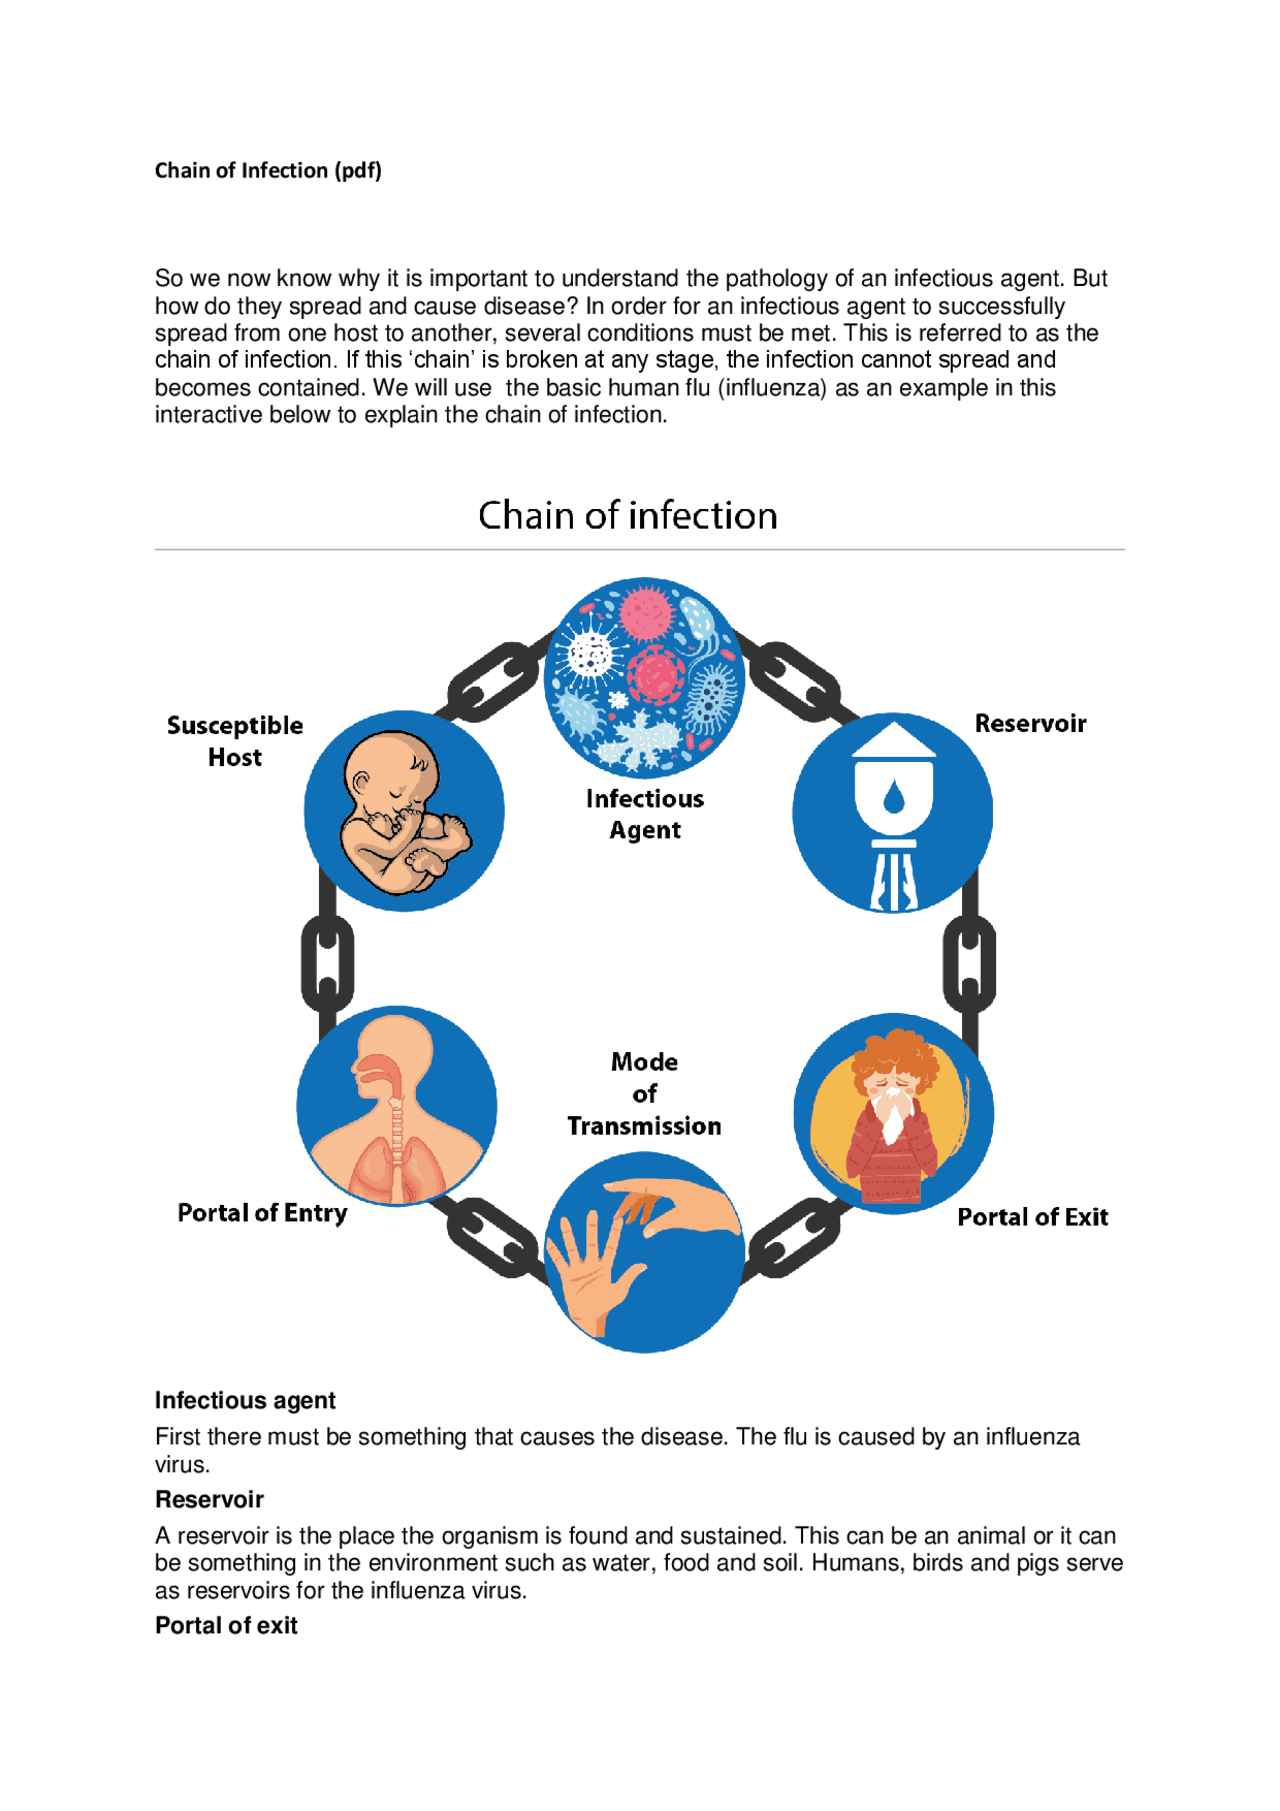
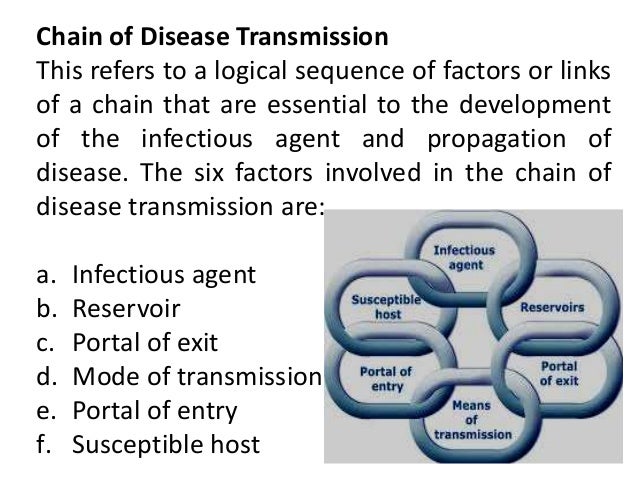
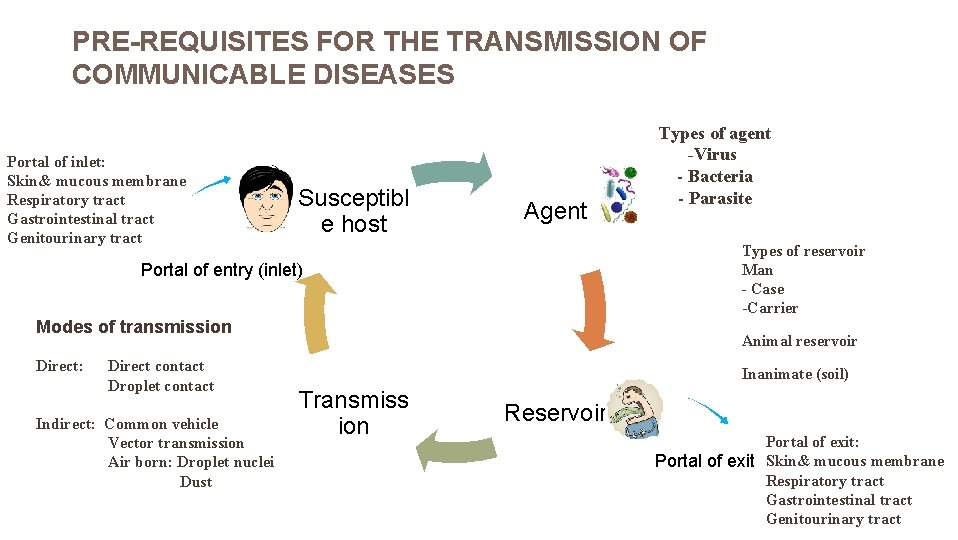
Contact tracing is not the dramatic TV version of it. It is mostly phone calls, note-taking, and trying to reconstruct a timeline from people who may not remember details accurately. The core idea is straightforward: find the person who was infected, identify everyone they were close to while infectious, notify those people, and break the chain. The reality of doing this repeatedly over the years involves dealing with memory gaps, unwillingness to cooperate, and the sheer volume of connections a single case can generate. I learned early on that the chain of transmission is rarely a neat line. It branches. It loops back. One person can seed dozens of secondary cases across entirely different social clusters without those clusters ever overlapping. This is what people mean by the silent spread—the period where cases appear without any clear link to a known source. Here is how you decode it.
Step one is defining the infectious period for the specific pathogen. That varies. Respiratory viruses typically have a window starting one to two days before symptoms appear and lasting through the first several days of illness. For some diseases, asymptomatic carriers play a role. For others, they do not. You need to know which applies before you start interviewing a case. Step two is the index case interview. This is where most programs stumble. You are asking someone who may be sick, stressed, or suspicious to recall every interaction over a multi-day window. The questions matter. Asking "who did you see?" produces vague answers. Asking "what did you do Tuesday morning? Where did you go? Who were you with?" produces usable data. Location, duration, and proximity are the three variables that determine whether an exposure counts. Proximity is the one beginners consistently underestimate. Sharing indoor air for twenty minutes matters more than a brief outdoor encounter. Ventilation, masks, and whether both people were speaking loudly all shift the risk profile. I once worked a case where a confirmed positive had met a contact outdoors for roughly four minutes while both were masked. We flagged it as low-risk. Two weeks later, that contact tested positive. The only common factor was a crowded grocery store they had both visited separately on the same day. The outdoor encounter was irrelevant. The lesson was simple: cast the net wider on common shared spaces, not just direct interactions.
Step three is identifying and prioritizing contacts. Not all contacts are equal. A household member facing prolonged indoor exposure ranks far above a cashier interaction lasting under two minutes. Triage separates urgent follow-ups from the large pool of lower-priority contacts. Programs that treat every contact the same either burn out their staff or miss the high-risk ones entirely. Here is the part nobody warns you about. Asymptomatic and presymptomatic spread is real and it changes the timeline. By the time someone tests positive, they may have already been transmitting for days. Relying on symptom onset as your anchor point will always miss exposures that happened before the case felt ill. The workaround is to ask about activities during the full infectious window, not just after symptoms started. In practice, this means going back further than feels natural.
Get the Full Details

I encountered a specific problem that came up repeatedly in dense urban settings. A case would report no close contacts, yet secondary infections kept appearing in the same neighborhood. The issue was shared ventilation and transit. People assumed they only counted interactions where they stood within six feet of someone. They did not account for the bus ride, the elevator, the doctor waiting room. These are harder to trace because there is no clean list of names. The workaround was pulling transit records where available, cross-referencing with other confirmed cases who had been in the same spaces at overlapping times, and issuing community notifications rather than individual ones for those shared-environment exposures. It is less precise but covers the gaps that individual interviews cannot. Notifications are the next step. This is where public trust becomes the limiting factor. If people believe the system will expose their behavior—whether it is illegal activity, immigration status, or social stigma—they will not cooperate. The notification itself should communicate what is known, what is not known, and what the contact should do next. Vague warnings create panic and noncompliance. Specific guidance reduces both. Quarantine and isolation recommendations depend on the pathogen and the local public health authority. Some jurisdictions require a set number of days. Others use a test-based strategy. The effectiveness of either approach hinges on whether the notified person actually follows the guidance, which circles back to trust and clarity.
Documentation is the unglamorous part that determines whether your work survives a review. Every contact identified, every risk assessment, every notification sent needs a record. The moment you rely on memory or informal communication channels, the chain becomes impossible to verify. Use a consistent template. Log dates, times, risk levels, and outcomes. If a second wave hits the same cluster months later, you need to be able to look back and see what was already checked. Counter-intuitive findings from experience. Digital contact tracing apps sound efficient. They are not a replacement for manual tracing. They capture a narrow slice of exposures—mostly phone proximity—and miss the majority of transmission routes. They also require adoption rates that most populations never reach. The best use of these tools is supplementary, not primary. I have seen programs overinvest in app data and underinvest in the interviews that actually uncover household transmission chains.
Another thing that surprises people: the majority of transmissions often come from a minority of cases. Superspreading events are not rare. A single infected person at a crowded indoor gathering can account for more secondary cases than dozens of routine interactions combined. Focusing resources on high-density indoor events during an outbreak yields more returns than chasing every minor contact downstream. There are limits to what contact tracing can do. It fails when the infectious period is too long relative to the detection delay. It fails in populations where people move frequently and leave the area before notification reaches them. It fails when there is no testing infrastructure to confirm whether a contact actually became infected. In these scenarios, broad public health measures—ventilation improvements, masking guidance, community testing—become more effective than tracing alone. If you are building a program or studying how these systems work, start with the pathogen-specific parameters. Understand the incubation period, the infectious period, the proportion of asymptomatic spread, and the typical transmission routes. The methodology stays the same, but the execution changes dramatically between a respiratory virus and a blood-borne pathogen. Treating them identically is a fast way to waste time and miss cases.
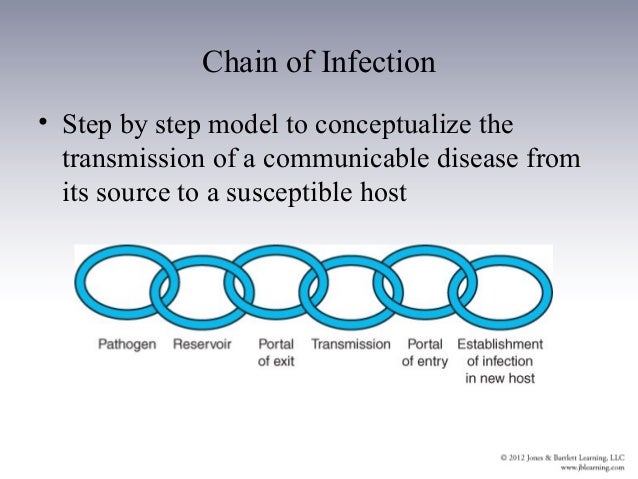
The work is repetitive and detail-heavy. It rewards patience more than speed. The people who do it well are the ones who treat each case as a puzzle with missing pieces rather than a checklist to complete. The chain breaks where the weakest link is found, and finding it usually requires looking past what the case reports and examining the environment instead.