
Perioperative Hourly Rounds: A Practical Guide
Hourly rounding used to be something we did because a policy said so. Now it's something we do because I've watched three surgeons ignore a dropping blood pressure trend for forty minutes straight when they weren't checking on their patient, and I've watched another catch a developing compartment syndrome issue because someone actually looked at the limb once an hour instead of waiting for a formal assessment. The difference between those two cases isn't magic. It's frequency of attention. Let me start with how this actually plays out on a real ward, not how the quality improvement department describes it. Your shift starts. You have six post-op patients from different surgeries. Instead of doing a comprehensive workup on everyone at the top of the hour and then forgetting about them for the next sixty minutes, you walk your floor every sixty minutes and hit each room. Three minutes per patient. Vital signs check. Incision look. Pain assessment. Line and drain check. Ability to void. Neuro status for spine cases. That's it. The format matters less than the consistency. I've seen paper checklists, EHR prompts, whiteboard updates, and nothing at all work. What doesn't work is skipping hours because the shift felt manageable. That's when the complications that hide in quiet periods show up. Hypovolemia after hip replacements. Early sepsis signals in abdominal cases. Urinary retention that could've been caught with a simple bladder scan instead of a catheter reinsertion at 2 AM.
What Actually Gets Caught
Here's the counter-intuitive part most people miss. Hourly rounds don't really catch the dramatic, life-threatening emergencies. The code blues and hemorrhages tend to announce themselves loudly enough. What hourly rounding actually catches are the slow drifts. The sodium creeping up in a trauma patient because the resuscitation fluid choice wasn't adjusted. The oxygen saturation ticking down from 96 to 93 over four hours on a general surgery patient who just looks tired. The abdominal distension building quietly in someone who hasn't passed flatus and nobody bothered to ask about it until they were vomiting. These are the complications that show a trend before they show a crisis. One data point is noise. Four data points in an hour is a pattern you can act on.
The Workflow
Start with a patient list and a route. Clock in at the top of the hour. Walk your designated path. Use a standardized set of checkpoints so you're not improvising what to look for each time. Document in real time if your EHR allows it, or use a pocket card and transfer notes within ten minutes of completing your round. End the hour by reviewing any flagged items and deciding who needs an immediate page versus a follow-up on the next round. I found that carrying a small card with the rounding checklist prevented me from forgetting steps when I was tired. Writing it down every time slowed me past a reasonable pace. The card stayed in my pocket for a full twelve-hour shift. When the hospital moved to barcode scanning for medication administration, we had to adapt. Added about ninety seconds per patient. Still faster than what we were doing before.
Get the Full Details
A Specific Problem I Dealt With
Last year we had a cardiac surgery patient on our floor. Blood pressure was borderline low all morning but trending within what looked like acceptable range on each hourly check. Nothing triggered a rapid response. Then at 3 AM the patient went into shock. The attending was confused why no one had escalated this. I pulled the hourly rounding logs and showed the trend. Systolic had dropped from 118 at midnight to 94 by 2 PM, but nobody connected it because each individual reading looked fine. We rewrote the rounding protocol to require noting the directional trend, not just the single number. Now the checklist includes a column for comparing to the previous hour. It's a small change but it caught two more deteriorating patients in the following month before they became emergencies. Rounds become a checkbox exercise when leadership treats compliance like the goal instead of outcomes. If you walk through rooms without actually looking at anything, you're not doing hourly rounds. You're performing presence. I've seen nurses clock in and clock out of patients in under thirty seconds. The patient was unconscious from oversedation and nobody noticed because the vitals on the monitor looked stable and the rounder never entered the room. Another problem is staffing. You cannot do meaningful hourly rounds with a nurse-to-patient ratio above four on a surgical floor. The math doesn't work. Sixty minutes divided by five patients gives you twelve minutes each including documentation and transit. That's enough time to skip actual assessment. I've worked both ratios and the difference in complication recognition was stark.
There's also the issue of night shift coverage. Most hospitals do hourly rounding during the day. Nights become a blind spot. Patients deteriorate fastest overnight and staffing is thinnest. If you're implementing this protocol, insist on night shift compliance at the same standard. We lobbied for mandatory hourly rounds on nights after a preventable cardiac arrest on the step-down unit. The union pushed back on staffing costs. We compromised on mandatory rounding every two hours on nights with bare minimum staffing, but I still think two hours is too long for a deteriorating post-op patient.
When It Doesn't Work
Hourly rounding is not a substitute for skilled clinical assessment. It won't catch deep vein thromboses in the early stages. It won't identify surgical site infections before they're clinically apparent. It won't replace the value of a senior surgeon's morning walk-through with institutional knowledge about which patients are high risk based on comorbidities and intraoperative course. It's a safety net, not a diagnostic tool. Think of it as early warning, not definitive evaluation. ICU patients don't need traditional hourly rounding. They're continuously monitored. What they need is something different. Bedside handoff between nurses every shift, family communication updates, and protocol-driven assessments. The hourly walk-through is designed for step-down and general surgical floors where monitoring is intermittent.
Getting Started
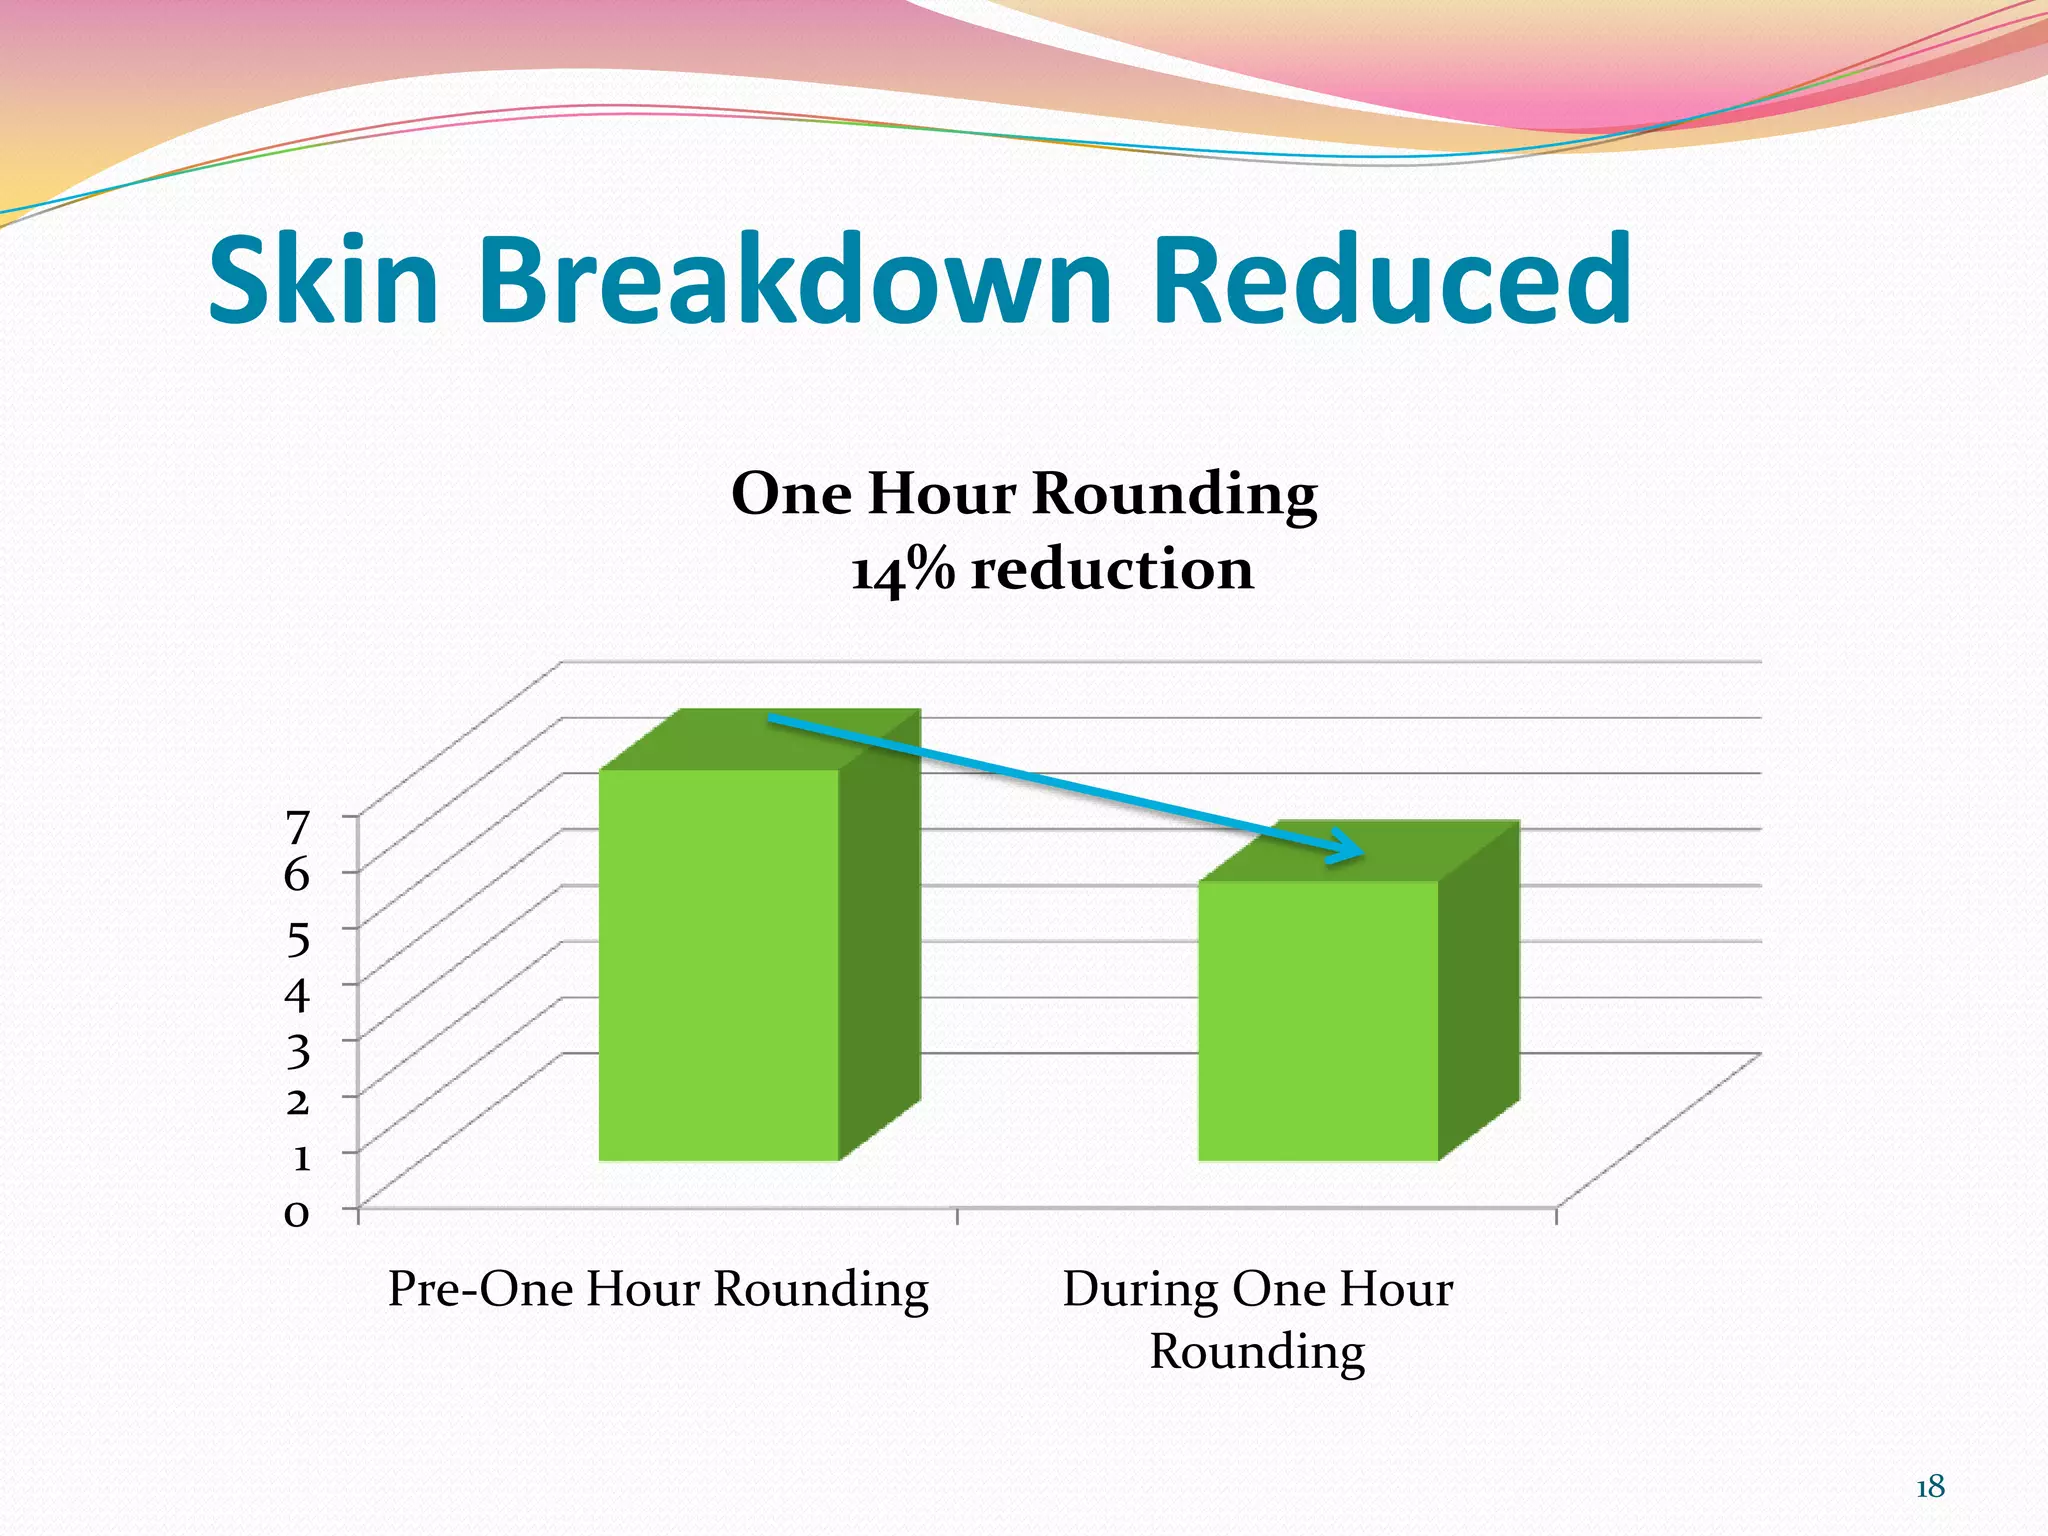
If your unit isn't doing structured hourly rounds yet, start with a pilot. Pick one ward. Run it for thirty days. Track complications that were caught in the first two hours of detection versus what used to happen when things were noticed only during scheduled assessments. Measure length of stay changes. Monitor patient satisfaction scores. Present the data to administration with actual numbers, not anecdotes. The initial pushback will come from staff who view it as extra work. Frame it as preventing the extra work of managing a codes and rapid responses. Show them the data from other units if you can find it. Most hospitals that implement this see a measurable reduction in unexpected transfers to the ICU within the first quarter. I've been around long enough to remember when we just checked on patients when something seemed wrong. The problem with that approach is that something usually seems wrong only after it's already serious. Hourly rounding changes the timeline. It moves detection earlier. It's not glamorous work. It's not exciting. But the outcomes speak for themselves.



