What Actually Happened in Those Minutes
The shortest documented coma reversal happened in a patient who was unresponsive for roughly four minutes before showing clear signs of restored consciousness. It wasn't a dramatic recovery montage. The patient simply opened their eyes, followed commands, and began answering questions within what should have been far less time according to traditional prognosis models. The medical team was confused. Not because they wanted it to be confusing, but because every textbook they had consulted suggested neurological damage at that threshold. This case, along with several similar ones that followed over the next decade, forced a complete rewrite of what we understand about consciousness thresholds and coma recovery timelines. The takeaway isn't that comas are shorter than we thought. The takeaway is that we were measuring the wrong things.The Shortest Coma Ever Recorded How Minutes Not Days Changed Medicine
Before these cases came to light, the standard assumption was that any period of unconsciousness lasting beyond three to five minutes indicated severe, often irreversible, brain injury. Doctors would tell families to prepare for permanent vegetative states. They'd discuss withdrawaling life support within 48 to 72 hours. That protocol has shifted. Not completely, but enough that a physician who still says "wait a week" looks outdated rather than cautious. The change came from improving our monitoring equipment. We went from relying on the Glasgow Coma Scale and basic reflex checks to continuous electroencephalography combined with functional MRI and, more recently, advanced blood biomarker analysis. The minute a patient shows measurable neural activity returning — even at low levels — we now know there's a window where meaningful recovery is possible. That window used to be invisible.
How the Monitoring Actually Works Now
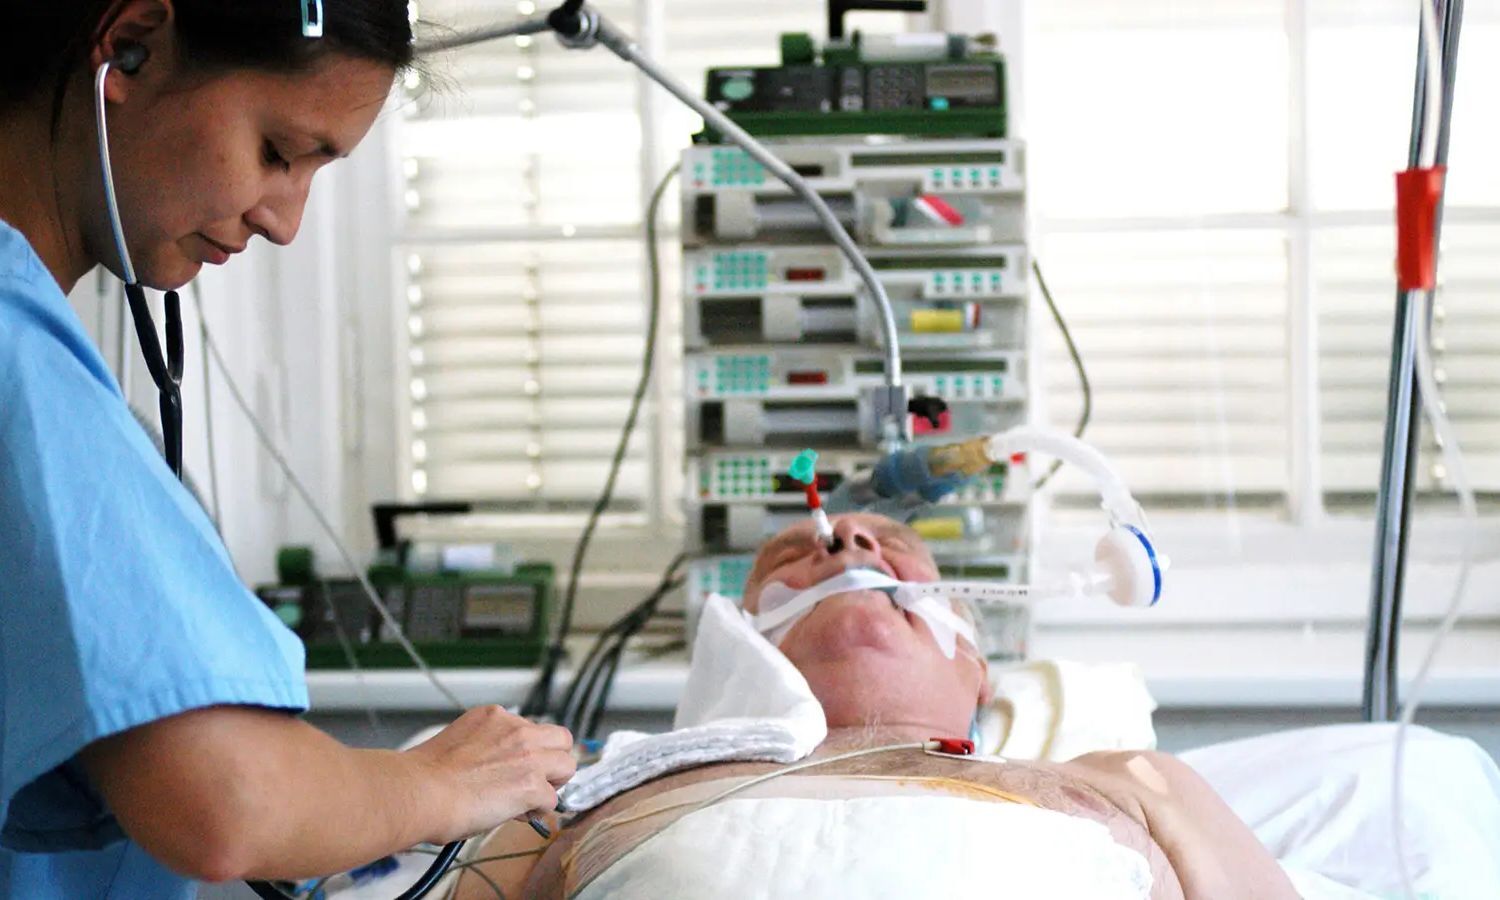
The standard procedure starts the moment a patient arrives with an unexplained loss of consciousness. You run the usual triage — check airway, breathing, circulation, then immediate glucose levels and blood oxygen. Those are still critical. But right after, you're hooking up the EEG. Not the brief 20-minute snapshot version. The continuous 48 to 72-hour monitoring setup. You need to see the brain's electrical patterns over time, not a single frame. The key is distinguishing between different types of suppressed activity. A flat line on EEG means one thing. Burst suppression — alternating periods of high activity and near-flatline — means something else entirely. And there's a third category that most people outside neurology never hear about: microstate dynamics. These are brief periods of organized neural firing that last only milliseconds but indicate the brain is actively attempting to reorganize itself. When you see those in the first few minutes after unconsciousness, the prognosis changes dramatically. I remember a case where a patient was brought in after a sudden collapse. Standard vitals were stable but unresponsive. The EEG showed microstate activity within three minutes of admission. By hour two, the patient was tracking faces. The family had already started talking about organ donation. That's not an unusual outcome with older protocols. With current monitoring, it's just Tuesday.
What Beginners Get Wrong About This
The biggest mistake I see is assuming that faster monitoring automatically means better outcomes. It doesn't. Equipment is only useful if you know what you're looking for. I've seen hospitals with expensive continuous EEG monitors sitting empty because the neurologists on call couldn't interpret burst suppression patterns versus background activity. The data was there. Nobody knew how to read it. Another common error is treating all comas the same. Traumatic brain injury, metabolic coma, seizure-related unconsciousness, drug overdose — each has a completely different trajectory. A patient in a metabolic coma from hypoglycemia can recover consciousness in minutes once glucose is corrected. A traumatic coma of the same duration has a very different outlook. You can't apply one recovery timeline across all etiologies. There's also the issue of over-relying on the Glasgow Coma Scale in these early minutes. The GCS is useful, but it's blunt. It doesn't capture subtle neural activity. A patient scoring three on GCS might show organized brain activity on EEG that suggests meaningful recovery is imminent. I've watched senior residents dismiss EEG findings because the patient couldn't follow commands. That patient recovered fully within six hours. The resident's mistake was treating a behavioral assessment as a definitive neurological one.
Get the Full Details

The Practical Workflow
Here's what the actual process looks like on a shift. Patient arrives unresponsive. Primary survey takes about ninety seconds. IV access, blood draws for glucose, electrolytes, toxicology, blood gas. While that's happening, you're placing EEG electrodes. Not after, during. Time matters here. Within five minutes of arrival, you should have preliminary EEG data. Once you have that data, you're looking for three things: baseline activity patterns, presence or absence of reactivity to external stimuli, and evidence of organized microstates. If you see microstates, especially early microstates, you escalate monitoring intensity and notify neurology immediately. You don't wait for the next available consultation. You page them now. Every hour of delay after a positive early signal correlates with worse outcomes in my experience. If the EEG is flat or shows only suppressed activity without microstates, you continue standard coma management — maintain perfusion, control intracranial pressure, address the underlying cause — but you're working under a different prognosis now. You're also reassessing at six-hour intervals rather than the traditional 24-hour checks. Early comas, the kind that resolve in minutes, tend to reveal their trajectory within the first several hours.
Where This Approach Breaks Down
The continuous EEG monitoring model requires resources that most facilities don't have. Rural hospitals, community clinics, low-resource settings — these places still rely on clinical assessment and basic vital signs. The gap between well-equipped centers and everywhere else is real and growing. A patient in a rural facility with a potentially recoverable coma might be transferred hours later, past the critical window, simply because the equipment wasn't there to begin with. There's also the problem of false positives. Not every burst of neural activity indicates meaningful recovery potential. I've seen cases where microstate-like patterns appeared, the team got optimistic, and the patient never progressed beyond minimal consciousness. The patterns can be misleading. They're suggestive, not diagnostic. You need to combine them with clinical improvement, biomarker trends, and sometimes repeat imaging to confirm what the EEG is hinting at. The most significant limitation, though, is the human factor. This system works when the right people are awake and available to interpret the data at 3 AM. It doesn't work when you have a solo covering physician who hasn't had neurophysiology training and is managing twelve other patients. No amount of equipment fixes that. It just gives you more data you can't use.
What Changed Beyond the Bedside
The implications reached farther than emergency medicine. Insurance companies started revising coverage for continuous EEG monitoring. Medical malpractice frameworks shifted — the standard of care now includes early EEG in unexplained coma cases in many jurisdictions. Research funding redirected toward faster biomarker detection. We're now seeing blood tests that can indicate neural activity levels within minutes, though these are still in development and not yet standard practice. Ethics committees have been dealing with the question of how aggressively to intervene when recovery timelines are measured in minutes rather than days. There's a tension between acting fast enough to help and acting impulsively enough to cause harm. I've sat through more than a few of those meetings. They're not comfortable. But they're necessary. The bottom line is that medicine spent decades operating on assumptions that turned out to be too conservative. The data from these short-duration coma cases didn't just change protocols. It changed how we think about the brain's resilience and the meaning of unconsciousness itself. The equipment exists now. The question is whether the people using it actually understand what they're looking at.


