Understanding Pelvic Anatomy: True Versus False Pelvis Explained
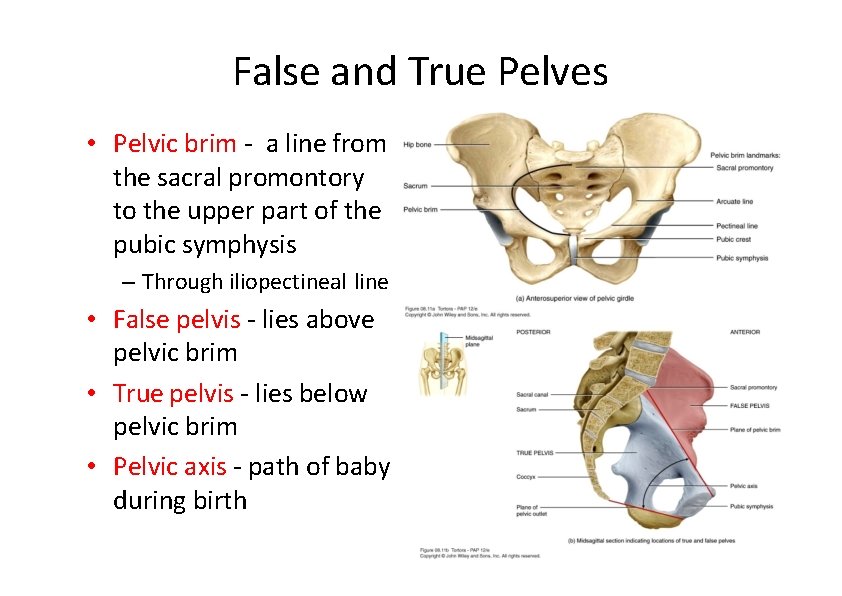
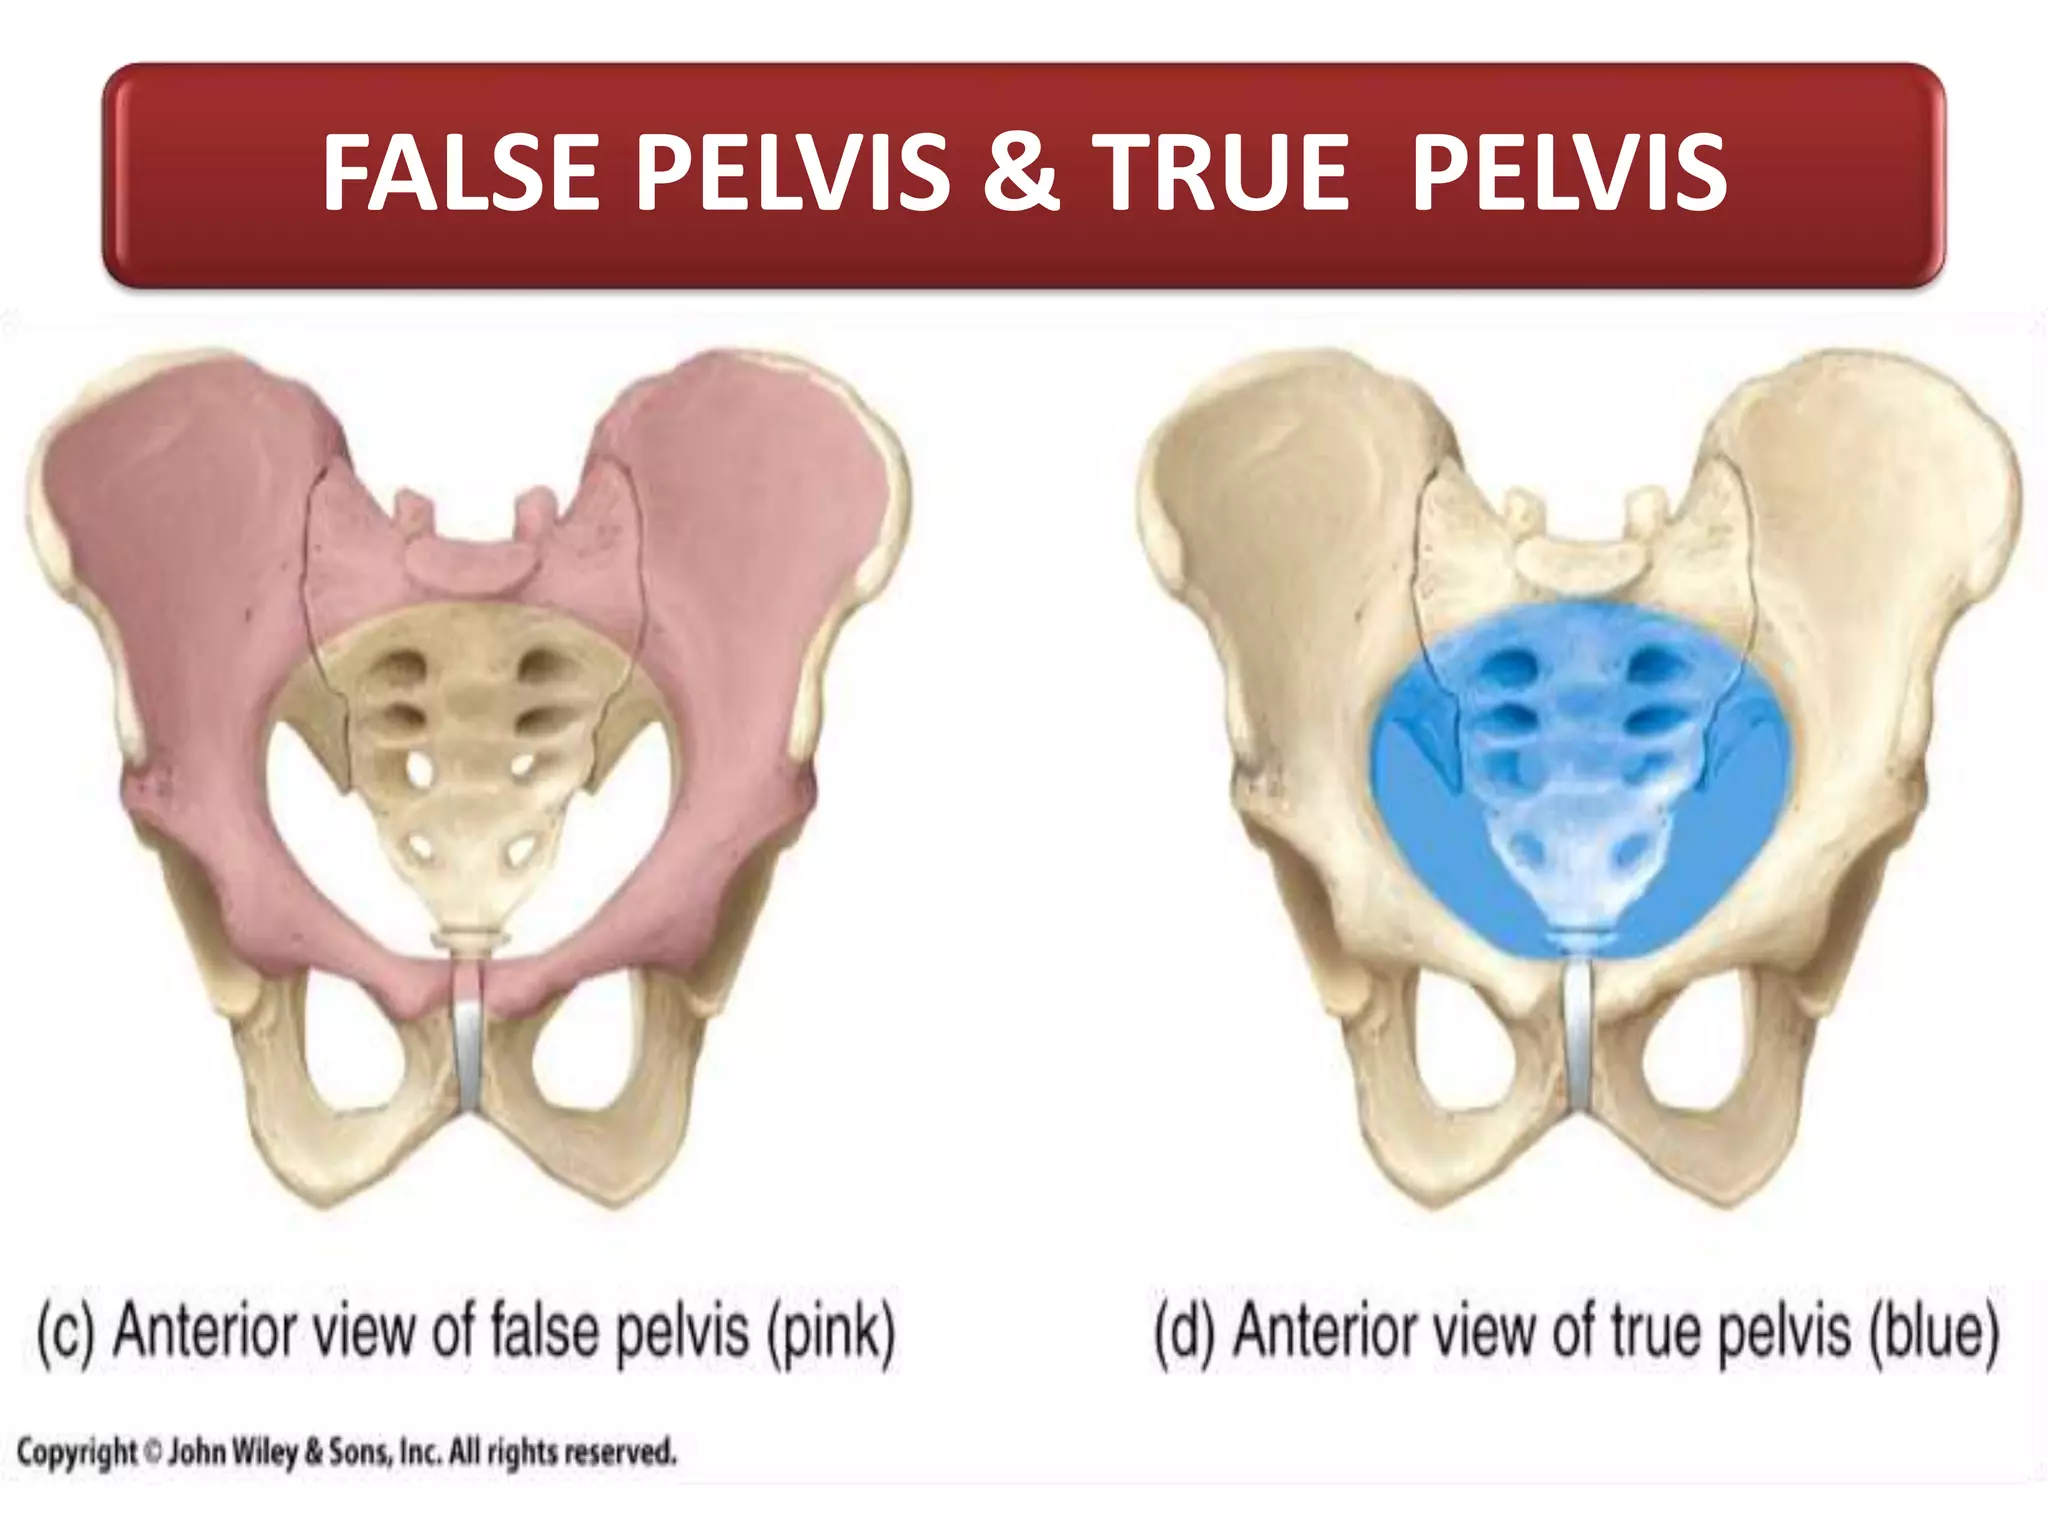
The pelvis is one of those body parts you don't think about until something goes wrong with it. Most people carry around vague ideas about hip dips, pelvic tilts, and whether their pelvis is "wide" or "narrow" without understanding the actual anatomy underneath. There is a real distinction between the true pelvis and the false pelvis, and it matters more than you might expect if you deal with lower back pain, posture issues, or even pregnancy-related discomfort. Here is what most fitness influencers and even some healthcare providers skip when they talk about pelvic shape. The false pelvis, also called the greater pelvis, is the upper, broader part that sits above the pelvic brim. It is essentially formed by the flared iliac bones and provides attachment points for your abdominal muscles. The true pelvis, or lesser pelvis, is the lower, funnel-shaped cavity below that brim. It houses your reproductive organs, bladder, and rectum. The boundary between them is the linea terminalis, a ring of bone you can feel if you press deeply into your lower abdomen near the hip bones. I learned this the hard way about three years ago. A physical therapist I worked with kept referencing my "false pelvis width" when discussing my anterior pelvic tilt, and I realized I had no idea what she was actually measuring. Turns out she was assessing the bi-iliac diameter, which is a standard anthropometric measurement used in obstetrics and ergonomics. The confusion was not trivial. Many people conflate pelvic tilt (anterior or posterior) with pelvic width or shape, and these are completely separate things. You can have a narrow true pelvis with a neutral pelvic tilt, or a wide false pelvis with significant anterior rotation. Mixing them up leads to wrong exercises, wrong braces, and sometimes worse outcomes.
How Pelvic Structure Actually Affects Movement and Pain
The true pelvis has what anatomists call the pelvic inlet and outlet. The inlet is the opening at the top, bounded by the sacrum posteriorly and the pubic symphysis anteriorly. The outlet is the lower opening, framed by the ischial tuberosities and the coccyx. These measurements determine things like vaginal delivery feasibility in obstetrics, but they also influence how your legs sit relative to your hips. A narrower true pelvic outlet can change your femoral angle, which cascades into knee and ankle alignment issues. Here is a counter-intuitive point that beginners usually miss. Pelvic width, the kind you see in women versus men broadly speaking, is largely determined by the false pelvis, specifically the flared iliac blades. But functional pelvic stability comes from the true pelvis and the surrounding musculature, especially the pelvic floor, transverse abdominis, and deep hip rotators. You can have wide hip bones and still have a poorly stabilized pelvis. Conversely, someone with narrow iliac wings can have excellent pelvic control through targeted training. The shape does not dictate the function as directly as marketing material would have you believe. I ran into a specific edge case working with a runner who had chronic anterior pelvic tilt and lower back pain. She had been told for years that her "narrow pelvis" was the problem and that she needed to widen her hip bones through exercises, which is anatomically impossible in adulthood since the iliac bones fuse by around age twenty-five. The actual issue was weak gluteal activation and overactive hip flexors, a common pattern in sedentary populations. We spent six weeks focusing on glute bridges, dead bugs, and hip flexor stretches rather than trying to change bone structure. Her pain dropped significantly within eight weeks, and her running cadence improved by roughly four percent, which is meaningful over a fifty-kilometer race.
Pelvic Assessment: What You Can Actually Measure at Home
You do not need specialized equipment to get a rough sense of your pelvic position. The wall test is the simplest method. Stand with your back against a wall, heels about six inches away, and notice the gap between your lower back and the wall. A gap larger than your hand thickness often suggests anterior pelvic tilt. A gap that is essentially zero or negative, meaning your lower back is pressed flat against the wall, may indicate posterior tilt. This is not diagnostic, but it gives you a baseline. Another practical check involves theASIS, the anterior superior iliac spines you can feel as the bony prominences at the front of your hips. Have someone look at you from the front while you stand neutrally. If one ASIS sits noticeably higher than the other, you may have a lateral pelvic tilt, often caused by leg length discrepancy or unilateral muscle tightness. This asymmetry is common, affecting roughly thirty to forty percent of the population to some degree, and usually resolves with targeted stretching and strengthening. The limitation here is that self-assessment has a margin of error of about plus or minus five degrees for tilt angle. If you are dealing with persistent pain, neurological symptoms, or injury recovery, professional assessment using goniometers or digital inclinometers is worth the cost. A physical therapist or osteopath can measure your pelvic tilt within one or two degrees of accuracy, which matters when tracking progress over months of rehabilitation.
Get the Full Details

Common Pitfalls in Pelvic Health Advice
The wellness industry has a habit of turning anatomical concepts into product categories. Pelvic tilts became exercises, pelvic floor training became a billion-dollar market, and pelvic bycles or seats are marketed as solutions for sitting-related discomfort. None of these are inherently bad, but they are often oversold. A pelvic tilt exercise will not change your bone structure. A pelvic floor trainer will not fix core weakness. And sitting on a bycle is not a substitute for proper chair ergonomics if your workspace is set up incorrectly. One dangerous myth is the idea that you can "correct" your pelvis into a permanent neutral position through exercises alone. Pelvic position is dynamic, changing with breathing, movement, and even time of day. Your pelvis tilts slightly forward when you inhale deeply due to diaphragm descent, and this is normal. Trying to hold a static "neutral" position for hours can create new problems, including muscle fatigue and restricted breathing. The goal should be mobility and control across ranges, not a fixed pose. Another overlooked point is the relationship between pelvic position and rib cage alignment. Many people focus exclusively on the pelvis while ignoring thoracic posture. A forward head posture and rounded shoulders often accompany anterior pelvic tilt, creating a kinetic chain issue. Addressing only the pelvis without considering the upper body can lead to incomplete recovery. I saw this repeatedly in a clinical setting, where patients would improve their pelvic tilt but still complain of neck and shoulder pain because their scapular stabilizers were never trained.
Practical Recommendations Based on Your Situation
If you are dealing with lower back pain, the first step is not to buy a pelvic belt or start an intense core routine. It is to assess whether your pain correlates with specific movements. Does bending forward relieve it? Does standing for long periods worsen it? These clues help distinguish between mechanical issues, such as disc-related pain, and muscular imbalances, which are far more common in desk workers. For general pelvic health maintenance, a simple routine takes about ten minutes daily. Include hip flexor stretches on both sides, glute bridges with a three-second hold at the top, bird dogs for core stability, and deep breathing to engage the pelvic floor naturally. Consistency matters more than intensity. Doing this routine three to four times per week for eight weeks produces measurable improvements in pelvic control for most healthy adults, according to published physical therapy studies. Specific populations need different approaches. Pregnant individuals should focus on pelvic floor relaxation rather than strengthening, as excessive tightness can complicate delivery. Athletes in power sports benefit from pelvic stability work to transfer force efficiently between upper and lower body. Older adults should prioritize balance training that challenges pelvic control, reducing fall risk by improving proprioception.
The takeaway is straightforward. Your pelvis is more complex than simplified fitness content suggests. Understanding the difference between true and false pelvis, recognizing that shape and position are separate variables, and avoiding the trap of thinking exercises can reshape adult bone structure will save you time, money, and unnecessary frustration. If problems persist beyond four to six weeks of consistent self-care, seek professional evaluation rather than escalating your routine blindly.