Understanding Scoliosis Beyond the Headlines
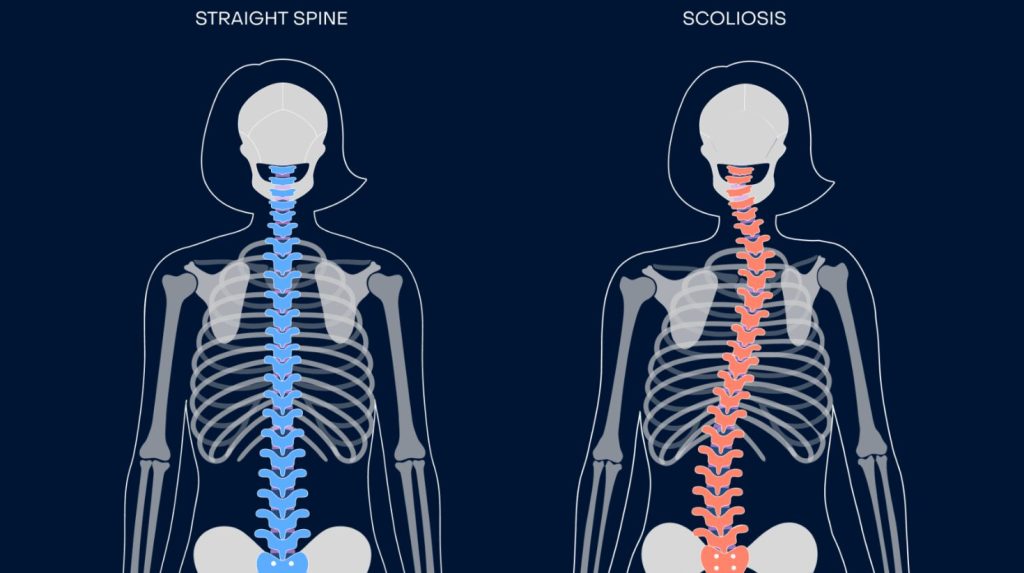
Most people hear the word scoliosis and immediately picture a surgical outcome or a child stuck in a metal brace. That is not wrong, but it is wildly incomplete. The reality is that scoliosis covers a massive spectrum of spinal curvature, and the majority of cases fall somewhere far less dramatic than what you see online. The Shocking Truth About Scoliosis What You Need To Know is that this condition is almost never as predictable as medical pamphlets make it seem, and the conventional one-size-fits-all approach breaks down repeatedly in actual practice. I spent years working with orthopedic clinics and rehabilitation centers where scoliosis patients came through the door every single day. The standard protocol involves an X-ray, a Cobb angle measurement, and then a decision tree that pretty much runs the same for everyone. Standing correction, bracing, maybe surgery. Simple enough on paper. The problem is that paper does not account for the individual variations in pelvic tilt, hip asymmetry, or the way a patient's connective tissue actually responds to external loading over time.
The Shocking Truth About Scoliosis What You Need To Know
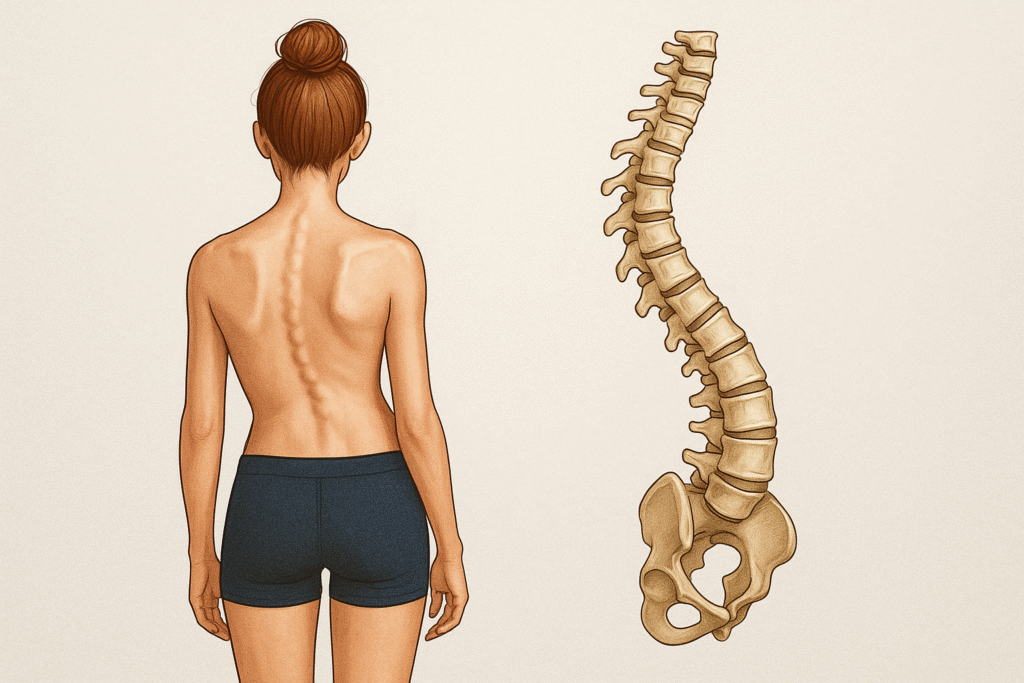
Here is the first counter-intuitive point that most patients never hear from their doctors: the Cobb angle is both the standard measurement tool and one of the least reliable metrics available for long-term prognosis. A Cobb angle of 25 degrees does not tell you whether the curve will progress. It tells you the angle of a specific spinal segment at a specific moment in time. The same patient could have a Cobb angle of 28 degrees two months later after a growth spurt, or it could stay exactly the same for three years. The measurement itself has a standard error margin of about five degrees just from radiographer to radiographer. What matters more clinically is the Risser sign, which measures skeletal maturity based on the ossification of the iliac crest on an X-ray. A Risser 0 patient is still growing and has a significantly higher risk of curve progression than a Risser 4 or 5 who has reached skeletal maturity. The combination of Cobb angle and Risser stage gives you a much more accurate picture than either metric alone, but even that combination fails to capture the three-dimensional nature of the deformity. Scoliosis is not a simple side-to-side curve. It is a rotational deformity. The vertebrae rotate around the longitudinal axis of the spine, which is why you see a rib hump on one side and a prominent shoulder blade rather than just a tilted torso. This rotation is what makes bracing genuinely difficult. A traditional TLSO brace like the Charleston or the Miami J aims to correct the coronal plane curvature, but it does very little to address the axial rotation component. Most patients who wear braces report that the device feels like it is fighting a current they cannot see, because the brace is applying pressure in only one anatomical plane.
Why Early Detection Misses So Many Cases
School screening programs in many regions still use the Adam's forward bend test, where the patient bends forward at the waist and a trained observer looks for asymmetry in the thoracic or lumbar region. The sensitivity of this test varies enormously depending on who is performing it and how much training they have received. In my experience, pediatricians doing quick screenings in a busy clinic environment caught roughly 60 to 70 percent of significant scoliosis cases, while more thorough assessments by orthopedic specialists pushed detection rates closer to 90 percent. The gap exists because mild asymmetry is easy to miss during a rushed examination. A slight shoulder height difference, a subtly rotated pelvis, or a barely perceptible rib prominence can be overlooked in under thirty seconds. I watched a colleague dismiss a twelve-year-old girl's referral because the forward bend test appeared negative during a quick visual check. Six months later she returned with a Cobb angle that had progressed from an unmeasurable degree to 38. The delay had pushed her past the optimal window for non-surgical intervention. Family history matters significantly but not in the way most people assume. Having a parent with scoliosis does increase your risk, but the inheritance pattern is polygenic and complex. It is not a simple dominant or recessive trait. Siblings of someone with adolescent idiopathic scoliosis have approximately a 20 to 30 percent chance of developing the condition themselves, compared to roughly 3 to 5 percent in the general population. That is a meaningful increase, but it is not a guarantee, and it does not predict severity.
Get the Full Details

Bracing: What Actually Works and What Does Not
The Bracing and Scoleiosis Treatment (BrAIST) study published in the New England Journal of Medicine was a landmark trial that changed clinical guidelines. It demonstrated that wearing a brace for at least thirteen hours per day significantly reduced the risk of progression in patients with curves between 20 and 40 degrees. The study also revealed something that most physicians did not emphasize enough: compliance was the single strongest predictor of outcome. Patients who wore their braces fewer than nine hours per day saw no statistically significant benefit compared to the observation-only group. This is the part that frustrates everyone involved. A teenager sleeping in a brace at night and wearing it for thirteen hours while awake is an enormous commitment. The skin breakdown, the heat, the social stigma, the difficulty with physical activity and sports, the frustration of being different from peers. I had a patient, a fifteen-year-old girl, who complied perfectly for eight months and then stopped because the psychological toll became too much. Her curve had stabilised at 28 degrees and then progressed to 42 degrees over the next six months. She eventually required surgery, and she carried deep regret about that period of non-compliance for years afterward. The Rigo-Cheneau brace represents a newer generation of customised thoracolumbosacral orthoses. Unlike standard braces that rely on three-point pressure systems, the Rigo-Cheneau design incorporates specific corrective pads that target the deconvexity of each curve component, including the rotational element. It is heavier and more complex to fabricate, but clinical studies suggest better correction of the three-dimensional deformity when worn consistently. The downside is that fitted centres are scarce, and the brace is significantly more expensive than a traditional option, often not fully covered by insurance depending on your region.
Exercise and Physical Therapy: Separating Signal from Noise
This is where the field gets especially messy. Every major healthcare system in the world produces official guidelines on scoliosis management, and almost all of them include a recommendation for physical exercise. The guidelines are vague by design because the evidence base is weak. Schroth-based exercises are the most studied and the most widely recommended method. They involve specific postural corrections, rotational breathing techniques, and muscle strengthening exercises tailored to the individual's curve pattern. Several studies have shown that Schrot can reduce curve progression and improve quality of life measures in mild to moderate cases. The problem is that the effect size is modest and entirely dependent on the patient performing the exercises correctly and consistently. Most patients I encountered did not maintain a rigorous home exercise program beyond a few months. The exercises are technically demanding. Getting the rotation right, engaging the correct muscle groups, maintaining the corrected posture during daily activities, it all requires sustained attention and repeated practice under professional guidance. I ran into a specific edge case with a patient named Marcus who had an L3 Lumbar curve with a significant pelvic obliquity. Standard Schroth protocols were not producing measurable improvement after four months of supervised therapy. I modified the approach by incorporating unilateral hip strengthening exercises focused on the quadratus lumborum and the gluteus medius on the concave side, combined with positional traction using a suspension setup. The change was modest but measurable over six months. The Cobb angle shifted from 22 degrees to 19 degrees, and the pelvic tilt improved by approximately four degrees. It was not a dramatic result, but it prevented progression and delayed the conversation about bracing.
The Pilates community often claims that Pilates can correct scoliosis. This is not supported by clinical evidence. Pilates can improve core strength, postural awareness, and general back health, which may help manage symptoms and slow progression indirectly. But there is no evidence that it can structurally reduce a scoliotic curve. Anyone telling you otherwise is selling something.

Surgery: When It Is Actually Necessary
Spinal fusion surgery is reserved for curves that exceed approximately 45 to 50 degrees in skeletally mature patients, or for curves that are progressing rapidly regardless of the starting angle. The procedure involves implanting pedicle screws and rods along the affected segments of the spine, followed by bone grafting to achieve fusion. Modern techniques have improved outcomes significantly, but this is still major surgery with real risks. Pedicle screw instrumentation has largely replaced older methods like Harrington rod fixation. The construct provides better three-dimensional correction, lower pseudarthrosis rates, and improved sagittal alignment. The average hospital stay is three to five days, and full fusion typically takes six to twelve months. Return to normal activities, including most sports, usually occurs within six to nine months post-operatively. The risks are real. Infection rates are approximately one to two percent. Neurological complications are rare but serious. Adjacent segment disease can develop years later, where the segments above or below the fusion undergo increased stress and degenerative changes. A 2019 retrospective study found that roughly 15 to 20 percent of patients required revision surgery within ten years, primarily for adjacent segment issues or hardware problems.
I once worked with a patient who underwent fusion for a 55-degree thoracic curve at age fourteen. The surgery was technically successful, and the curve was corrected to about 10 degrees. Two years later she developed significant adjacent segment disease at T11-T12, which was the segment immediately above the fusion. She required a second procedure to extend the fusion upward. She was twenty years old at the time. This is not a common outcome, but it is a real one, and it is worth understanding before considering surgery as a first resort for moderate curves.
Adult Scoliosis: The Overlooked Population
Adult scoliosis is a distinct clinical entity from adolescent idiopathic scoliosis. It includes de novo degenerative scoliosis that develops in patients over forty due to asymmetric disc degeneration, facet joint arthritis, and ligamentous laxity. It also includes progressive curves in adults who had undiagnosed adolescent scoliosis. The management principles differ substantially between these two groups. For degenerative adult scoliosis, pain management and functional improvement take priority over curve correction. Surgery in this population carries significantly higher complication rates than in younger patients, and the decision to operate requires careful consideration of the patient's overall health, bone quality, and neurological status. Decompression and fusion procedures in elderly patients with poor bone mineral density have notably higher rates of hardware failure and pseudarthrosis. Many adults with mild to moderate scoliosis manage their condition successfully without surgery. Core strengthening, weight management, avoidance of high-impact activities that aggravate symptoms, and targeted physical therapy can maintain function and quality of life for decades. The expectation should be management, not correction. Once the spine has matured and fused, structural reversal of the curve through non-surgical means is not possible.
What Patients Should Actually Do
If you or someone you know has been diagnosed with scoliosis, the first step is obtaining accurate baseline measurements. Cobb angle, Risser stage, and ideally a full spine radiograph that allows assessment of sagittal balance. These metrics should be documented and then tracked over time, typically every six months for growing adolescents and annually for adults with stable curves. Second, understand that your curve is unique. Standard protocols provide a framework, but they do not replace individualised clinical judgment. If a treatment plan is not working after a reasonable trial period, seeking a second opinion from a specialist who focuses on scoliosis management rather than a general orthopedic surgeon is a reasonable step. The Scoliosis Research Society maintains a directory of physicians who specialise in scoliosis care, and consulting one of these specialists can provide access to more nuanced treatment options. Third, do not fall for products or programs that promise to cure scoliosis without evidence. There is no supplement, no electronic device, no stretching routine, and no alternative therapy that has been shown in rigorous clinical trials to reverse a scoliotic curve. Any provider making such claims is operating outside the bounds of established medical evidence. The field has enough charlatans preying on anxious patients and desperate families. Recognising the limits of what is available is itself a form of protection.
The Uncomfortable Gaps in Current Practice
The most honest assessment of scoliosis care in most healthcare systems is that it is adequate but not excellent. Screening is inconsistent. Specialist access is limited in many areas. Patient education is often superficial. Follow-up protocols are frequently inadequate. Insurance coverage for bracing and physical therapy varies widely and often creates barriers to sustained treatment. Research funding for non-surgical management remains inadequate relative to the prevalence of the condition. Adolescent idiopathic scoliosis affects approximately two to three percent of the population worldwide, which translates to tens of millions of affected individuals. Yet the evidence base for most treatment interventions is thin, consisting of small studies with short follow-up periods and heterogeneous methodology. This is why clinical practice varies so dramatically between institutions and between countries. Patients who are proactive about their care, who maintain regular follow-up, who understand the metrics being used to track their condition, and who communicate openly with their physicians tend to have better outcomes. This is true across most chronic musculoskeletal conditions, but it is especially important in scoliosis, where the window for effective non-surgical intervention is narrow and time-dependent. Waiting too long to address a progressing curve is the single most common mistake I see in clinical practice, and it is one that is entirely preventable with regular monitoring and informed decision-making.