Understanding Cleft Lip and Cleft Palate: What Actually Happens
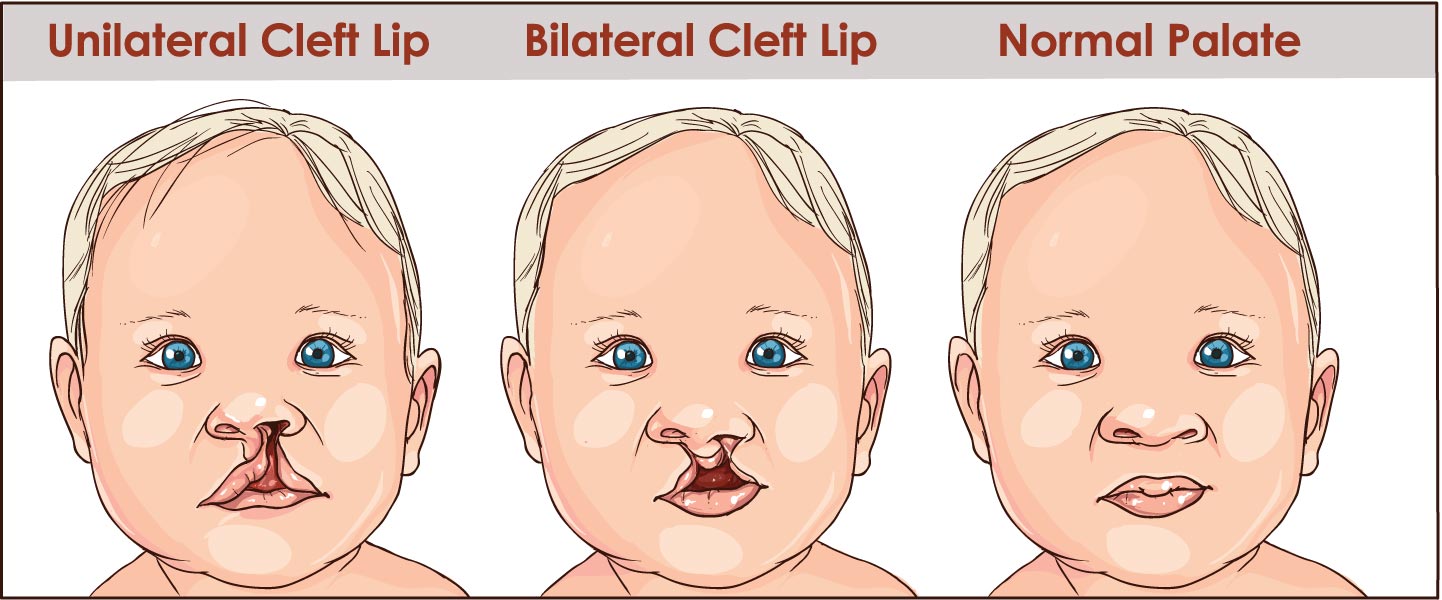
Cleft lip and cleft palate are birth defects that occur when a baby's lip or mouth doesn't form properly during pregnancy. They're more common than most people realize, affecting roughly 1 in 700 babies worldwide. The two conditions often occur together, but they're separate issues requiring different surgical approaches.
The Shocking Truth About Harelip And Cleft Palate What You Need To Know
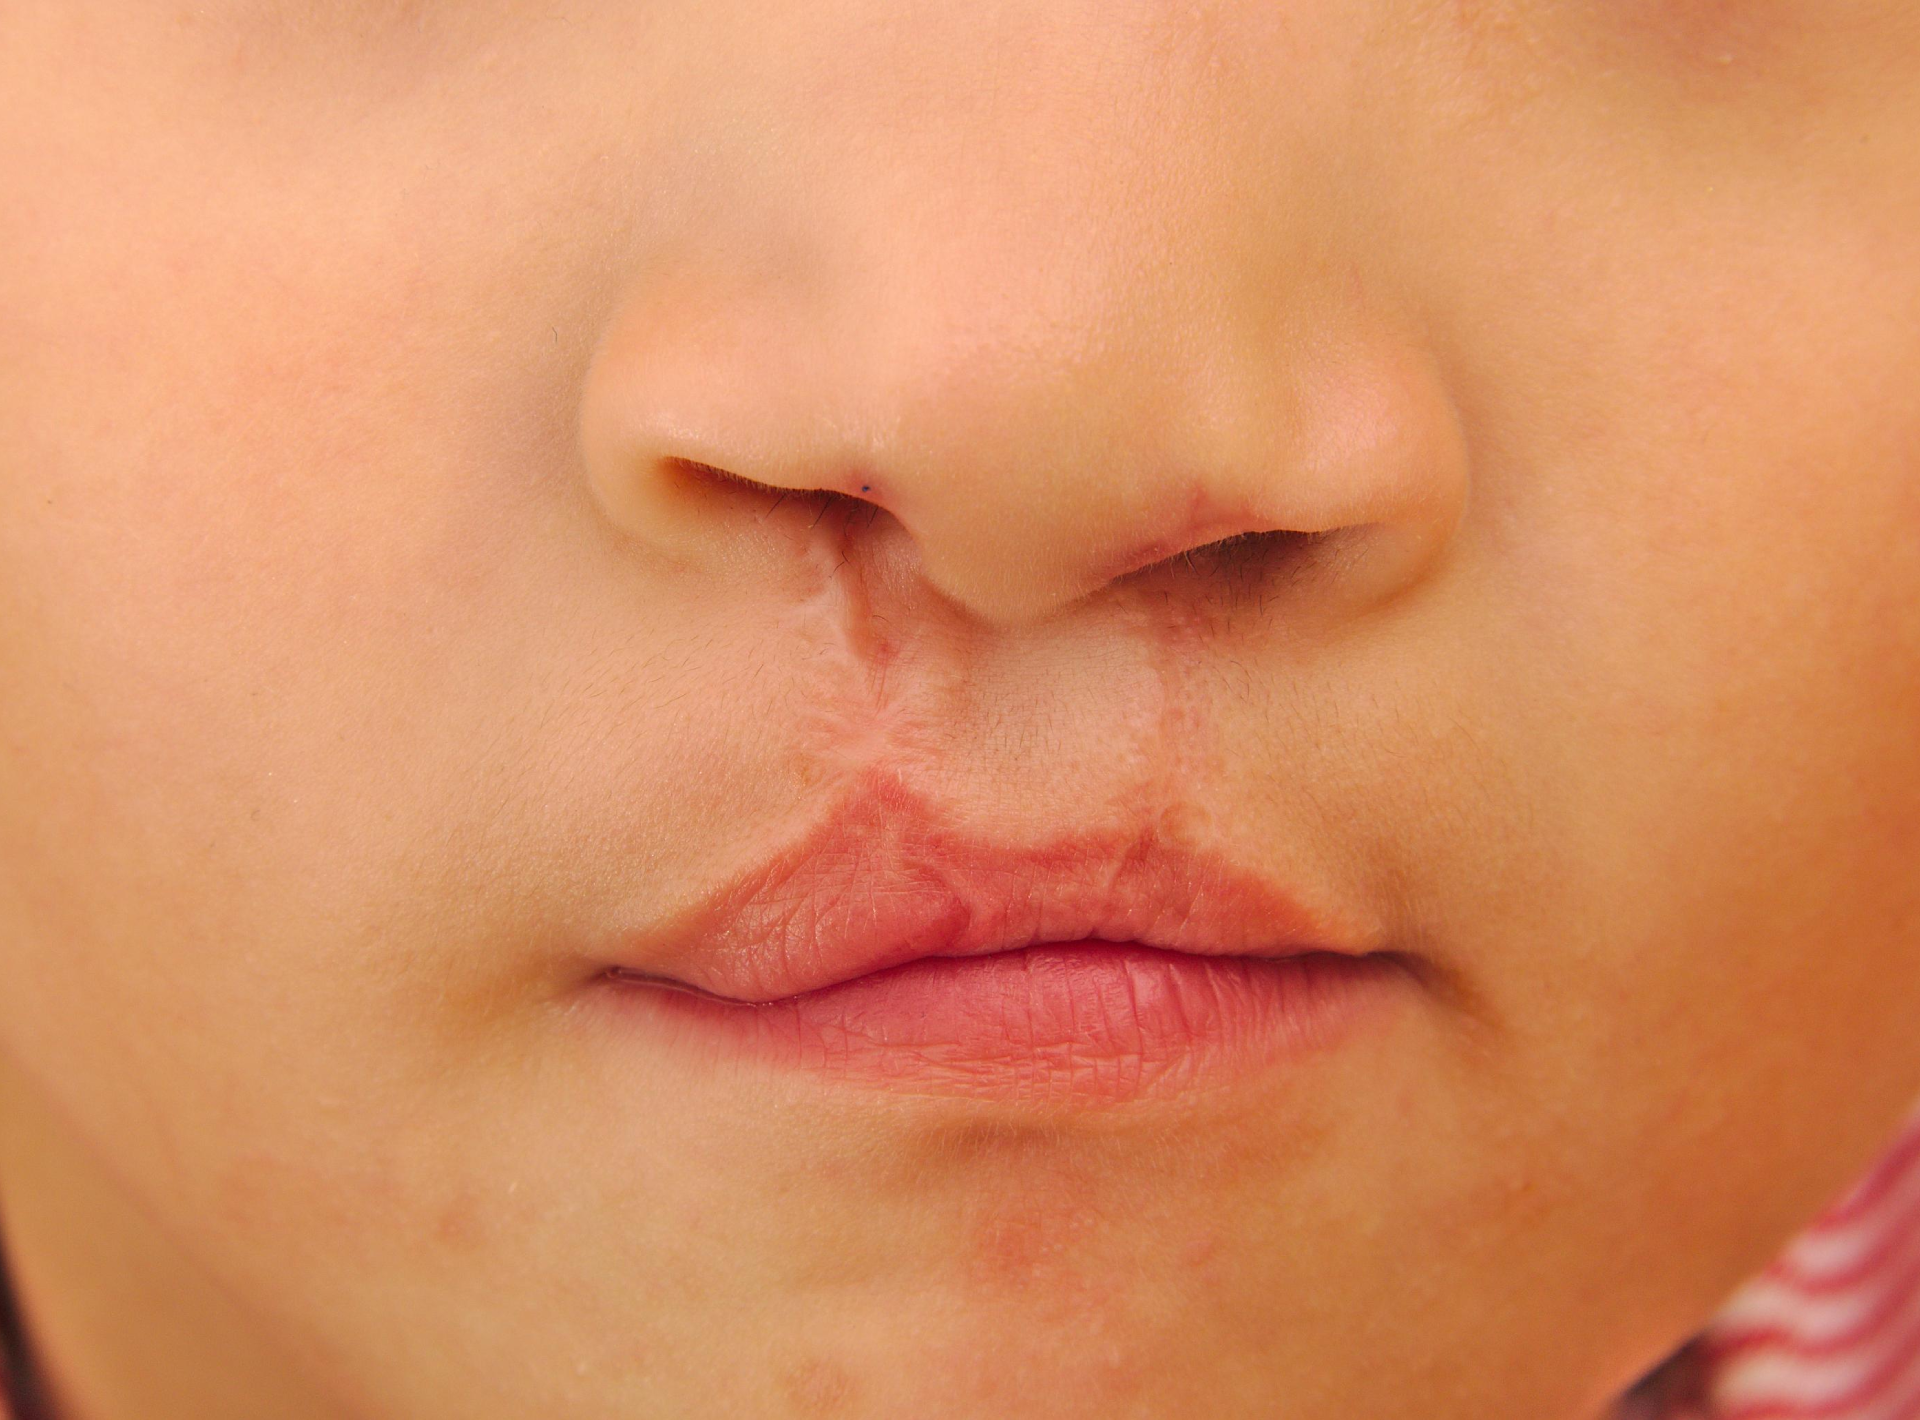
The term "harelip" is outdated and increasingly considered offensive. Medical professionals use "cleft lip" now. The old terminology comes from a mistaken belief that the condition resembled a hare's split upper lip. It's a sloppy comparison that dehumanizes children born with the condition. If you're reading older materials, you'll see "harelip" used frequently, but modern clinical settings have moved past it. Here's what most people don't understand about the timeline. A cleft lip repair, called cheiloplasty, typically happens when the baby is around 3 to 6 months old. The classic rule of thumb surgeons use is the "rule of tens": the baby should be at least 10 weeks old, weigh at least 10 pounds, and have a hemoglobin level of at least 10 grams per deciliter. This isn't arbitrary — it's about minimizing anesthesia risk in infants whose bodies are still developing rapidly. Cleft palate repair, or palatoplasty, usually follows between 9 and 18 months of age. The timing matters because you need to repair the palate before speech development becomes established. If you wait too long, the child develops compensatory speech patterns that are extremely difficult to undo later. But operating too early carries its own risks, including potential impact on midface growth. It's a genuine balancing act.
One thing I've seen repeatedly — and this caught me off guard when I first worked in this area — is how much variation exists even within the same family. If one child in a family has a cleft, the recurrence risk for subsequent siblings is approximately 4 percent. That sounds low, but it's substantially higher than the general population risk of about 0.1 percent. Genetic counseling before pregnancy is genuinely useful for affected families, not just informational window dressing. The feeding challenges in newborns with clefts are more severe than most parents prepare for. Babies with cleft palate cannot create adequate suction because the opening between the mouth and nose prevents the pressure seal they need. Standard bottles won't work. Specialized bottles like the Haberman feeder or Pigeon bottle have soft squeeze bulbs or one-way valves that help. You can find these through pediatric cleft clinics or online medical supply retailers. Getting the right feeding equipment before discharge from the hospital prevents a lot of stress in the first weeks. Ear problems are the hidden complication most people miss. The muscles that open and close the Eustachian tube attach to the soft palate. When the palate is cleft, those muscles don't function correctly. This leads to fluid buildup in the middle ear — otitis media with effusion — in roughly 90 percent of children with cleft palate. The fluid causes conductive hearing loss, which directly impacts speech and language development. Most kids with cleft palate need tympanostomy tubes placed by age 1, often before the palate repair itself. Audiologists should be monitoring hearing from the first few months of life, not waiting until speech delays become obvious.
Surgical outcomes have improved dramatically over the past few decades, but they're not perfect. Primary palatoplasty aims to reconstruct the musculature of the soft palate to enable normal speech, but up to 30 percent of patients will still develop velopharyngeal insufficiency — meaning the palate doesn't close properly against the back of the throat during speech. This results in hypernasal speech that sounds like the person is talking through their nose. These cases often require a secondary procedure called a pharyngoplasty, usually around age 5 or 6, before formal speech therapy begins in earnest. Orthodontic intervention is another area where timing is everything. Children with clefts, especially cleft lip and palate, frequently have misaligned teeth and jaw discrepancies because the cleft disrupts normal facial growth. Alveolar bone grafting — taking bone from the hip or leg and placing it into the gum line where the cleft was — typically happens between ages 7 and 10, just before the canine tooth is about to erupt. Doing it too early risks affecting jaw growth; doing it too late means the tooth can't come through properly. This is one of those moments where the surgical plan has to coordinate closely with the orthodontist's timeline. Multidisciplinary care is the standard now, and for good reason. A single surgeon can fix the lip or the palate, but managing the full spectrum of needs requires a team: plastic surgeon, oral surgeon, ENT, speech therapist, orthodontist, audiologist, geneticist, and sometimes a psychologist or social worker. The best outcomes come from centers that see enough cleft cases annually to maintain expertise across all these specialties. If you're in a rural area without a dedicated cleft team, ask about telemedicine follow-ups and travel arrangements to the nearest comprehensive center. The initial surgeries might happen locally, but the long-term coordination works best when everyone involved knows each other.
Get the Full Details

Psychological support matters more than the surgical repairs themselves in the long run. Children with clefts face staring, questions, and sometimes bullying. Studies show higher rates of anxiety and depression in teens and young adults with cleft history, particularly when social support was inadequate during childhood. Parents should seek out peer support groups — organizations like Operation Smile, the Cleft Palate Foundation, and local cleft support networks connect families with others who've been through the same process. This isn't soft advice. Kids who feel understood by peers with similar experiences tend to cope better with the repeated procedures and therapies that lie ahead. Adults born with clefts are a growing population as surgical techniques improve and life expectancy rises. Some adults who didn't have access to repair in childhood or grew up in underserved areas are now seeking secondary revisions. The field of adult cleft care is still developing, but it exists now. If you're an adult with an unrepaired or poorly repaired cleft, search for centers with adult cleft programs. They can assess what's feasible and discuss realistic outcomes. Cost is a significant barrier in many parts of the world. In the United States, the total cost of cleft repair and associated care over a child's first several years can easily exceed $100,000, though insurance coverage varies widely. Programs like Children's Health Insurance Program (CHIP) and Medicaid cover many cleft-related services, but gaps remain. International efforts by organizations such as Smile Train fund surgeries in developing countries, performing hundreds of thousands of repairs annually at a fraction of the cost. The medical quality from these programs has improved considerably, though outcomes naturally vary by surgeon experience and facility resources.
Research into the causes continues. We know clefts result from a combination of genetic and environmental factors, but pinpointing exactly which genes and which environmental triggers matter most for any individual case remains incomplete. Folic acid supplementation before and during early pregnancy has been linked to reduced risk, though it doesn't eliminate it entirely. Avoiding smoking, alcohol, and certain medications like anti-seizure drugs during pregnancy is standard advice, but the evidence linking these specifically to clefts is stronger for some factors than others. The prognosis is good for most children with access to modern cleft care. With timely surgery, speech therapy, orthodontic treatment, and psychological support, children with cleft lip and palate can speak clearly, eat normally, and lead typical lives. The challenges are real and prolonged, but they're manageable when the right team is involved from the start.