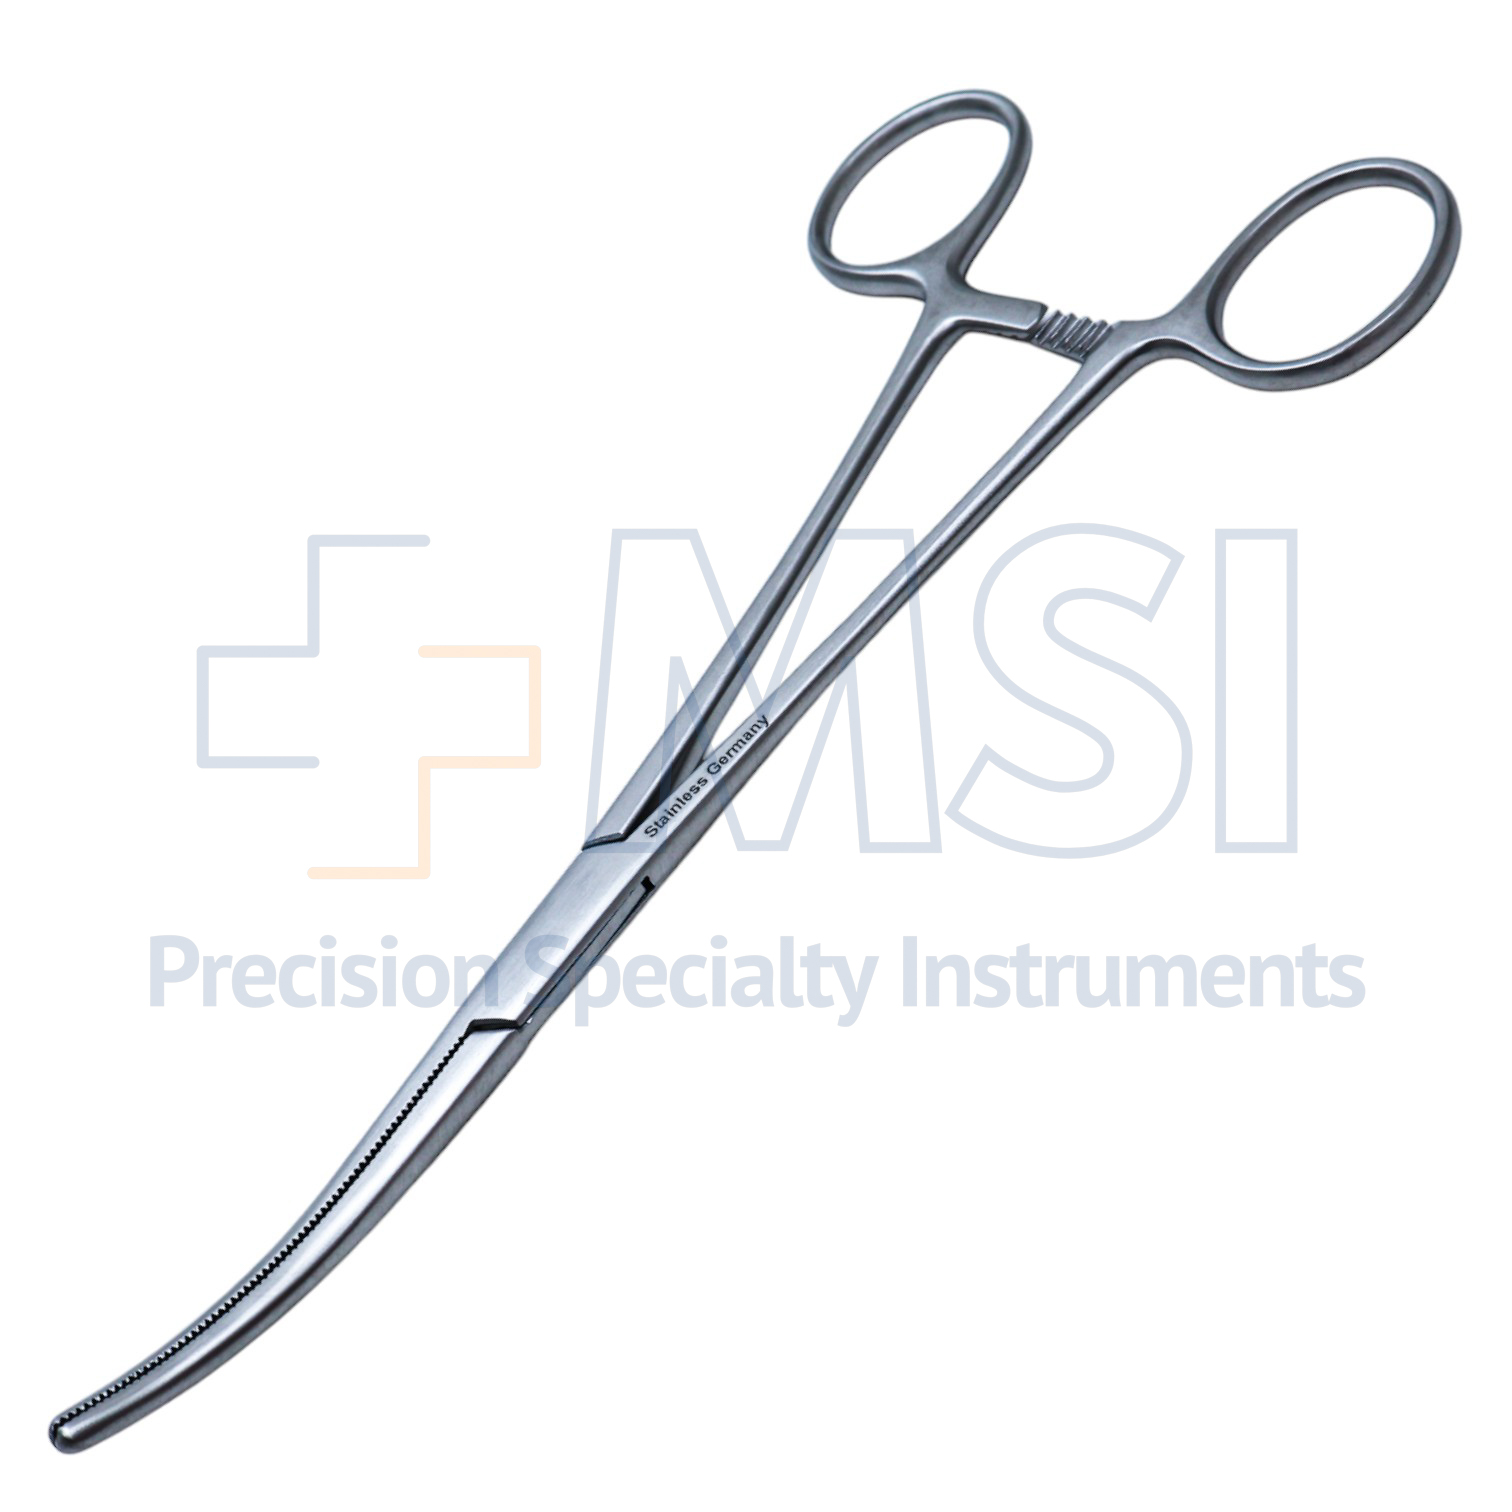
Getting a grip on Rochester Pean Forceps in the OR
The Rochester Pean forcep is one of those instruments you stop noticing after a while. It's a curved artery clamp, roughly 5.5 inches overall, with transverse serrations along the jaw tips. You find it hanging on every basic surgical tray. Surgeons use it for vessel ligation, tissue hemostasis, and sometimes for gentle retraction during dissection. Themakes it easier to reach into deeper planes without the shaft digging into surrounding tissue. I learned to use these on second-year surgical rotation at a busy community hospital. Our attending would hand me a Pean, I'd clamp something, and five minutes later he'd ask me to move it because it was blocking his view or compressing adjacent structures I hadn't accounted for. That's the first lesson: a Rochester Pean is not just a clamp. It's a spatial decision. The design comes from Joseph B. Pean, a French surgeon in the late 1800s. The curved version differs from the straight in that the arc lets you approach vessels at an angle rather than straight on. That matters when you're working around the carotid sheath or dissecting around the iliac bifurcation. The jaws lock with a ratchet mechanism—typically three to five clicks of jaw closure—and the serrations bite into tissue to prevent slippage under tension. That's why they work well for vessels up to about 5mm before you graduate to a Kelly or a mosquito for smaller work.
Here's something most residents don't pick up early: the lock position changes the pressure profile. When you engage the first click, you're getting a light crush—enough to approximate tissue but not occlude a medium artery. Third click is usually where you get firm vessel control without crushing through. If you're trying to place a ligature around a vessel already clamped with a Pean, you want that third click. Second click gives you more room to thread the suture. I've seen fellows overtighten on the fifth click and then spend ten minutes trying to free a necrotic vessel wall because they crushed the adventitia flat. The real nuance with Rochester Peans is jaw engagement technique. You don't clamp and close in one motion the way you do with a needle driver. You position the open jaws around the structure, let the tips emerge from the other side, then close progressively. If you close too fast, you grab surrounding fat, nerve, or adjacent vessel wall along with your target. In a field that's already blood-filled, that mistake costs you visibility and time. I spent a half-hour at 2 AM dissecting a Pean out of a mesenteric fold during a bowel resection because I'd been sloppy on the initial placement. The attendant didn't say anything but his face did all the talking. Material matters too. Most modern Rochester Peans are surgical stainless steel, autoclavable, and come in both standard and fine versions. The fine version has narrower, more delicate jaws and is better for vascular work where precision trumps grip strength. The standard has broader jaws and is useful for bulk tissue. Don't use a standard Pean on a superficial vein—you'll distort it. Use the fine variant or drop down to a Kelly.
There's also a maintenance angle people ignore. These instruments have a box lock joint near the midpoint. If that joint gets dried blood and isn't cleaned properly through the instrument washer, it stiffens. A stiff Pean feels fine until you're in a tight space and need to open and reposition quickly. I once had a set of Peans where the ratchet was so gummed up I could only reliably lock at the first and fifth clicks, skipping the middle positions entirely. That made ligature placement nearly impossible without dropping and reclosing, which in a vascular field means releasing and potentially bleeding. The fix was soaking them in enzymatic cleaner for twenty minutes before the standard autoclave cycle. Now I check the action of every hemostat before I bring it into the sterile field. Limitations are straightforward. Rochester Peans aren't designed for delicate microvascular work—go below 2mm and you want a micro-clamp or an aneurysm needle. They're also not ideal for pulsatile vessels under high pressure because the serrated jaws can cut into the vessel wall if you leave them clamped for extended periods. I've seen temporary ischemia develop in bowel segments where a Pean was left on the feeding vessel for thirty-plus minutes during a prolonged dissection. Use vessel loops or self-retaining clamps like a Satinsky for longer cases. And for arterial bleeds where you need true vascular control, a vascular clamp like a Bulldog or a Satinsky clamp is the right tool. A Pean will work in a pinch, but it's not precision vascular instrumentation. The curved design has another limitation worth noting. Because the jaws arc, you can't always see exactly what's inside them when you're closing in a deep wound bed. That's a common cause of incomplete clamping—you think you've got the vessel but you've only caught part of it. The workaround is to gently pull on the clamped tissue after locking to confirm the whole circumference is secured before you ligate. It adds two seconds and has prevented more than one bleeding event I can think of.
Get the Full Details

If you're studying for boards or prepping for clinical rotations, the key takeaways are: know when to use a Pean versus a Kelly versus a mosquito, understand that jaw closure level matters for your outcome, and treat instrument maintenance as part of your responsibility, not the sterile processing department's problem. The Rochester Pean isn't glamorous. It doesn't have the flash of a vessel sealer or the sophistication of a laparoscopic grasper. But it's been doing the same job reliably for over a century, and in most general surgery cases, it's still the fastest way to get a vessel under control.


