Compensation Structures in Sonography: What the Numbers Actually Look Like
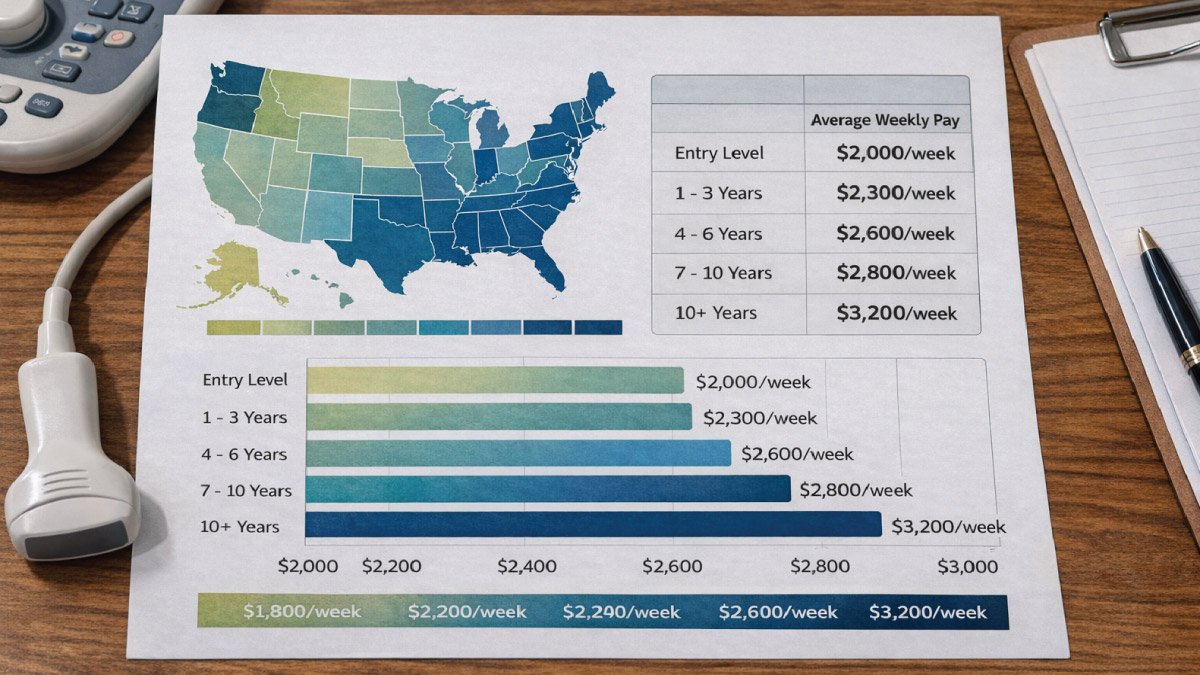
The difference between a traveling sonographer paycheck and a staff sonographer paycheck isn't as clean as most contract summaries make it seem. I've sat through enough orientation calls and read enough offer letters to know that base rate alone tells you almost nothing about what you're actually walking away with. The industry standard framing usually presents travel as strictly more lucrative, and on paper it often is. In practice it depends on how you read a contract. Here is how I break it down when someone asks me to look at an offer. Staff sonographer positions in the United States generally run from about $75,000 to $110,000 annually depending on specialty, geography, and whether the facility is a hospital system or private practice. Cardiac and vascular specialties sit at the top end. Pediatric and general imaging lean lower. Benefits packages at major health systems tend to include retirement matching, health insurance subsidies, and paid time off that typically adds another 15 to 20 percent to total compensation when you value it properly. Travel sonography contracts vary wildly. The national averages I see float around $2,000 to $3,500 per week gross, sometimes higher in critical shortage areas. A 13-week assignment at $2,800 per week comes to roughly $36,400 in gross pay before taxes. Multiply that by three assignments per year and you are looking at a little over $109,000 gross. That sounds competitive with staff until you account for the hidden costs of being mobile.
Let me walk through a specific scenario I dealt with a couple years ago. A facility offered me a contract at $2,600 a week in a rural Midwest location. The rate looked decent on the surface. I checked the housing stipend breakdown and it was pegged to a GSA rate that hadn't been updated since the prior fiscal year. The actual rental market in that county had jumped 18 percent over two years due to a nearby manufacturing plant expansion. I calculated that the stipend would cover roughly 60 percent of a two-bedroom apartment. I had to bring $700 a month out of my weekly paycheck just to stay housed. That cut my effective hourly rate down significantly. I declined the assignment and took a nearby position at $2,300 a week with a fully furnished housing option included. The lower gross rate ended up being worth more because I did not bleed money on rent differentials. This is the part most agencies do not highlight upfront. Tax-free stipends for housing and meals only work if the stipend actually covers your expenses. When it does not, the math collapses. You need to verify the GSA rate against current rental listings on sites like Zillow or ApartmentList before you sign anything. Do it yourself. Agency-provided housing estimates are sometimes generous. Staff positions have their own financial drag that people gloss over. Mandatory overtime at hospital systems can be brutal. A sonographer working 36 hours a week with two mandatory 12-hour weekends per month is effectively working 44 billable hours. The hourly equivalent of an $85,000 salary under those conditions drops closer to $38 per hour instead of the stated $40. Some facilities compensate overtime at 1.5x, others do not. You have to read the union contract or employee handbook carefully before accepting.
Travel contracts often include premium pay for weekends and holidays. A weekday rate of $2,500 might jump to $3,200 on a Saturday. That premium structure can materially shift your annual total. I once took a contract specifically because the weekend differential was clearly spelled out in the offer. The base rate was lower than a comparable assignment, but the weekend markup made the annualized figure roughly $15,000 higher over a full year of assignments. Benefits represent another major branching point. Staff roles at well-funded health systems typically include employer contributions toward health insurance that can range from $400 to $900 per month depending on plan type. Retirement matching up to 5 percent is not unusual at larger systems. Travel contracts rarely include these. Some agencies offer a stipend in lieu of benefits, but it is usually far less than what you would receive as a permanent employee. If you are calculating true financial value, you need to add the benefits package to the staff salary and subtract the benefits gap from the travel income before declaring a winner. There is a counter-intuitive detail about travel sonography that beginners miss. The highest-paying assignments are not always in the cities you assume. Remote rural hospitals and critically short staffing areas in the Mountain West and parts of the Deep South frequently post weekly rates above $3,500 because they cannot recruit locals. A staff position in a major metro like Los Angeles or New York might pay $120,000 with high cost of living. A travel contract in western Montana at $3,800 a week with low cost of living and tax-advantaged stipends can net more take-home pay annually. Location arbitrage is real and it matters more than most people realize.
Get the Full Details

The flip side is job stability. Staff positions provide consistent schedules, predictable income, and protection from the assignment gap. If you finish a 13-week contract and the next one falls through, your cash flow stops immediately. I have seen sonographers go four to six weeks between assignments during slower hiring seasons, usually in late summer and early winter. During one stretch last year, I knew two colleagues who each had seven-week gaps. That is a real financial risk you need to plan for with a reserve fund of at least two months of expenses. Specialty choice matters more than people admit. Interventional radiography and cardiac cath lab sonography consistently command the highest rates on both travel and staff tracks. Neurosonology and MSK ultrasound tend to sit in the middle. General abdominal and OB/GYN are the most saturated markets, which drives rates down slightly, especially for travelers who are willing to take any available assignment. If you want a practical framework, I use this approach. Take the total annual compensation of the staff offer including benefits valued at market rate. Then take the travel contract and calculate net income after subtracting verified housing shortfalls, lost benefits, and any agency fees or license costs. Run both numbers against your actual tax situation. Travel income is often structured with a higher W-2 wage and a taxable stipend component, which pushes you into a different bracket than you expect. Get a quick projection from a CPA who understands travel healthcare before you commit.
The straightforward answer to whether travel or staff pays more is that travel usually wins on gross income if you pick contracts carefully and manage housing costs. Staff usually wins on net stability and total compensation when benefits are properly counted. The financial edge belongs to whoever reads the fine print first.