Understanding Burn Surface Area Estimation in Clinical Practice
The Rule of Nines is a quick assessment tool used by emergency medical professionals to estimate the percentage of total body surface area affected by burns. It divides the adult body into sections that each represent 9% or multiples of 9% of the total surface area. This matters because fluid resuscitation calculations, particularly the Parkland formula, depend heavily on an accurate burn percentage. Getting that number wrong can mean under-resuscitating a patient or flooding them with unnecessary fluids. I have seen multiple versions of this protocol circulate online with slightly different wording, which causes confusion among students and new clinicians. The core concept remains the same, but the exact percentages assigned to certain body parts can vary depending on which textbook or guideline you are following.
The Rule Of Nines In Burns Care Demystifying The Standard Protocol For Estimating Burn Surface Area And Guiding Treatmen
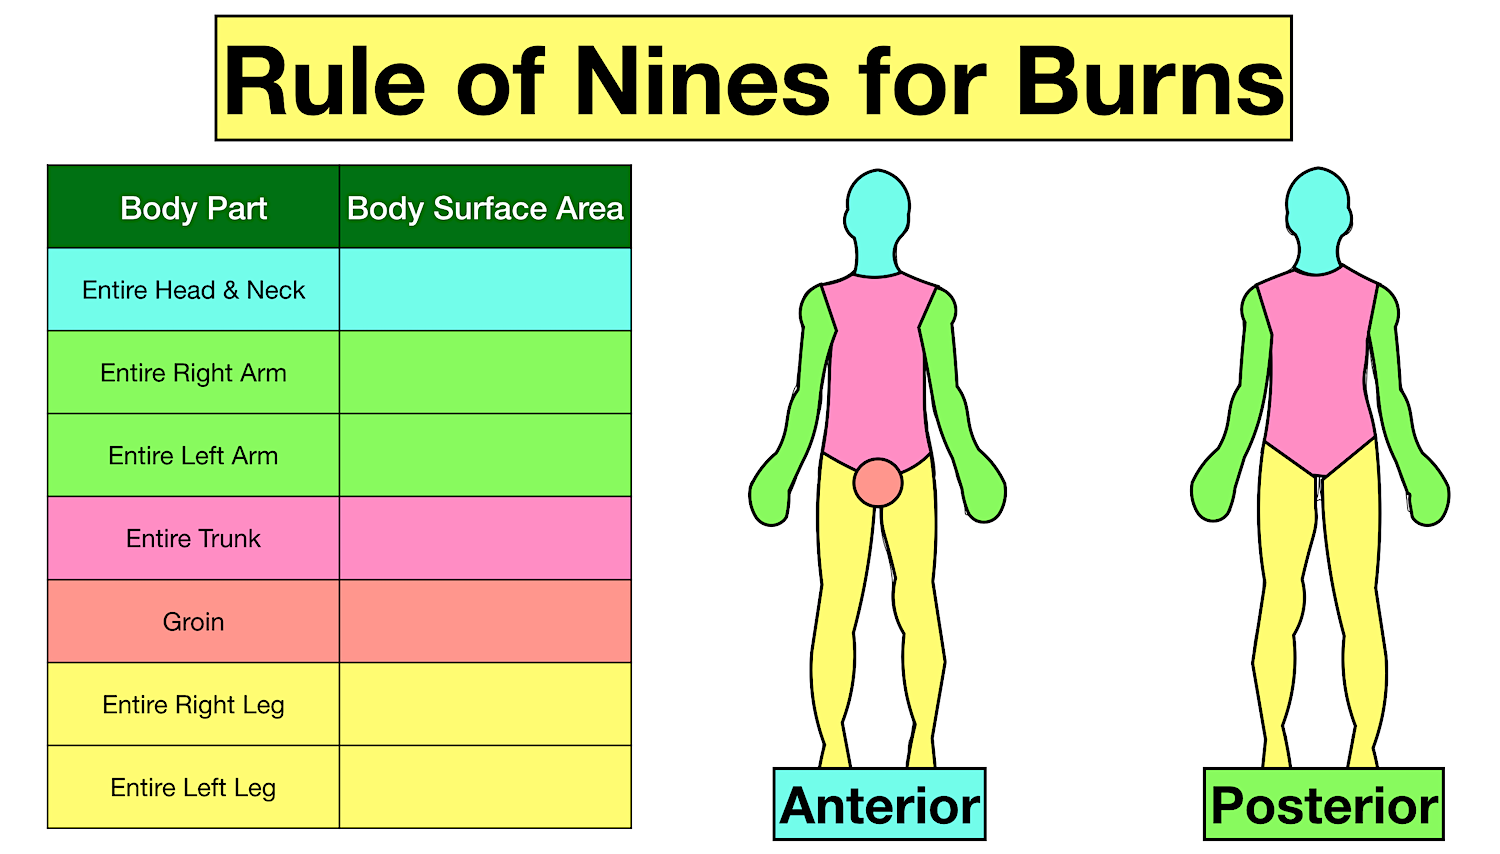
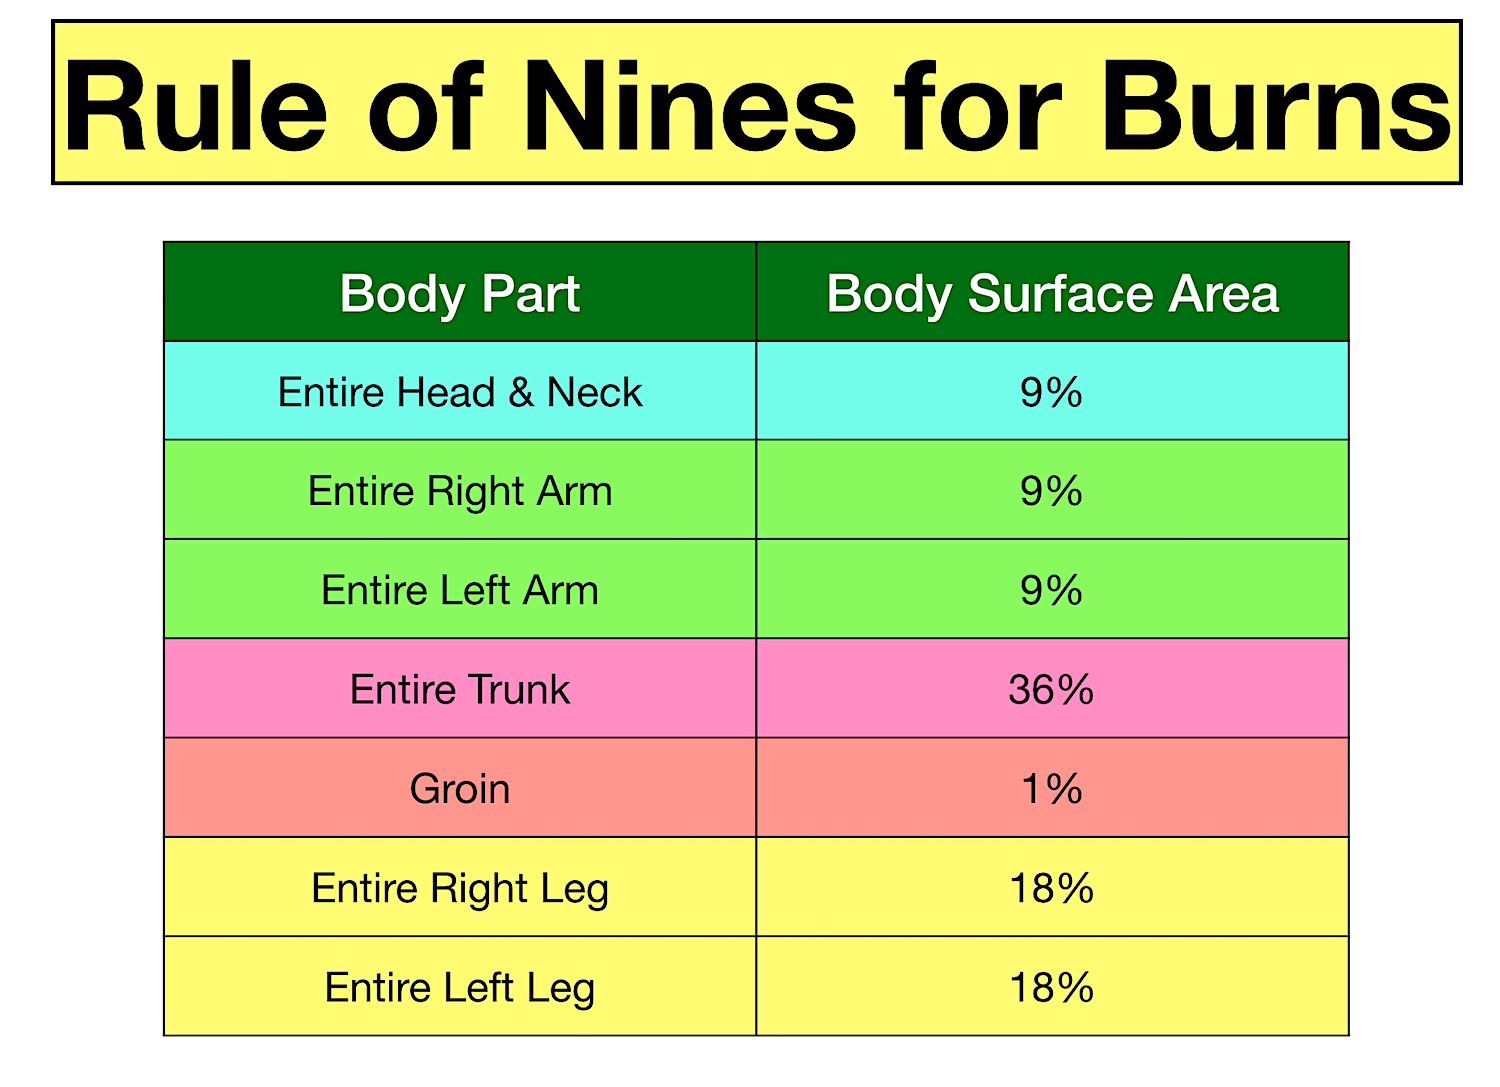
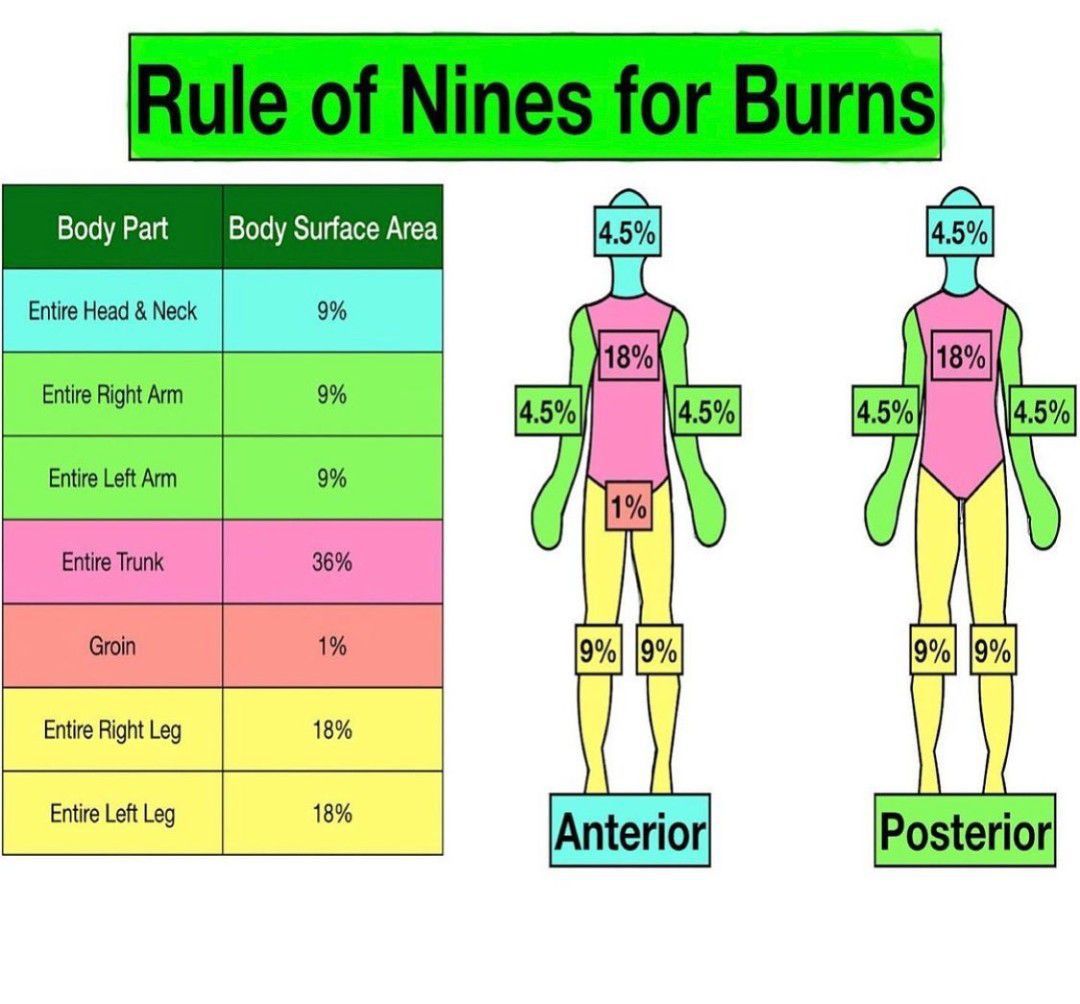
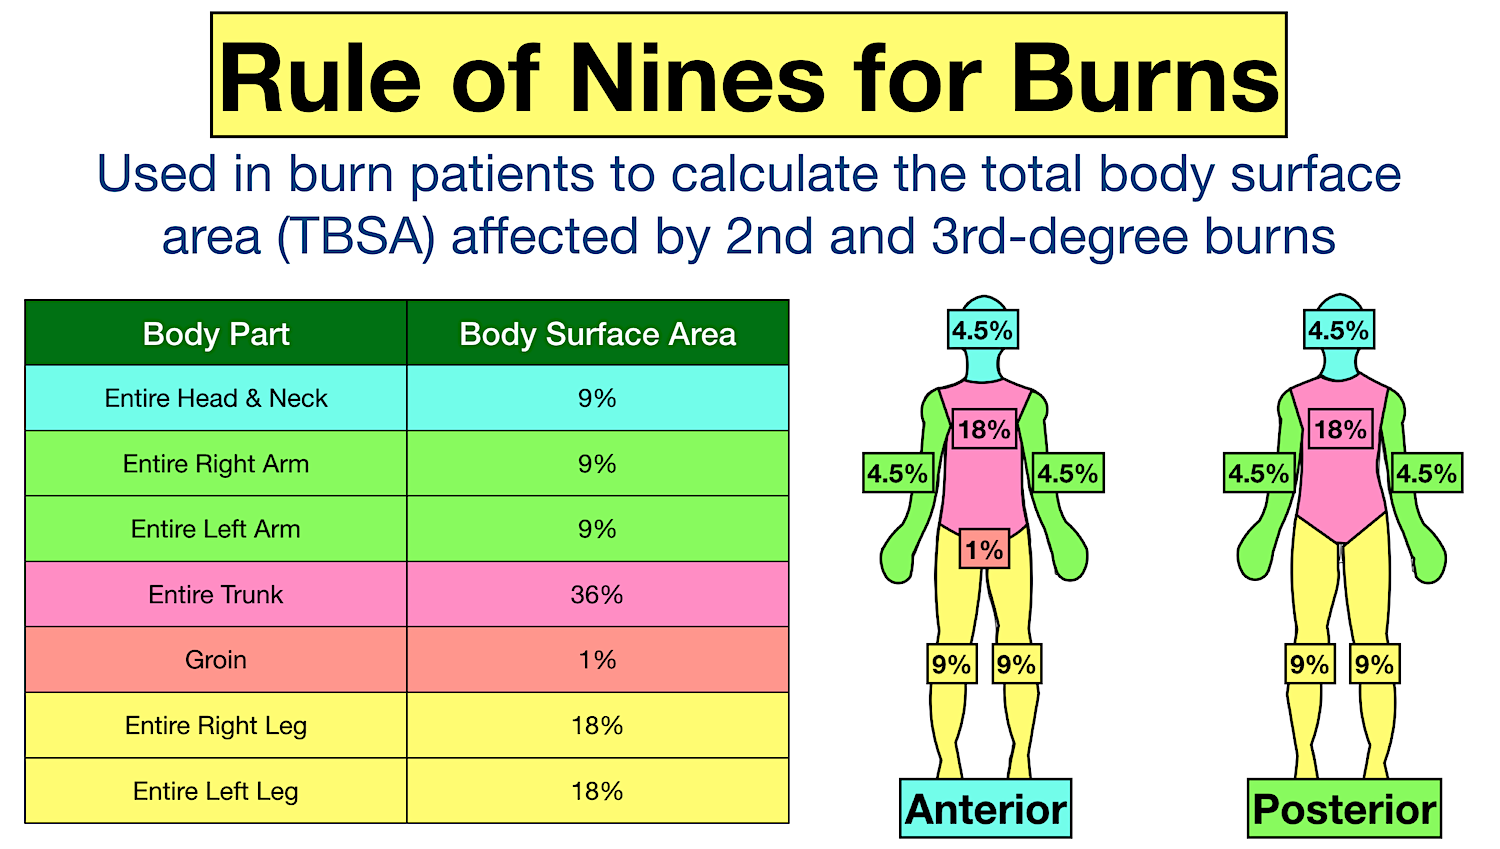
Here is how the standard adult breakdown works. The entire head and neck equals 9%. Each upper extremity is 9%, so both arms together total 18%. The anterior trunk, which includes the chest and abdomen, accounts for 18%. The posterior trunk or back is another 18%. Each lower extremity is 18%, making both legs 36% total. The genitalia and perineal region make up the remaining 1%. Add those up and you get 100%. The method only applies to partial thickness and full thickness burns. Superficial burns like sunburns do not factor into the calculation because they do not cause the same fluid loss or systemic response. I learned this the hard way early in my career when I included superficial erythema in a calculation for a patient who had walked in after a kitchen accident. The attending physician pointed out that the redness alone does not drive fluid shifts the way dermal damage does. One important limitation with this method is that it was designed for adults. Children have proportionally larger heads and smaller legs, so the percentages need adjustment. The Lund Browder chart is more accurate for pediatric patients, but it requires a reference table and takes more time to complete. In a busy emergency department during a mass casualty incident, you may not have that luxury. Many clinicians still use a modified Rule of Nines for children, assigning the head at 18% and each leg at 13.5% instead of the adult values.
Another practical issue I encountered involves irregular burn patterns. A patient came in with flame burns covering roughly half of the right arm and a scattered splash across the left thigh. Estimating that visually using the Rule of Nines required me to mentally split the arm into halves and quarter the thigh region. I ended up documenting it as approximately 4.5% from the arm and 4.5% from the thigh, totaling 9%. The attending asked me to walk through my reasoning, which is standard practice. Being able to articulate your estimation process matters more than hitting the exact percentage because no visual assessment will ever be perfectly precise. There is also a common mistake people make where they count the burn area twice if a wound wraps around a body part. The anterior and posterior surfaces of an extremity together equal the full 9% for that limb. If a burn goes all the way around the arm, you assign the full 9%, not 9% for the front and another 9% for the back. I have seen this error repeated in exam questions and in actual chart notes from residents who were still learning the system. Once you have the estimated total body surface area burned, you plug it into fluid management protocols. The most widely used is the Parkland formula, which calculates the first twenty-four hour fluid requirement as four milliliters times the patient's weight in kilograms times the percentage of second or third degree burns. Half of that total volume is given in the first eight hours from the time of injury, not from the time of hospital arrival. The remaining half is administered over the next sixteen hours. This timing detail trips up many people because it is easy to assume the clock starts at admission.
Get the Full Details
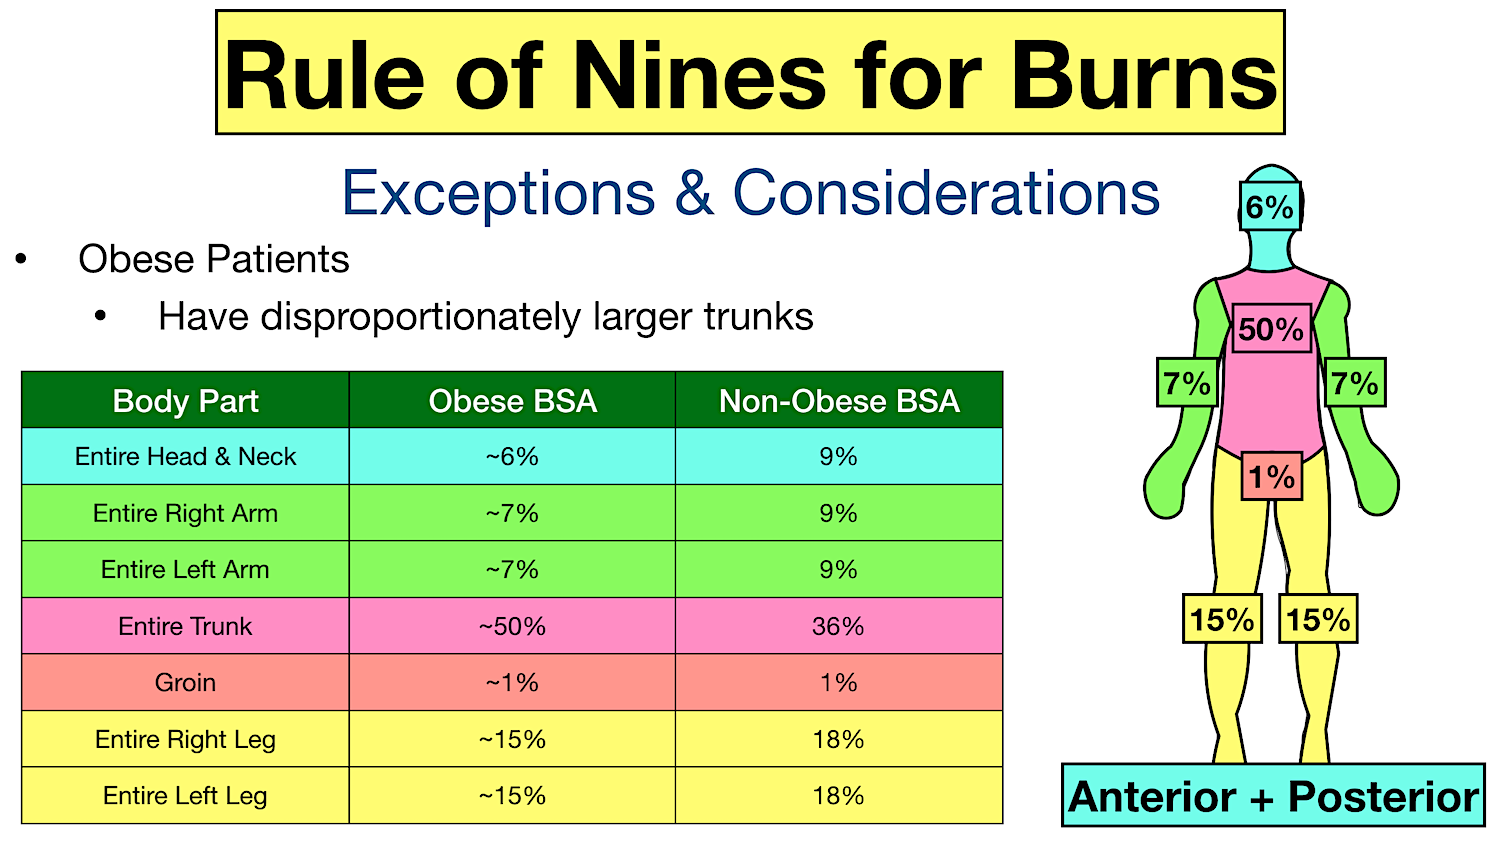
Some facilities use modified Brooke or Consensus formulas instead, which use different multipliers. The principle is the same across all of them. You need a reasonable estimate of burn surface area before any of those calculations become useful. That is why the Rule of Nines remains a foundational skill despite its simplicity. The rule also has limitations beyond the pediatric adjustment issue. It does not account for varying body habitus. A very large or very small patient does not change the percentage assignments, but it can affect how accurately you estimate burn extent visually. Obesity can also obscure anatomical landmarks that help you distinguish between burned and unburned skin, especially in skin folds where flames or hot liquids may have pooled. For complex cases involving inhale injury or mixed burn depths, the Rule of Nines serves as a starting estimate rather than a definitive measurement. Clinicians often use it alongside clinical judgment and sometimes digital planimetry tools if they are available and the patient is stable enough for transport to imaging. Those tools are more accurate but impractical in most emergency settings, which is why the Rule of Nines persists as the standard initial assessment method.
If you are studying for exams or preparing for clinical rotations, practice estimating burn percentages on diagrams before you encounter real patients. The visual component takes time to develop. Recognizing what constitutes partial thickness versus full thickness on unfamiliar skin tones also improves with exposure, and that distinction directly affects whether you include a burn area in your calculation at all. Documentation should always note that the percentage is an estimate based on the Rule of Nines. Exact measurements are not possible in the initial evaluation phase, and recording it as an estimate protects against the false precision that can creep into clinical notes. Attending physicians and burn center teams will adjust fluid rates based on urine output and hemodynamic response regardless of your initial calculation, so treat the Rule of Nines as a guide, not a final answer.