Why We Still Use This Method Despite Its Flaws
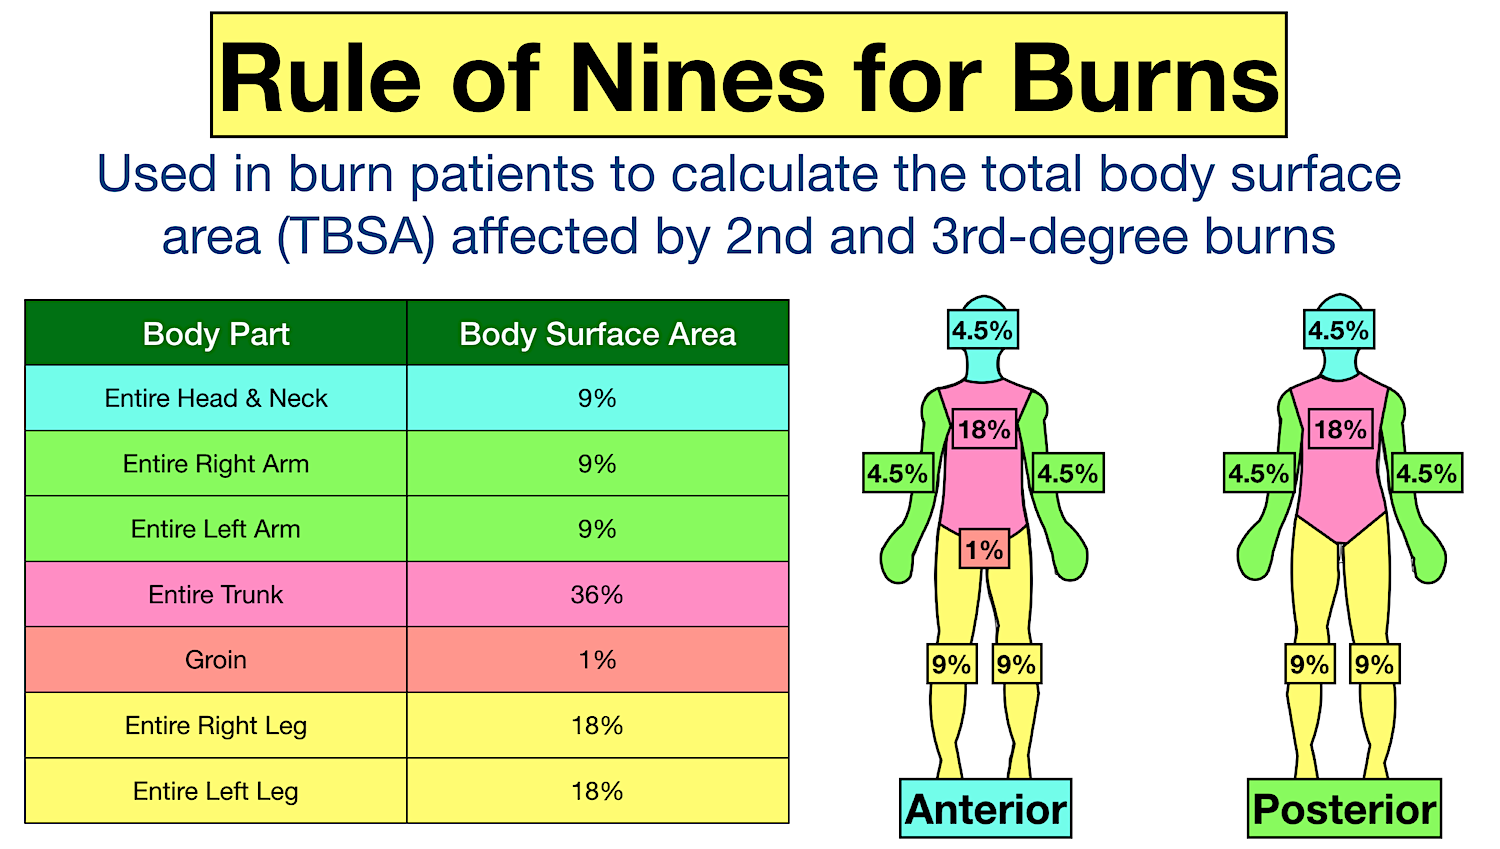
I have been doing burn assessment in emergency departments for over a decade. The Rule of Nines is still the first tool we reach for when a patient walks through the door with burns, even though every attending will tell you the same thing — it is a rough estimate designed for speed, not precision. You are not going to get exact numbers from it. You are going to get numbers fast enough to make triage decisions without spending twenty minutes staring at someone's leg. The core concept is straightforward. An adult's body is divided into sections that each represent 9 percent or multiples of 9 percent of total body surface area. The head is 9 percent. Each arm is 9 percent. The front of the trunk is 18 percent. The back of the trunk is 18 percent. Each leg is 18 percent. The genitals make up the remaining 1 percent. That is the baseline you memorize and apply under pressure.
The Rule Of Nines Burn Assessment Explained A Lifespan Guide To Rapid Fire Calculations
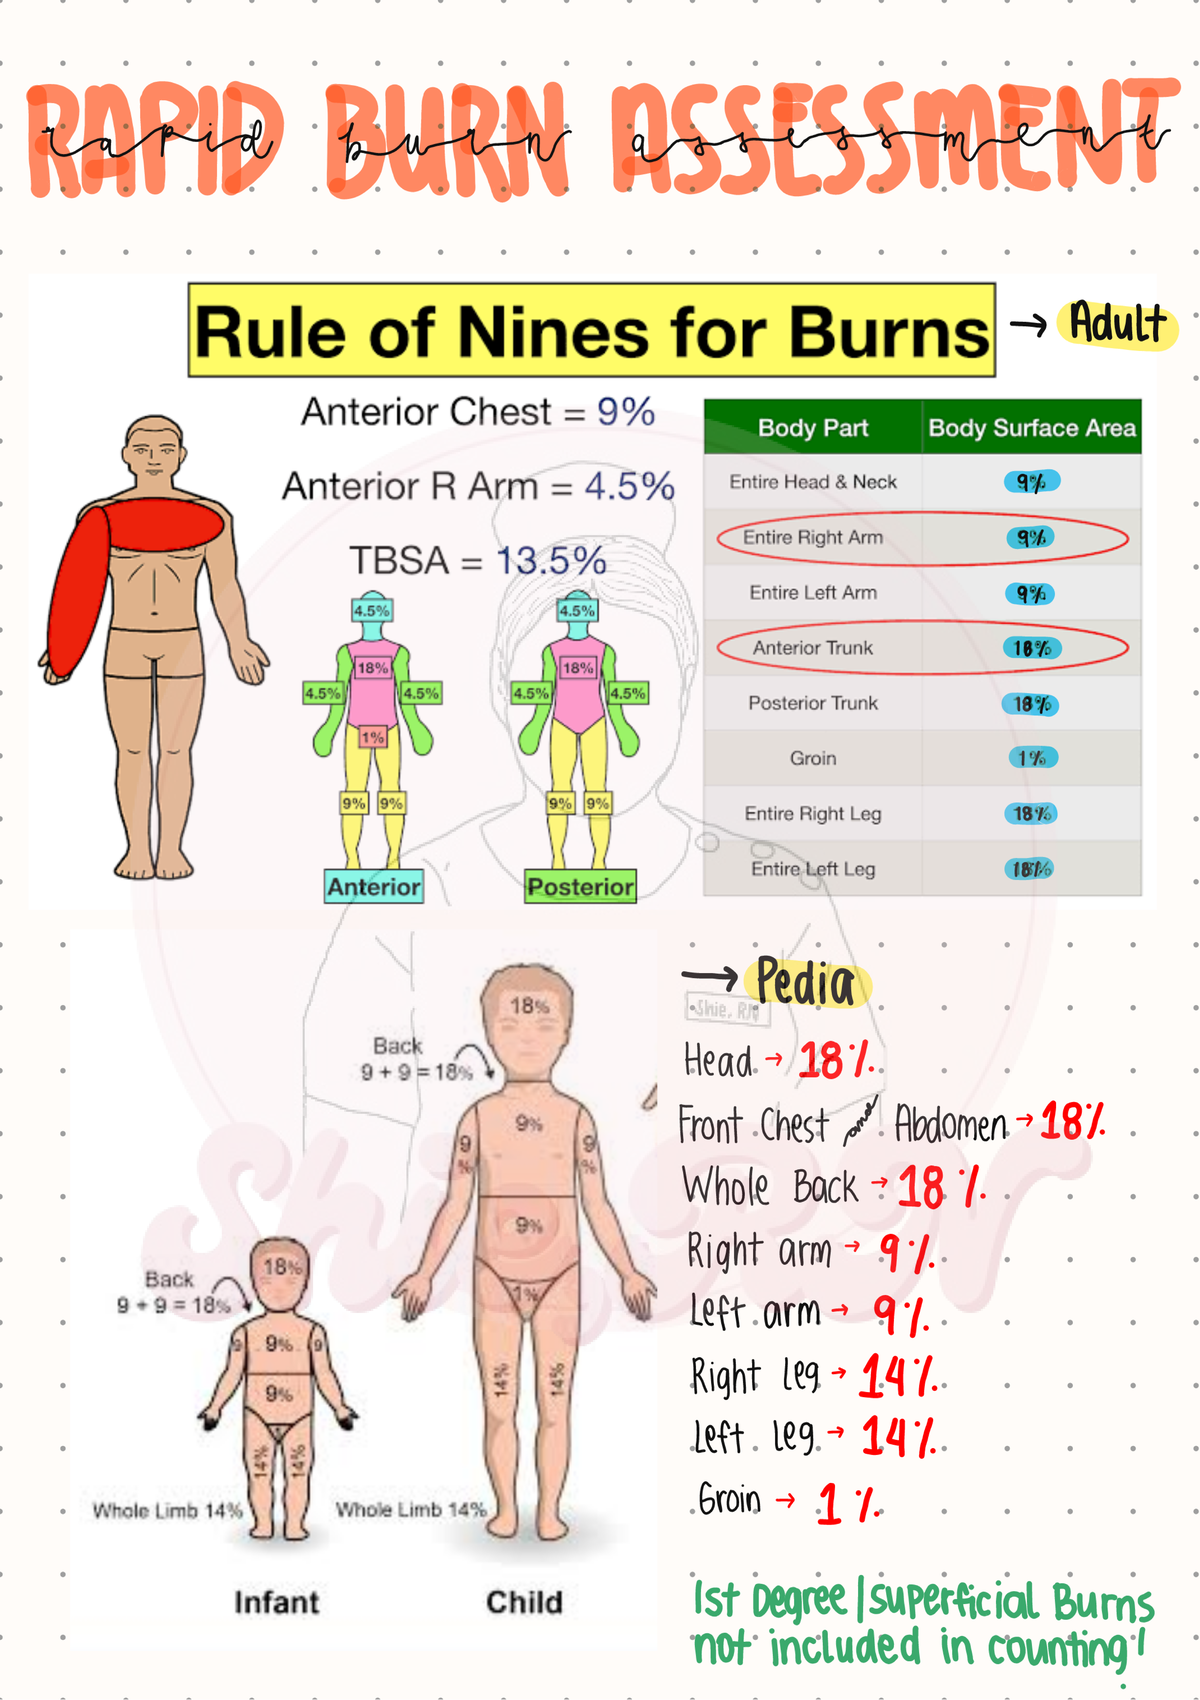
Here is where people mess up in practice. They treat the rule as if it gives you a final answer when it really just gives you a starting point. The percentages shift depending on whether you are dealing with a child, an elderly person, or someone with a different body habitus. Infants have proportionally larger heads, so the modified rule adjusts the head to 18 percent and each leg down to 14 percent. If you use the adult version on a two-year-old, your burn percentage will be wildly inflated and you will either over-transfer or under-prioritize fluids. The real work starts when you try to apply 9 percent increments to irregular burn shapes. I remember a trauma call a few years ago where a patient had scald burns on the anterior left leg, but the burns didn't cover the full anterior surface. They went from the mid-thigh down to the ankle, but only on the medial and anterior aspects, leaving the lateral side clear. The rule of nines would have me mark that leg as 9 percent. The actual burned surface was probably closer to 5 or 6 percent. I ended up using the palm method as a supplement, treating the patient's own palmar surface as roughly 1 percent of their total body surface area and tiling it across the irregular areas. It took an extra thirty seconds and gave me a number that actually made sense for fluid resuscitation calculations. Front of each arm: 4.5 percent. Back of each arm: 4.5 percent. That detail matters more than most people realize. Beginners often assume an entire arm is 9 percent and then second-guess themselves when they see partial thickness burns on just the anterior surface. Break it down. Anterior arm is 4.5. Posterior arm is 4.5. Anterior hand is 0.5. Posterior hand is 0.5. You will find yourself using these sub-divisions constantly once you stop treating each limb as a single block.
Another thing nobody stresses enough is the difference between superficial, partial thickness, and full thickness burns in the context of the rule of nines. The Rule of Nines only applies to partial and full thickness burns. Superficial burns, the kind that look like a bad sunburn and leave the skin intact without blisters, do not count toward total body surface area calculations for fluid resuscitation or transfer decisions. I have seen residents mark down full-leg anterior burns only to have it pointed out that the patient only had erythema and no dermal injury. Those burns are painful but they change nothing about management. The biggest practical limitation of this system is that it assumes a standardized adult male body. When you are dealing with obesity, amputations, or significant asymmetry, the percentages stop being reliable. A patient with a below-knee amputation on the right side does not have 18 percent in that right leg. They have roughly 9 percent distributed across the remaining structures. I learned this the hard way during a burn center transfer case where the receiving facility questioned our admission numbers because we had included the amputated limb's surface area in the calculation. We recalculated without it and the difference moved the patient from borderline admission criteria into clear admission territory. The math was simple but the consequence was significant. For quick reference in the field or on a busy floor, here is the standard breakdown you should have committed to memory:
Get the Full Details

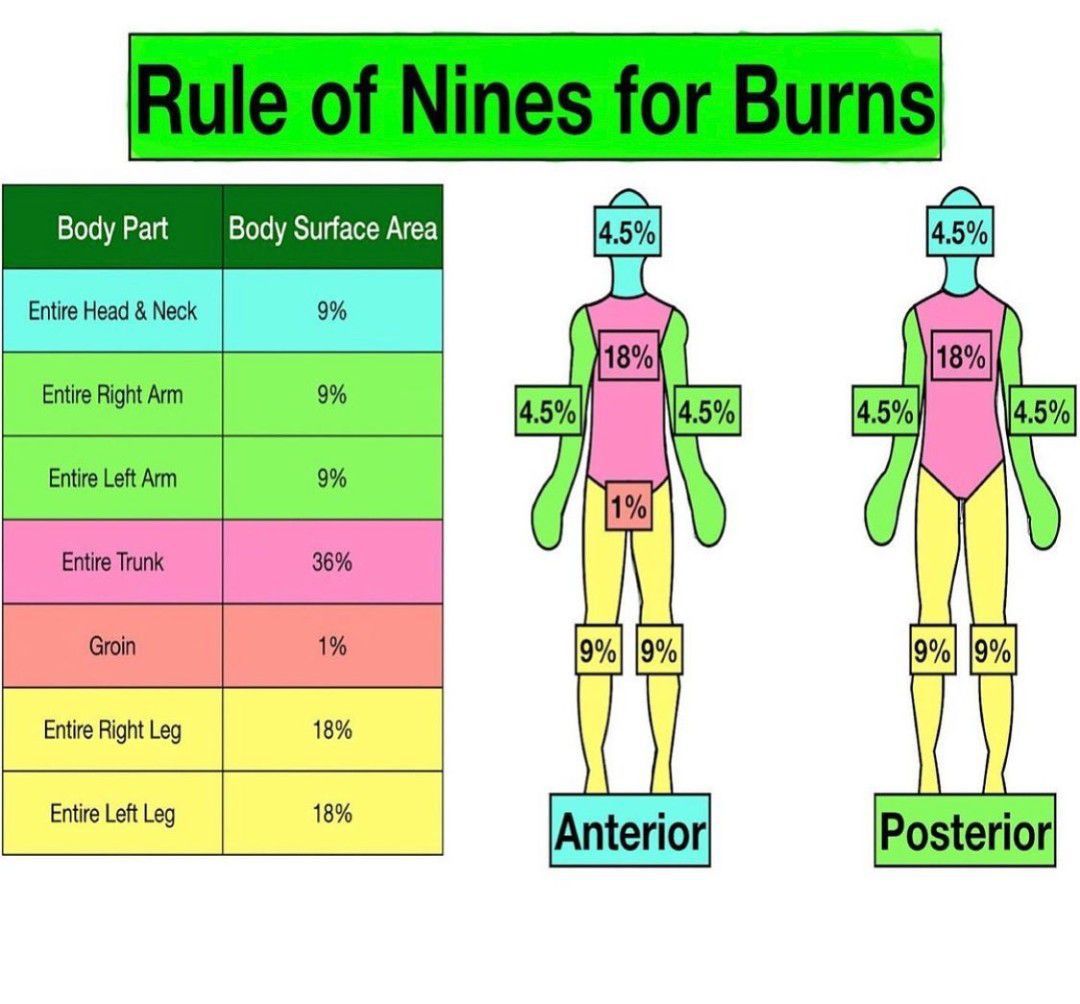
Head and neck: 9 percent (front 4.5, back 4.5) Each upper extremity: 9 percent total (front 4.5, back 4.5) Each lower extremity: 18 percent total (front 9, back 9)
Anterior trunk: 18 percent Posterior trunk: 18 percent Genitalia: 1 percent
Total: 100 percent The palm method works as a cross-check for smaller or scattered burns. A patient's palm including the fingers represents approximately 1 percent of their total body surface area. It is not perfectly accurate but it is close enough for clinical purposes and it scales to whatever size body you are working with. I use it constantly when burns cover irregular patches across the trunk or when a burn spans multiple anatomical regions that the rule of nines handles poorly. One advanced nuance that separates people who use this method well from people who use it sloppily is understanding that the rule is designed for estimated burn surface area, not measured surface area. The difference shows up most clearly with circumferential burns. A burn that goes all the way around an arm is not double the area of a burn on just the anterior surface because the circumference of a cylinder is not the same as its projected frontal view. The actual surface area of a circumferential arm burn is closer to the full 9 percent of that arm, not 18 percent. You will catch this error if you actually visualize the limb as a three-dimensional object rather than a flat diagram.

When the rule of nines fails completely, which is more often than you might expect with pediatric burns or very large surface area burns, the Lund-Browder chart is the standard alternative. It accounts for age-related proportional changes and lets you map individual body regions with more granularity. Most burn centers will ask for Lund-Browder on any pediatric admission. The rule of nines is still useful for initial field assessment and rapid decision-making, but it should not be the last word in your documentation if you have the time and tools to do better. Fluid resuscitation formulas like the Parkland formula depend entirely on your TBSA number, so getting the burn percentage wrong propagates through every subsequent clinical decision. A 10 percent error in your surface area estimate translates directly into a 10 percent error in your fluid order. That is why the supplemental methods matter. The palm method, the Lund-Browder chart, and even rough visual estimation trained against known surface areas all serve as reality checks against the rigid geometry that the rule of nines imposes on human bodies. If you are studying for exams, memorize the adult breakdown cold. If you are actually using this clinically, learn when to move past it. The method will get you to a usable number in under a minute. The judgment to know when that number needs adjusting is what separates competent assessment from checkbox medicine.