How Software-Defined Networking Is Changing Anesthesia Monitoring in Modern Operating Rooms
The traditional operating room runs on hardware. Monitors, ventilators, infusion pumps, and anesthesia machines all had their own dedicated cables, proprietary protocols, and isolated data silos. When a cardiac event happened at 2 AM, the anesthesiologist was reading from a machine that could not export its data anywhere. That is changing fast. SDN is the infrastructure layer that makes it possible to treat the entire OR as a programmable network instead of a collection of incompatible devices. SDN in anesthesia environments separates the control plane from the data plane. Instead of every device making routing and policy decisions independently, a central controller orchestrates traffic flow, prioritizes clinical data, and enforces security policies across the entire surgical suite. For anesthesia specifically, this means hemodynamic waveforms, capnography traces, and drug administration logs can be streamed in real time to aggregation platforms, electronic health records, and machine learning models without the latency and compatibility headaches that defined earlier integration attempts. I spent three years working with OR network upgrades at a regional trauma center. The first time we deployed a full SDN stack, the immediate benefit was not flashy. It was that we stopped losing data during peak surgical hours. Before SDN, we had a flat Ethernet network where imaging PACS traffic, surveillance camera feeds, and anesthesia monitor streams all competed for the same bandwidth. During a busy evening of combined spinal-epidural cases, the anesthesia workstation data would throttle. We missed two episodes of desaturation alerts because the monitoring dashboard was lagging forty seconds behind real time. That did not happen after the SDN rollout. Traffic policies gave clinical monitoring streams hard priority over everything else. Forty seconds of lag became four milliseconds of jitter.
The architecture works like this. You have network elements like switches and wireless access points that simply forward packets based on flow rules. Those rules are installed by a centralized SDN controller, which maintains a global view of the network topology and policy intent. For anesthesia workflows, the controller can dynamically adjust bandwidth allocation when a case shifts from routine to high acuity. It can isolate the anesthesia data VLAN from guest Wi-Fi and administrative traffic. It can push firmware updates across all OR devices in a controlled window instead of having each manufacturer do it on its own schedule, which is how most patch-related downtime happened before.
What SDN Actually Enables in Anesthesia Practice
The most practical outcome is unified data visibility. Anesthesiologists can see vitals from the main OR monitor, the backup monitor, the portable ultrasound, and the post-anesthesia care unit handoff dashboard all flowing through the same network fabric with consistent timing. Without SDN, achieving that required point-to-point integrators, HL7 interfaces, and expensive middleware from vendors who rarely talked to each other. With SDN, the network itself becomes the integration layer. The controller maps device endpoints to clinical data classes and routes them to the appropriate destination. Another outcome is enforceable security compliance. HIPAA and Joint Commission requirements around data-in-transit encryption and access control are difficult to audit on legacy networks. SDN controllers maintain persistent state. You can query exactly which device sent which packet to which endpoint at any given time. During a routine audit last year, we pulled six months of traffic logs from the controller in about twelve minutes. The same task on the old network would have taken a week of manual switch configuration checks and fragmented log compilation. Predictive analytics is where SDN shows its real advantage. Machine learning models for predicting intraoperative hypotension, emerging sepsis, or difficult airway complications need clean, timestamped, high-frequency data from multiple sources. SDN ensures that data arrives in the right format, at the right time, and in the right order. We ran a pilot using a hypotension prediction model trained on data streamed through our SDN fabric. The model flagged thirty-two patients who subsequently experienced significant blood pressure drops. Twenty-nine of those events were preceded by a detectable hemodynamic trend at least eight minutes before the drop became clinically obvious. That warning window does not exist without reliable, low-latency data delivery.
Get the Full Details
Setting Up an SDN Environment for Anesthesia Workflows
Start with a controller selection. The major vendors in this space include Cisco Intersight, Juniper Mist, and OpenFlow-compatible open source options like ONOS and OpenDaylight. For a hospital environment, proprietary enterprise controllers tend to integrate better with existing IT infrastructure and provide vendor support, which matters when a switch fails mid-case. Open source controllers are viable for research deployments and smaller facilities with in-house networking expertise. Next, inventory every networked device in your anesthesia zones. I mean every device. Not just the anesthesia workstations. infusion pumps with network ports, wireless patient monitors, ceiling-mounted display panels, environmental control systems, and even some surgical lights in newer ORs have network interfaces. Each one needs an endpoint profile in the SDN controller. Without complete inventory, you will have blind spots where devices bypass policy controls entirely. We learned this the hard way when a newly installed portable ventilator in the pre-op holding area was routing data outside the monitored VLAN because it had not been profiled. It sat on the network for eleven months before we caught it during a routine security sweep. Define your traffic classes. At minimum you need clinical monitoring traffic, medication administration telemetry, imaging and ultrasound streams, administrative and EMR traffic, and general facility IoT. Assign priority levels. Clinical monitoring and medication telemetry should sit at the top. Imaging gets high but slightly lower priority because it can tolerate more latency. Administrative traffic goes below clinical. Facility IoT goes to best-effort. The controller enforces these classes using QoS tagging at the switch level.
Implement segmentation. Each anesthesia zone should have its own virtual network. Pre-op, OR suite, PACU, and procedural sedation areas should not share the same broadcast domain. SDN makes this straightforward because segmentation is policy-driven rather than requiring physical VLAN changes on every switch. If you add a new OR, you assign it to the anesthesia segment through the controller interface. No cabling changes, no switch reconfiguration, no overnight maintenance window. Deploy monitoring and alerting. The SDN controller should feed into your existing network operations center dashboard. Configure alerts for anomalous traffic patterns, unexpected device connections, bandwidth threshold breaches, and policy violations. Set thresholds based on your baseline. A sudden spike in monitoring traffic from a single workstation usually means a device is malfunctioning and retransmitting data. That triggered alert helped us catch a faulty capnography module that was generating false waveform data and saturating its own network segment before the clinical alarm ever sounded.
Where SDN Falls Short in Anesthesia Settings
SDN is not a universal fix. Legacy anesthesia machines from the early 2000s do not support TCP/IP natively. They use serial connections or proprietary digital buses. Adding those to an SDN fabric requires protocol gateways, which introduce additional failure points and latency. In our facility, about eighteen percent of our devices in older wings needed external gateways. Those gateways failed twice in the first year, and each failure took the connected devices offline until we replaced them. Budget for spare gateways and test failover procedures regularly. Wireless coverage inside ORs is another persistent problem. Steel structural elements, lead-lined walls, and dense equipment racks create dead zones that no amount of controller intelligence can fix. We had a stretch of corridor between the pre-op and two ORs where wireless signal dropped below usable thresholds during certain shift changes. Mobile anesthesia tablets went offline for ten to fifteen seconds at a time. The SDN controller re-established connections quickly, but the clinical workflow stuttered. The fix was additional wired access points, which required renovation work we had not planned for. There is also a human factor. Many anesthesiologists do not want their monitoring data flowing through a programmable network controlled by IT policy. They worry about latency, about data loss, about the controller becoming a single point of failure. Those concerns are not entirely unfounded. If the SDN controller crashes, the entire network reverts to default switching behavior. Devices still communicate, but policy enforcement stops. Traffic prioritization disappears. Bandwidth contention returns to what it was before SDN. We configured a redundant controller pair with automatic failover and tested the degradation scenario monthly. Under load, failover took approximately three seconds. Clinicians noticed nothing during those three seconds because the switches maintained their last known forwarding tables. But the risk exists, and it requires a documented contingency plan.

Cost is another factor. A full SDN deployment across a ten-OR suite with full anesthesia zone coverage ran approximately eighty-five thousand dollars in our case. That includes controllers, managed switches, wireless infrastructure upgrades, gateway hardware, and about two hundred and forty hours of engineering time over six months. Smaller facilities with fewer than five ORs may find the economics unfavorable unless they share infrastructure across multiple departments. Combining anesthesia, perioperative nursing, and surgical instrumentation networking on the same SDN fabric can spread the cost enough to make the numbers work.
A Practical Troubleshooting Scenario
Here is a specific issue I encountered that illustrates how SDN changes the troubleshooting paradigm. We had intermittent desaturation data gaps on two anesthesia workstations in OR three. The gaps appeared randomly, lasted two to four seconds, and occurred mostly during the afternoon block. Standard network diagnostics showed no errors. Switch port counters were clean. Cable tests passed. We ruled out hardware failure on the workstations themselves because the gaps only appeared in networked data transmission, not on the local screen. The SDN controller logs revealed the pattern. A wireless access point on the third floor was undergoing scheduled firmware reconciliation every day at 1:47 PM. The reconciliation caused a brief authentication loop for devices associated with that access point. OR three used that access point. The workstations would lose association for roughly three seconds, then reconnect, then lose it again during the same window. Local monitoring continued normally because the workstations retained cached data, but any cloud-synced or remotely accessed information dropped during those gaps. The workaround was to shift OR three to a different access point and configure a static policy in the controller that excluded the 1:45 to 1:50 PM window from triggering reassociation for that specific device group. The gaps stopped immediately. On a legacy network, we would have replaced cables, swapped switches, and possibly replaced the workstations before finding that the problem was a firmware schedule conflict. SDN observability cut the diagnosis time from weeks to about four hours.
What Comes Next
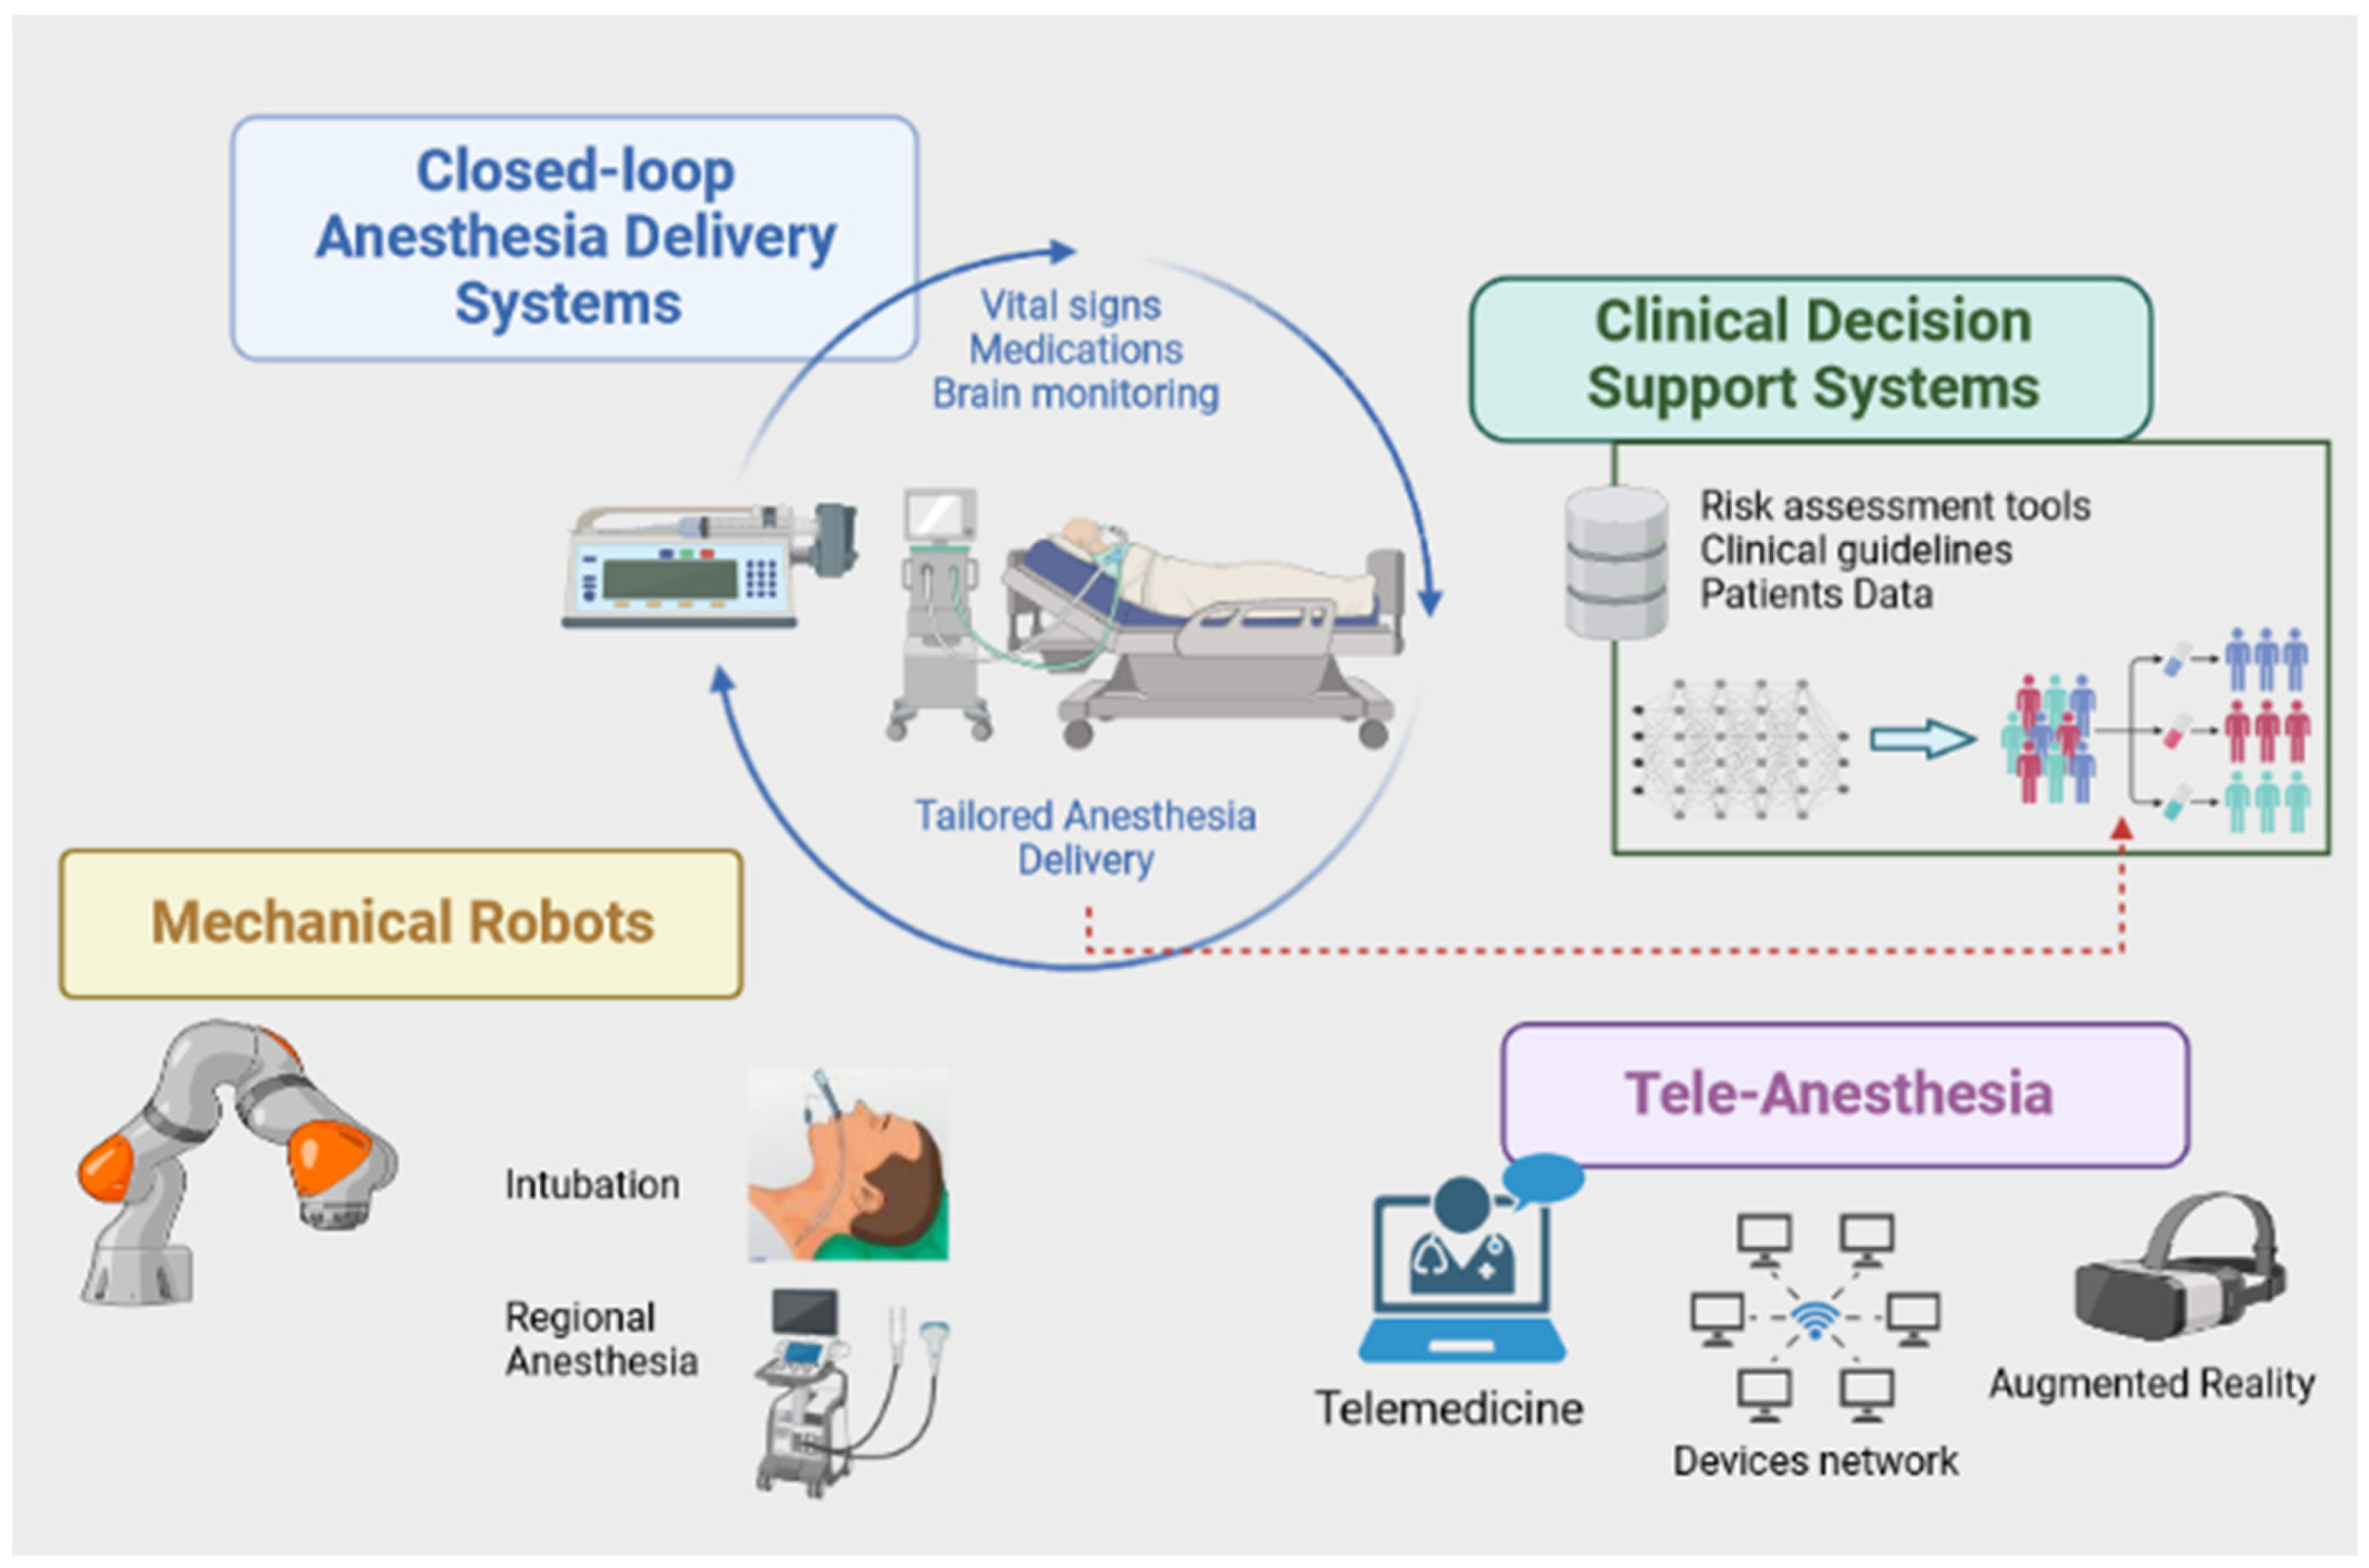
The trajectory is toward closed-loop anesthesia delivery systems that use SDN infrastructure to feed real-time physiological data into automated drug titration algorithms. Early research already demonstrates viable prototypes. The bottleneck is not the networking technology. It is regulatory clearance and the inherent risk of automating dosing decisions. Until those barriers shift, SDN in anesthesia remains primarily an integration and reliability play rather than an automation enabler. That is still valuable. Reliable data delivery saves lives more often than automated dosing ever will in the current regulatory climate. If you are evaluating an SDN deployment for your anesthesia practice, start with a network audit. Map every device, every data flow, and every failure you have experienced in the past two years. Those failure points tell you exactly where SDN will help and where it will not. Do not expect the deployment to solve clinical workflow problems that are fundamentally about communication and staffing. SDN fixes data movement. It does not fix understaffed PACUs or poorly designed handoff protocols. Keep those distinctions clear during planning meetings. The engineers will present SDN as a comprehensive solution. It is not. It is a targeted infrastructure improvement with genuine and measurable impact on data reliability, security posture, and analytical capability. That is enough.