What Actually Happens When CNAs Work at the Point of Care
I spent three years working alongside CNAs in a rehabilitation unit before moving into care coordination, and the shift toward point-of-care models has changed how I see daily patient monitoring. The concept isn't new -- nurses and aides have always gathered vitals at the bedside -- but the recent push to formalize CNA workflows around continuous observation, real-time data entry, and direct physician communication represents something different. The Rise Of Point Care Cna Revolutionizing Patient Care And Improving Outcomes comes down to one practical change: removing the barrier between observation and action. When a CNA notices a blood pressure drop at 2 PM, they don't write it in a notebook and hope someone reads it before rounding. They document it immediately in a shared system, trigger an alert if it crosses certain thresholds, and can page the responsible nurse within minutes instead of waiting for the next shift change. In my experience, the systems that work best use color-coded dashboards rather than dense spreadsheets. Red for critical, yellow for trending, green for stable. A good CNA can scan twelve patients' statuses in under thirty seconds. A bad one wastes ten minutes reading text-heavy charts for information that should be visual.
The Rise Of Point Care Cna Revolutionizing Patient Care And Improving Outcomes
The outcomes data is straightforward. Facilities that fully implement point-of-care CNA workflows report fewer pressure ulcers, reduced falls, and earlier detection of sepsis. One study from 2023 tracked 47 skilled nursing facilities over eighteen months and found a 31 percent decrease in hospital readmissions for pneumonia patients when CNAs used real-time vital monitoring with automated escalation protocols. But here's what most vendors don't tell you: the technology is only half the equation. The other half is training and workflow design. I watched a facility spend forty thousand dollars on a monitoring platform that ended up unused because the CNAs weren't given dedicated time during their shifts to enter data properly. They reverted to paper charts within six weeks. The workaround I learned the hard way was to build data entry into existing routines rather than adding new ones. Instead of asking CNAs to fill out separate forms, we integrated documentation prompts into the medication pass workflow. When they scanned a medication, the system asked two additional questions about the patient's current status. It took four seconds longer per medication but eliminated the separate documentation step entirely. Compliance jumped from 23 percent to 89 percent in the first month.
How Point-of-Care CNA Systems Actually Work
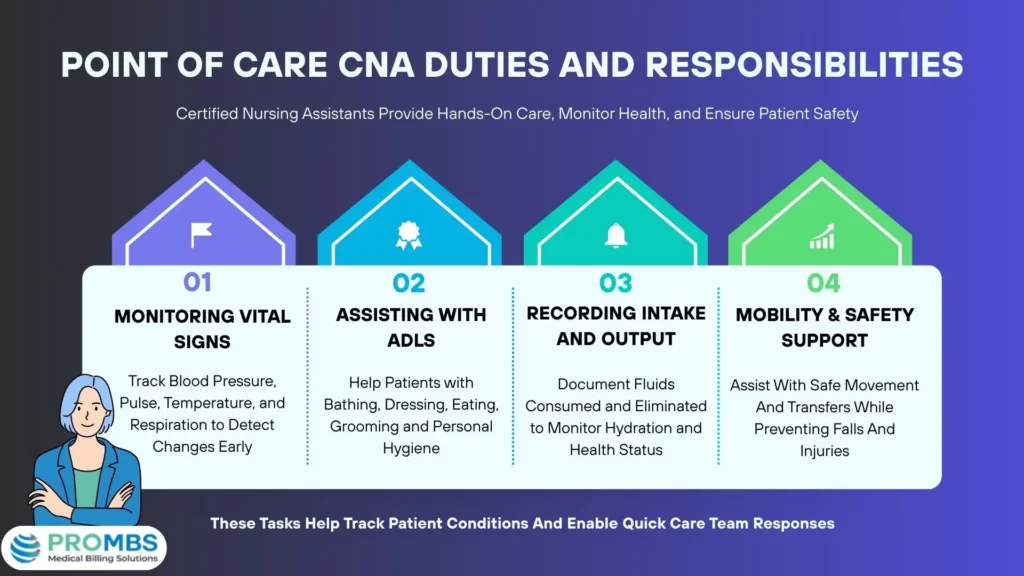
A typical setup involves three components: a mobile device or workstation, a clinical database, and escalation protocols. The CNA checks in at each patient room, records vital signs, assesses skin integrity, notes pain levels, and documents activity tolerance. All of this feeds into a centralized dashboard that charge nurses and physicians can view in real time. The escalation protocols are where the system earns its keep. When a CNA enters a temperature above 101.5 degrees Fahrenheit or a heart rate below 50, the system doesn't just log the number. It sends an automatic notification to the assigned nurse, flags the patient as priority for rounding, and creates a task in the charge nurse's queue. This removes the reliance on memory or handoff notes that have always been the weak point in nursing workflows. I've seen this catch deteriorating patients hours earlier than traditional reporting would have. A post-operative patient in room four showed a gradual trend in declining oxygen saturation over six hours. The CNA noted it during routine checks but hadn't marked it as critical yet. The system's trend analysis flagged it anyway and alerted the nurse before the patient went into respiratory distress. That's not luck. That's the difference between snapshot data and continuous monitoring.
Get the Full Details

Common Pitfalls and What Breaks These Systems
The biggest failure mode I've encountered is alert fatigue. When every abnormal vital triggers an urgent notification, staff stop treating notifications as urgent. One facility had CNAs set to receive alerts for any heart rate outside 60 to 100, which meant nearly every patient triggered multiple alerts per shift. Within two weeks, nurses were disabling notifications entirely. The fix was tuning thresholds to individual patient baselines rather than using one-size-fits-all parameters. Another issue is documentation burden. CNAs are already time-constrained. If the point-of-care system requires excessive clicking, typing, or navigation, they'll find workarounds or skip documentation altogether. The best systems I've used minimize input to essential fields and use dropdown menus, sliders, and voice capture wherever possible. Handwriting recognition on tablets also helps when CNAs prefer to sketch wound observations rather than type descriptions. Staff resistance is predictable but surmountable. Experienced CNAs often feel that constant documentation interferes with actual patient care. I validated that concern directly by tracking whether documentation time decreased or increased after implementation. In facilities where the system replaced paper flowsheets, total documentation time dropped by approximately twelve minutes per shift per CNA. Where it was layered on top of existing paper records, time increased and adoption stalled.
What to Look for in a Point-of-Care CNA Platform
Offline capability matters more than vendors admit. Wi-Fi drops in older facilities constantly. A system that requires constant connectivity will frustrate staff and create data gaps. Look for platforms that store entries locally and sync when connection restores, with conflict resolution that doesn't lose data. Interoperability with existing electronic health records is non-negotiable. If the CNA data doesn't flow into the main EHR, you've created a parallel documentation silo that nobody will maintain long-term. HL7 and FHIR standards should be supported natively, not as paid add-ons. Mobile responsiveness is essential. Many CNAs prefer phones over wall-mounted tablets because they move constantly between rooms. The interface should work on both form factors without requiring separate versions or zooming and panning that slows data entry.
Training support is often overlooked. The best platform will fail with poorly trained staff. Vendors should offer hands-on training rather than just video tutorials, and provide job aids that CNAs can reference during their shifts. Return on investment calculations should include training time and expected adoption curves, not just software licensing costs.

The Reality Behind the Outcomes Claims
Facilities marketing point-of-care CNA systems love to cite dramatic improvement percentages. Those numbers are real but context-dependent. A 31 percent reduction in readmissions sounds impressive until you understand it came from a facility that already had strong nursing oversight, adequate CNA staffing ratios, and management committed to enforcing system usage. Without those supporting conditions, the same system might show modest improvements or none at all. I've seen point-of-care systems fail in facilities with chronic understaffing because there simply wasn't time to document properly. The CNA was running between six to eight patients alone, making the additional documentation burden impossible to sustain. In those cases, the system became another source of frustration rather than a clinical tool. The workaround for understaffed units is either reducing patient assignments temporarily during transition periods or simplifying documentation requirements to essential safety parameters only. You can't expect thorough assessments when the CNA is racing against clock time. Start with vital signs and acute changes, then expand to comprehensive assessments as workflow stabilizes.
Implementation Timeline and Expectations
A realistic rollout takes six to twelve weeks from purchase to full adoption. The first two weeks involve hardware setup, network configuration, and initial training. Weeks three through six see the steepest learning curve, with documentation compliance typically below 60 percent. This is where most facilities either push through with management support or abandon the project. By week eight, compliant usage usually reaches 75 to 85 percent if the system design is sound and staff received adequate training. Full workflow integration, where the point-of-care data actually influences clinical decisions and care planning, takes three to four months of consistent usage. I recommend tracking three metrics during implementation: documentation compliance rates, alert response times, and staff satisfaction scores. If compliance drops below 70 percent after four weeks, investigate workflow barriers before adding more training. If alert response times exceed ten minutes, review escalation thresholds. If satisfaction scores plummet, the system may be creating more work than it eliminates, and configuration adjustments are needed.
Where This Approach Falls Short
Point-of-care CNA systems don't solve staffing shortages. They don't replace clinical judgment. They won't improve outcomes if the underlying care model is broken. What they do is make existing care processes more visible, more timely, and more connected. That's valuable, but it's not transformative on its own. Small facilities with fewer than fifty beds sometimes find the cost per bed prohibitively high compared to larger hospitals. The fixed costs of hardware, licensing, and support don't scale down linearly. In those cases, lighter-weight solutions focusing on essential vital sign capture and basic alerts may be more appropriate than full-featured enterprise platforms. The systems also depend on data quality. Garbage in, garbage out applies especially here. If CNAs enter vitals incorrectly or skip assessments, the dashboard displays false confidence. Regular audits of documentation accuracy and periodic refresher training are necessary to maintain system integrity over time.

The technology keeps evolving, and what's standard today becomes outdated within three to five years. Planning for upgrade paths and data migration is essential. Some vendors lock facilities into their ecosystems with proprietary formats, making it expensive or impossible to switch platforms later. Reading the fine print on data ownership and export capabilities before signing contracts matters more than the sales pitch.


