Why Your Drug Trial Doses Keep Failing You
Most people think of personalized medicine as some futuristic dream where doctors scan your genome and hand you a custom pill. The reality is messier and older than that. Pharmacogenomics has been around since the 1950s when researchers noticed some patients reacted badly to standard doses of drugs like succinylcholine because they lacked a functional variant of the butyrylcholinesterase enzyme. It's not new. What's changed is the cost of genetic sequencing dropped from billions of dollars to under a thousand dollars per whole genome in roughly fifteen years, and computational tools finally caught up to handling the data. I spent about eight years working in clinical pharmacology consulting before moving into healthcare informatics, and the disconnect between what the literature claims and what actually happens in practice is huge. Let me walk through how it works, what trips people up, and where the whole system breaks down.
The Rise Of Personalized Medicine Breaking Down Barriers To Effective Treatment
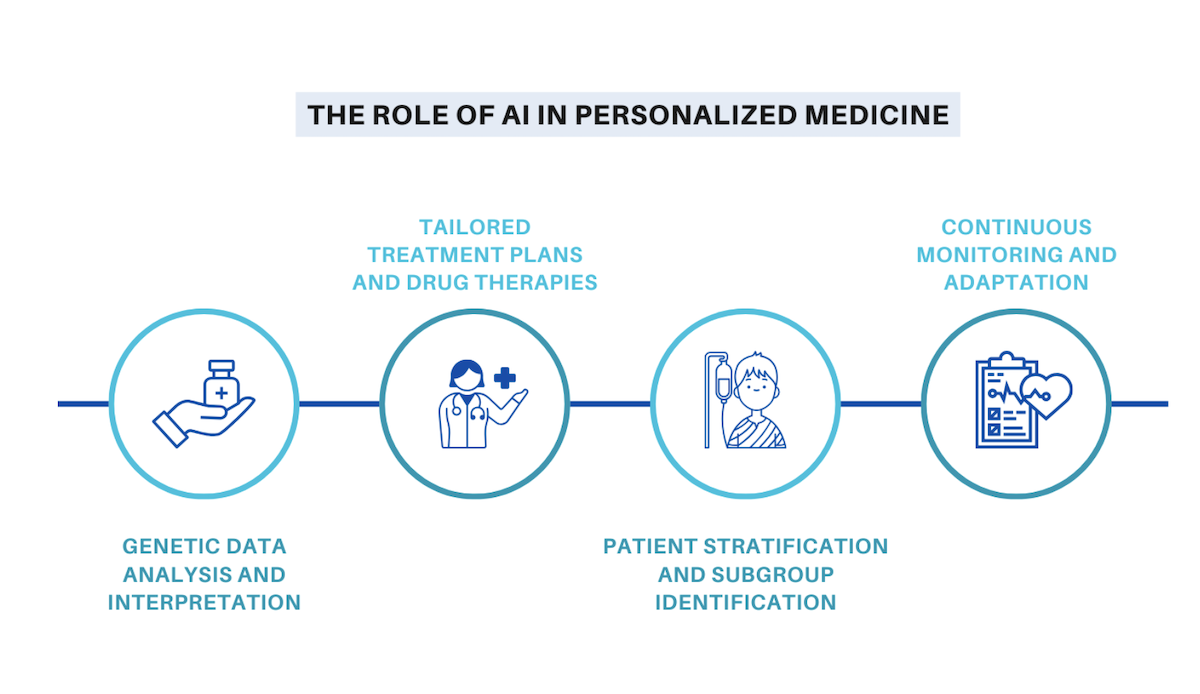
The core mechanism is straightforward: instead of the traditional one-size-fits-all dosing model where a drug is approved based on average population response, personalized medicine stratifies patients by genetic markers, biomarkers, or other biological variables to predict who will respond, who won't, and who might experience adverse events. The implementation pipeline typically runs through three stages: genotyping or phenotyping the patient, interpreting those results against established clinical decision support databases, and adjusting the treatment protocol accordingly. The databases doing the heavy lifting here are things like the Clinical Pharmacogenetics Implementation Consortium (CPIC) guidelines, the Dutch Pharmacogenetics Working Group recommendations, and the FDA's table of pharmacogenomic biomarkers with associated drug labels. These aren't academic exercises. They're curated sets of evidence that tell you, for instance, that a patient carrying two non-functional alleles of CYP2D6 should receive approximately half the standard dose of codeine because their body cannot convert it to morphine efficiently. Or that carriers of certain HLA-B*15:02 alleles face a dramatically elevated risk of Stevens-Johnson syndrome when prescribed carbamazepine, regardless of dose. One thing beginners consistently miss is the difference between predictive biomarkers and susceptibility markers. A predictive biomarker tells you whether a specific drug will work for a specific patient. A susceptibility marker tells you the patient's risk of developing a disease at all. They get lumped together in marketing materials, but the clinical application is entirely different. Personalized medicine for treatment selection relies on predictive biomarkers. Most of the commercial direct-to-consumer genetic tests you see advertised actually report susceptibility markers, which is why they're largely useless for prescribing decisions. The two categories require completely different evidentiary thresholds before they're clinically actionable.
Another counter-intuitive point that comes up constantly: having a variant doesn't always mean you change the drug. Sometimes you just change the dose. This distinction matters because changing drugs introduces new variables like unfamiliar side effect profiles and insurance authorization hurdles, while adjusting a dose is a much lower-friction intervention. For example, with warfarin dosing, genetic variants in CYP2C9 and VKORC1 explain roughly 30-40% of the dose variability. That's significant, but it's not deterministic. Many patients with "suboptimal" genotypes still do fine on standard protocols. The gene-based dosing algorithms like the IBIOID model help, but they're adjuncts, not replacements for clinical judgment. Here's where I ran into a specific problem that illustrates the gap between theory and practice. A few years back, a colleague was managing a patient with treatment-resistant depression who had failed SSRIs, SNRIs, and multiple atypical antipsychotics as augmentations. The patient's CYP2D6 genotype came back as a poor metabolizer. The standard guidance would be to avoid CYP2D6-metabolized antidepressants like duloxetine and nortriptyline. We switched to vortioxetine, which has minimal CYP2D6 involvement, and saw improvement within six weeks. But here's the thing that nobody warns you about: the psychopharmacogenetic databases have very weak evidence backing many of their recommendations. The CPIC guidelines for antidepressants are rated "level C" evidence, which means consensus-based rather than trial-backed. You're essentially making a reasonable guess dressed up in scientific language. The workaround I ended up using was combining the pharmacogenetic data with therapeutic drug monitoring. Instead of blindly switching medications based on genotype alone, I measured actual drug concentrations in the patient's blood after they'd been on a medication for a steady state period. That gave us real pharmacokinetic data that either confirmed or contradicted the genetic predictions. In about 20% of cases I encountered, the genotype-based prediction didn't match the observed plasma concentration. The reason is that genotype is only one variable. Drug interactions, liver function, age, and other environmental factors can override genetic predictions entirely.
Get the Full Details

So how do you actually implement this if you're a clinician or a healthcare organization looking to get started? Here's the practical sequence: First, pick your starting indications. Don't try to do everything at once. The strongest evidence exists for oncology therapies targeting specific mutations, warfarin dosing, clopidogrel response in cardiac patients, and certain psychiatric medications. Start with the conditions where the genotype-drug pair has the most robust supporting data. Every other area is still research-grade at best. Second, choose your testing approach. You can use commercial pharmacogenetic panels from companies like Genelex, OneOme, or Invitae. These typically test 30-50 genes relevant to drug metabolism and cover enough ground for most prescribing decisions. Alternatively, if you're in a larger health system, you might consider whole exome or whole genome sequencing with targeted reporting pipelines, which is more expensive upfront but gives you data you can reuse across multiple clinical encounters without retesting.
Third, integrate the results into your workflow. This is the hardest part and where most implementations fail. A genetic result sitting in a PDF report is useless. The data needs to feed into your electronic health record system with clinical decision support that triggers at the point of prescribing. Tools like OneOme's MatchMaker or CPIC's decision support integrations with Epic and Cerner can do this, but they require significant IT investment and ongoing maintenance. I've seen clinics try to save money by manually reviewing reports and they burned through staff time without improving patient outcomes. Automation isn't optional here. Fourth, establish a feedback loop. Track your patient outcomes after implementing pharmacogenetic-guided prescribing. Are you seeing fewer adverse drug events? Faster time to therapeutic response? Better adherence? Without measuring results, you can't justify the continued investment, and personalized medicine initiatives tend to get defunded when leadership can't see the return. Now let's talk about where this approach fundamentally falls apart, because it's important to be honest about the limitations rather than sell a vision that doesn't exist yet.
The biggest bottleneck is that pharmacogenetics explains only a fraction of interindividual variability in drug response. For most common drugs, known genetic variants account for somewhere between 10% and 40% of the variability in efficacy or toxicity. The rest is environmental, epigenetic, microbiome-related, or simply unknown. This means that even with perfect genetic data, you're still going to have a substantial number of patients who don't respond or who experience adverse effects despite having a "favorable" genotype. The genetics is necessary but far from sufficient. Another hard limitation is the evidence base for non-European populations. The vast majority of pharmacogenetic research has been conducted in populations of European ancestry. Variant frequencies, gene-drug interaction strengths, and even the clinical significance of certain genotypes can differ substantially in African, Asian, and indigenous populations. If you implement a personalized medicine program in a diverse patient population without accounting for this, you risk widening health disparities rather than narrowing them. This isn't a theoretical concern. Studies have shown that polygenic risk scores derived from European GWAS data perform significantly worse when applied to other ancestral groups. Data privacy and consent are also thorny issues that get glossed over. Genetic data is uniquely sensitive. A pharmacogenetic test result tells you not just about the patient but about their biological relatives. There have been documented cases where incidental findings from pharmacogenetic testing revealed non-paternity or unexpected carrier status for serious conditions, creating ethical dilemmas that most clinicians are not trained to handle. Any implementation needs a robust genetic counseling framework, which most hospitals don't have the capacity to provide.

Cost-effectiveness is another area where the picture is mixed. Some analyses show that pharmacogenetic-guided prescribing saves money in high-cost specialties like oncology and cardiology, where a single adverse drug reaction or treatment failure can cost tens of thousands of dollars. Other analyses, particularly in areas with weaker evidence like psychiatric pharmacogenetics, show negligible or even negative returns on investment. The cost per successful outcome varies enormously depending on the indication, the population, and the healthcare system you're operating in. If you're looking for a more immediately practical alternative to full pharmacogenetic testing, consider starting with therapeutic drug monitoring for high-alert medications. Measuring trough levels of drugs like vancomycin, lithium, valproate, and tacrolimus is well-established, requires no genetic infrastructure, and directly addresses dose optimization for individual patients. It's not personalized medicine in the genomic sense, but it achieves the same clinical goal and has a much lower barrier to implementation. Many health systems that eventually adopted full pharmacogenomic programs started with TDM as a stepping stone. The field is moving forward, but the timeline is slower than the hype suggests. The structural barriers—evidence gaps in diverse populations, workflow integration challenges, privacy concerns, and uneven cost-effectiveness—are real and they aren't going away soon. What works today is a targeted, evidence-based approach focused on indications with strong genotype-drug pairs, backed by therapeutic drug monitoring where possible, and implemented with realistic expectations about what genetics can and cannot predict. The broader vision of truly personalized treatment is still emerging, and it will need more rigorous prospective trials before it lives up to its promise.