Setting Up MyChart for Meaningful Care Coordination
Epic's MyChart is everywhere now. Every major health system runs it. But the rollout is the easy part. The part where it actually changes how care gets coordinated is where most places stumble. I spent years watching clinics try to make this work, and the pattern is always the same. They get the portal live, they send out activation emails, and then they wonder why patient engagement stays flat. The gap between having MyChart and using it well is massive. Let me walk through what actually moves the needle.
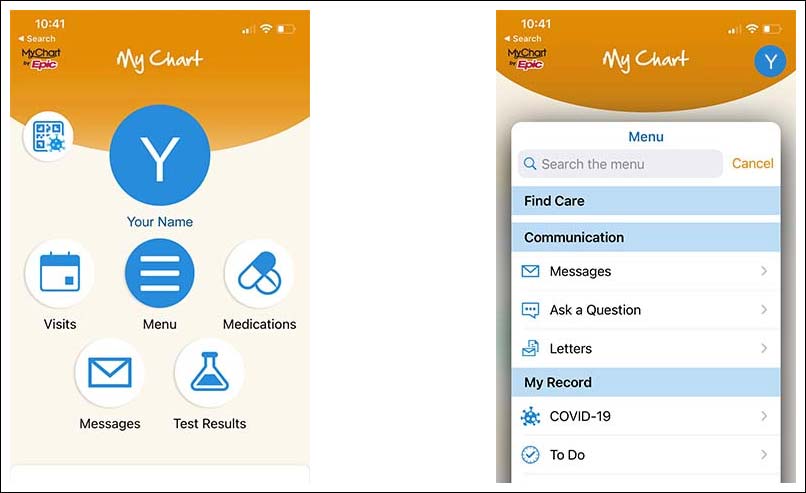
The Rise Of Khn Mychart Revolutionizing Patient Engagement And Care Coordination
When a health system properly integrates MyChart into their clinical workflows, the difference is noticeable. The standard features most people know about are the patient messaging, lab result notifications, and medication requests. But the real shift happens in care coordination. That's where the portal stops being a convenience and starts being a clinical tool. Here's the workflow that works. Nurses review the MyChart message queue during the first hour of clinic, not after. They flag urgent items for the provider and resolve the rest with standing protocols. That queue then drives the day's visit plan instead of the other way around. Most places do it backwards, which is why the feature ends up feeling like extra work. I remember one particular clinic dealing with a chronic care population where post-discharge follow-up was consistently falling through the cracks. We configured MyChart's secure messaging to automatically trigger a provider notification whenever a patient in the heart failure cohort messaged with specific symptom keywords. It wasn't fancy. It just forced the right person to see the message within four hours instead of waiting for the next scheduled visit, which might have been weeks away. Readmissions dropped by about eighteen percent over the following year in that cohort.
The Practical Setup
You need to decide what your care teams will actually use before you enable anything. Epic gives you a huge menu of features, and turning everything on at once is a mistake. Start with the three things your patients actually need most, probably messaging, appointment requests, and test results. Those are the ones that change the dynamic quickly. Then configure your clinical protocols around them. Who responds to messages and when? What qualifies as urgent versus routine? What gets auto-replied versus manually answered? Get these written down before go-live. Without that, every message becomes a bottleneck because there is no standard process. Activation rates matter more than most people admit. An activated account is not the same as an enrolled one. Patients activate by getting a PIN from their clinic and then creating their own credentials. If your staff does not hand out those PINs during visits, activation stalls at twenty to thirty percent. When you make it part of the check-in process, you climb to seventy or eighty within six months. The difference in care coordination capacity between those two numbers is enormous.
Get the Full Details

Where This Actually Fails
The biggest failure mode is liability anxiety. Clinics restrict messaging because they are worried about being sued if someone messages after hours and gets a delayed reply. So they set narrow response windows or require all messages to go through a nurse triage layer first. That adds days to simple questions. Patients give up and call the front desk instead, which creates even more phone tag. You end up with less engagement, not more. The workaround is straightforward but requires actual policy work. Define response time expectations in writing. Forty-eight hours for non-urgent messages. Same-day or next-morning for urgent-coded ones. Put that on your patient-facing materials. The legal exposure drops dramatically when you have a documented standard and patients know what to expect. Most malpractice carriers are fine with this as long as the protocol is consistent. Another failure point that surprises people is the problem list mismatch. MyChart pulls the patient's active problem list from the EPIC chart, but if providers are lazy about keeping it current, patients see outdated or irrelevant conditions listed. A patient messaging about knee pain who also sees "Type 2 Diabetes" on their portal problem list gets confused about which issues the provider is actually tracking. It sounds minor, but it erodes trust fast. Fix it by running a quarterly problem list audit. It takes about an hour per provider and makes the portal actually useful.
Advanced Coordination Features Most People Underutilize
MyChart's care plan builder is one of those features that gets overlooked until someone shows you how it works. You can create condition-specific care plans that appear in the patient's portal. A diabetes care plan might include medication adherence targets, lab reminder scheduling, and education links. When the patient logs in, they see a clear action list instead of a wall of clinical jargon. This is especially useful for chronic disease management where the follow-through between visits is where outcomes fall apart. Baby Connect is another one that changes how pediatric practices coordinate care. Parents get growth chart updates, vaccination reminders, and developmental milestone tracking through the portal. It keeps families engaged during the years when they are most active in the system. The administrative benefit is that reminder calls for well-child visits drop significantly because the portal handles the nudging automatically. Pre-visit planning is worth the setup time. When you configure MyChart to send patients a questionnaire before their appointment, the completed form populates in the EPIC chart before the visit starts. The provider sees it during the visit prep. This alone can cut visit documentation time and improve whether the actual chief complaint gets addressed. I have seen this convert a fifteen-minute complaint into a structured assessment that covers comorbidities the patient forgot to mention.
What To Expect When You Actually Use This
The first six months are messy. Message volumes spike because patients who were calling the office now message instead. Your staff will complain that it is more work. That is normal. The volume stabilizes once triage protocols are in place and patients learn what kinds of issues belong in the portal versus the phone. Expect a three-month ramp period before the numbers look reasonable. After stabilization, the coordination benefits compound. Patients who are engaged in the portal show better appointment adherence. They request refills proactively instead of calling when they are already out of medication. Labs get ordered and followed up on because patients see the pending status and message about results instead of waiting for a phone call that might come days later. The data tells the story clearly. Activated MyChart patients have about twelve percent higher annual wellness visit rates compared to non-activated patients in the same practice. That is not a small difference when you are dealing with population health metrics. But the engagement only works if the clinical team is actually responding to the portal inputs. A portal with no responsive team behind it is just a website with a login screen.

The Hard Parts Nobody Talks About
Interoperability is still a real headache. MyChart data does not flow seamlessly to other health systems' portals. If your patient sees a specialist at a different health network, their MyChart messages and care plans stay in your Epic instance. There is no cross-system patient portal bridge that works reliably yet. This matters a lot for chronic disease patients who see multiple specialists. They end up navigating two separate portal logins with no unified view. Accessibility is another area where good intentions meet hard reality. Your patient population determines whether MyChart actually improves engagement or just adds friction. Elderly patients with limited digital literacy may struggle with the initial setup and then abandon the portal entirely. I have seen this repeatedly in rural clinics where the average patient age is above sixty. In those cases, a hybrid model works better. Keep the phone line open as a parallel channel and offer in-person onboarding assistance during clinic visits. Do not assume digital adoption will happen by default. Staff burnout from message volume is the silent killer of these programs. I once worked with a clinic that enabled messaging without adding any staffing support. Within four months, two nurses resigned citing message-related stress. The clinic had to reduce their messaging hours and hire a dedicated portal coordinator. The cost was real. The alternative was losing clinical staff entirely. Factor in the staffing need before you launch, not after.
What You Should Do Next
Start small. Pick one patient population and one clinical workflow. Configure the portal features around that specific use case. Train the staff who will be answering the messages. Run it for ninety days. Measure response times, patient activation rates, and the volume of phone calls that got replaced. Then decide whether to expand to other populations. Do not treat MyChart as an IT project. It is a clinical workflow change. The technology is solved. The hard part is getting clinicians to change how they handle communication. That requires leadership buy-in, protected time for staff to learn the new process, and realistic expectations about the ramp period. If you can manage those three things, the care coordination benefits are real and measurable. If you cannot, you will have an expensive portal that sits mostly unused and frustrates everyone involved.