What Ambulatory Referral Actually Means in Practice
The term gets thrown around a lot in healthcare IT circles, but most people don't really know what it looks like on the ground. Ambulatory referral is the process of directing patients from primary care or emergency settings to outpatient specialists, diagnostic centers, and follow-up services without requiring inpatient admission. The whole point is keeping people out of hospitals when they don't need to be there. It sounds simple enough, but the infrastructure behind it is surprisingly messy and most systems still run on spreadsheets, faxes, and phone calls. I spent about three years integrating ambulatory referral workflows into a mid-size health network before moving to a consulting role. What I learned is that the technology part is actually the easier half. The harder part is getting clinicians to adopt it consistently and dealing with the edge cases that break every implementation.
The Rise Of Ambulatory Referral Revolutionizing Healthcare Access And Efficiency
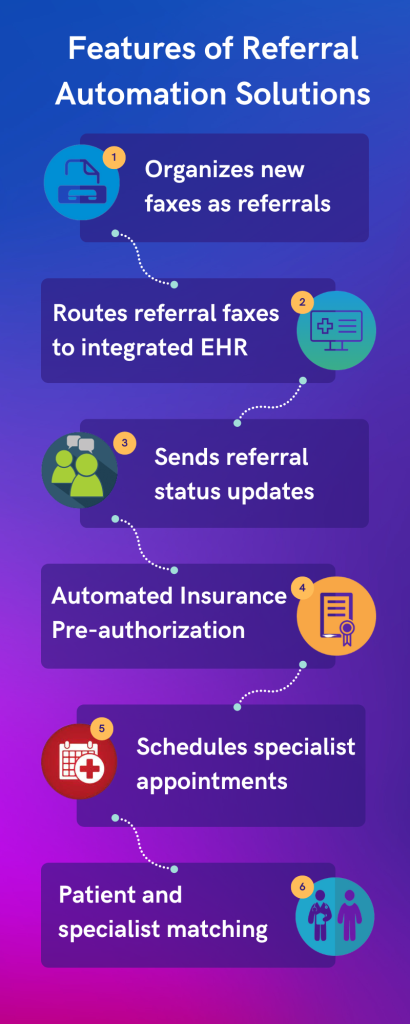
Health systems have been quietly building this capability for a while now, but the shift really accelerated around 2023 when payer incentives and regulatory pressure converged. Value-based care models started penalizing avoidable readmissions more aggressively, and outpatient referral leakage became a financial bleeding point. Hospitals realized that sending a patient to the wrong specialist or delaying a diagnostic referral by days was costing them both money and quality metrics. The automation of referral routing, real-time specialist availability matching, and closed-loop tracking of referral outcomes is what's actually driving the change now. Here's how a functional ambulatory referral pipeline works under normal conditions. A primary care physician identifies the need for a specialist consult during a patient encounter. The EHR generates a structured referral order that includes diagnosis codes, clinical notes, and requested urgency level. That referral gets routed through a central platform that matches it against available specialists based on insurance contract, location, wait time, and quality scores. The patient receives an appointment offer within days rather than weeks. The referring provider gets confirmation, and the specialist's office receives the complete clinical packet. Follow-up tracking ensures the patient actually showed up and that the specialist sends back a consultation note. Most health systems don't have that clean a workflow. They have something more like a patchwork of e-fax, patient portal messages, and phone tags between scheduling desks.
The real efficiency gains come from closing the loop. Open-loop referrals where a patient never completes the visit are still incredibly common, often running at rates between 25 and 40 percent depending on the specialty and population. Closed-loop systems track every step from order to completion and flag drop-offs. I worked with one network that cut their referral completion rate from 58 percent to 82 percent simply by adding automated SMS reminders and a callback queue for uncompleted referrals. The technology wasn't groundbreaking. The discipline of tracking was. There are a few things most implementations miss. First, the referral destination network matters more than the referral creation tool. You can have the best ordering interface in the world, but if your contracted specialist pool has six-month wait times for dermatology and neurology, your patients will find their way around your system anyway. Second, not all referrals need the same routing logic. A routine follow-up for hypertension management and an urgent new-onset headache referral should follow completely different pathways. Most platforms treat them identically and that's a mistake.
Get the Full Details

Setting Up an Ambulatory Referral Workflow From Scratch
Start by mapping your current state, even if it's uncomfortable. Document every referral type you handle, the average turnaround time, the completion rate for each specialty, and where the biggest drop-offs happen. You'll be surprised how much of this data exists in people's heads rather than in any system. I recommend shadowing three or four referral coordinators for a full day. They'll show you the workarounds that actually keep things running. Once you have that baseline, evaluate platforms against a specific set of criteria. Don't get swept up in demo features. Check whether the platform supports two-way integration with your major EHRs without requiring custom interfaces. Look for built-in specialist directory maintenance and real-time scheduling connectivity. Verify that it can handle risk-stratified routing and that reporting gives you visibility into completion rates, not just referral volume. Most importantly, confirm it integrates with your existing patient communication tools rather than requiring a separate patient engagement layer. Implementation typically takes four to eight months for a health system of moderate size. The timeline stretches when you're dealing with multiple EHR vendors across different facilities. If you're smaller and looking at a single EHR environment, you can realistically expect a functional rollout in about twelve weeks with a focused team.
Here's the practical sequence. Month one covers requirements gathering, vendor selection, and architecture planning. Month two is configuration and integration development, including specialist directory population and routing rule setup. Month three involves user acceptance testing with actual referral scenarios and workflow validation. Month four is go-live with a pilot group, followed by phased expansion. Don't skip the pilot phase. Launching to all providers simultaneously is one of the fastest ways to create referral chaos.
Common Problems and How to Handle Them
Specialist directory data decays quickly. I once discovered that nearly 30 percent of the specialists in a platform's directory had outdated insurance contracts or had moved practices. This isn't hypothetical. When a referral routes to a specialist who no longer accepts the patient's insurance, the patient gets denied at check-in, the specialist's office is confused, and the referring provider gets a bounced appointment. The system logs it as a completed referral because an appointment technically happened. It's a quality metric disaster waiting to happen. The workaround is fairly straightforward but requires ongoing maintenance. Build a quarterly directory refresh cycle that cross-references specialist enrollment data against payer contract databases. Automate where possible, but keep a manual verification step for high-volume referral specialties. Your care coordination team should have flagged accounts for direct confirmation when data mismatches appear. Another problem that comes up frequently is urgency mismatch. A PCP marks a referral as routine when the clinical picture suggests urgency, or vice versa. The routing engine sends a complex cardiac case through the same queue as a straightforward dermatology follow-up. The fix is embedding clinical decision support at the point of order entry. When a PCP selects certain diagnosis codes or lab values, the system prompts for urgency assessment rather than assuming routine routing. This reduces both delays for time-sensitive cases and bottlenecking of routine referrals through urgent pathways.

Patient no-shows remain the single largest leak in the referral pipeline. SMS reminders help but only marginally. The more effective approach combines reminder sequences with proactive rescheduling. When a patient misses an appointment, the system should immediately trigger a callback attempt and offer alternative time slots before closing the referral loop. I've seen networks reduce no-show rates by roughly 35 percent using this protocol alone.
Measuring Whether It's Actually Working
Don't rely on referral volume alone. That metric goes up regardless of whether anything improved. Track referral-to-appointment turnaround time by specialty. Monitor the first-contact resolution rate at the specialist office. Measure closed-loop completion rates at 30 and 60 days. Track patient satisfaction specifically around the referral experience. And monitor the rate of referrals going to out-of-network or non-contracted specialists, which indicates routing failures. Financial metrics matter too. Calculate the cost per completed referral including staff time, technology licensing, and communication overhead. Compare this to the cost of unclosed referrals in terms of delayed diagnoses, avoidable ED visits, and patient escalations to inpatient care. The math usually favors the automated system, but the gap narrows if you're not achieving decent completion rates. There are scenarios where ambulatory referral automation simply doesn't add much value. Rural health systems with very small provider panels sometimes can't justify the platform cost because the referral volume is too low to sustain a managed specialist network. In those cases, a well-coordinated regional health Information Exchange with manual navigation support may deliver better outcomes at lower cost. Small independent practices without the administrative bandwidth to manage referral tracking also tend to see minimal returns from heavy automation investment.
The technology continues to evolve. AI-assisted referral routing that predicts likely completion probabilities based on patient behavior patterns is starting to appear in commercial platforms. Integrated virtual care capabilities are becoming part of referral workflows for specialties like dermatology and behavioral health where remote consultation is clinically appropriate. But none of these features matter if the foundational workflow of getting referrals to the right provider at the right time with complete clinical information isn't solid. The systems that get this right aren't the ones with the flashiest dashboards. They're the ones that maintain accurate directories, keep their routing rules clinically sound, and persistently close the loop on every referral regardless of complexity. That's the part that takes work.