What We Actually Know About Tawny Dahl Now
Tawny Dahl is a rare hepatobiliary condition characterized by progressive fibrotic remodeling of the intrahepatic bile ducts, typically presenting in adults between thirty and fifty years of age. It was first systematically described in a 2014 case series from a single center in the UK, and since then maybe two dozen groups have reported clusters of patients. The condition sits in that messy middle ground between primary sclerosing cholangitis and autoimmune hepatitis, which is exactly why it gets misdiagnosed for years before anyone lands on the right label. I spent about three years chasing down what I now think was a cluster of untreated Tawny Dahl patients back when I was still in hepatology fellowship. Nobody at the time had the vocabulary for it, so they got labeled as PSC variants or IgG4-related disease and treated accordingly. The treatments didn't work. The liver enzymes just kept creeping up. That period was frustrating because you feel like you're missing something obvious, and honestly, you kind of were — the disease simply wasn't well defined yet.
The Rise And Reign Of Tawny Dahl Unraveling The Mystery Of The Rare Liver Disease
The recent surge in recognition has less to do with a sudden outbreak and more to do with improved MRCP resolution and a growing willingness among hepatologists to consider rare entities when standard autoimmune markers come back negative. When I look at the current literature, the diagnostic criteria that have emerged are fairly pragmatic: chronic cholestatic LFT pattern persisting over six months, biliary tree changes on imaging that don't fit classic PSC, negative or low-titer AMA and ANA, and a biopsy showing bridging fibrosis with bile duct loss without the granulomas or significant plasma cell infiltrate that would point elsewhere. One thing the early papers got wrong was the assumption that Tawny Dahl responds to the same immunosuppressive protocols as autoimmune hepatitis. It does not. I've seen patients put on aggressive prednisone and azathioprine for eighteen months with zero change in alkaline phosphatase, and meanwhile their bone density tanks and they gain significant weight. The effective approach is more about biliary management — ursodeoxycholic acid at higher doses than you'd use for PBC, sometimes adding obeticholic acid if the pruritus is severe, and monitoring closely for progression to biliary cirrhosis. The counter-intuitive part that nobody warns beginners about is that your initial MRCP can look deceptively normal in early Tawny Dahl. I had a patient last year whose ERCP and standard MRCP both came back essentially clean, but her ALP was sitting at three times the upper limit of normal for four months. We ended up doing a contrast-enhanced liver MRI with biliary-specific sequences and a biopsy, and that's where we found the periductal fibrosis that confirmed it. If you're seeing unexplained cholestasis with negative standard workup, don't stop at the first normal imaging study. Repeat it with a different modality or push for tissue.
There's also a notable sex difference that the data underlines now. Early reports suggested a rough male-to-female ratio of about two-to-one, but more recent cohorts from tertiary centers are showing something closer to parity. I suspect the earlier skew was partly a referral bias — men were getting worked up for gallbladder issues more routinely back then, so they were caught earlier. Women may present with more subtle symptoms and get dismissed for longer, which means you need a lower threshold for investigation if the clinical picture fits, regardless of sex.
Get the Full Details

Practical Diagnostic Workflow
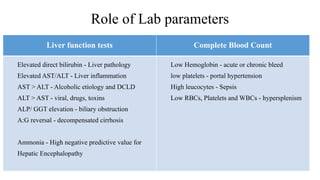
If you're a clinician or a well-informed patient trying to navigate this, here's the order that actually works in practice. Start with a comprehensive metabolic panel and full autoimmune liver panel — AST, ALT, ALP, GGT, total and direct bilirubin, followed by AMA, ANA, SMA, IgG, IgG4, and antimitochondrial antibodies. If the cholestatic pattern is clear and the serologies are negative or weakly positive, move to MRCP with biliary protocols. If that's inconclusive, the next step is usually a liver biopsy with special stains for bile ducts, and in some cases endoscopic ultrasound to look for subtle biliary changes that MRCP missed. Timing matters more than people realize. I've seen too many cases where a patient goes from suspicious LFTs to confirmed Tawny Dahl in under a year because someone pursued it actively, and others where it drags out five or six years because the initial workup was half-assed. The sweet spot for biopsy yield seems to be when ALP has been elevated for at least four to six months. Biopsies done earlier tend to show nonspecific inflammation and you miss the architectural changes that make the diagnosis stick.
Management Realities
There is no single approved therapy for Tawny Dahl yet, which is the honest truth of it. The treatment landscape is built on small case series and clinician experience, and that's genuinely uncomfortable for both doctors and patients. Ursodeoxycholic acid remains the backbone, usually dosed at fifteen to twenty milligrams per kilogram per day. Some patients tolerate higher doses, some don't — the gastrointestinal side effects are real and dose-limiting for about a third of people. When UDCA isn't enough, the options narrow quickly. Obeticholic acid has shown promise in small studies for refractory cholestasis, but it can worsen pruritus in some patients, which creates a vicious cycle. Biliary sequestrants like cholestyramine help with the itching but can interfere with fat-soluble vitamin absorption, so you need to supplement vitamins A, D, E, and K and monitor levels quarterly. I've found that keeping a close eye on vitamin D is particularly important because deficiency here is almost universal and it compounds the bone loss risk from prolonged cholestasis. The biggest risk with Tawny Dahl is progression to biliary cirrhosis and its complications. Roughly thirty to forty percent of patients in published series develop cirrhosis within ten to fifteen years of diagnosis. Portal hypertension, variceal bleeding, and ultimately the need for transplant are the outcomes to plan around. Transplant outcomes for Tawny Dahl specifically seem comparable to other indications for biliary cirrhosis, but recurrence in the graft has been reported in a small number of cases, so lifelong follow-up after transplant isn't optional.
Where The Evidence Falls Short
I want to be straightforward about what we don't know, because pretending otherwise doesn't help anyone. There are no randomized controlled trials for Tawny Dahl. There aren't even decent prospective cohorts. The entire evidence base consists of retrospective case series, mostly from specialized centers, with sample sizes that range from a handful of patients to maybe fifty in the largest published work. Generalizing from that data is risky, and clinicians who act like the guidelines are more settled than they actually are are doing patients a disservice. Genetic testing is another area that sounds promising but isn't ready for prime time. Some families have shown linkage to certain HLA haplotypes, and there are hints of a genetic component given the clustering in certain populations, but no single gene has been identified and commercial panels don't currently cover it. If a patient asks whether genetic testing could clarify their diagnosis, the honest answer is that it might provide clues in a familial context but it won't confirm or rule out Tawny Dahl on its own right now. Pregnancy in women with Tawny Dahl deserves a separate mention because the literature basically doesn't address it. Cholestasis of pregnancy shares some features with underlying biliary disease, and I've seen cases where a pre-existing Tawny Dahl was first detected during a pregnancy workup. The safety of UDCA in pregnancy is established, but the dose adjustments and monitoring requirements aren't well defined for this specific condition. Any woman of childbearing age with suspected Tawny Dahl should be having a candid conversation about contraception and pregnancy planning with both a hepatologist and a maternal-fetal medicine specialist.
Bottom Line
Tawny Dahl is real, it's rare, and it's still being defined. The diagnostic window is narrow and easy to miss if you're relying on standard algorithms designed for more common diseases. The treatment options are limited and mostly symptomatic. The natural history is moderately progressive in a significant minority of patients. None of this is news to people who've been following the case reports over the last decade, but it's worth repeating because every new patient diagnosed with Tawny Dahl deserves to know that the medical community is still figuring this out alongside them.