Understanding Blood Group Compatibility in Practice
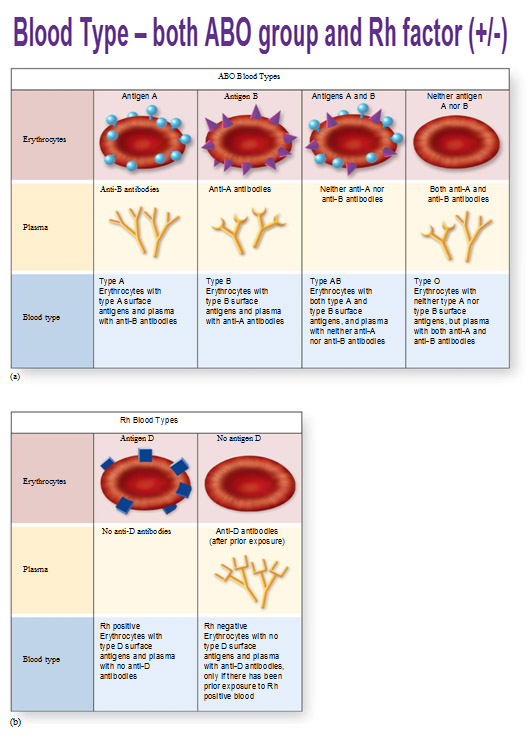
The Rh factor is a protein found on the surface of red blood cells. If you have it, you are Rh positive. If you do not, you are Rh negative. That is the basic definition. The positive variant is far more common. Across most global populations, roughly 85 percent of people carry it. The negative variant clusters more heavily in certain regions, like Europe, where about 15 percent of the population lacks the antigen. I ran into a real issue a few years ago while reviewing compatibility charts for a university lab project. I was cross-referencing Rh-positive individuals as recipients and noticed that most standard sources simply state "Rh positive can receive Rh positive or Rh negative." That is technically correct, but it glosses over an important detail that matters in practice. The D antigen — the specific protein that defines Rh status — comes in subtypes. Some people express a weaker form called D partial or D variant. Standard typing will flag them as positive, but they may lack certain epitopes that a conventional positive donor carries. If you transfuse without checking for weak D or partial D variants, an immune response can still occur. It is rare in routine care, but in hematology clinics, it shows up. The workaround is simple enough: if a patient has an antibody screen that is positive despite being typed as Rh positive, run a molecular test or a thorough antibody identification panel before issuing more blood. It adds a day to the process, but it prevents hemolytic reactions that testing alone would miss. Here is another thing most guides skip. Rh compatibility is not just about the D antigen. There are over 50 known Rh system antigens, though D, C, E, c, and e are the clinically significant ones. When we talk about being Rh positive, we are almost always referring only to D. The other antigens can still trigger immune reactions. A patient who is missing the C antigen, for example, can develop anti-C antibodies even if they are D positive. In transfusion medicine, extended phenotyping or genotyping is standard for patients who need chronic transfusions, like those with sickle cell disease. Without it, you end up matching only D and leaving the rest to chance, which increases the risk of alloimmunization over time.
How Rh Testing Actually Works in a Lab
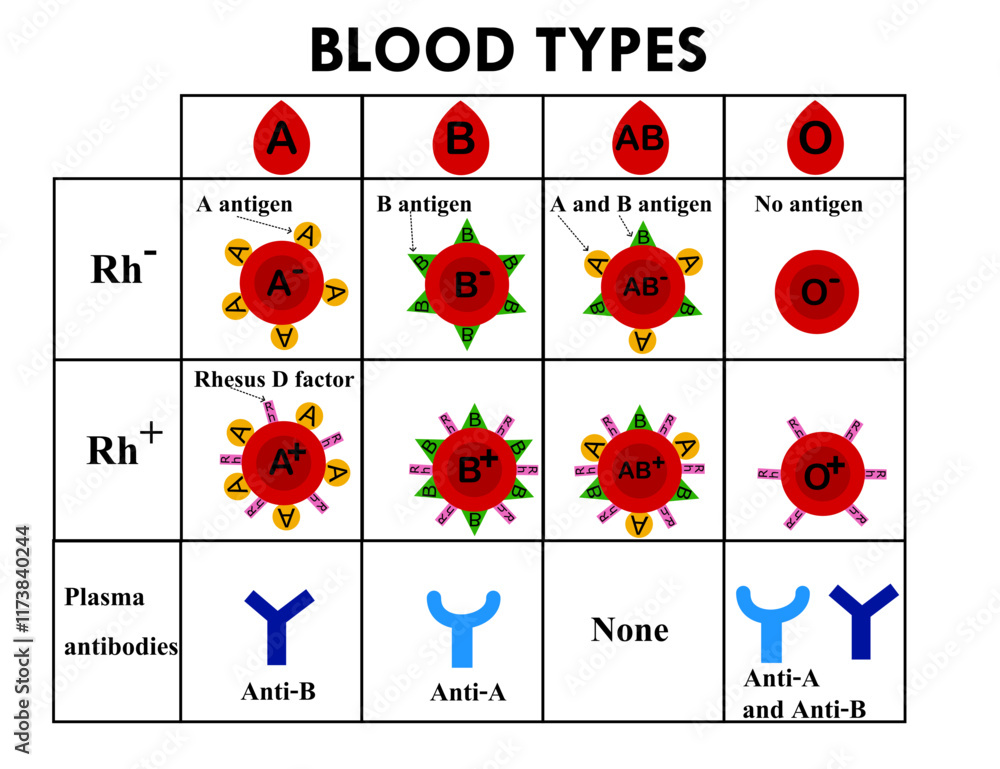
The process starts with a blood sample. Two main methods exist. The tube method uses anti-D reagent mixed with red cells, then centrifugation to check for agglutination. The rapid method uses a card or slide and gives results faster but is less sensitive. Neither is perfect. Weak D positives, for instance, can be missed entirely on a slide test. That is why many labs default to the tube method or an acid elution test for confirmation. Once the D antigen is confirmed present, the sample is classified as Rh positive. That result then feeds into broader blood typing, which also checks ABO antigens. The full blood type — like A positive or O negative — determines both what a person can donate and what they can safely receive. The Rh positive recipient can accept both Rh positive and Rh negative blood. The reverse is not true. An Rh negative recipient exposed to Rh positive blood will typically form anti-D antibodies, which complicates future transfusions and pregnancies.
Why Rh Positivity Matters Beyond Transfusions
Pregnancy introduces a different layer of complexity. If an Rh negative mother carries an Rh positive fetus, which happens when the father passes on the D antigen, fetal red cells can enter maternal circulation during delivery or trauma. The mother immune system sees the D antigen as foreign and produces anti-D antibodies. This is hemolytic disease of the fetus and newborn, or HDFN. It is manageable today because of Rho(D) immune globulin, commonly known as Rhogam. It is administered around 28 weeks of pregnancy and within 72 hours after delivery. The shot works by coating any fetal Rh positive cells in the mother's bloodstream before her immune system can mount a response. It prevents sensitization entirely in the vast majority of cases. The timing matters. If Rhogam is given too late, after sensitization has already occurred, it will not reverse existing antibodies. The fetus may already be at risk. That is why prenatal antibody screening is routine. I have seen cases where a patient assumed she was fine because her first pregnancy went smoothly, only to have complications in the second because the initial Rhogam dose was never administered. The medical record had no mention of it. It is a small detail that gets overlooked, and it carries real consequences.
Get the Full Details
Common Misconceptions
There is a persistent myth that Rh positive blood is "stronger" or superior in some way. It is not. It is simply more common. Populations with historically high exposure to certain pathogens, like Plasmodium falciparum in malaria-endemic regions, may have selected for certain blood type distributions, but the Rh factor itself does not confer broad protective advantages. The science here is still developing. Some studies suggest weak associations between Rh type and conditions like preeclampsia or certain infections, but nothing definitive enough to change clinical practice. Another misconception is that Rh positive people can only receive Rh positive blood. They can receive Rh negative blood just fine. The reverse is the constraint. Rh negative individuals must avoid Rh positive transfusions unless no alternative exists, and even then, only after careful consideration. In emergency situations where type-specific blood is unavailable, O negative is used for Rh negative patients because it lacks both ABO and Rh antigens, minimizing immediate reaction risk.
What You Should Do If You Know Your Rh Status
If you are Rh positive, there is not much special action required. Your blood is compatible with a large portion of the population, which makes you a versatile donor. Rh positive women do not need Rhogam during pregnancy since their bodies already carry the D antigen. Rh positive men and women alike should simply ensure their blood type is documented, ideally through a formal test rather than relying on hearsay. Home test kits exist, but they are not as reliable as laboratory typing, especially for distinguishing weak D variants. If you are Rh negative, the advice is different. Keep records. Inform any healthcare provider before procedures or pregnancies. If you are a woman of childbearing age, discuss Rhogam prophylaxis with your obstetrician early. Do not assume prior pregnancies were uncomplicated just because you had no known issues. Silent sensitization can occur without obvious symptoms.
Limitations of Current Typing Methods
Even standard Rh typing has gaps. Chimerism, bone marrow transplants, and certain leukemias can alter red cell antigen expression. A patient who received a bone marrow transplant from an Rh positive donor may test as positive for the D antigen, but their original Rh status and associated antibodies may still be clinically relevant. I encountered this in a hospital setting where a patient's transfusion record showed Rh positive status, but their historical antibody profile indicated they had formed anti-D before the transplant. The current typing did not reflect the full picture. The fix was pulling pre-transplant records and cross-referencing them, which took additional time but prevented a potential error. Another limitation is population diversity. Most Rh typing research and reference ranges come from European-derived populations. Allele frequencies differ in African, Asian, and Indigenous populations. Some groups have higher rates of weak D variants or rare Rh phenotypes that standard testing panels are not designed to catch. Labs in diverse regions should have protocols that account for this, but not all do. If you are in an area with a broadly mixed population, asking your provider whether they perform extended Rh genotyping is reasonable, especially if you have a history of transfusions or pregnancy complications.