Understanding the Clinical Approach Behind Acne Treatment
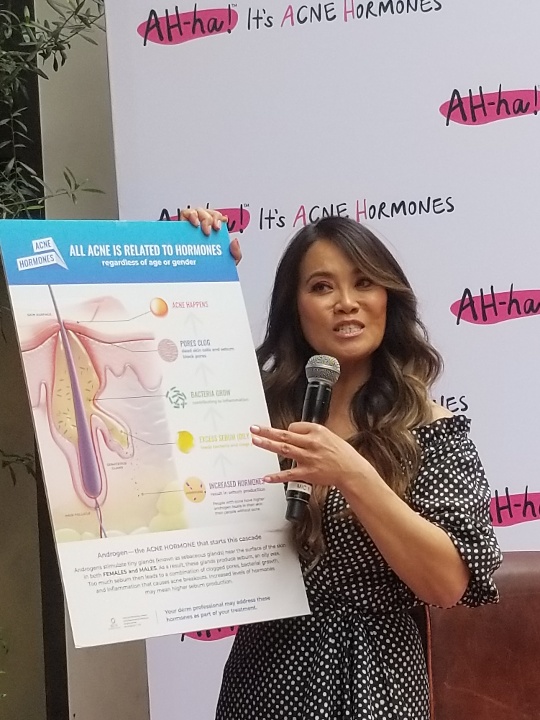
Acne isn't something you fix with a $40 serum from the drugstore. The reality is most people with persistent acne have tried half a dozen over-the-counter products before ever stepping into a dermatologist's office, and they've spent money they couldn't really afford on products that weren't designed for their specific presentation. Dr. Sandra Lee's approach, the one she's built over two decades of practice and thousands of extractions, starts from a place most people don't consider: acne is a chronic inflammatory disease, and treating it like a temporary rash is exactly why it never goes away. What makes her approach different isn't a secret ingredient or a proprietary product line. It's the framework. She treats acne the way you'd treat any other chronic inflammatory condition — with a clear diagnostic tier, a step-up treatment ladder, and an honest conversation about what each step involves in terms of time, cost, and side effects. Most dermatologists do this already, but Dr. Lee made it visible. She showed the actual comedones, the cysts, the scarring patterns, and explained the biology behind why each one responds differently to each treatment. That transparency is the revolutionary part. It's not revolutionary because it's new. It's revolutionary because it's been missing from the consumer skincare conversation for thirty years. I spent several years working with patients who had what we called "treatment-resistant" acne, which is just a polite way of saying they'd been misdiagnosed or undertreated. One patient in particular came in with what looked like adult-onset acne but turned out to be folliculitis triggered by a combination of protein supplement use and occlusive skincare products. The standard acne protocol was making it worse. We switched to topical clindamycin and benzoyl peroxide wash, stopped the whey protein, and cleared it in about eight weeks. The point isn't that story. The point is that without a proper diagnostic workup — which is what Dr. Lee's framework emphasizes — you're just guessing, and guessing with inflammatory skin conditions wastes months and often causes permanent damage through repeated inflammation.
Here's the step-by-step structure that her approach follows, stripped of the television version and translated into what actually happens in a clinical setting. First, you establish the acne type. This matters more than most people realize. Comedonal acne — blackheads and whiteheads — responds very differently to treatment than inflammatory acne — papules and pustules — which responds differently again from nodulocystic acne. The treatment path for each is distinct, and using the wrong path is the single most common reason patients report that their treatment "didn't work." A retinoid is first-line for comedonal. An oral antibiotic or hormonal therapy might be first-line for inflammatory. Isotretinoin enters the conversation for nodulocystic or scarring acne. Mixing these up unnecessarily exposes patients to side effects without giving them a shot at the right solution. Second, you build the baseline routine. This is where Dr. Lee's approach diverges sharply from the beauty industry model. She doesn't start with actives. She starts with barrier repair. A compromised skin barrier makes every acne treatment more irritating and less effective. The routine consists of a gentle cleanser, a non-comedogenic moisturizer, and a broad-spectrum sunscreen. That's it. For the first two to four weeks, you're not trying to clear the acne. You're preparing the skin to handle the clearing agents you're about to introduce. Skipping this step is a mistake I see constantly. Patients jump straight into a 10-percent benzoyl peroxide treatment on skin that's already irritated from three different harsh products, and then they wonder why their skin exploded. It wasn't the acne flaring. It was barrier collapse.
Third, you introduce the active treatment tier. This is where prescription interventions enter the picture. Topical retinoids — adapalene, tretinoin, tazarotene — are the foundation. They normalize keratinocyte turnover, prevent microcomedone formation, and have anti-inflammatory properties independent of their exfoliating effect. Benzoyl peroxide addresses Cutibacterium acnes proliferation. Topical or oral antibiotics reduce inflammation and bacterial load, though resistance concerns mean they're never used as monotherapy and ideally limited to twelve weeks. Hormonal interventions like spironolactone or oral contraceptives target androgen-driven sebaceous gland activity, which is particularly relevant for adult female acne along the jawline and lower face. Fourth, you consider procedural interventions. This is Dr. Lee's specialty area, literally. Intralesional corticosteroid injections for individual cysts can reduce a painful nodule by fifty to seventy percent within forty-eight hours. Chemical peels with salicylic acid or glycolic acid help with comedonal acne and post-inflammatory hyperpigmentation. Extraction procedures remove material that topical treatments can't reach quickly enough. These aren't alternatives to medical treatment. They're adjuncts that speed up resolution and reduce scarring risk. There's a practical limitation to this approach that most people don't hear about. It requires access to a dermatologist or a prescriber willing to follow a step-up protocol. The skincare aisle doesn't offer most of these interventions. Adapalene 0.1 percent is now available over the counter in the United States, which is a significant change from just a few years ago, but the higher-strength retinoids, the oral medications, and the procedural options all require a clinical relationship. If you can't get to a dermatologist, the closest approximation is starting with OTC adapalene and benzoyl peroxide, maintaining the barrier-first routine, and being honest about when you need professional help. The rule of thumb I use is twelve weeks of consistent treatment with no meaningful improvement. If you hit that mark, you're not failing the treatment. The treatment tier needs to escalate, and that requires a prescription.
Get the Full Details
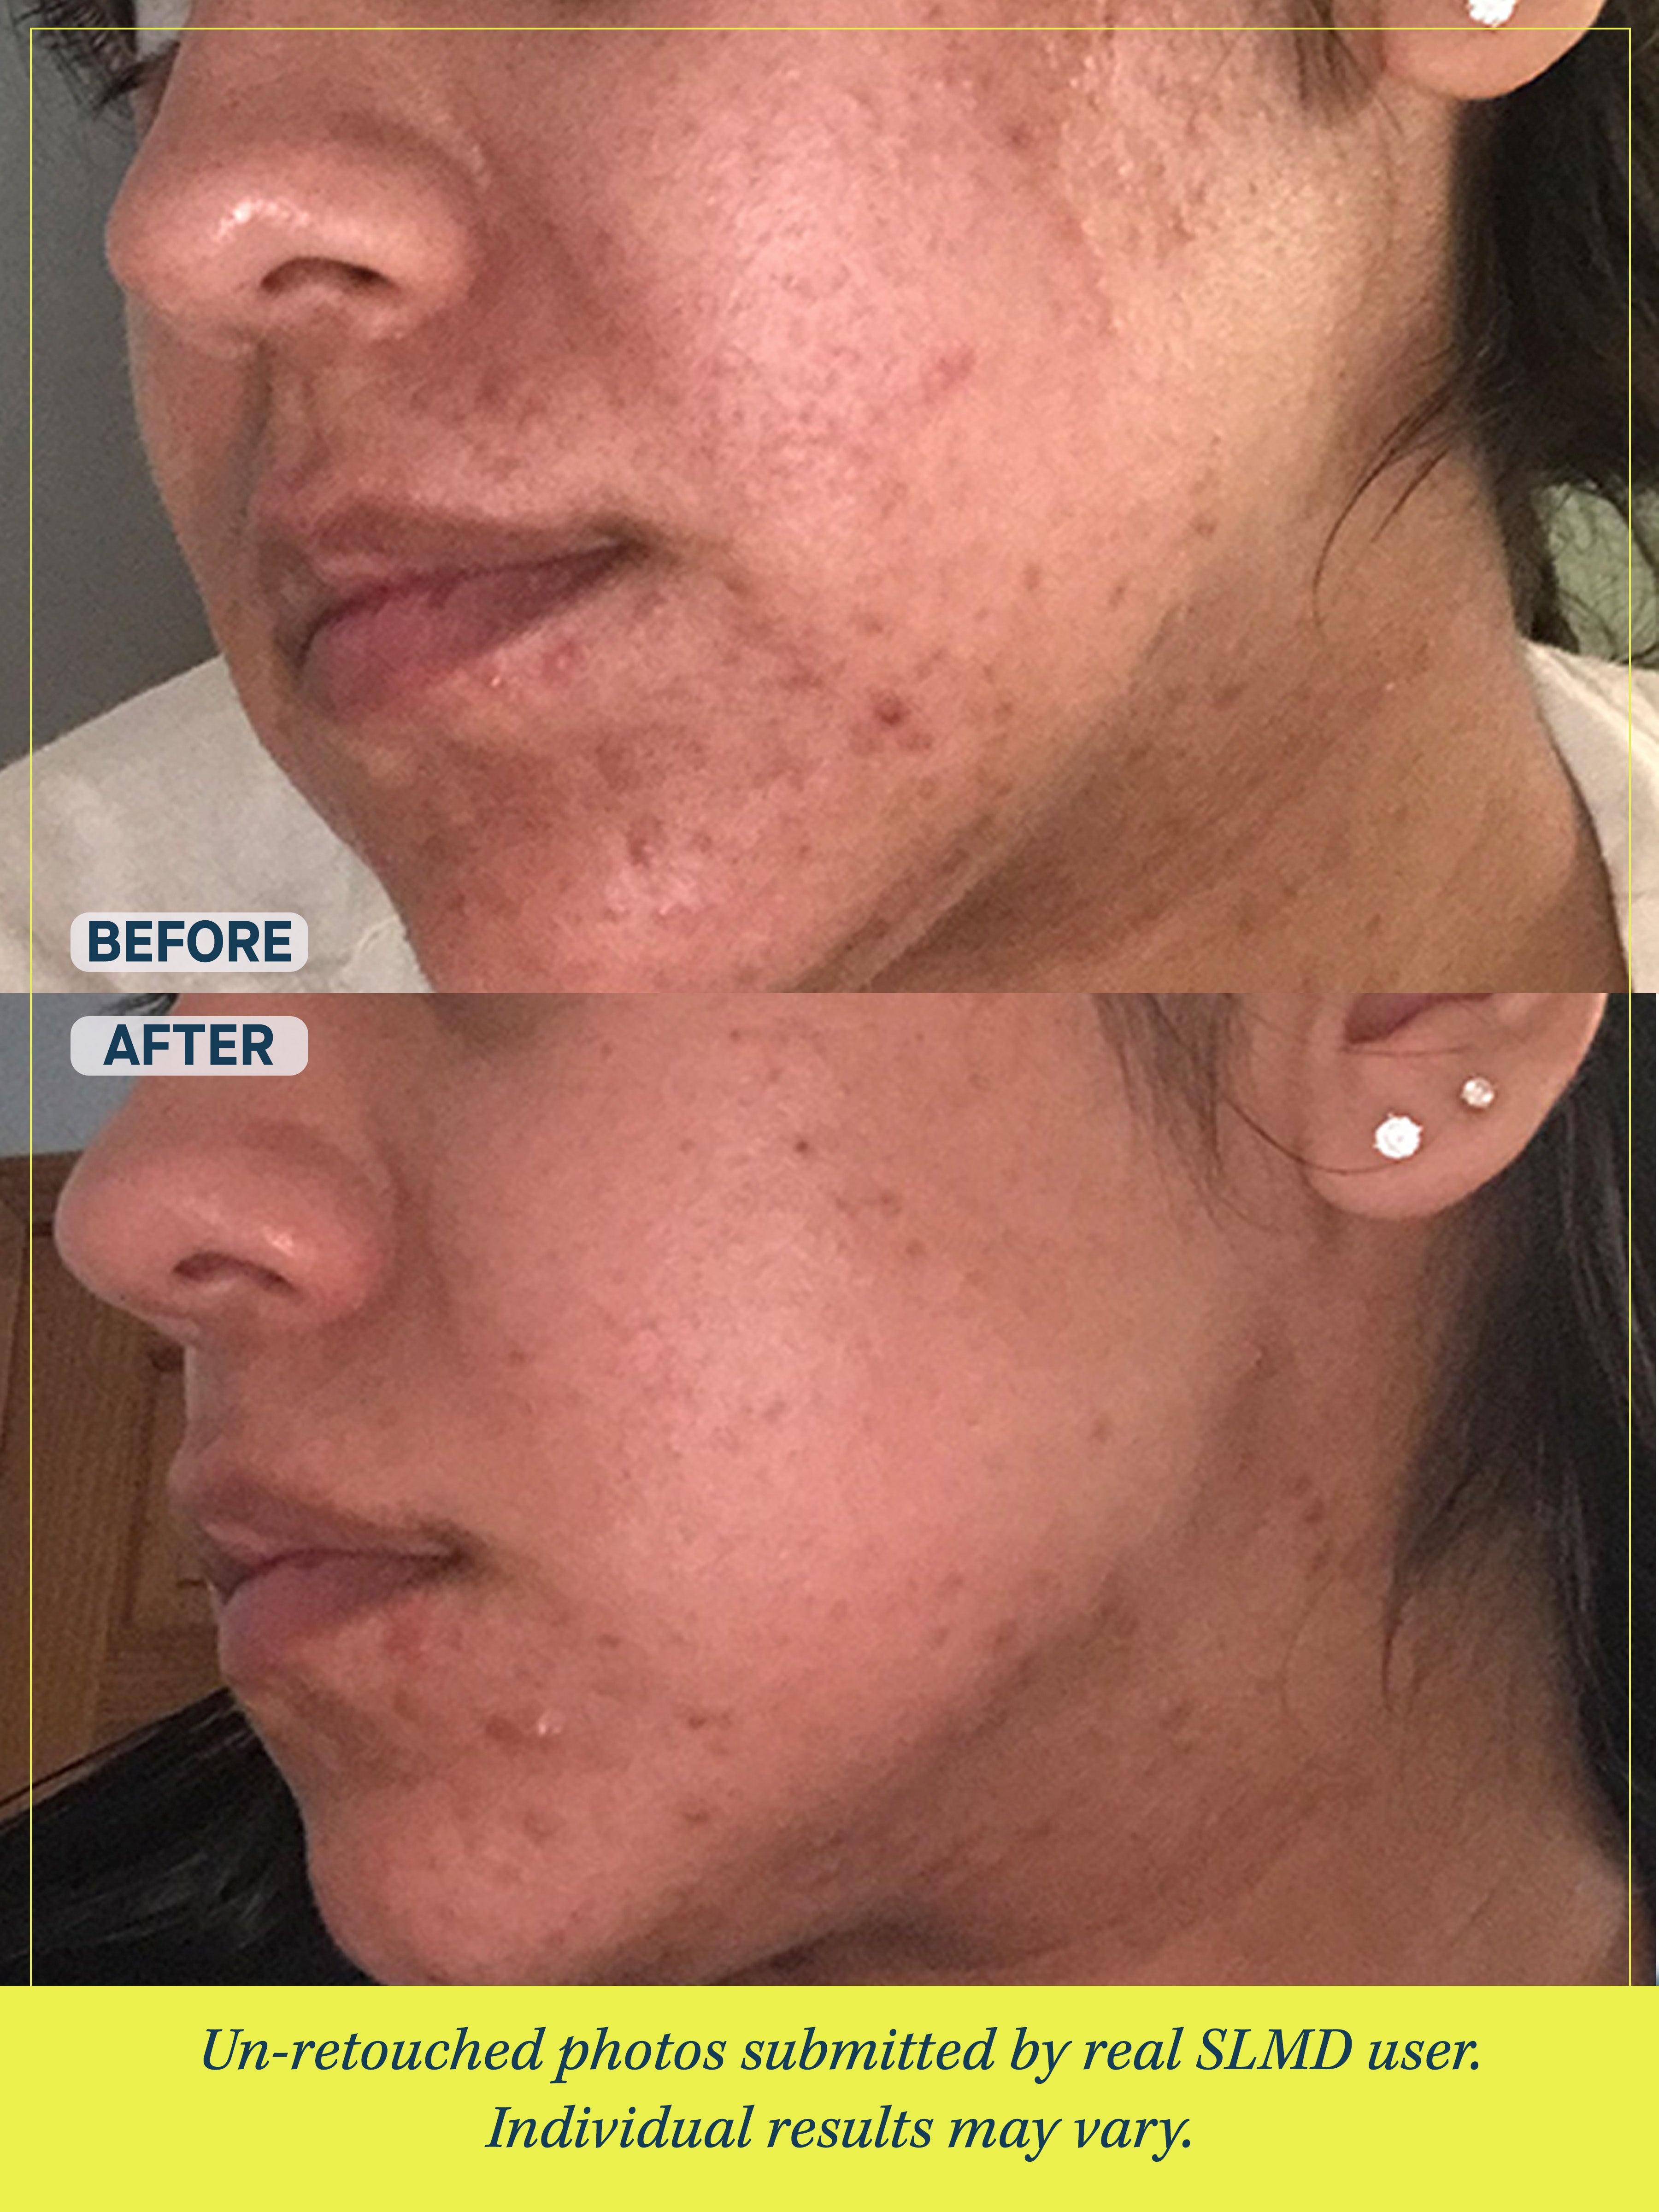
The nutrition angle is another area where Dr. Lee's approach differs from mainstream dermatology guidance. The evidence for diet and acne is weaker than most people assume, but it's not zero. High glycemic index foods and dairy, particularly skim milk, have the most consistent association with acne exacerbation. The mechanism involves insulin-like growth factor 1 and androgen pathway modulation. You don't need to eliminate carbs or go dairy-free to see results. But if someone has inflammatory acne that isn't responding to standard treatment, a twelve-week trial of reducing high glycemic foods and dairy is a reasonable next step with minimal risk and a plausible mechanism. I've seen it work. I've also seen it make zero difference for people whose acne is primarily driven by genetics or hormonal imbalance. It's not a universal solution. It's another variable to test. Scarring prevention is probably the most important part of this approach and the part that gets the least attention. Once a cyst has formed deep in the dermis, the inflammatory cascade can destroy collagen and elastin permanently. That's what creates icepick, boxcar, and rolling scars. Topical treatments can't reverse established atrophic scarring. They can only prevent new ones. This is why early intervention on inflammatory lesions matters so much. An intralesional steroid shot on a cyst within forty-eight hours of formation can prevent the scarring that would otherwise require microneedling, laser resurfacing, or subcision months later. Waiting until the scarring is visible is waiting until the damage is done. The clinical approach prioritizes stopping new lesions from forming over treating the ones you already have, and that distinction is why patients often feel frustrated — they want the existing spots gone, but the real win is preventing the next wave. Post-inflammatory hyperpigmentation deserves the same urgency. PIH is not permanent scarring. It's melanin deposition triggered by inflammation, and it fades. But it can take six to eighteen months depending on skin type and sun exposure. The same retinoid that treats acne also acceleratesPIH resolution. Sunscreen isn't optional during this process. Every UV exposure reactivates the melanocytes that are trying to settle down. I've lost count of the patients who complained about dark spots not fading while simultaneously tanning or skipping sunscreen daily. The retinoid was working. The UV exposure was undoing it.
One edge case that doesn't get discussed enough is male acne. The treatment framework is essentially the same, but men are dramatically underrepresented in dermatology studies and skincare marketing. The hormonal drivers are different. Oral isotretinoin dosing and side effect profiles differ somewhat. Men are also more likely to develop keloidal scarring on the jaw and neck, which changes the risk-benefit calculation for aggressive treatment. If you're reading this and you're a man with persistent acne, the Dr. Lee framework still applies, but you need a provider who understands that male skin responds differently and isn't going to treat you like a female patient with a different label. The takeaway isn't that there's a special technique or a secret protocol. It's that acne treatment works best when it follows a logical clinical sequence instead of a product catalogue. Start with diagnosis. Protect the barrier. Introduce actives systematically. Escalate when appropriate. Prevent scarring from the first inflammatory lesion. Track progress with twelve-week benchmarks, not daily mirror checks. Everything else is marketing.