Understanding Gas Exchange in the Lungs
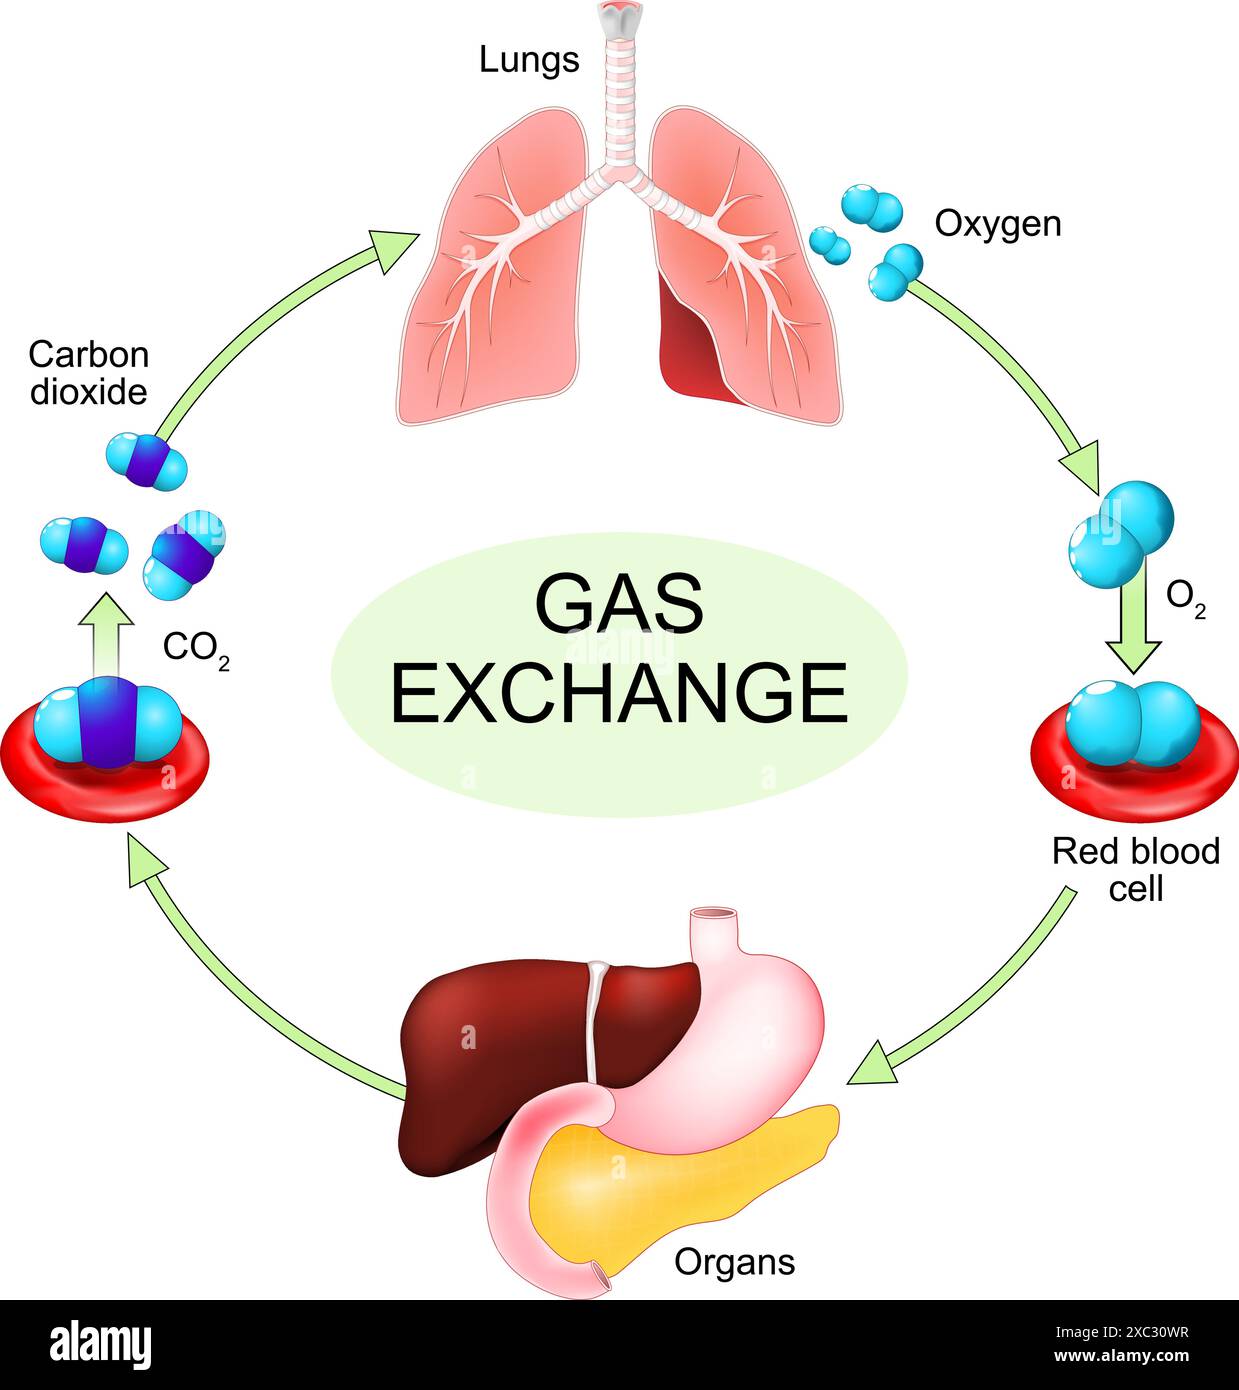
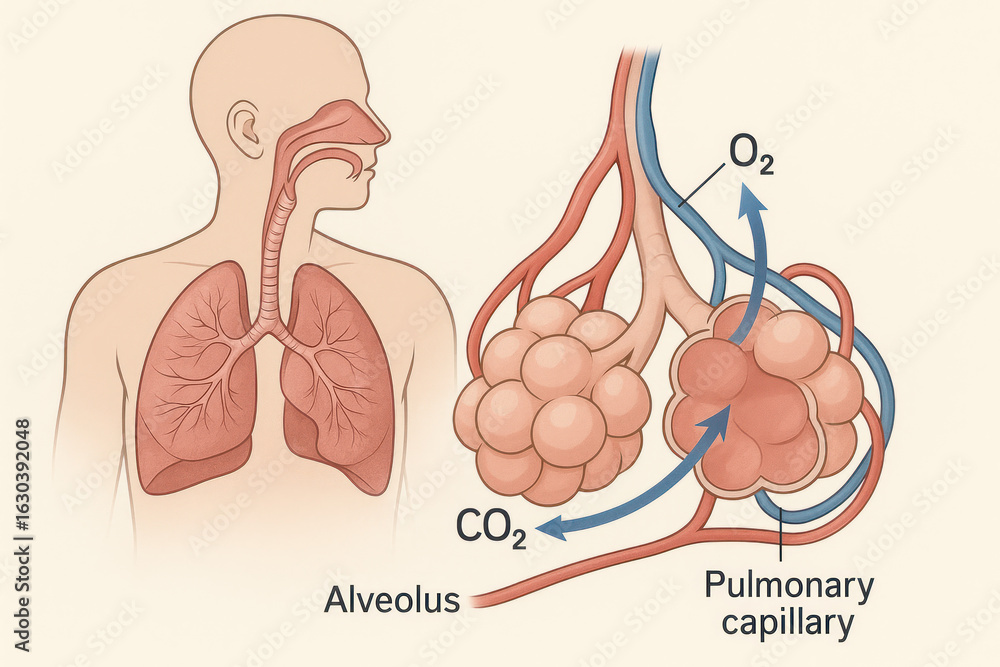
The respiratory system isn't some mystical organ setup. It's a plumbing problem solved by evolution. Air goes in, oxygen gets pulled across a membrane, carbon dioxide gets pushed the other way, and then it all goes back out. That's it. The complexity comes from scale and precision, not magic. When I first studied this in med school, we spent weeks on alveolar architecture and didn't really get it until I held a pair of inflated lungs in the dissection lab. They're light. Almost absurdly light. A total of about three hundred million alveoli per lung, each one barely visible to the naked eye, but collectively they create a surface area roughly the size of a tennis court. That's where the actual exchange happens. The mechanism itself is straightforward diffusion. Oxygen moves down its partial pressure gradient from the alveolus into the capillary blood. Carbon dioxide does the reverse. Fick's law of diffusion governs everything here. The rate depends on surface area, membrane thickness, and the pressure gradient. Change any of those variables and gas exchange changes with them. Simple physics. Brutally effective physics.
How the System Actually Works Under Stress
I remember working a clinical rotation where a patient came in with severe pneumonia. Most of the textbook knowledge breaks down when the alveoli fill with fluid. The diffusion distance increases dramatically because oxygen has to cross not just the alveolar-capillary membrane but also this inflammatory exudate. Their oxygen saturation dropped to around 82 percent on room air. We put them on high-flow nasal cannula at sixty liters per minute with forty percent FiO. They stabilized within twenty minutes. The point isn't the case itself. It's that the respiratory system has compensatory mechanisms that most people don't think about. Chemoreceptors in the carotid bodies and aortic arch monitor arterial oxygen, carbon dioxide, and pH. When PaCO rises even slightly above forty millimeters of mercury, the drive to breathe increases exponentially, not linearly. That's why hypercapnia can become a quiet killer in COPD patients — their chemoreceptors reset and they end up relying more on hypoxic drive. Give them too much oxygen without monitoring and you can suppress their respiratory drive entirely.
Dead Space and Why It Matters
Anatomical dead space is about one fifty milliliters in a healthy adult. That's the air remaining in the trachea, bronchi, and bronchioles after exhalation. It doesn't participate in gas exchange. Then there's alveolar dead space, which is normally near zero but increases in conditions like pulmonary embolism where alveoli are ventilated but not perfused. The physiologic dead space is the combination of both. In practice, dead space becomes a real problem during mechanical ventilation. I once worked with a patient on a ventilator who had a dead space fraction approaching forty percent of each tidal volume. That meant most of what we were ventilating wasn't actually participating in gas exchange. We had to increase minute ventilation significantly to maintain acceptable PaCO levels. The math is straightforward: alveolar ventilation equals tidal volume minus dead space volume, multiplied by respiratory rate. Get this wrong and you're either hyperventilating or letting CO accumulate without realizing it.
Get the Full Details
Common Misunderstandings About Breathing
People often think breathing is primarily about oxygen intake. It's not. It's about carbon dioxide elimination. Oxygen is abundant in ambient air at roughly twenty-one percent. Carbon dioxide is only about zero point zero four percent. The body cares far more about keeping CO tightly regulated between thirty-five and forty-five millimeters of mercury than it does about oxygen, which has a much wider safe range. Hyperventilation before a dive, for example, lowers CO enough that you can pass out from hypoxia without feeling the urge to breathe. That's how shallow water blackout kills trained swimmers. Another misconception is that deep breathing is inherently better. It isn't. Optimal breathing at rest is quiet, nasal, diaphragmatic, and occurs at about twelve to fourteen breaths per minute. Forceful deep breaths activate different mechanoreceptors and can actually decrease gas exchange efficiency by causing uneven ventilation distribution due to gravity-dependent perfusion gradients. The ventral regions of the lungs receive more blood flow than the dorsal regions in an upright person, and matching ventilation to that perfusion pattern is what keeps the V/Q ratio close to one.
What Happens When the System Fails
Pulmonary fibrosis is a good example of structural failure. The alveolar walls thicken with scar tissue. Surface area decreases. Membrane thickness increases. Both changes work against diffusion. Oxygen transfer becomes so impaired that patients are often hypoxemic at rest and crash hard with minimal exertion. There's no workaround for advanced fibrosis other than transplantation. Early intervention with immunosuppressants can slow progression in some cases, but the damage is fundamentally architectural and largely irreversible. Atelectasis is another common clinical problem that illustrates the system's fragility. After surgery, especially abdominal or thoracic procedures, patients breathe shallowly to avoid pain. This leads to alveolar collapse, particularly in the dependent lung regions. Within hours, ventilation-perfusion mismatch develops. The shunt fraction can rise significantly. We use incentive spirometry and early mobilization to prevent it. It's cheap, simple, and reduces postoperative pulmonary complications by roughly twenty to thirty percent based on the literature.
Practical Takeaways
The respiratory system works through passive physical principles most of the time. You don't need to understand surface tension equations to breathe, but knowing that surfactant reduces alveolar surface tension and prevents collapse at low volumes explains a lot about neonatal respiratory distress syndrome and ARDS management. Without surfactant, the smaller alveoli would empty into the larger ones due to Laplace's law. Pulmonary edema from positive pressure ventilation can also wash out surfactant, creating a vicious cycle. If you're studying this for exams, focus on the relationships rather than memorizing isolated facts. Know how altitude affects partial pressures. Understand why a right-to-left shunt causes hypoxemia that doesn't improve much with supplemental oxygen while a V/Q mismatch does. Recognize that the respiratory control system prioritizes pH and PaCO over PaO under normal circumstances. These connections matter more than any single number.


