What Actually Happens When You Get Treated for Pyelonephritis
Pyelonephritis is a bacterial infection of the kidneys, usually caused by E. coli traveling up from the urinary tract. It is not the same as a bladder infection, and it does not resolve on its own without antibiotics. The difference between a standard UTI and pyelonephritis matters because the recovery trajectory is completely different, and people who under-treat it end up in the hospital anyway. I worked in urology support for several years, and the pattern I saw constantly was patients who felt 80 percent better on day two of antibiotics, stopped worrying about it, and then came back three weeks later with a relapse or an abscess. That is not a criticism of the patients. It is just a pattern. The infection is deep in the renal parenchyma, and the tissue needs time to actually heal even after the bacteria are mostly gone.
The Pyelonephritis Recovery Timeline How Long Does Healing Really Take
Here is the straightforward timeline based on clinical data and the typical course I observed in practice. Days 1 to 3: This is the acute phase. Fever, flank pain, nausea, and sometimes vomiting are present. Once appropriate antibiotics are started, fever usually breaks within 48 to 72 hours. That is the single most important indicator that the treatment is working. If fever persists past day three, the antibiotic may need to be changed or imaging needs to be done to rule out an abscess or obstruction. Blood cultures are drawn at admission in most hospital protocols, and urine culture results come back in 24 to 48 hours to confirm the organism and adjust antibiotics accordingly. Days 3 to 7: Symptoms continue to improve. Pain drops from severe to manageable. Appetite returns. Most patients with uncomplicated acute pyelonephritis are still on oral antibiotics at this stage if they were admitted, or transitioning from IV to oral if they started in the hospital. The total antibiotic course is typically 7 to 14 days depending on the organism and severity. I have seen providers prescribe 7-day courses for mild cases with fluoroquinolones, which is acceptable per IDSA guidelines, but 10 to 14 days is more common in real-world practice because clinicians tend to hedge when kidney tissue is involved.
Days 7 to 14: This is the tissue recovery window. The bacteria may be cleared, but the inflamed renal tissue is still healing. Fatigue lingers for many people. Some report a low-grade sense of malaise or mild flank discomfort even though the infection is gone. This is normal. Pushing back into heavy work or exercise before day 10 usually just prolongs the fatigue. I watched patients consistently underestimate this phase and return to full activity on day five, then feel wiped out for another week. The timeline is not linear. Weeks 2 to 4: For uncomplicated cases, most people are essentially back to normal by the end of week two. For complicated cases, or patients who required hospitalization, IV antibiotics, or had an underlying anatomical issue, recovery can stretch to four to six weeks. Complete resolution of inflammation on imaging, if it was obtained, usually happens around week three, but you do not need imaging to confirm recovery unless symptoms persist. Complicated cases: This category includes patients with kidney stones, urinary obstructions, diabetes, immunosuppression, or structural abnormalities. Recovery in these cases is slower and less predictable. The initial infection may clear, but the underlying problem keeps the system vulnerable. I had a case where a patient with an undiagnosed ureteral stricture had recurrent fevers two weeks after a seemingly successful antibiotic course. A CT urogram revealed the obstruction, and once it was stented, the infections stopped. The lesson here is that recurrent pyelonephritis should always prompt imaging, not just another round of antibiotics.
Get the Full Details

Factors That Change the Timeline
Several variables shift the recovery window significantly, and they are worth understanding before you estimate your own timeline. Age and immune status: Older adults and immunocompromised patients tend to clear infections more slowly. Fever may take longer to resolve, and fatigue lasts longer. In one study, patients over 65 took roughly 40 percent longer to achieve defervescence compared to younger patients on the same antibiotic regimen. Antibiotic choice and resistance: If the causative organism is resistant to the initial antibiotic, the clock resets. Delay in appropriate coverage is the single biggest predictor of prolonged hospital stays and worse outcomes. Empiric therapy often starts with ceftriaxone or a fluoroquinolone, then gets adjusted once culture results arrive. Sometimes the adjustment means a longer total course.
Hydration status: Dehydration slows renal clearance and delays symptom resolution. Patients who maintain good oral hydration during treatment tend to feel better faster. I have no hard data on the exact magnitude of this effect, but the physiological mechanism is straightforward: better perfusion means better antibiotic delivery to the infected tissue. Pregnancy: Pyelonephritis in pregnancy is treated more aggressively because of the risk of preterm labor and sepsis. Hospitalization is standard, IV antibiotics are typical, and the recovery timeline is monitored more closely. Even after discharge, follow-up urine cultures are usually done at one-week intervals until delivery.
What Recovery Actually Feels Like
Most people expect a sharp line between sick and recovered. It does not work that way. The fever goes away first, then the pain, then the nausea, then the fatigue. Each symptom clears on its own schedule. You might be afebrile and pain-free by day four but still unable to do anything more demanding than grocery shopping until day ten or so. One thing patients consistently report is that the first few days of feeling better feel almost too good. That is a trap. The kidney tissue is still damaged internally. Rest during the first full week is not optional advice. It is physiologically necessary. Skipping it does not speed things up. It just spreads the recovery out over a longer, more unpredictable period.

Pitfalls That Delay Recovery
Stopping antibiotics early: This is the most common mistake. Feeling better is not the same as being cured. Stopping at day five because you feel fine leaves residual bacteria that can rebound into a more resistant infection. Always finish the prescribed course. Ignoring persistent fever: If you are on day three of antibiotics and still running a fever above 100.4 F, contact your provider. This does not necessarily mean failure, but it does warrant a reassessment. Repeat cultures, imaging, or antibiotic changes may be needed. Self-diagnosing a UTI instead of pyelonephritis: Many people with early kidney infection assume it is a bladder infection and try to treat it at home. By the time they present to a clinic or ER, the infection has already advanced. flank pain and fever are the distinguishing features. If you have those plus urinary symptoms, seek care promptly rather than waiting.
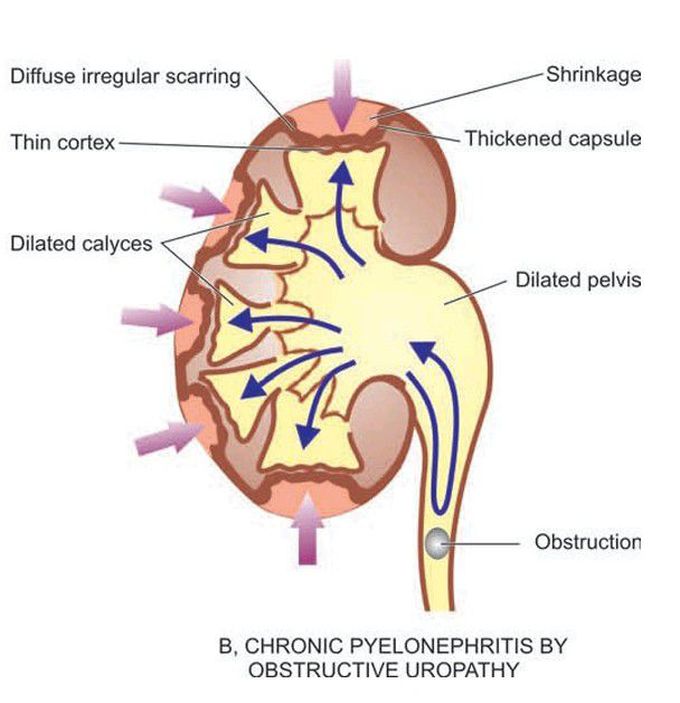
Underlying anatomical issues: As mentioned earlier, recurrent pyelonephritis is often a sign of an untreated structural problem. Stones, strictures, vesicoureteral reflux, and prostate enlargement in men can all predispose you to kidney infections. If you have had more than one episode, imaging is not optional. It is standard of care.
When to Worry
Seek immediate medical attention if you experience any of the following during recovery: persistent high fever beyond 72 hours of antibiotics, inability to keep fluids down due to vomiting, severe worsening pain, confusion or altered mental status, or signs of sepsis such as rapid heart rate, low blood pressure, and extreme lethargy. Sepsis from pyelonephritis is a real and potentially fatal complication, especially in older adults. For most otherwise healthy people with a timely diagnosis and appropriate antibiotics, pyelonephritis follows a predictable course. The worst of it is over in three days. Full recovery takes about two weeks. Complicated cases take longer and require closer monitoring. The single best thing you can do is get treated early and complete the full course of antibiotics without deviation.