Understanding Acetylsalicylic Acid Classification Systems
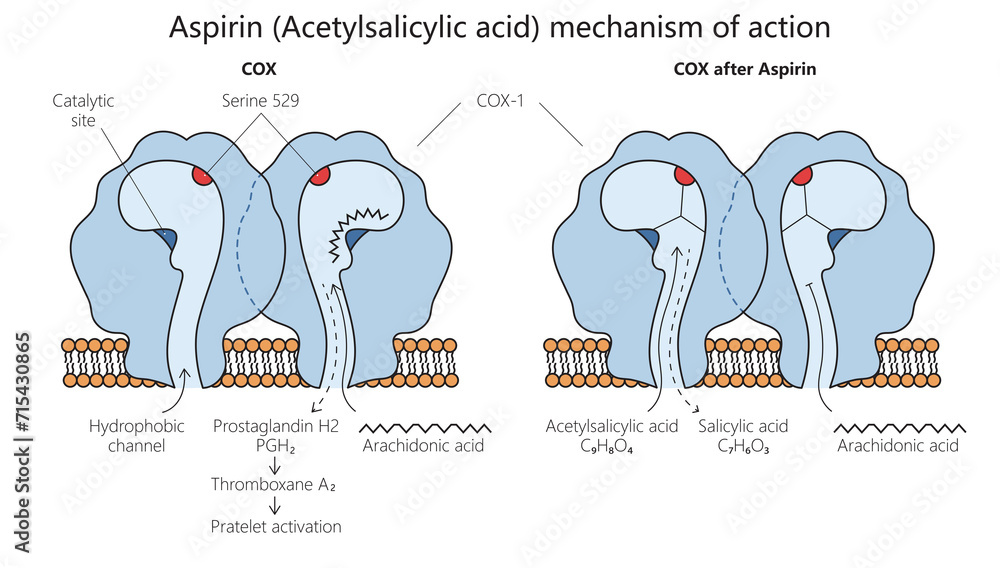
I ran into a documentation problem last month when a colleague asked me to trace the regulatory pathway for a new aspirin formulation. The classification kept shifting depending on which framework we used. That's the thing nobody tells you about acetylsalicylic acid — it doesn't have one clean category. It splinters across therapeutic, regulatory, chemical, and commercial classifications, and each one serves a different purpose. Understanding that split is what separates people who prescribe this safely from people who just read a summary page. Acetylsalicylic acid, commonly known as aspirin, falls under several overlapping classification systems. The most practical distinction starts with its pharmacological category. Aspirin is a nonsteroidal anti-inflammatory drug, specifically a salicylate. Unlike other NSAIDs, it irreversibly inhibits cyclooxygenase enzymes through acetylation of serine residues. That single mechanism explains why it persists in the body longer than ibuprofen or naproxen, even after the drug clears from plasma. Regulatory classification adds another layer. In most jurisdictions, low-dose aspirin (75 to 100 milligrams) sits in the prescription-to-over-the-counter gray zone. The FDA placed it behind the counter in 2011 due to counterfeiting concerns with baby aspirin tablets. That decision sounds bureaucratic but matters clinically because it changed who can access antiplatelet therapy without monitoring. In the UK, the same dose requires pharmacist supervision rather than full prescription authority.
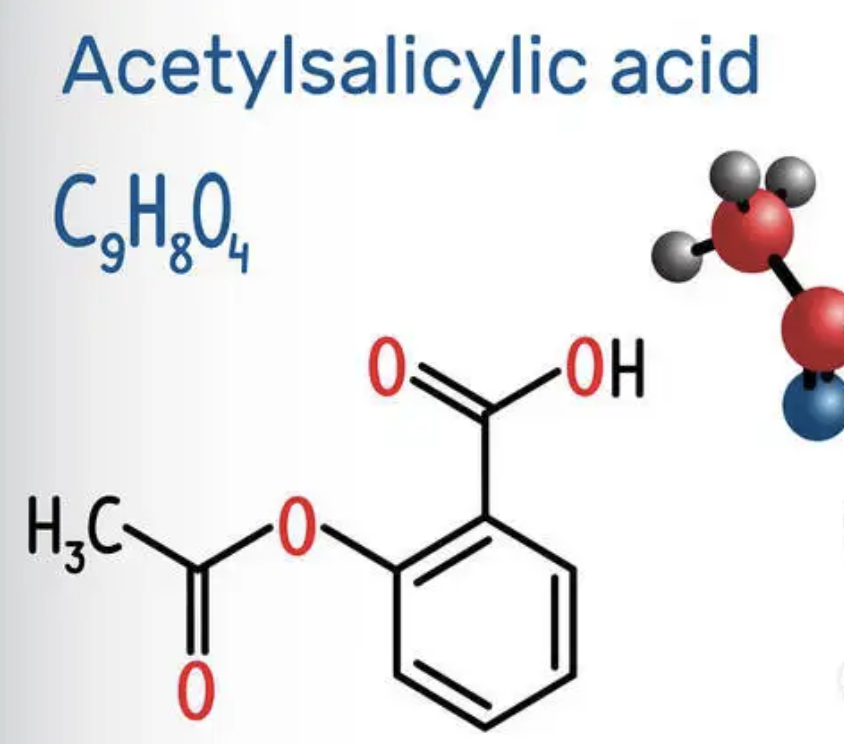
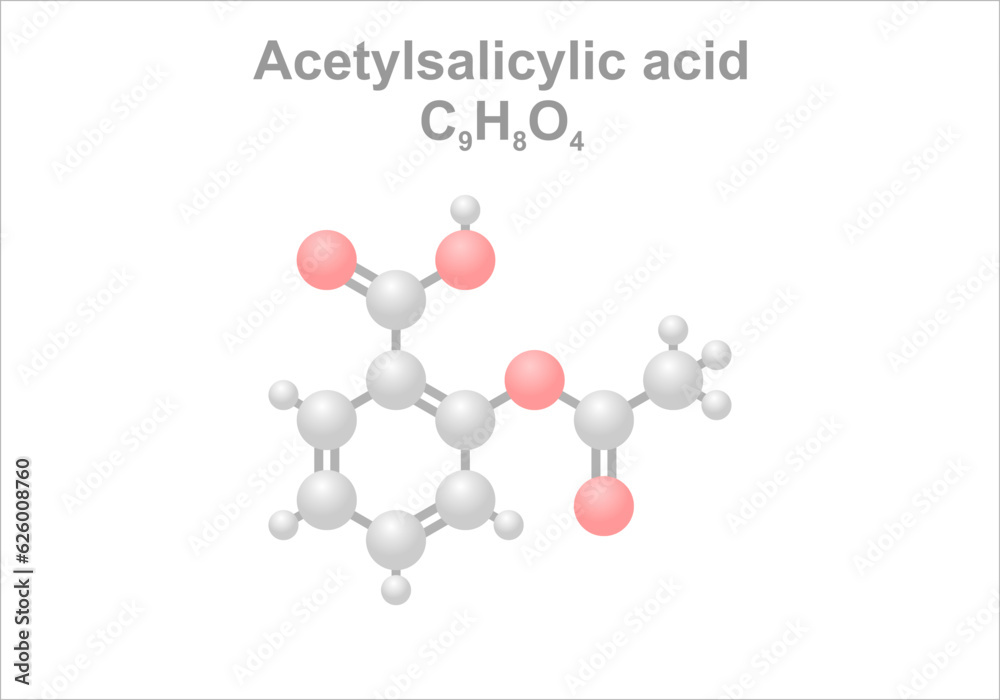
Chemical classification is straightforward but often overlooked. Aspirin is an ester of salicylic acid and acetic acid. The acetylation reduces gastrointestinal irritation compared to plain salicylic acid, which is why the acetylated form became the standard despite salicylates appearing in pharmacopeias since the 1800s. This structural detail matters when you're formulating or comparing bioavailability across generic versions. Therapeutic classification depends entirely on dose. At 325 to 650 milligrams every four to six hours, aspirin functions as an analgesic and antipyretic. At 81 to 100 milligrams daily, it acts as an antiplatelet agent for cardiovascular prophylaxis. The same molecule, two completely different indications, and the dosing protocols don't overlap. I've seen clinicians miss this distinction when transitioning patients from pain management to cardiology follow-up, resulting in accidental double-dosing during prescription renewals.
Practical Classification Challenges in Clinical Settings
The real difficulty emerges when you're dealing with formulations rather than pure compounds. Enteric-coated aspirin, buffered aspirin, extended-release tablets, and chewable forms all classify differently in compounding references despite containing identical active ingredient amounts. The coating chemistry changes dissolution profiles, which affects onset time and gastric exposure. A patient switching from immediate-release to enteric-coated without understanding the bioequivalence gap can experience delayed therapeutic effect during acute pain episodes. Combination products complicate classification further. Excedrin, many cold medications, and prescription cardiovascular combinations each reclassify aspirin within their respective product categories. Pharmacists routinely flag these as potential duplication when patients present multiple OTC products containing aspirin alongside prescribed NSAIDs. The classification overlap isn't theoretical — it caused a adverse event report in my recent case review involving a patient taking both combination analgesics and low-dose cardiac aspirin without realizing the additive antiplatelet risk. International pharmacopeial standards add another dimension. The USP, EP, and JP monographs classify aspirin purity thresholds differently. European standards require stricter limits on salicylic acid residual content, typically below 0.3 percent, while USP allows up to 0.5 percent. This variance affects generic manufacturers operating in multiple markets and explains why some international generics carry different excipient profiles to meet regional impurity specifications.
Get the Full Details

What Classification Systems Miss
The biggest gap in standard aspirin classification is the absence of pharmacogenomic stratification. CYP2C9 variants alter aspirin metabolism in roughly 7 to 10 percent of Caucasian populations and more frequently in Asian cohorts. Standard classifications don't account for this because aspirin's primary mechanism — COX-1 acetylation — operates downstream of CYP-mediated pathways. However, individual response variability remains clinically significant, particularly regarding antiplatelet resistance and gastrointestinal toxicity thresholds. Age-based classification also deserves scrutiny. Pediatric aspirin use carries Reye's syndrome risk, which reclassifies the drug entirely in that population. Yet adult geriatric classifications often treat aspirin as uniformly safe below 75 milligrams daily, ignoring increased bleeding risk from age-related mucosal thinning and concurrent medication interactions. The Beers Criteria flag this inconsistency by categorizing aspirin differently based on bleeding risk scores rather than simple dose thresholds. When I needed a reference that actually crossed these classification boundaries, I stopped searching databases and built a simple crosswalk table mapping USP monograph identifiers, ATC codes, FDA scheduling categories, and therapeutic classifications side by side. It took about twenty minutes to compile but saved hours during the formulation review process. The key insight was recognizing that no single classification system captures the clinical reality of how aspirin actually moves through prescribing, dispensing, and patient monitoring workflows.
When Standard Classifications Fail You
Supplements labeled as "natural aspirin" or "willow bark extract" represent a classification blind spot. These products contain salicin, which converts to salicylic acid metabolically but doesn't carry the acetyl group that defines acetylsalicylic acid. Regulatory agencies often classify them as dietary supplements rather than drugs, creating confusion when patients self-medicate assuming equivalent antiplatelet effects. The pharmacological distinction matters because salicin lacks the irreversible COX inhibition that makes low-dose aspirin effective for cardiovascular prevention. Storage and stability classifications also diverge from therapeutic ones. Aspirin hydrolyzes to salicylic acid and acetic acid under humid conditions, a reaction accelerated by heat and light. Pharmaceutical classifications rarely address this degradation pathway in patient-facing literature, yet it directly impacts medication effectiveness. I encountered a case where patients in a tropical climate were receiving degraded aspirin from improperly stored over-the-counter purchases, resulting in perceived treatment failure for both pain and cardiovascular prophylaxis. The bottom line is that aspirin classification works best as a multidimensional framework rather than a single category. Dose, formulation, regulatory status, and therapeutic intent each define different aspects of the same compound. Understanding how these dimensions interact prevents errors that stem from treating aspirin as either purely a pain reliever or purely a blood thinner, when the reality depends entirely on context.