Aspirin Isn't Just a Painkiller. It's a Pharmacologically Multi-Tool, and Most People Use It Wrong.
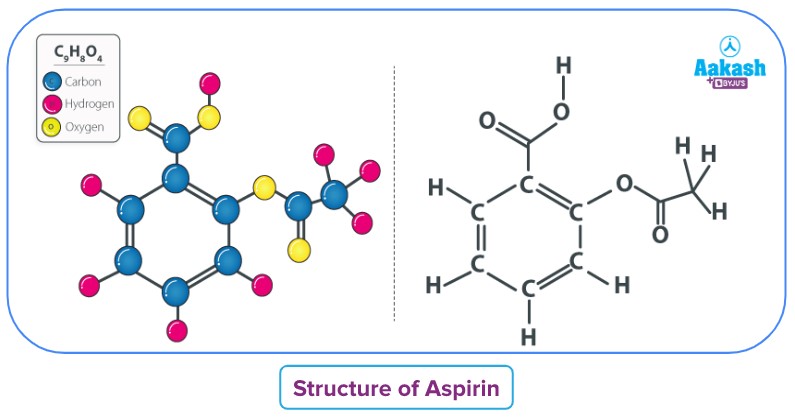
You've probably taken it for a headache at some point. But understanding what it actually does at the molecular level changes how you think about when to take it, when not to, and why the dose matters more than most patients realize. The Power Of Aspirin Understanding Its Classification And Uses goes beyond the bottle label, and honestly, most drug guides don't bother explaining it properly. Aspirin, or acetylsalicylic acid, is classified as a non-steroidal anti-inflammatory drug, a salicylate, and an antiplatelet agent. These three labels describe different pharmacological activities of the same molecule, and that's where confusion starts. People see NSAID and think it only treats inflammation. They see antiplatelet and assume it's only for heart patients. Both are wrong. The mechanism is straightforward but easily misunderstood. Aspirin irreversibly acetylates the COX-1 and COX-2 enzymes. COX stands for cyclooxygenase. This enzyme converts arachidonic acid into prostaglandins and thromboxanes. Prostaglandins mediate pain, fever, and inflammation. Thromboxane A2, produced primarily in platelets via COX-1, triggers platelet aggregation and vasoconstriction. Because aspirin forms a permanent covalent bond with the enzyme, the effect lasts for the lifetime of the platelet — roughly 7 to 10 days. Platelets have no nucleus, so they can't synthesize new enzyme. This is why low-dose aspirin works as a daily blood thinner and why you can't just stop it quickly if something goes wrong.
Higher doses hit COX-2 more prominently, which is where the anti-inflammatory and analgesic effects come from. The threshold between antiplatelet dosing and anti-inflammatory dosing isn't clean. It's a continuum. That matters clinically. I ran into a specific problem a while back working with a patient on low-dose aspirin for secondary cardiovascular prevention who also had osteoarthritis. They started taking 650mg ibuprofen three times daily for knee pain. Within a week, their platelet inhibition was effectively cancelled. Ibuprofen competitively binds the same active site on COX-1 that aspirin needs to access. The mechanism is well documented — ibuprofen physically blocks aspirin's acetylation site if taken beforehand. The patient's platelet function tests came back essentially normal, meaning the protective effect of the aspirin was gone. We switched them to acetaminophen for pain and added a topical NSAID, which has minimal systemic absorption and doesn't interfere with platelet COX-1. The platelet inhibition recovered within days.
Dosing Ranges and What They Actually Do
Low-dose aspirin, typically 75 to 100mg daily, is the standard antiplatelet regimen. This dose selectively inhibits thromboxane production in platelets while having minimal effect on vascular prostacyclin, which is produced by endothelial cells and acts as a vasodilator and inhibitor of platelet aggregation. The selectivity isn't absolute, but at this range it's clinically significant. This is the dose used for secondary prevention after myocardial infarction, stroke, or stent placement. Intermediate doses, roughly 300 to 600mg, provide analgesic and antipyretic effects. This is what most OTC pain relief tablets contain. The onset is 30 to 45 minutes orally. Peak plasma concentration comes in about two hours. Food slows absorption but doesn't significantly reduce total bioavailability. Taking it with food mainly reduces gastric irritation, which brings me to the next point. Anti-inflammatory doses run from 3 to 4 grams per day in divided doses. This is where aspirin competes with other NSAIDs for the top spot in efficacy for conditions like rheumatoid arthritis. It hasn't been the first-line choice for decades because the dose required produces unacceptable side effects in many patients. Gastrointestinal toxicity, renal impairment, and tinnitus are dose-dependent. Tinnitus at around 4 grams per day is actually a clinical warning sign of salicylate toxicity. If your ears start ringing, you're already in dangerous territory.
Get the Full Details

What Aspirin Does That Other NSAIDs Don't
The irreversible COX inhibition is unique to aspirin among the commonly used NSAIDs. All others are reversible inhibitors. This has two major consequences. First, the antiplatelet effect is prolonged and cumulative with daily dosing. Second, there's no rapid offset. If you need to reverse the effect — say, before surgery — you can't just stop taking it. You wait for new platelets to be generated. That's typically 5 to 7 days, sometimes longer depending on turnover rate. This is why surgeons ask patients to stop aspirin a week before procedures. It's not arbitrary. Second, aspirin has a mild uricosuric effect at low doses, meaning it can actually increase uric acid excretion. At high anti-inflammatory doses, this effect reverses and aspirin can competitively inhibit uric acid secretion in the renal tubules, potentially worsening gout. I've seen this happen. A patient with a history of gout was started on high-dose aspirin for rheumatoid arthritis and had a severe flare within days. Switching to a different anti-inflammatory resolved it, but the lesson was clear — aspirin's effect on uric acid is bidirectional and dose-dependent, and this interaction is rarely flagged in patient information leaflets.
Limitations and Where Aspirin Completely Fails
Primary prevention of cardiovascular disease is the biggest area of controversy right now. Multiple large trials over the past decade have shown that for people without established cardiovascular disease, the benefit of daily low-dose aspirin is marginal at best and the bleeding risk is real. Major guidelines now recommend against routine aspirin for primary prevention in adults over 60. The risk of gastrointestinal bleeding and intracranial hemorrhage increases with age and is not trivial. For someone in their fifties with multiple risk factors, the decision is more nuanced. For someone in their seventies with no prior events, the math doesn't work in aspirin's favor anymore. Aspirin also doesn't work for everyone as an antiplatelet. Approximately 5 to 10 percent of patients show aspirin resistance, meaning their platelets don't adequately inhibit aggregation despite compliance. The causes are heterogeneous — genetic variants in COX-1, increased turnover of platelet precursors, elevated baseline platelet reactivity, drug interactions. There's no single test that's universally accepted for screening, and routine resistance testing isn't standard practice. If a patient has a recurrent thrombotic event while apparently compliant on aspirin, switching to a P2Y12 inhibitor like clopidogrel is the typical move, sometimes combined with aspirin for a defined period. Reye's syndrome is the hard contraindication. Aspirin in children and teenagers with viral infections — particularly influenza and varicella — can trigger this rare but fatal condition causing acute encephalopathy and liver failure. The mechanism involves mitochondrial dysfunction, and while the exact trigger isn't fully understood, the association is robust enough that pediatric use is essentially banned in nearly all developed countries. This isn't a soft warning. It's an absolute no.
Practical Stuff People Get Wrong
Enteric-coated aspirin is marketed as being easier on the stomach. It is, slightly. The coating delays release until the medication reaches the small intestine, which reduces direct gastric mucosal contact. But aspirin still gets absorbed systemically and still inhibits COX-1 in gastric mucosal cells. The protection is real but limited. If you're on daily low-dose aspirin and have a history of peptic ulcer disease, an enteric coat alone won't keep you safe. A proton pump inhibitor is the evidence-based add-on, and it should be discussed with a prescriber. Another common mistake is crushing or chewing enteric-coated tablets to "make them work faster." This destroys the coating and exposes the gastric mucosa to concentrated aspirin, increasing ulcer risk without any meaningful speed benefit. If you need rapid absorption, use plain aspirin tablets instead. They're equally effective and cheaper. Alcohol and aspirin together is a bad combination for gastric mucosa. Both independently damage the stomach lining through different mechanisms — alcohol disrupts the mucus barrier, aspirin inhibits prostaglandin-mediated protective mechanisms. Together they multiply the risk. Even moderate drinking while on daily aspirin therapy warrants caution.

Bottom Line
Aspirin is one of the most studied drugs in medical history and still one of the most misused. It's not a harmless OTC pill you can take regularly without thinking. The classification as NSAID, analgesic, and antiplatelet reflects its actual multi-mechanism profile, and each mechanism has different dosing thresholds, different time courses, and different risk profiles. Understanding that distinction is what separates informed use from guesswork.



