Palpation And Clinical Relevance Of The Posterior Medial Malleolus
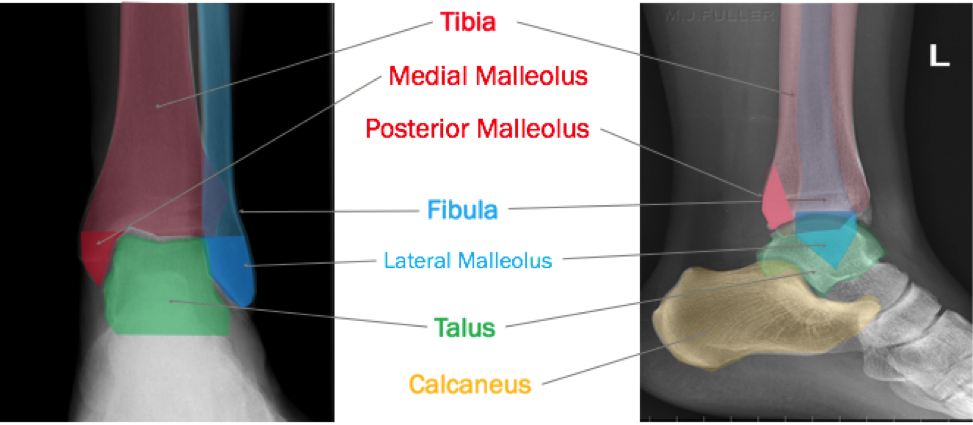
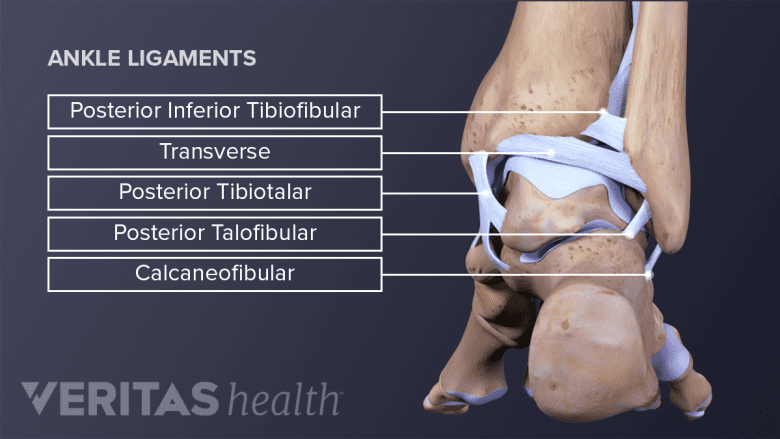
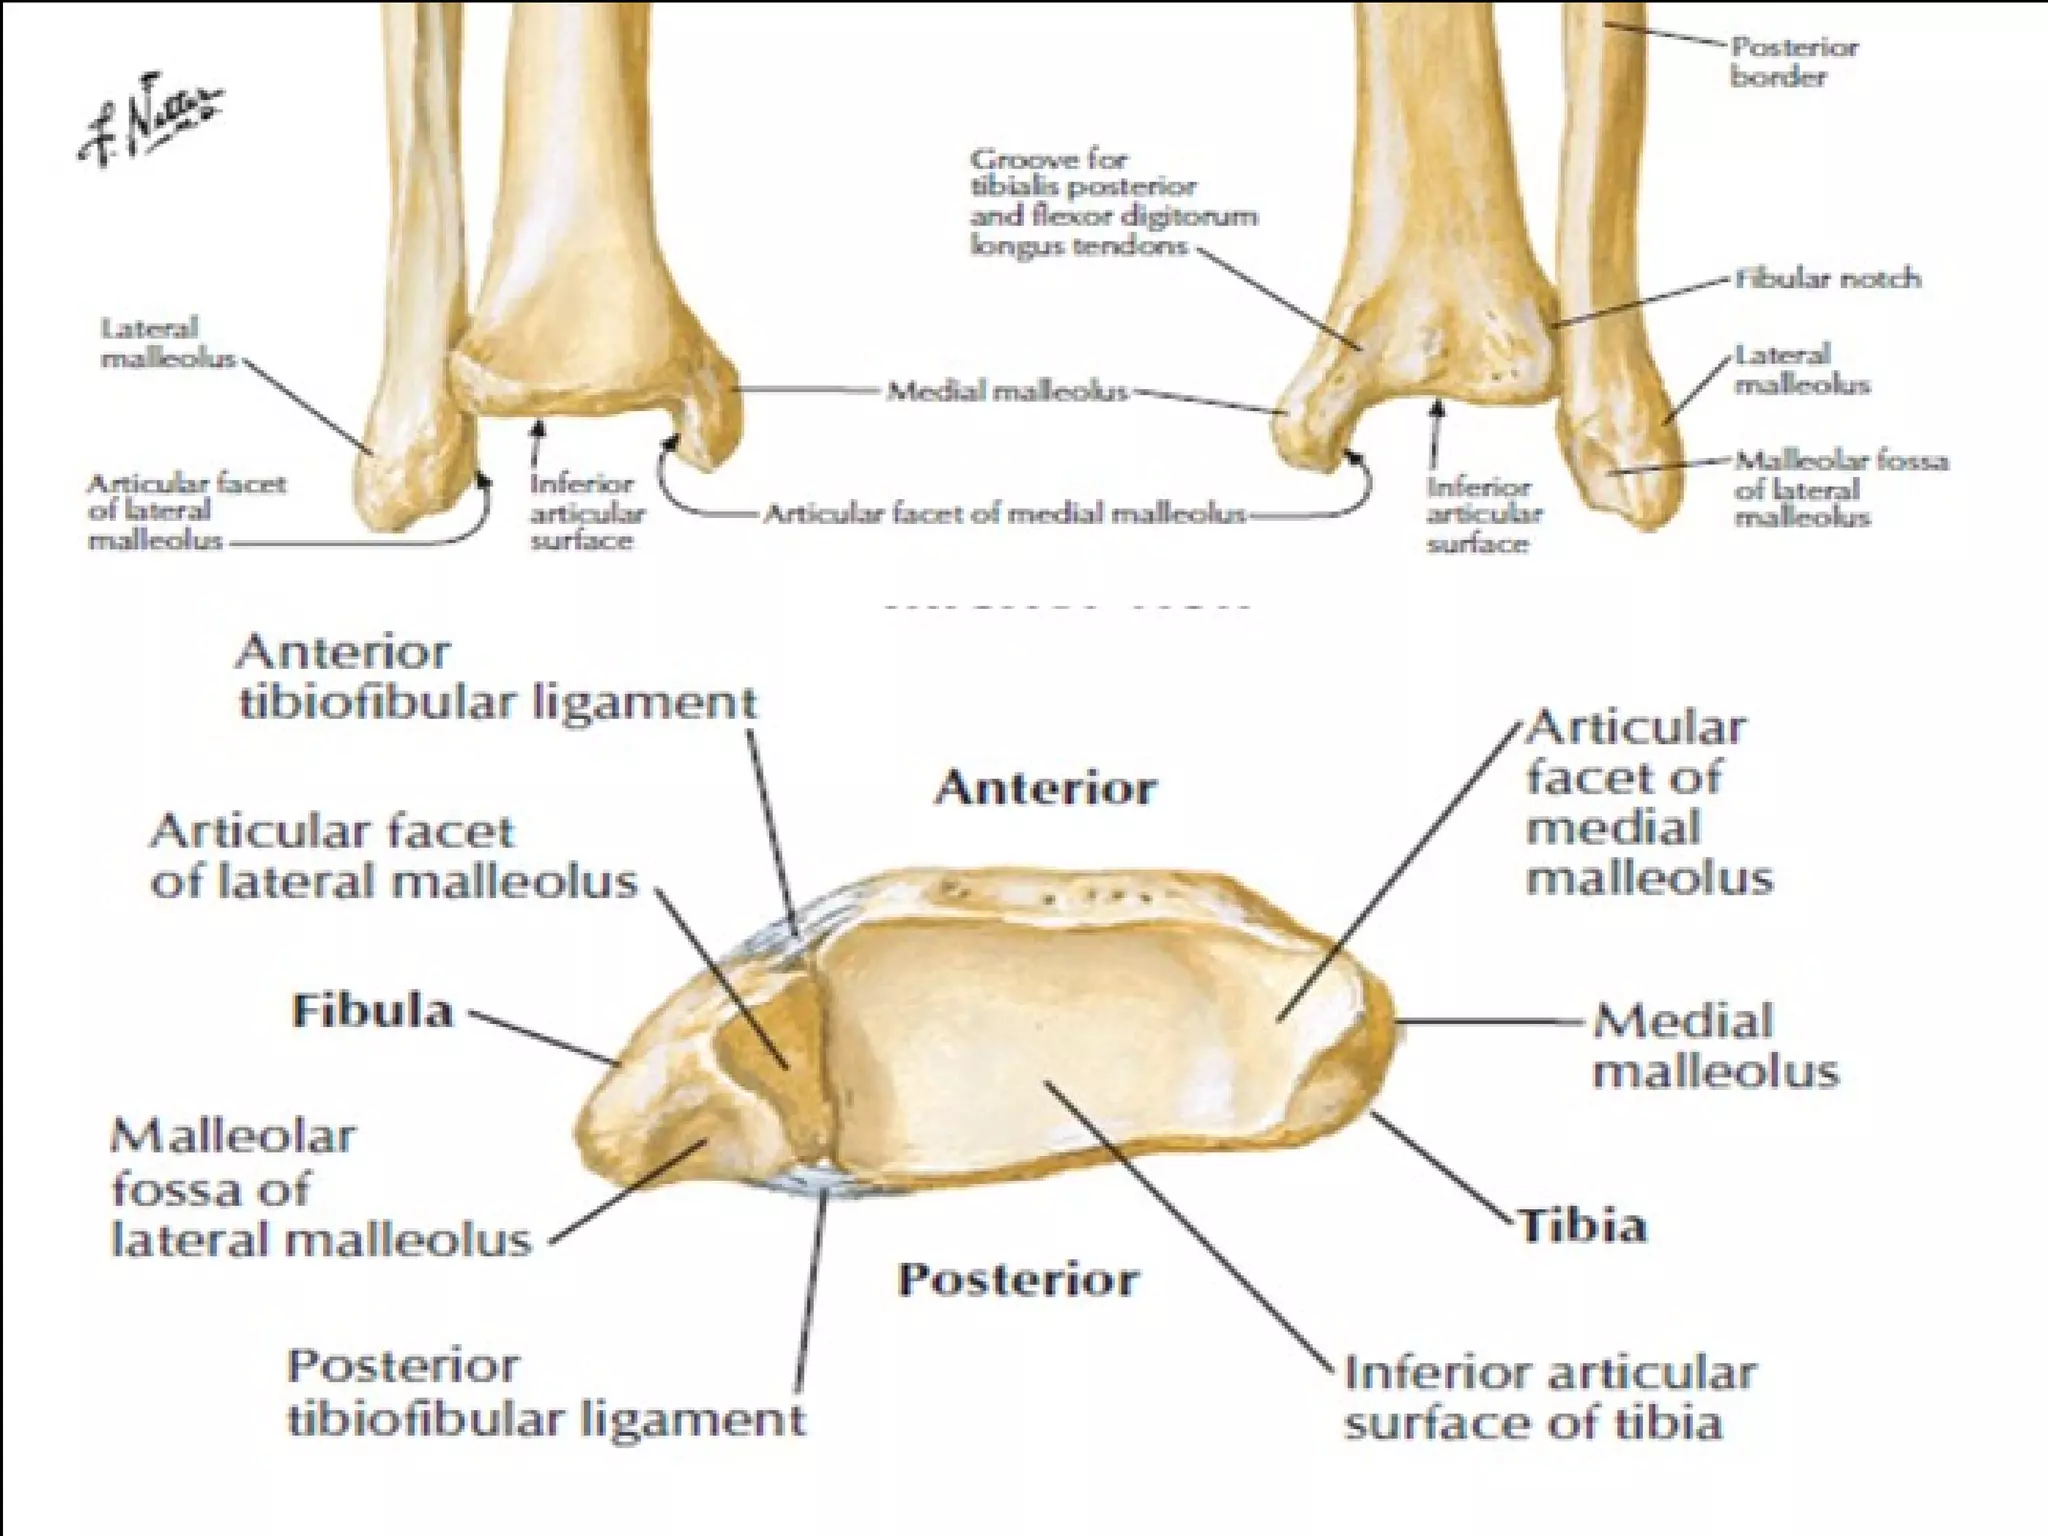
The posterior medial malleolus is the bony prominence on the inner side of the ankle, forming part of the distal tibia. It sits behind the tip you can feel on the inside of your ankle. The structure matters clinically because several important tendons and neurovascular bundles pass immediately behind it through a space called the tarsal tunnel. When I first started doing soft tissue work around the ankle, I treated the posterior medial malleolus as just a reference point. That changed quickly when I began encountering persistent plantar foot pain in patients who had zero obvious foot pathology. The posterior tibial tendon, flexor digitorum longus, and flexor hallucis longus all run behind this bony landmark, compressed between the malleolus and the talus and calcaneus below. The tarsal tunnel itself is only about a centimeter or two wide. Anything swelling in there changes the mechanics for everyone downstream. One detail most anatomy texts don't emphasize enough is that the posterior tibial vein and nerve sit most superficially and closest to the bone surface. The artery lies deeper. This layering matters because when you are doing a nerve block or need to assess for tarsal tunnel syndrome, pressing directly on the posterior medial malleolus with your thumb and asking the patient to report radiating paresthesia into the sole is a valid first screening test. Tinel's sign at this location is positive in roughly 60 to 70 percent of confirmed tarsal tunnel cases, according to the literature I've seen. The remaining cases usually require ultrasound or MRI to visualize the actual compression, often from a ganglion cyst or varicose vein rather than the more commonly cited flatfoot deformity.
I ran into a specific case last year involving a marathon runner who complained of burning along the medial arch after about eighteen miles. Standard rest and ice did nothing. She had no pes anserine bursitis, no posterior tibial tendon dysfunction on palpation, and her foot posture looked normal. I ended up pressing along the posterior aspect of the medial malleolus while her ankle was in slight dorsiflexion and she reported the burning flared sharply. The trigger point wasn't in the tendon at all. It was the flexor hallucis longus running through that same tight posterior space, becoming irritated by repetitive push-off. We switched her from barefoot minimalist shoes to a more supportive trainer, added gentle FHL stretching before runs, and adjusted her mileage by about twenty percent for three weeks. The symptoms resolved within four weeks. If I had only been treating the arch or the tendon insertion, we would have kept missing it.
Palpation Technique And Clinical Applications
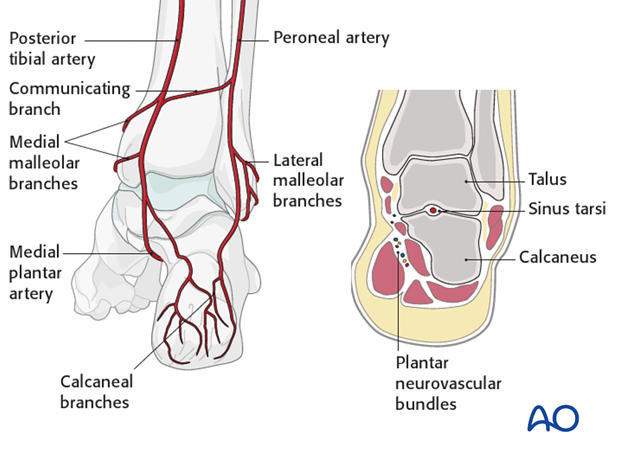
To palpate the posterior medial malleolus properly, have the patient lie prone or sit with the knee flexed and the ankle in neutral. You can also have them sit with the leg extended and externally rotated so the inner ankle is accessible. Use the pad of your index or middle finger and press backward and slightly inward, following the posterior border of the malleolus. You should feel the groove behind the bone where the tendons sit. This is deeper than it looks. The subcutaneous tissue over the posterior medial malleolus is thin, which is why you can feel tenderness easily, but the structures you are probing are several millimeters below the skin surface. The blood supply in this region comes primarily from branches of the posterior tibial artery. If you are assessing for vascular compromise, the posterior tibial pulse is typically palpable just behind and slightly below the posterior medial malleolus. It can be difficult to find in edematous ankles. In those situations, Doppler is more reliable than manual palpation. I usually switch to Doppler when I cannot locate the pulse after thirty seconds of careful searching, which tells me edema or body habitus is interfering. The nerve supply to the skin overlying the posterior medial malleolus comes from the saphenous nerve proximally and the tibial nerve branches distally. This is relevant for surgical incisions. A longitudinal incision directly over the posterior border risks injuring the saphenous nerve, which runs about one centimeter posterior to the malleolus. A transverse incision or one placed slightly more posterior avoids this. I've seen complications from poorly placed posterior medial ankle incisions in orthopedic notes. The sensory deficit in those cases can persist for months or longer.
Get the Full Details
Imaging Considerations
X-rays of the ankle will show the posterior medial malleolus clearly on lateral and mortise views. Fractures of this area are less common than lateral malleolar fractures but do occur, usually as part of a bimalleolar injury pattern. The key is getting a proper mortise view with the ankle internally rotated about fifteen degrees so the clear space between the malleoli and the talus is visible. If you suspect a posterior wall fracture of the distal tibia, a CT scan gives you far more detail than plain films. I usually recommend CT when there is intra-articular involvement or when surgical fixation is being considered, because you need to see the fracture lines in three dimensions. Ultrasound is useful for dynamic assessment of the tendons that pass behind this structure. You can watch the posterior tibial tendon glide in real time while moving the ankle through dorsiflexion and plantarflexion. This is where you catch subclinical tendinosis that MRI might miss if the patient was still during the scan. The limitation here is operator dependence. A poor technique or an inexperienced sonographer will give you a useless study. I have had patients referred to me from clinics where the ultrasound was read as normal despite obvious clinical tenderness, only for a second opinion to show significant peritendinous fluid and partial tearing. MRI remains the gold standard for evaluating tarsal tunnel syndrome and soft tissue masses in this region. The resolution is sufficient to visualize the tibial nerve, the surrounding fascia, and any space-occupying lesions. The downside is cost and availability. An MRI of the ankle without contrast typically takes about forty-five minutes and costs between eight hundred and two thousand five hundred dollars depending on your location and insurance. For straightforward posterior medial malleolus pathology without neurological symptoms, ultrasound is often sufficient and far cheaper. Reserve MRI for cases where surgery is being planned or when the diagnosis remains unclear after conservative management.
Common Pathologies And When To Refer
Tarsal tunnel syndrome is the most recognized condition involving this area, but it is not the only one. Posterior tibial tendon dysfunction presents with progressive flattening of the arch and pain along the posterior medial ankle. The tendon runs directly behind the posterior medial malleolus, so inflammation or degeneration here causes localized tenderness that worsens with single-leg heel raises. Flexor hallucis longus tendinitis, sometimes called dancer's tendonitis, causes pain that is deep and posterior to the malleolus, often exacerbated by toe flexion. These conditions overlap significantly in their symptom presentation, which is why accurate palpation of the posterior medial malleolus and surrounding structures is essential before committing to a treatment plan. I refer to orthopedics when there is a confirmed fracture, when a mass is identified on imaging, or when tarsal tunnel symptoms persist beyond six to eight weeks of conservative treatment including rest, NSAIDs, orthotics, and physical therapy. Surgical decompression of the tarsal tunnel has a reasonable success rate, but it is not trivial. The surgeon works in a confined space with critical neurovascular structures. Post-operative recovery typically involves non-weight bearing for about two weeks, then gradual weight bearing over the next three to four weeks, with full activity resumption around six to eight weeks depending on the individual. Complication rates are low but real, including wound healing problems, nerve irritation, and recurrent symptoms if the decompression was incomplete. For the majority of patients presenting with posterior medial ankle discomfort, the answer is not surgery. It is activity modification, targeted rehabilitation, and addressing biomechanical contributors. Overpronation increases tension on the posterior tibial tendon and compresses the tarsal tunnel. A well-fitted orthotic with medial arch support can reduce symptoms significantly within a few weeks. I have seen patients avoid surgical intervention entirely by switching to structured orthotics and committing to a twelve-week stretching and strengthening program. It takes consistency. There is no shortcut.
Practical Tips For Clinicians And Patients
If you are a clinician assessing the posterior medial malleolus region, start with palpation before ordering imaging. Document exactly where the tenderness is maximal, whether it reproduces distal symptoms, and what movements exacerbate or relieve it. Note the quality of the posterior tibial pulse. Record neurological findings including light touch and pinprick sensation in the plantar foot distribution. These baseline measurements matter if the patient eventually needs surgery, because post-operative neurological changes can be compared to pre-operative status. If you are a patient experiencing chronic medial ankle or plantar foot pain, pay attention to what activities trigger the symptoms. Running and jumping activities compress the tarsal tunnel repeatedly. Standing for extended periods does the same through static load. Keeping a simple activity log for one to two weeks often reveals patterns that neither you nor your doctor noticed beforehand. This information is useful for guiding both treatment and further evaluation. The posterior medial malleolus is a small structure with outsized clinical importance. The tendons, nerves, and vessels that pass behind it are critical for lower extremity function. Understanding the anatomy, recognizing the common pathologies, and knowing when to investigate further or refer out will save time for everyone involved. Most cases resolve with conservative care. A minority need imaging and surgical consultation. The difference usually comes down to careful initial assessment rather than jumping straight to expensive diagnostics.