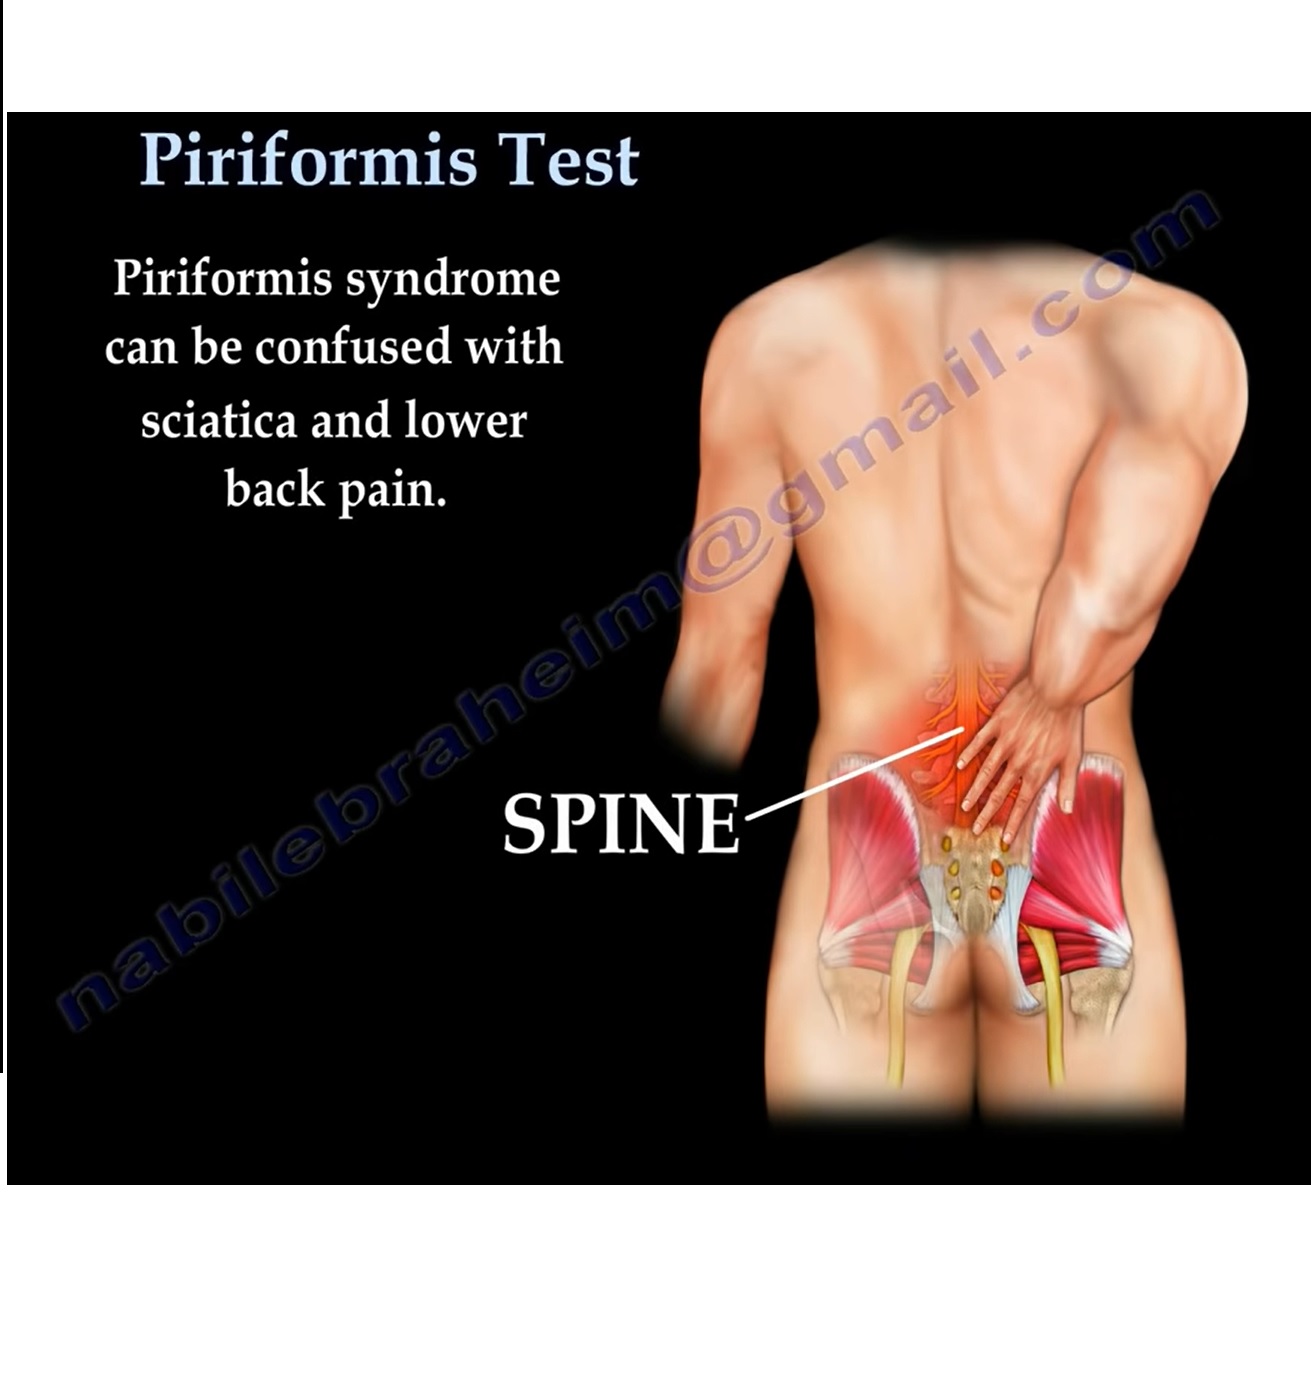
Why Lower Back Pain Often Isn't Actually Your Lower Back
I spent a good chunk of my early career treating what looked like lumbar spine issues only to find the real culprit was a tight muscle sitting right under the glutes. Patients would come in describing radiating pain down their leg, and the reflex was always to order an MRI or start manipulating the spine. That approach works about half the time. The other half? The pain traces back to the piriformis, a small pear-shaped muscle deep in the buttock that sits right on top of the sciatic nerve in most people. Before you go down the imaging rabbit hole, there is a clinical test that has been around for decades and still holds up. It is not fancy, it does not require equipment, and when done properly it can tell you whether your piriformis is the source of the problem or just an innocent bystander. This is where the piriformis test comes into play, and understanding how to apply it correctly can save you weeks of wasted treatment and unnecessary scans.
The Piriformis Test Unlocking The Secrets Of The Lower Back
The basic idea behind testing for piriformis involvement is straightforward. You position the patient so the piriformis muscle is either stretched or contracted, then you assess whether that maneuver reproduces the patient's familiar symptoms. If the test reliably brings back the same pain pattern they complain about daily, you have a positive finding that points toward piriformis syndrome rather than a disc issue or spinal stenosis. There are several variations of this test, and each one interrogates the muscle from a slightly different angle. The FAIR test is probably the most commonly used in clinical settings today. FAIR stands for Flexion, Adduction, and Internal Rotation. The patient lies on their unaffected side while the examiner flexes the hip to about 90 degrees, brings the knee across the body into adduction, and rotates the hip inward. This position puts the piriformis on stretch. If the patient reports pain in the buttock or radiating symptoms down the leg during this maneuver, the test is considered positive. The Beatty test takes a different approach. The patient lies on their unaffected side with both legs straight. The examiner then asks the patient to lift the affected leg off the table while keeping it straight. This isolates the piriformis as the primary abductor of the hip. A positive finding is when pain appears in the piriformis region during the lift, or when the examiner can palpate the muscle becoming prominent and tender. I have found this one particularly useful when the FAIR test gives ambiguous results because some patients cannot tolerate the stretch position well enough to cooperate fully.
The Pace sign is another option worth knowing about. The patient sits on the edge of the examination table with knees together. They are asked to resist outward pressure on their knees while the examiner pushes inward. This contracts the piriformis against resistance. Pain during this resisted abduction suggests piriformis involvement. It is quick to perform and does not require much space, which makes it practical for busy clinics or even for patients to try themselves as a screening measure before seeking professional evaluation.
Get the Full Details

What Positive Results Actually Mean
A positive piriformis test does not automatically confirm piriformis syndrome as a standalone diagnosis. The piriformis can be irritated secondarily from lumbar radiculopathy, sacroiliac joint dysfunction, or even hip pathology. The key is to correlate the test findings with the patient's history and other clinical features. If someone has a positive piriformis test but also presents with neurological deficits like diminished reflexes, motor weakness, or sensory changes that follow a dermatomal pattern, you need to look higher up the chain and consider spinal causes first. I learned this the hard way early in my practice. A patient came in with classic sciatica symptoms and a strongly positive FAIR test. I was confident about piriformis syndrome and started a course of piriformis-focused stretches and manual therapy. After three weeks with no improvement, I ordered imaging and found a significant L5-S1 disc herniation compressing the nerve root. The piriformis was tight, yes, but it was compensating for the underlying spinal issue, not causing it. That case changed how I approach these tests. Now I always run through a full neurological screening before committing to any single diagnosis based on piriformis findings alone.
Limitations and Common Pitfalls
No clinical test is perfect, and the piriformis tests are no exception. Sensitivity and specificity vary widely across studies, with some reporting sensitivity as low as 40% and specificity around 60%. This means a positive test does not guarantee piriformis involvement, and a negative test does not rule it out. The variation likely comes from differences in how the tests are performed and what thresholds clinicians use to call a result positive. One common pitfall is over-reliance on a single test. I recommend using at least two different piriformis maneuvers plus assessment of lumbar spine range of motion and neurological function before drawing conclusions. Another issue is patient variability in pain tolerance and cooperation. Some patients clamp down on the test positions out of fear or discomfort, which can produce false positive results from general muscle tension rather than true piriformis irritation. The piriformis test also struggles in patients with obesity or significant gluteal musculature. The muscle sits deep, and in larger patients it can be difficult to isolate through surface palpation or to produce a clean mechanical stretch during positioning. In these cases, imaging-guided diagnostic injections into the piriformis region can provide more definitive information. If the injection temporarily resolves the symptoms, you have strong confirmation that the piriformis is the pain generator.
How to Use This Information Practically
If you are dealing with persistent lower back or buttock pain that radiates down the leg, trying a basic piriformis assessment at home can give you useful directional information before you see a professional. Sit on a firm chair and note whether crossing the affected leg over the opposite knee while leaning forward reproduces your symptoms. This is a crude version of the stretch component used in formal testing. If it does, make a note of it for your clinician. For healthcare providers, incorporating piriformis testing into your routine assessment of lower quadrant pain can improve diagnostic accuracy and reduce unnecessary referrals. Start with the FAIR test as your primary screen, then add the Beatty or Pace test if the results are unclear. Document your findings carefully, including which position provokes symptoms and the exact quality and radiation pattern of the pain. This information helps guide treatment decisions and provides a baseline for tracking progress over time. When piriformis involvement is confirmed, treatment typically involves a combination of gentle stretching, manual therapy to release the muscle, and strengthening of the surrounding hip stabilizers. Most patients see meaningful improvement within four to six weeks of consistent conservative care. Surgery is rarely indicated and reserved for cases that fail extensive non-operative management. Physical therapy techniques such as deep friction massage, trigger point release, and nerve gliding exercises can accelerate recovery when applied by a trained practitioner.

When to Seek Professional Evaluation
Self-assessment has its place, but certain red flags should prompt immediate medical attention regardless of piriformis test results. These include bowel or bladder dysfunction, progressive weakness in the legs, numbness in the saddle area, unexplained weight loss, fever, or pain that worsens at night and is not relieved by position changes. These symptoms suggest conditions that require urgent diagnosis and treatment beyond what piriformis-related issues would produce. For most people with chronic buttock and leg pain, a structured approach that includes proper clinical testing, accurate diagnosis, and targeted treatment yields better outcomes than guessing and trying random exercises. The piriformis test is one tool in that process, not the entire process. Used appropriately alongside other clinical findings, it can help unlock why your lower back pain persists and point you toward the right treatment path rather than a dead end.