Understanding Peripheral Vision Beyond Basic Eye Charts
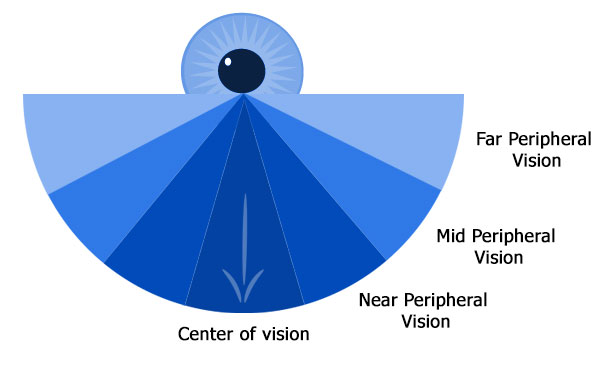
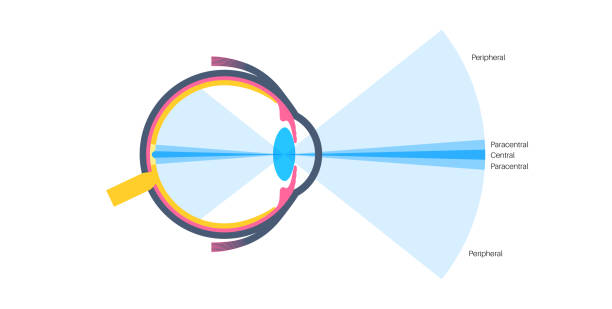
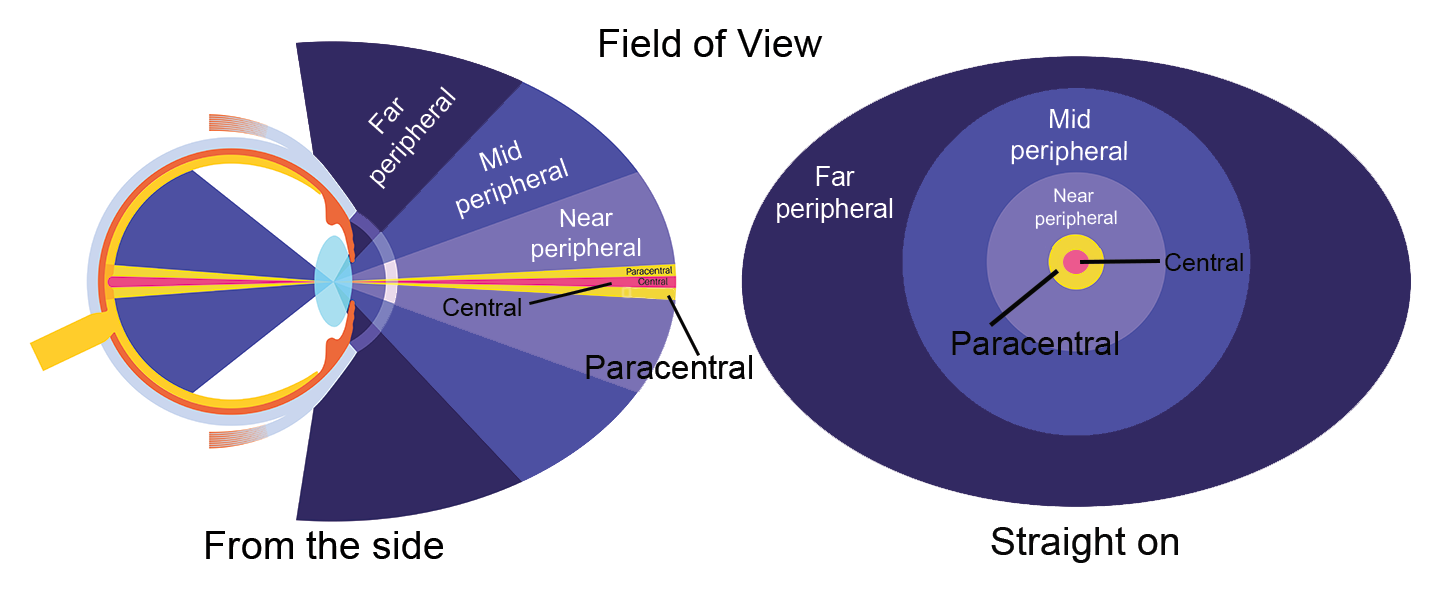
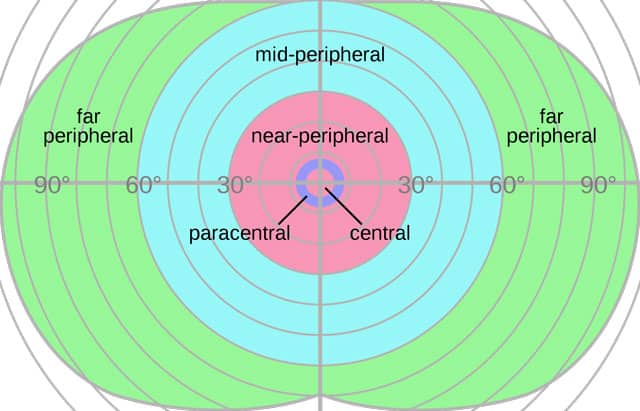
Most people think eye exams end once the optometrist tells you whether you need glasses. The standard 20/20 test measures central acuity — what you see when you stare straight ahead. That leaves a large gap in understanding how your visual field actually functions in clinical practice. Peripheral vision refers to the entire area you can see without moving your eyes or head, and the medical terms surrounding it matter more than patients typically realize. I have spent years watching patients and even some clinicians mix up terms that sound interchangeable but mean very different things on a perimetry report. Here is how the vocabulary actually breaks down in a real clinical setting. Visual field is the complete area a person can perceive while fixating on a single point. It is not the same as visual acuity. A patient can have perfect 20/20 central vision and still have significant field loss. Peripheral vision is the portion of the visual field outside the central 30 degrees. Everything beyond that is what most people casually call "side vision."
Hemianopia is the term for loss of half the visual field. Bitemporal hemianopia means the outer halves are missing from both eyes — typically pointing to a chiasmal lesion, often a pituitary mass pressing on the optic chiasm. Homonymous hemianopia affects the same side in both eyes and usually traces back to damage somewhere along the post-chiasmatic visual pathway in the brain. I had a patient last year who complained only about bumping into doorframes on his left. His central acuity was 20/20 in both eyes. The perimetry revealed a right homonymous superior quadrantanopia. An MRI confirmed a small left occipital infarct he had not even known about until that point. Quadrantanopia means a quarter of the visual field is lost. Superior or inferior is determined by the patient's perspective, not the clinician's. That detail matters because a superior quadrantanopia suggests damage to the inferior visual pathway — Meyer's loop in the temporal lobe for temporal field defects, or the parietal optic radiations for parietal defects. Getting the anatomy right on these maps changes where you look for the lesion. Scotoma is any localized area of reduced or absent vision surrounded by normal field. It can be absolute, meaning no perception at all in that spot, or relative, where the person detects stimuli only when they are brighter or larger. A central scotoma is clinically significant because it overlaps with the fixation point. A paracentral scotoma sits just outside central vision and is common in glaucoma. I once missed an early glaucomatous scotoma because I was reading the printout too quickly and focused on the overall deviation probability plot rather than tracing the individual points on the raw grayscale. That taught me to always look at the raw data first before trusting summary statistics.
Altitudinal defect describes field loss confined to either the upper or lower half, bounded roughly by the horizontal meridian. This pattern is characteristic of anterior ischemic optic neuropathy, or NAION when it is non-arteritic. The affected hemisphere corresponds to the oppressed portion of the optic nerve head blood supply. Not every altitudinal defect is ischemic, but the pattern should trigger a vascular workup rather than a routine glaucoma referral. Tunnel vision is the lay term for severe concentric constriction of the visual field. In medical language this is described as a markedly reduced field radius, often less than 10 degrees. Retinitis pigmentosa and advanced glaucoma are two common causes, but so are certain medication toxicities, particularly from hydroxychloroquine used long-term for autoimmune conditions. Screening guidelines recommend baseline perimetry before starting the drug and annual field testing after five years of use, though many specialists now recommend earlier and more frequent monitoring. Visual field testing itself comes in two main flavors. Static perimetry presents stationary targets at varying intensities at fixed locations. Automated static perimetry using a Humphrey Field Analyzer is the standard in ophthalmology and neurology clinics. Dynamic perimetry moves targets along paths, which is the principle behind Goldmann kinetic perimetry. Goldmann remains useful when patients cannot cooperate well with standard automated tests — pediatric populations, cognitively impaired individuals, or those with nystagmus tend to produce more reliable results with kinetic methods.
Get the Full Details
Mean deviation and pattern standard deviation are the two summary indices you will see on every Humphrey printout. Mean deviation compares the patient's total sensitivity across all tested points against an age-matched normative database. A more negative MD indicates greater overall depression of the field. Pattern standard deviation isolates localized defects by removing the effect of a uniform depression. When both MD and PSD are abnormal, you are looking at a real structural loss rather than a diffuse dulling from cataract or poor pupil dilation. The fatigue index, false positives, and false negatives printed at the bottom of the report tell you how reliable the test was. A false positive rate above 15 percent usually means the patient is pressing the button randomly, possibly from anxiety or confusion about the instructions. I once reviewed a report that showed a dramatic new superior field defect in a patient who had been referred urgently from neurology. The false positive rate was 22 percent and the fixation losses were 18 percent. Repeat testing the following week with a different technician produced a normal field. The apparent defect was an artifact of testing conditions, not pathology. Giant cell arteritis deserves special mention because missing it has consequences. Patients over 50 presenting with new altitudinal field loss, headache, scalp tenderness, and elevated inflammatory markers need immediate high-dose corticosteroids regardless of whether the temporal artery biopsy has been scheduled. Treatment should never wait for biopsy confirmation. Permanent vision loss from arteritic anterior ischemic optic neuropathy can occur within hours of onset.
The limitations of perimetry are worth stating plainly. Visual field testing is subjective. It depends entirely on the patient's attention, comprehension, and response consistency. A cataract can mimic a glaucomatous defect. Poor dilation can produce artificial nasal steps. Retinal pathology anywhere along the pathway from cornea to occipital cortex can alter field results, and the test alone cannot distinguish among those causes. Perimetry is a functional map, not an anatomical diagnosis. You need OCT imaging, fundus examination, and clinical context to correlate what the field shows with what is actually happening structurally. If you want a practical reference to keep nearby, the American Academy of Ophthalmology's Basic and Clinical Science Course volume on neuro-ophthalmology and the Glaucoma section remains the most current freely available resource. Most hospital libraries carry it, and several chapters are available through their public education portal. The field testing atlas from the John A. Moran Eye Center also provides excellent image examples of common defect patterns with corresponding anatomical correlations. Learning these terms matters because the language shapes how specialists communicate about your vision. When your neurologist mentions bitemporal hemianopia, you should understand that it points toward the sella turcica region. When your ophthalmologist discusses a paracentral scotoma with elevated pattern standard deviation, that is an early glaucomatous signal worth tracking over time rather than dismissing as noise. The difference between accurate understanding and vague anxiety in these situations is simply knowing the vocabulary.