What "Peripheral" Actually Means When a Doctor Uses It
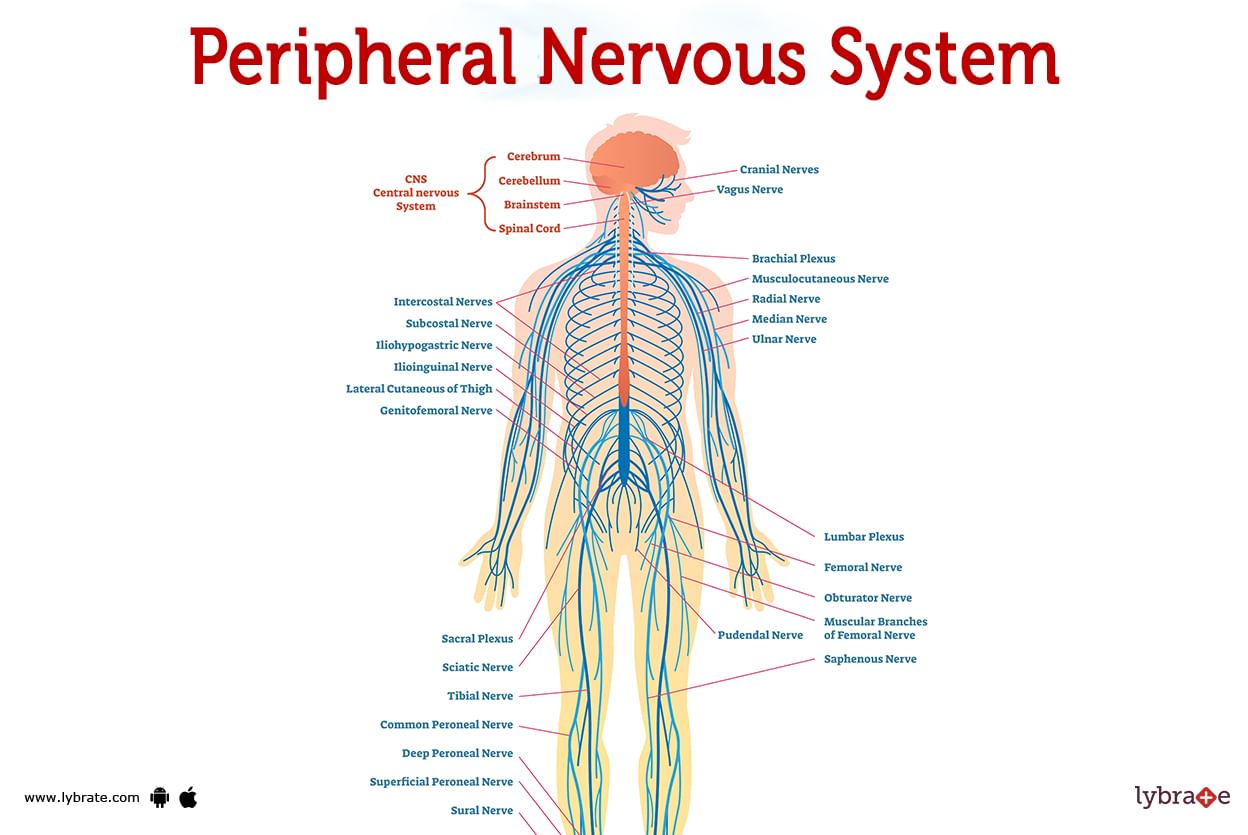
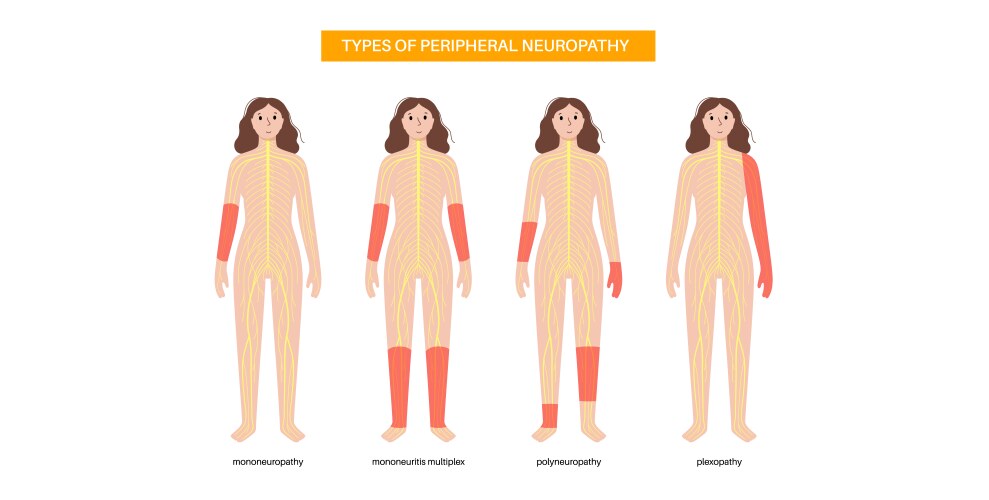
The word peripheral shows up constantly in medicine, and it does not mean the same thing in every sentence. That is the first problem. A clinician might say a patient has "peripheral edema," "peripheral neuropathy," "peripheral artery disease," "peripheral cyanosis," "peripheral smear," or "peripheral venous access," and each one refers to something structurally and clinically different. Getting the meaning wrong is not just sloppy shorthand. It can lead to incorrect triage decisions, unnecessary tests, or telling the patient something that does not match the actual pathology. At its core, peripheral in anatomy means "away from the center." That center can be the brain and spinal cord, it can be the aorta, it can be the trunk of the body, or it can refer to the outer limits of a visual field. The anatomical direction is straightforward. The clinical implications vary wildly depending on which center is being referenced. When we talk about the peripheral nervous system, we are referring to all the nerves outside the brain and spinal cord. This includes cranial nerves, spinal nerve roots, peripheral nerve trunks, and terminal sensory and motor endings. A peripheral neuropathy is fundamentally different from a central nervous system lesion in terms of presentation, workup, and treatment. Distal symmetric polyneuropathy, for example, produces a glove-and-stocking sensory loss pattern. A radiculopathy from a herniated disc follows a myotomal distribution. Both involve the periphery, but the localization changes everything about how you approach the case.
I recall a patient who came in complaining of numbness and tingling in both feet. The word "peripheral" was used early in the chart review and everyone assumed peripheral neuropathy from diabetes. The symptoms were distal and symmetric, which fits the pattern. But the onset was subacute over three weeks, not the gradual years-long progression typical of diabetic neuropathy. We held off on the standard metformin-adjustment conversation and ran a serum protein electrophoresis instead. Turns out the patient had a monoclonal gammopathy causing an unrelated peripheral neuropathy. The word peripheral had pointed us in a broadly correct anatomical direction, but it almost blinded us to the etiology. That is one of the quiet traps of this terminology.
Peripheral Vascular Terminology
The vascular usage of peripheral is equally loaded. Peripheral artery disease specifically refers to atherosclerotic narrowing of arteries distal to the aortoiliac segment. This typically means the superficial femoral, popliteal, tibial, and peroneal arteries. It does not include the carotids, renals, or mesenterics, even though those vessels are technically peripheral to the heart. The distinction matters because peripheral arterial disease carries a different risk profile and treatment algorithm than cerebrovascular or visceral arterial disease. Peripheral cyanosis and central cyanosis represent the same clinical sign—blue discoloration of the skin—but the mechanism and urgency are completely different. Peripheral cyanosis occurs when blood flow to the extremities slows down and tissues extract more oxygen than usual. Cold exposure, Raynaud phenomenon, and heart failure can all cause it. Central cyanosis indicates a problem with gas exchange in the lungs or a right-to-left cardiac shunt. One is often benign and temperature-related. The other requires immediate investigation. Telling a patient they have "peripheral cyanosis" when they actually have central cyanosis because you checked the lips and nails but not the tongue and mucous membranes is a real diagnostic error I have seen happen. I once worked through a case where an elderly patient presented with cold, bluish toes. The initial read was peripheral vascular disease. Ankle-brachial indices confirmed reduced flow, but the pattern was atypical. The patient also had bilateral knee replacement hardware from decades prior. The toe discoloration was partly due to localized vasoconstriction from chronic neuropathy and reduced motor function in the lower legs, not pure atherosclerosis. We adjusted the compression stockings, added a calcium channel blocker for vasodilation, and avoided an unnecessary angiogram. The peripheral finding was real. The assumed peripheral arterial disease was only partially correct.
Get the Full Details
Peripheral in Laboratory and Diagnostic Contexts
A peripheral blood smear is not a "less important" blood test. The adjective here refers to the source of the sample—peripheral circulation as opposed to bone marrow aspirate or cerebrospinal fluid. But the clinical weight of a peripheral smear can be enormous. It is the first line for diagnosing hemolytic anemias, malaria, and certain leukemias. A novice might glance at a smear and miss a smudge cell or a teardrop poikilocyte that changes the entire diagnostic path. Peripheral blood stem cell collection is another example where the term is purely descriptive of anatomical origin but carries enormous procedural significance. Mobilizing stem cells into peripheral circulation using G-CSF and then performing apheresis is a standard approach for transplant patients. But the peripheral blood counts during mobilization can show dramatic leukocytosis, and the apheresis team needs to monitor for splenic rupture risk, which is rare but real. The word peripheral here masks a complex physiologic manipulation.
Peripheral Vision and Neuro-Ophthalmology
In ophthalmology and neurology, peripheral vision refers to the visual field outside the macular or central focus. Loss of peripheral vision follows predictable patterns. Retinitis pigmentosa produces concentric ring-shaped constriction. Glaucoma causes arcuate scotomas that respect the horizontal meridian. A occipital lobe stroke can produce homonymous hemianopsia. Telling a patient "you are losing peripheral vision" without specifying the pattern and likely cause is unhelpful at best and anxiety-inducing at worst. A glaucoma patient and a retinitis pigmentosa patient need entirely different counseling, monitoring schedules, and genetic conversations. Peripheral edema is one of the most commonly used phrases in clinical practice and one of the least precisely defined. It simply means swelling in the extremities, usually the lower legs and feet. But the differential is extremely broad. Cardiac causes, renal causes, hepatic causes, venous insufficiency, lymphedema, medication side effects like amlodipine or pioglitazone, deep vein thrombosis, and hypoalbuminemia can all present as peripheral edema. The word itself gives no directional clue toward any specific etiology. I learned this the hard way with a patient who had bilateral pitting edema extending to the mid-calves. The chart said peripheral edema secondary to heart failure, which was the working diagnosis from a prior encounter. The patient was on furosemide and seemed stable on paper. But the edema was not improving. I pressed into the pretibial area and noted that the pitting was slow to recoil, and the skin had a peau d'orange texture that suggested lymphedema rather than simple fluid overload. We stopped increasing the diuretic, ordered a lymphatic ultrasound, and referred to a lymphedema therapist. The diuretics were not going to help. The term peripheral edema had been used as a diagnostic endpoint rather than a descriptive starting point.
Why This Terminology Creates Communication Problems
The biggest issue with peripheral terminology is that clinicians use it as shorthand with each other, then the same shorthand gets passed to patients without translation. A doctor might document "peripheral neuropathy" and move on. When they tell the patient, "You have peripheral nerve damage," the patient now has a mental image of severed wires that is neither accurate nor useful. The patient may then Google the term and land on worst-case scenarios about Guillain-Barre or terminal conditions. The workaround I use is to replace the adjective with the anatomical description and the functional consequence. Instead of saying peripheral neuropathy, I say the nerves that carry sensation from your feet and hands into your spinal cord are irritated or damaged. Then I explain what that means for balance, sensation, and daily function. It takes longer. It also produces better adherence to treatment plans and fewer 2 a.m. symptom-checker queries from anxious patients. Similarly, peripheral artery disease should be explained as narrowed arteries in the legs that reduce blood flow during walking. The word peripheral sounds minor to a layperson. It does not convey the claudication, the amputation risk, or the cardiovascular comorbidity that actually accompanies the diagnosis. Patients who understand the functional impact of their peripheral arterial disease are more likely to comply with exercise programs, antiplatelet therapy, and smoking cessation.

Pitfalls That Beginners Miss
One counter-intuitive point that is worth emphasizing: peripheral does not mean mild or less serious. A peripheral nerve injury from a deep laceration can be devastating. A peripheral artery occlusion can mean limb loss within hours. Peripheral edema from constrictive pericarditis carries a higher mortality risk than many central findings. The anatomical qualifier tells you location, not severity. This is a misconception that persists even among senior residents who confuse peripheral with peripheral as in minor. Another frequent error is assuming that peripheral findings rule out central pathology. A patient with peripheral neuropathy can simultaneously have a spinal cord lesion causing myelopathy. The two can coexist, and the myelopathy can be missed if the clinician attributes all neurological symptoms to the peripheral process. I saw this with a diabetic patient whose foot symptoms were so prominent that the upper extremity weakness and gait instability were attributed to deconditioning. An MRI of the cervical spine later revealed a compressive myelopathy that required surgical decompression. The peripheral disease was real. It was not the whole story.
When the Term Fails Completely
There are clinical scenarios where "peripheral" is simply not applicable and using it obscures more than it clarifies. Small vessel disease, for instance, affects arterioles and capillaries that are too distal to be captured by standard peripheral arterial imaging. Calling this peripheral vascular disease is technically incorrect and leads to inappropriate angiography requests. Similarly, autonomic dysfunction involves peripheral nerves but is not a peripheral neuropathy in the traditional sense. Labeling it as such generates a workup for structural nerve damage that will come back negative and delay the correct diagnosis of dysautonomia or pure autonomic failure. For these edge cases, moving beyond the peripheral label to more precise terminology—microvascular dysfunction, small fiber neuropathy, autonomic neuropathy—produces better diagnostic pathways. The peripheral label is a starting point, not an endpoint. Treating it as final is where mistakes accumulate.