What Lives on Your Left Side
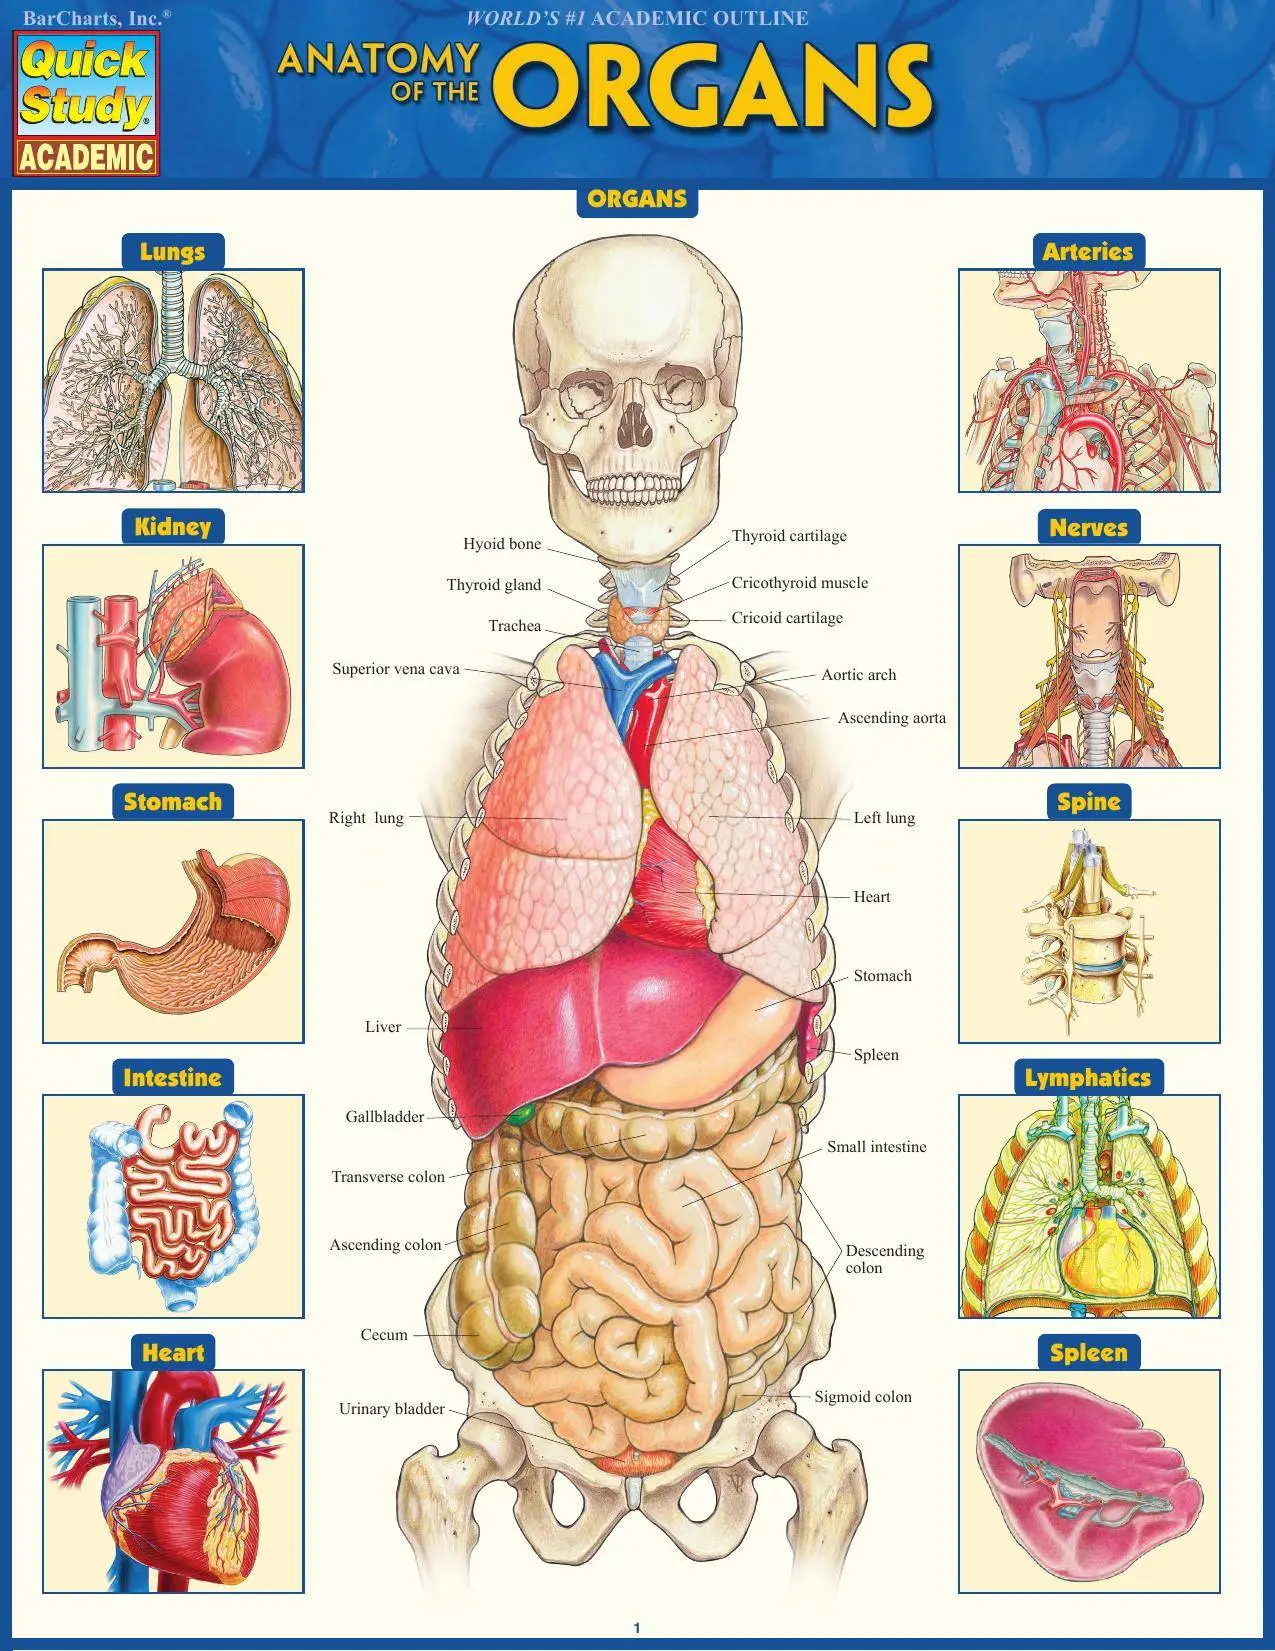
Most people think of the body as a mirror — two symmetrical halves doing the same work. It isn't. The left side is a different arrangement of organs, packed into a different space, with different relationships to each other than you'd expect. If you're studying anatomy, prepping for surgery, or just trying to understand why your left flank hurts after a heavy meal, you need to know what's actually there and where it sits.The left upper quadrant alone houses the stomach, spleen, left kidney, pancreas tail, splenic flexure of the colon, and a significant portion of the small intestine. Move down into the left lower quadrant and you've got the descending colon, sigmoid colon, left ureter, and in females the left ovary and fallopian tube. The left lung also takes up space here, though it's not identical to the right — it's smaller, with two lobes instead of three, and carries the cardiac notch that makes room for the heart. Let me walk through this from the top down, the way I'd actually use it when tracing pain or interpreting an imaging study. Thoracic cavity, left side: The left lung has the lingula (homologous to the right middle lobe) and the superior and inferior lobes. The left hemidiaphragm sits slightly lower than the right because the liver pushes up on that side. Between the lung and diaphragm you've got the costophrenic recess — a common place for fluid to collect. The left heart border is mostly the left ventricle, which is why trauma to the left precordium can be so destructive; there's barely any padding between the sternum and the ventricle.
Left subphrenic space: This is the potential space between the diaphragm and the liver/stomach. After abdominal surgery, blood and pus love to collect here. I once watched a post-op patient with a subphrenic abscess present with nothing but left shoulder pain and a low-grade fever for three days before anyone connected the dots. The referred pain travels via the phrenic nerve (C3-C5), same pathway as gallbladder pain on the right. Never skip the shoulder exam. Left upper quadrant organs: The stomach occupies the majority of this space, tucked under the left rib cage. The spleen sits posterior and lateral to it, wedged between the stomach and the left kidney. This is why splenic injuries can present with gastric compression symptoms — early satiety, left-sided fullness — before they present with hemodynamic collapse. The splenic flexure of the colon hooks around the inferior pole of the spleen. A distended flexure can mimic splenic pain, and vice versa. I had a patient with severe constipation whose left upper quadrant pain was misread as splenic infarction on initial CT; the colon was just loaded with stool. Don't confuse colonic distension with solid organ pathology. The left kidney sits retroperitoneally at approximately T12-L3. It's positioned slightly higher than the right kidney because the liver displaces the right side downward. The left renal vein runs between the superior mesenteric artery and the aorta — the "nutcracker" region. Nutcracker syndrome (left renal vein compression) is a real thing and causes left flank pain, hematuria, and sometimes varicocele in males. If you're seeing unexplained left-sided renal vein hypertension, check the angulation at that crossover point.
Pancreas tail: The body and tail of the pancreas extend all the way to the splenic hilum. This is clinically relevant because pancreatic tail lesions can invade the spleen directly, and splenic artery aneurysms (the most common visceral artery aneurysm) sit right along the pancreatic border. A ruptured splenic artery aneurysm is a maternal mortality risk in pregnancy — not something to miss on imaging. Left lower quadrant: The descending colon runs down the left flank, becoming the sigmoid colon as it approaches the pelvis. The sigmoid is redundant in many people — some have two full S-loops. This redundancy matters for colonoscopy navigation and for understanding why diverticulitis hits the left side more often in Western populations (the sigmoid bears the highest intraluminal pressure according to the Law of Laplace). The left ureter crosses the bifurcation of the left common iliac artery. A left ureteral stone will typically cause flank pain that radiates anteriorly and inferiorly toward the groin and labia or scrotum. The radiation pattern follows the genitofemoral and ilioinguinal nerves. I've seen enough of these to know that the pain can make patients feel like they need surgery when they actually just need tamsulosin and time.
Get the Full Details
Pelvic structures: In females, the left ovary and fallopian tube occupy the left adnexa. Ovarian cysts here can cause dull left-sided pain that's easy to attribute to colonic issues. The key differentiator is usually cyclicity and the presence of adnexal mass on exam. In males, the left spermatic cord and vas deferens descend through the inguinal canal — left-sided inguinal hernias are slightly less common than right but follow the same pathway through the deep inguinal ring.
Common Mistakes When Reading Left-Sided Anatomy
One thing that trips people up is the relationship between the spleen and the 9th, 10th, and 11th ribs. The spleen lies directly beneath these posterior ribs. A fracture of any of those three ribs on the left should automatically raise suspicion for splenic injury, even if the patient is hemodynamically stable at presentation. Contusions can expand slowly. I saw a trauma case where the spleen looked fine on the initial CT and a delayed rupture occurred six hours later — the patient was sent home because the first scan was "negative." Another counter-intuitive point: the heart's apex points left, but the heart itself is predominantly a left-sided organ. Only about one-third sits to the right of the midline. When you're auscultating the left heart borders, you're hearing across the left ventricle and left atrium primarily. S3 and S4 heart sounds are loudest at the apex, which is the 5th intercostal space at the midclavicular line on the left. The left colic flexure can also be a site of closed-loop obstruction if the colon is fixed by adhesions — a surgical emergency that's easy to miss because the pain pattern overlaps with renal colic, splenic pathology, and gynecological conditions. If a patient has left upper quadrant pain with vomiting and no bowel movements, don't stop at "probably gastritis."
A note on variation: Situs inversus affects roughly one in 10,000 people. In this condition, all organs are mirrored — the heart is on the right, the liver on the left, the stomach and spleen on the right side. If you're a medical student or clinician, learn to confirm laterality on every imaging study before you commit to a diagnosis. I once read a CT report that described a "right lower lobe mass" before realizing the entire thorax was mirrored. The mass was on the left. The patient would have been prepped for the wrong side. Kidney position also varies. A left nephroptosis (floating kidney) can cause left flank pain that's positional — worse when standing, relieved when supine. This is more common in thin women and is often missed on standard supine CT because the kidney reduces back into place when the patient lies down. An upright IVU or MRI is needed to capture the displacement. Finally, the left adrenal gland has a different venous drainage than the right. The left adrenal vein drains into the left renal vein, while the right drains directly into the IVC. This matters surgically — during left adrenalectomy, controlling the adrenal vein requires mobilizing the kidney slightly to access the renal vein junction. Miss this anatomy and you're bleeding into the retroperitoneum.