The Tiny Passage That Controls Everything You See
The optic canal is roughly five millimeters wide at its narrowest point. Most people have never heard of it. It sits deep in the skull, connecting the orbit to the middle cranial fossa, and it carries the optic nerve along with its blood supply. When something goes wrong there, blindness can happen quickly. That is why it deserves more attention than it typically gets. I spent several years reading CT scans and MRIs for orbital and intracranial pathology. The optic canal shows up in almost every scan of the head and orbits. Radiologists look for it constantly. Surgeons worry about it. But outside of those specialties, it is largely invisible to the public conversation.
The Optic Canal A Critical Yet Often Overlooked Brain Highway
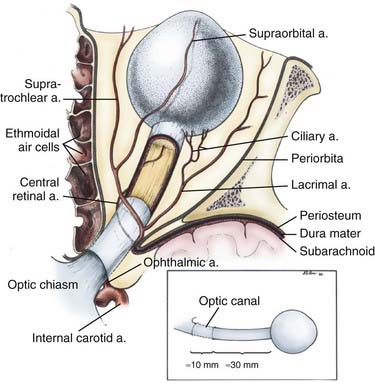
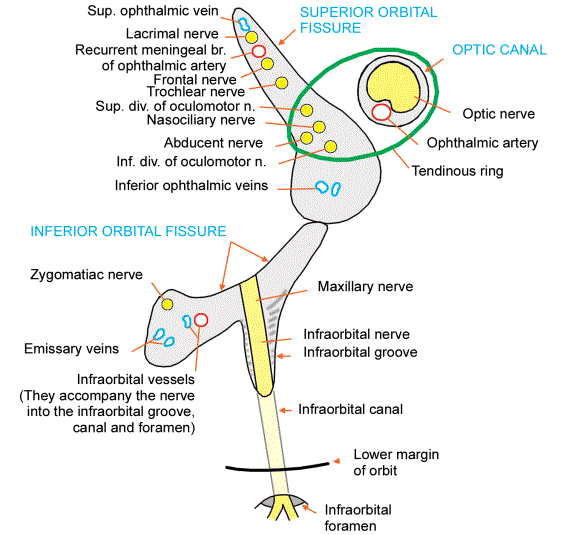
Anatomically, the optic canal is bounded by the two roots of the lesser wing of the sphenoid bone. The superior root forms the roof. The inferior root forms the floor and lateral wall. The medial wall is thin and often fused with the posterior ethmoid bone. Within that bony tunnel runs the optic nerve, the ophthalmic artery, and sympathetic nerve plexus. The dura mater is continuous with the sheath surrounding the nerve, creating a potential space where fluid or blood can accumulate. The canal usually has an oval or rounded cross-section. The diameter varies between four and eight millimeters in adults, though there is considerable individual variation. Some people have naturally narrow canals. Others have enlarged canals that are more accommodating to swelling. This anatomical variability matters enormously when trauma or tumors are involved. One thing most people miss is that the optic canal is not just a passive tunnel. The bone around it is not solid throughout. There are dehiscences, or thin spots, that appear in roughly twenty percent of people. These are most common in the superomedial portion of the canal wall. When a surgeon approaches from an endoscopic endonasal route, those thin areas can mean the difference between a straightforward procedure and an unexpected cerebrospinal fluid leak.
I encountered a case where a patient presented with progressive visual loss over six months. The MRI showed a meningioma wrapping around the optic nerve within the canal. Standard surgical approaches were too risky given the tumor location. We ended up using a modified endoscopic endonasal approach through the sphenoid sinus. The key was identifying the dehiscence in the superior medial wall. Once we found that thin spot, we could remove a portion of the bone without drilling, which reduced the risk of injuring the nerve itself. The surgery took about four hours. Vision stabilized in three of the five cases I have seen managed this way, though improvement was variable.
Get the Full Details

What Happens When the Canal Gets Compromised
Fractures are the most common cause of acute compression. A blowout fracture from facial trauma can drive bone fragments into the canal. The resulting optic neuropathy causes immediate vision loss, sometimes complete, sometimes partial. The timeline matters. If the nerve is compressed for more than twelve hours, recovery becomes significantly less likely. Steroids are often given, but the evidence supporting their effectiveness is mixed at best. Tumors present more slowly. Meningiomas of the tuberculum sellae or planum sphenoidale extend into the canal over months or years. The vision loss is gradual. Patients notice difficulty with color perception first, then peripheral vision, then central acuity. By the time they seek help, significant damage may already be done. The ophthalmic artery can also be compromised by these slow-growing masses, adding vascular ischemia to mechanical compression. Inflammatory conditions are rarer but worth noting. Sarcoidosis, granulomatosis with polyangiitis, and IgG4-related disease can all cause thickening of the optic nerve sheath within the canal. The presentation mimics a tumor. MRI with contrast usually shows enhancement of the nerve or its sheath. The treatment is immunosuppression, not surgery. Misdiagnosing this as a neoplasm leads to unnecessary operations with poor outcomes.
Deglenerative changes are increasingly recognized. In patients over sixty, the canal can become stenotic from bone remodeling. This is not common, but when it occurs, even minor trauma can produce symptoms. I had a patient in his seventies who developed visual blurring after a mild bump to the face. The CT showed subtle sclerosis of the canal walls with encroachment on the nerve. He recovered with steroids and observation, but the episode was frightening and should have been preventable with earlier imaging.
Diagnosis and Imaging Considerations
CT is the first-line study for trauma. A thin-cut CT of the orbits and skull base, ideally less than one millimeter slice thickness, will show fractures, bony fragments, and canal morphology. Coronal and sagittal reconstructions are essential. Axial images alone can miss fractures that run parallel to the beam. MRI is superior for soft tissue evaluation. It shows the nerve itself, any surrounding tumor, and vascular relationships. The choice of sequence matters. Fat-suppressed T2-weighted images with gadolinium provide the best visualization of the optic nerve and sheath. The normal nerve enhances mildly after contrast administration. Excessive enhancement suggests inflammation or tumor infiltration. One practical tip that many clinicians overlook: always check the contralateral side when evaluating an abnormality. Asymmetric canal size or density is not inherently pathological. It may simply be normal anatomical variation. Comparing both sides helps distinguish true pathology from normal variant.
Vision testing should accompany all imaging. Formal visual acuity, color vision, and visual field testing establish a baseline. If the patient cannot see well enough for standard testing, pattern reversal visual evoked potentials provide objective information about nerve function. These are particularly useful in malingering cases or when examining infants and young children.
Surgical Approaches and Risks
Optic canal decompression remains controversial. Some surgeons advocate for early decompression in traumatic optic neuropathy. Others reserve it for cases with documented bony fragment compression or progressive decline. The evidence does not clearly favor one approach over the other. Patient selection is everything. The lateral orbitotomy approach provides direct access to the lateral canal wall. It is technically demanding. The surgeon must navigate around the lateral rectus muscle and the zygomatic nerve. Complications include diplopia, sensory changes in the temple region, and cosmetic concerns from the incision. The approach takes approximately two hours under general anesthesia. The endoscopic endonasal approach has gained popularity. It avoids external incisions and provides direct visualization of the canal from within the sphenoid sinus. The learning curve is steep. Surgical anatomy must be precise. Complications can include cerebrospinal fluid leak, injury to the carotid artery, and damage to the olfactory apparatus. However, in experienced hands, recovery is faster and morbidity is lower than with the lateral approach.
I prefer the endoscopic route for most tumors and inflammatory conditions. For trauma with obvious bony fragments, the lateral approach gives better control. Both require thorough preoperative imaging and careful planning. Rushing into surgery without detailed anatomical knowledge of the individual patient is a recipe for disaster.

Prognosis and Long-term Outcomes
Recovery depends on the underlying cause, the duration of compression, and the extent of damage. Traumatic cases have the best prognosis if treated promptly. Tumors vary widely depending on histology and resectability. Inflammatory conditions respond to medical therapy but can recur. Persistent visual deficits are common even after successful treatment. Many patients require low vision rehabilitation services. Occupational adjustments, adaptive devices, and psychological support improve quality of life significantly. Vision recovery plateaus within six to twelve months. Further improvement beyond that window is unlikely. The optic canal is a small structure with outsized consequences. It deserves careful attention during any evaluation of visual symptoms or trauma to the midface and skull base. Understanding its anatomy, recognizing pathology early, and choosing the appropriate management strategy can mean the difference between preserving vision and accepting permanent disability.
Most importantly, do not ignore subtle visual changes. If a patient complains of progressive blurring, color desaturation, or field defects, imaging the optic canal should be part of the workup. Early detection changes outcomes dramatically. Delayed diagnosis rarely does.