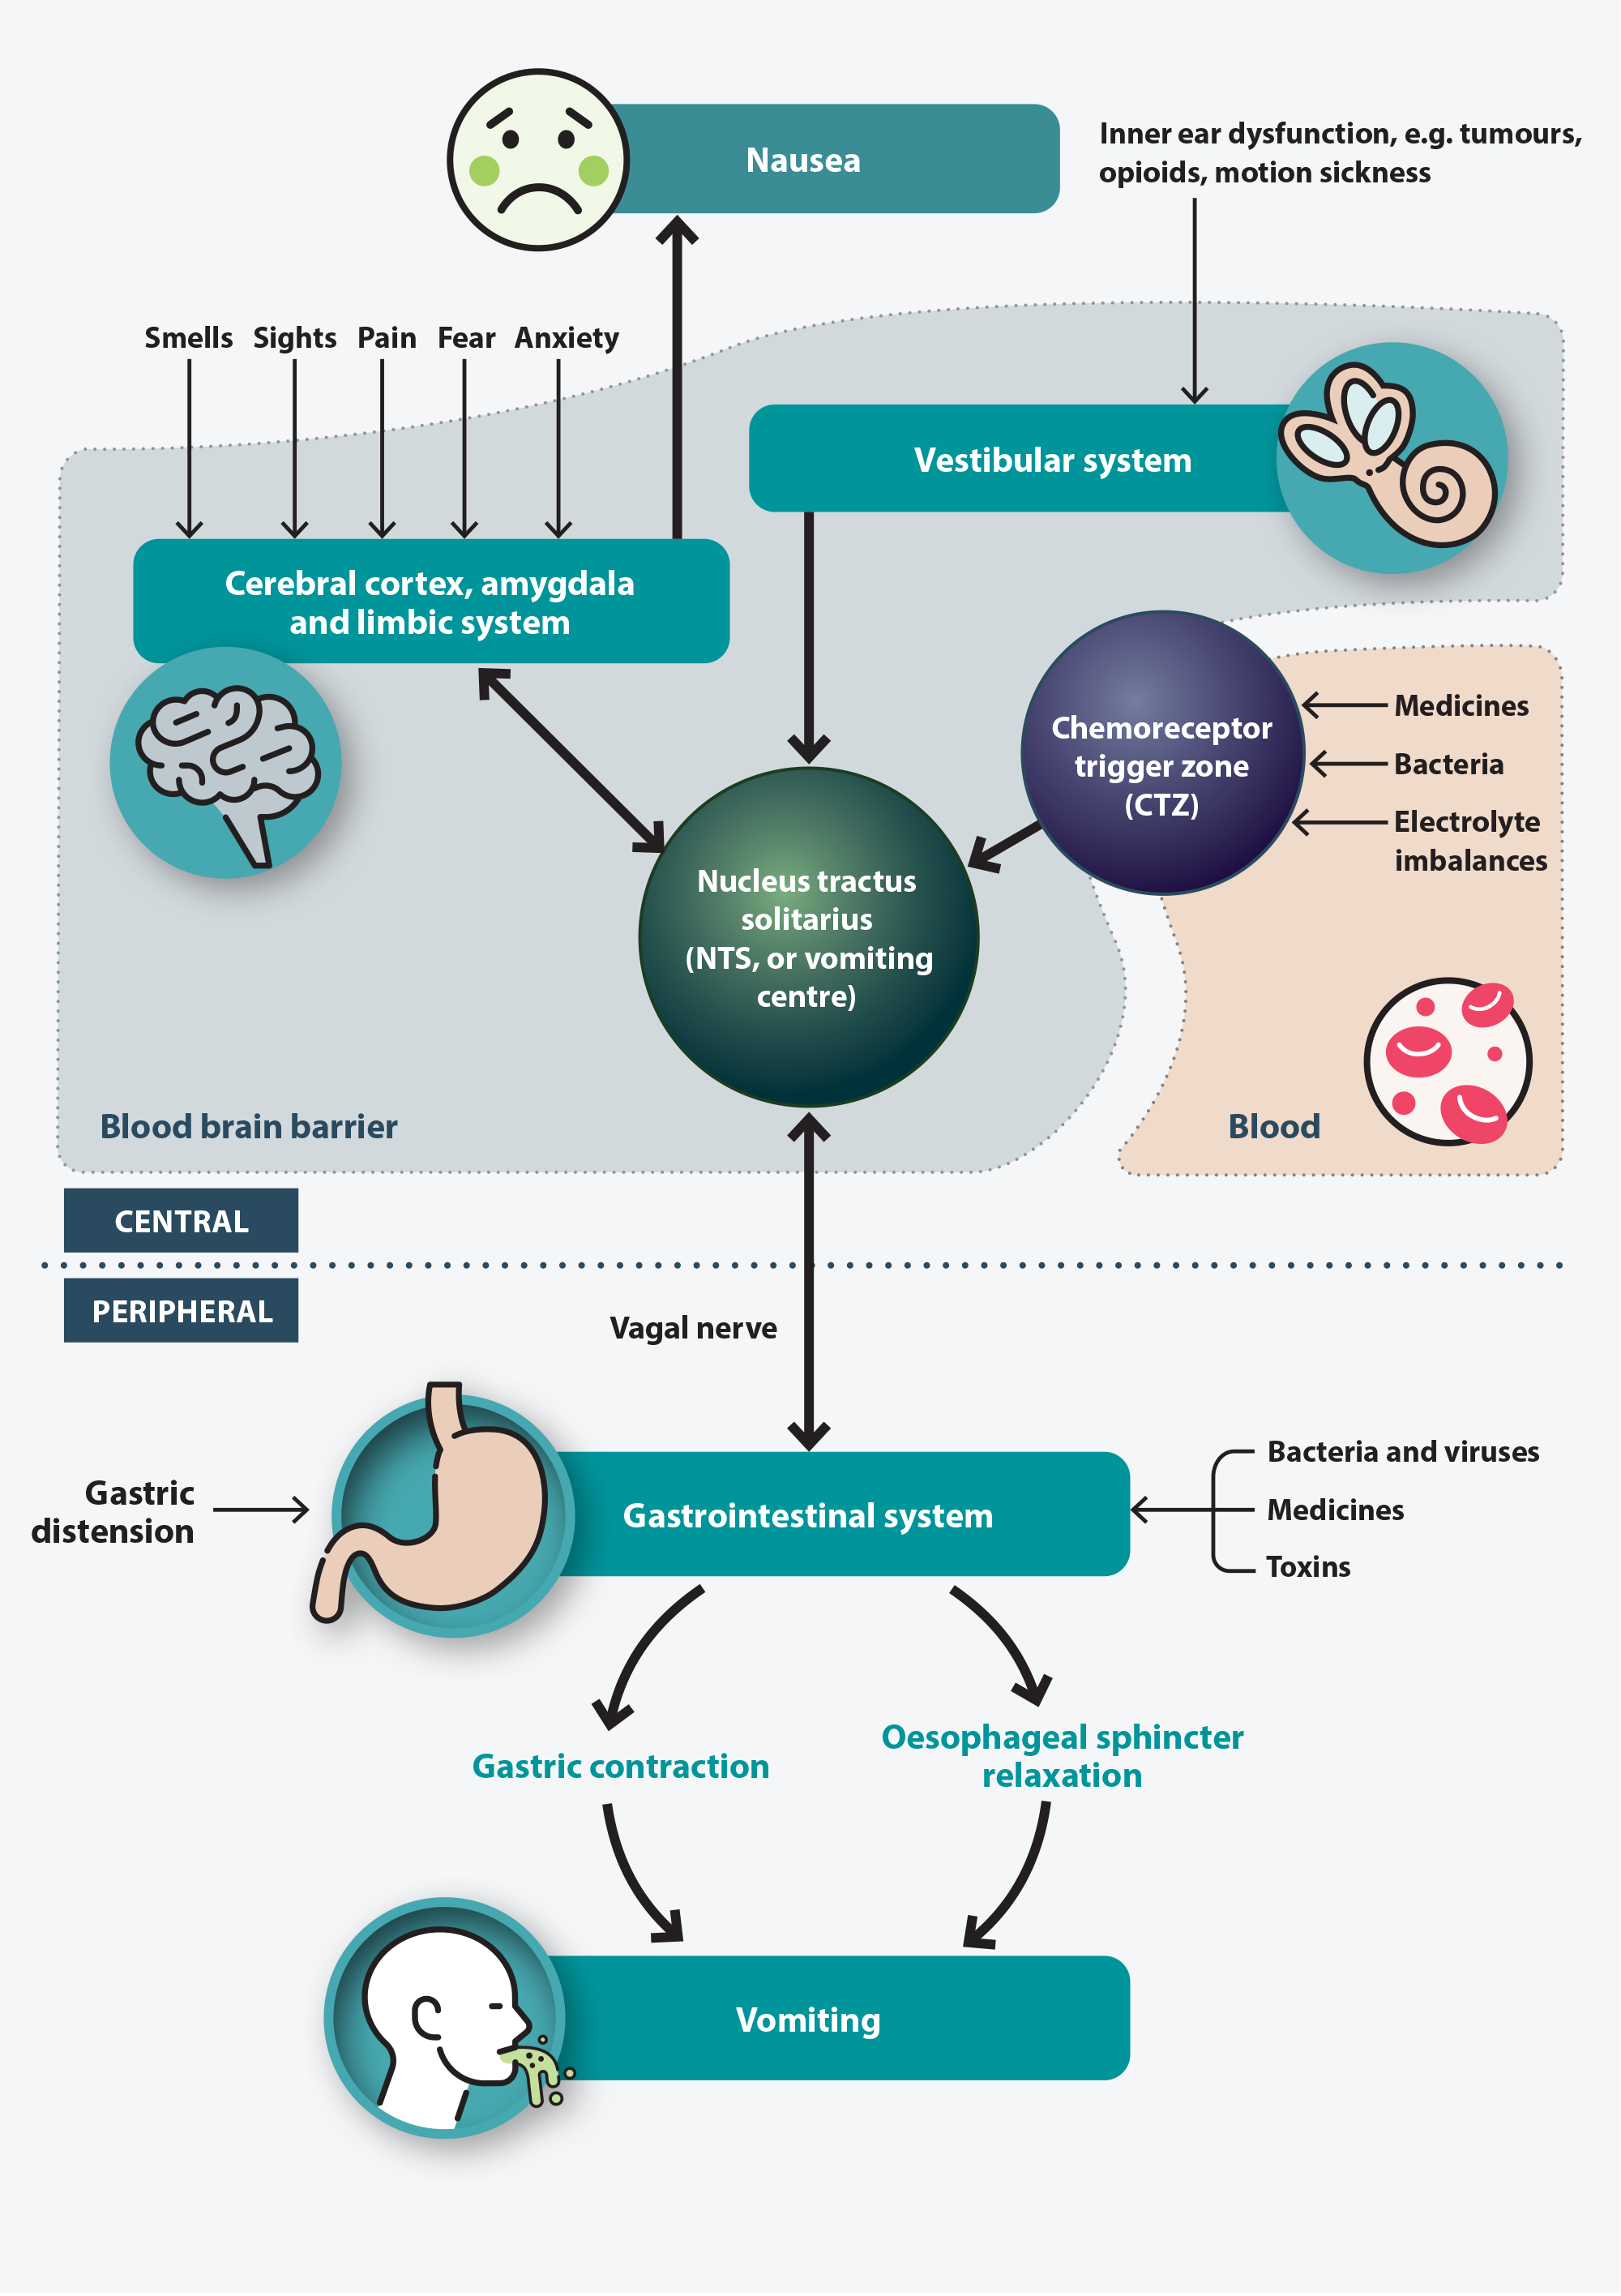
What NV Actually Means in Clinical Practice
NV stands for nausea and vomiting. It is one of those abbreviations that appears constantly in charting, medication orders, and nursing notes. At first glance it seems straightforward. The reality of using it effectively is more complicated than writing two letters on a flow sheet. I have seen documentation get sloppy because people assume NV covers everything about a patient's emesis history. It does not. NV is shorthand for symptom presence, not a substitute for actual assessment. When I worked in the emergency department, I watched residents chart "NV x 3" and walk away without noting whether the patient had bilious emesis, hematemesis, or simple non-bloody regurgitation. That level of documentation creates problems later, especially when you are deciding between antiemetics or escalating to imaging.
The Nv Medical Abbreviation A Complete Guide To Nausea And Vomiting Assessment Documentation And Clinical Decisionmaking
Here is what most people miss about NV documentation. The abbreviation itself is fine. The issue is what gets left out when you rely on it. In clinical settings, NV should never be the only entry in your assessment. You need to capture onset, frequency, character of emesis, associated symptoms, fluid intake status, and what interventions have already been tried. A practical framework I use goes like this. Document the timeline first. When did the nausea start relative to vomiting? Often patients report nausea hours before they actually vomit. Noting that sequence matters because it changes your differential. Post-chemotherapy nausea typically precedes vomiting by a known window. Post-operative NV often presents differently depending on the anesthesia agent used. Character matters too. I once had a patient whose chart simply read "patient reports NV." The nurse had not documented whether the vomitus contained blood, bile, or coffee-ground material. By the time I saw the patient, he was tachycardic and hypotensive with a distended abdomen. It turned out to be a bowel obstruction with early ischemic changes. If the initial documentation had captured that the emesis was fecaloid in nature rather than just labeled NV, we might have gotten surgical consultation earlier. That was a close call and it cost the team another four hours of work.
Assessment Components That Actually Matter
When you document NV, you should be checking several specific things. Frequency is obvious but often poorly recorded. How many episodes? Were they productive or non-productive retching? Productive retching without expulsion still dehydrates patients and raises intragastric pressure. That distinction changes your fluid management decisions. Associated symptoms need explicit notation. Dizziness suggests orthostatic hypotension from volume depletion. Headache with NV raises concern for increased intracranial pressure. Diarrhea alongside vomiting points toward infectious gastroenteritis rather than a surgical abdomen. Abdominal pain location is critical. Periumbilical pain migrating to the right lower quadrant with NV is textbook appendicitis until proven otherwise. Chart that migration specifically instead of just writing "abdominal pain present." Medication review is another area where NV documentation fails patients. I have reviewed charts where a patient was clearly experiencing drug-induced nausea from opioids, antibiotics, or metformin, but the documentation never connected the timing. The next provider ordered additional antiemetics instead of adjusting the offending medication. That is a common and preventable error.
Get the Full Details

Hydration markers deserve their own section in the note. Mucous membrane moisture, skin turgor, urine output, heart rate changes, and blood pressure trends give you a much clearer picture than a generic NV label. I usually document a quick hydration score based on these markers. It takes thirty seconds and prevents the kind of ambiguity that leads to delayed IV access and unnecessary repeat labs.
Decision-Making Implications of NV Documentation
The way you document NV directly influences what decisions get made afterward. A brief note saying "NV controlled with ondansetron" tells the next provider nothing about whether the dose was adequate, whether the patient tolerated oral intake afterward, or whether breakthrough nausea occurred later that shift. A more useful entry specifies the dose, route, time administered, and whether symptoms resolved within the expected timeframe. In surgical contexts, NV documentation affects clear-to-liquids clearance decisions. I have seen patients marked as diet advanced despite ongoing nausea because the chart only said "NV improved." Improved compared to what baseline? That vague language has led to post-op aspiration events in my experience. Be specific about improvement relative to the presenting complaint. For patients with chronic conditions, NV changes can signal deterioration before other markers appear. A heart failure patient developing new onset NV may be experiencing worsening renal perfusion or medication toxicity rather than a primary gastrointestinal issue. Recognizing that pattern requires you to document NV in context rather than as an isolated symptom entry.
Common Pitfalls to Avoid
One frequent mistake is documenting NV without noting the patient's oral intake status during the same period. If a patient has been vomiting and simultaneously refusing fluids, you need both pieces of information visible to anyone reading the chart. Without the intake data, you cannot accurately assess hydration trajectory. Another pitfall is using NV as a discharge disposition justification. "Patient tolerant of PO with no further NV" is not sufficient. You need to specify what "tolerant" means. Did the patient drink eight ounces? For how long were they observed? Any breakthrough symptoms after the observation window? Those details matter when the patient presents again two days later with dehydration. Some clinicians also neglect to document non-pharmacological interventions attempted. Position changes, ginger supplementation, acupressure wrist bands, and environmental modifications are part of the full picture. They are not secondary concerns. In pregnancy-related NV, for example, omitting these interventions from the record makes it impossible for subsequent providers to understand what has or has not been tried before escalating to prescription antiemetics.

The abbreviation NV itself is not problematic. The problem is using it as a shorthand that replaces actual clinical observation. Write the assessment. Document the details. The two letters will mean something when someone else reads them six hours later or on a different shift.