Understanding Newborn Breathing Patterns
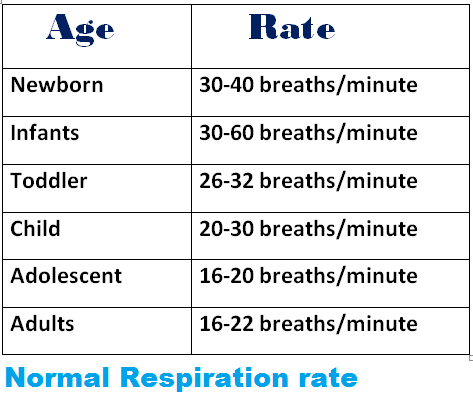
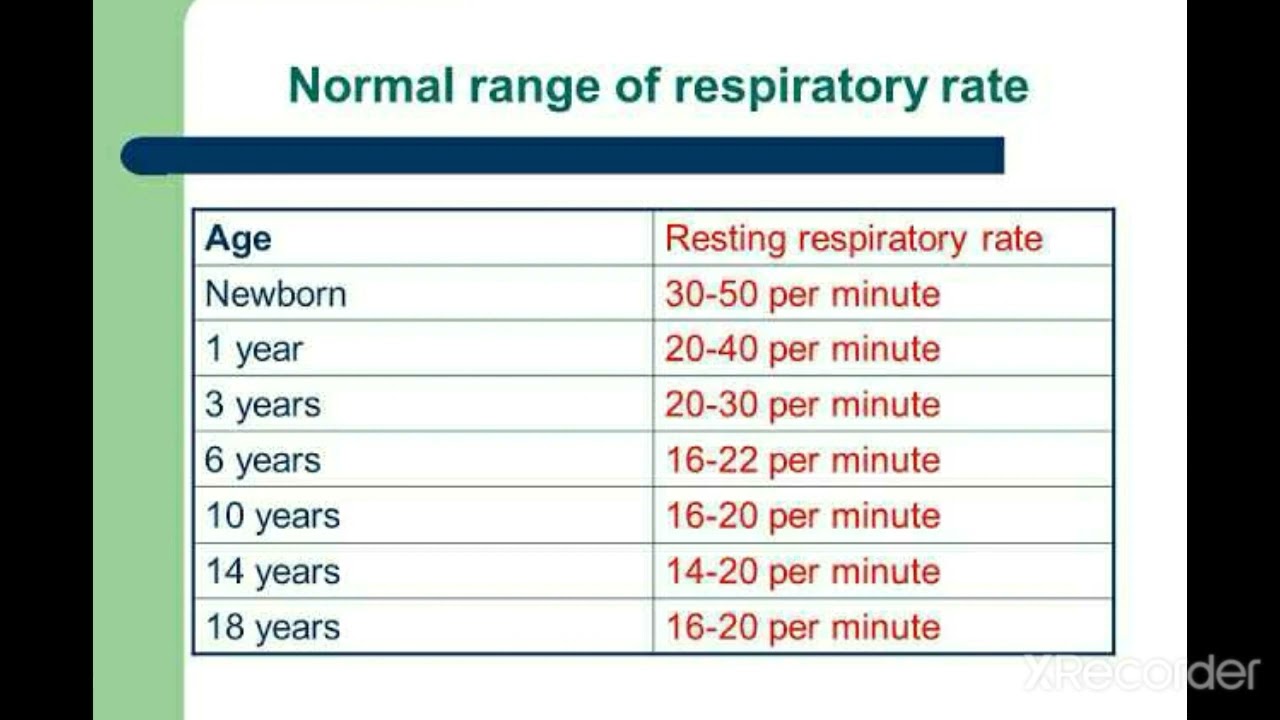
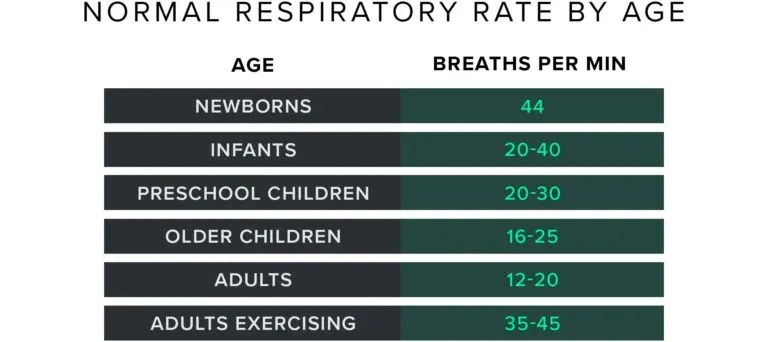
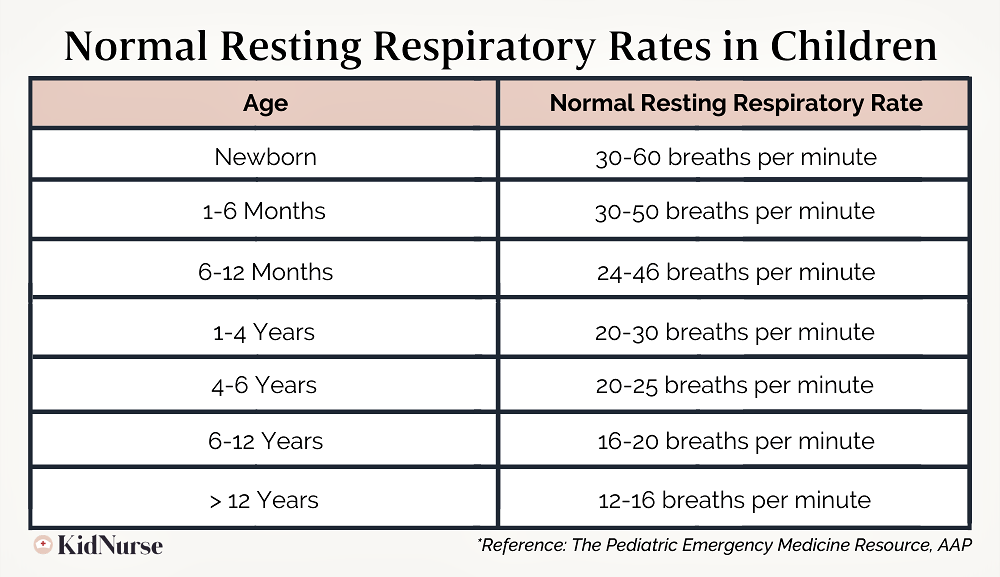
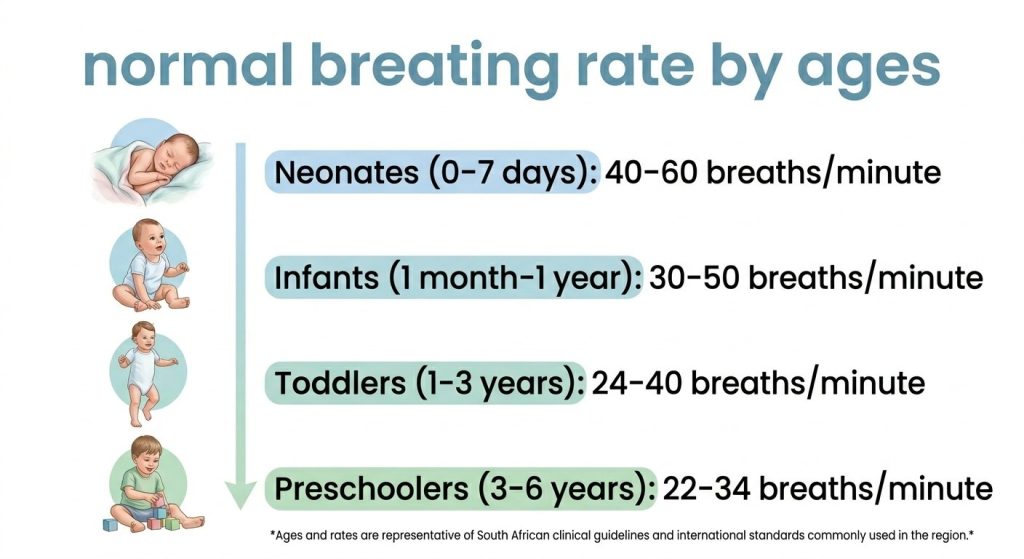
Most parents panic when they first check their newborn's breathing rate. They count breaths for a full minute, see a number that seems way too high, and immediately reach for the phone. Here is what actually matters about the normal respiration rate of newborns and why the numbers on the page don't always match what you are seeing at 3 AM. A healthy newborn typically breathes between 40 and 60 times per minute when quietly asleep. That is the clinical baseline you will find in pediatric references. Anything consistently above 60 breaths per minute for more than ten minutes is considered tachypnea and warrants medical evaluation. Anything below 30 is bradypnea and is a separate concern. But the range between 40 and 60 is where most confusion happens because newborn breathing is not like adult breathing. It is irregular by design. I spent years in neonatal units watching this exact scenario play out. Parents would call the pediatrician's emergency line because their baby's breathing looked nothing like the textbook drawing. The baby would pause for eight seconds, then take three rapid shallow breaths, then settle into a normal rhythm. The parent had counted during the pause and assumed respiratory distress. In almost every case, the pediatrician would ask them to come in, watch the baby sleep for five full minutes, and confirm periodic breathing. It is normal. It is not apnea of prematurity. It is just how immature respiratory centers work in the first few weeks of life.
Periodic breathing peaks around two weeks of age and usually resolves on its own by three months. During a periodic breath, you will see a pause lasting up to ten seconds followed by a cluster of faster breaths. The key differentiator from true apnea is that the baby does not change color during the pause. If the lips or face turn blue or pale, that is a different problem entirely.
How to Count Properly
Here is the part most guides skip: you cannot count newborn respiration while the baby is crying, feeding, or fussing. A crying newborn will regularly hit 80 breaths per minute, and that is not pathological. You need to count when the baby is in a deep sleep state. Ideally, count for a full sixty seconds. Thirty-second counts are acceptable if you multiply by two, but anything less than that introduces significant error because of the natural irregularity I just described. The practical method is straightforward. Wait until the baby has been asleep for at least fifteen minutes. Make sure the room is quiet and the baby is not wrapped too tightly. Place your hand lightly on the chest or abdomen and count each rise as one breath. Watch the chest wall move rather than listening. A lot of people try to count breaths by hearing air movements, but newborn nasal passages are tiny and airflow sounds are unreliable indicators of actual respiratory rate. I learned this the hard way with my first child. I was listening for breath sounds and consistently undercounted by roughly eight breaths per minute compared to what I later measured by watching chest movement. The difference mattered when I was trying to decide whether to go to the emergency room. Watching the chest resolved the ambiguity every time.
Get the Full Details
When to Worry
There are specific signs that go beyond a high number on a count. Grunting is one. If the baby is making a grunting sound at the end of each exhalation, that indicates increased work of breathing and possible respiratory distress. Nasal flaring is another. Retractions are the most clinically significant sign. Look between the ribs, above the collarbone, and below the rib cage. If those areas pull in deeply with each breath, the baby is working hard to move air and needs evaluation. Fast breathing alone without any of those other signs is less urgent in a term infant who is feeding well and has normal color. But fast breathing plus grunting plus retractions is a clear signal. In my experience, the parents who caught these early were the ones who knew what retractions looked like rather than just focusing on the number. They watched the chest wall and noticed the pulling before they even counted breaths.
Common Pitfalls
The biggest mistake people make is measuring after a bath or during fever. Both raise the respiratory rate significantly. A newborn with a temperature of 100.4 Fahrenheit or higher should be evaluated regardless of respiratory rate because fever in the first month of life is treated seriously. Another mistake is counting while the baby is swaddled tightly. A snug wrap can artificially slow chest expansion and give you a deceptively low number. Loosen the swaddle or unwrap the baby before counting. There is also a specific scenario that catches people off guard. I encountered a case once where a baby had a normal respiratory rate at rest but dropped to the low thirties during active feeding. The parents thought the baby was breathing fine because the resting count was normal. What was actually happening was mild upper airway obstruction that only became apparent when the baby was using more effort during feeds. The workaround was watching the baby breathe while feeding, not just while sleeping. That single additional observation caught a mild laryngomalacia that would have been missed otherwise.
Advanced Nuance: Apnea vs Periodic Breathing
Parents often confuse the two. True apnea in newborns is defined as a pause lasting longer than twenty seconds, or any pause accompanied by bradycardia or color change. Periodic breathing pauses are shorter and lack those secondary signs. The distinction matters because periodic breathing generally needs no intervention while true apnea requires monitoring and sometimes medication. One counter-intuitive point: preterm infants can have normal periodic breathing and still be at higher risk for true apnea later. If your baby was born before thirty-five weeks, even if they passed the routine screening in the hospital, periodic breathing patterns should still be monitored closely at home for the first three months. The respiratory center maturation timeline varies significantly with gestational age.
What Numbers Mean in Practice
If your newborn consistently breathes above 60 per minute while asleep and undisturbed for more than ten minutes, contact your pediatrician. If the rate drops below 30, seek care sooner rather than later. Between 40 and 60 is normal, but context matters. A rate of 55 in a baby who is eating well and sleeping peacefully is less concerning than a rate of 50 in a baby who seems lethargic and refuses feeds. Clinical context always outweighs the raw number. There is no reliable home monitor that replaces a visual count. Commercial pulse oximeters designed for home use are generally inaccurate at the perfusion levels found in newborn extremities. The red light flickering on a baby's finger often reads fine while the respiratory rate displayed may be off by ten or more breaths. Trust your eyes. Watch the chest. Count for a full minute. Repeat if something feels off. Most importantly, trust your instinct. If you are watching your baby and something about the breathing pattern feels wrong, it probably is. The numbers help, but parental intuition in the first few weeks of life is surprisingly accurate when it comes to detecting respiratory issues. I have seen too many cases where the clinician arrived and confirmed what the parent already knew.