Reading NKA on a Chart Is Easier Than You Think
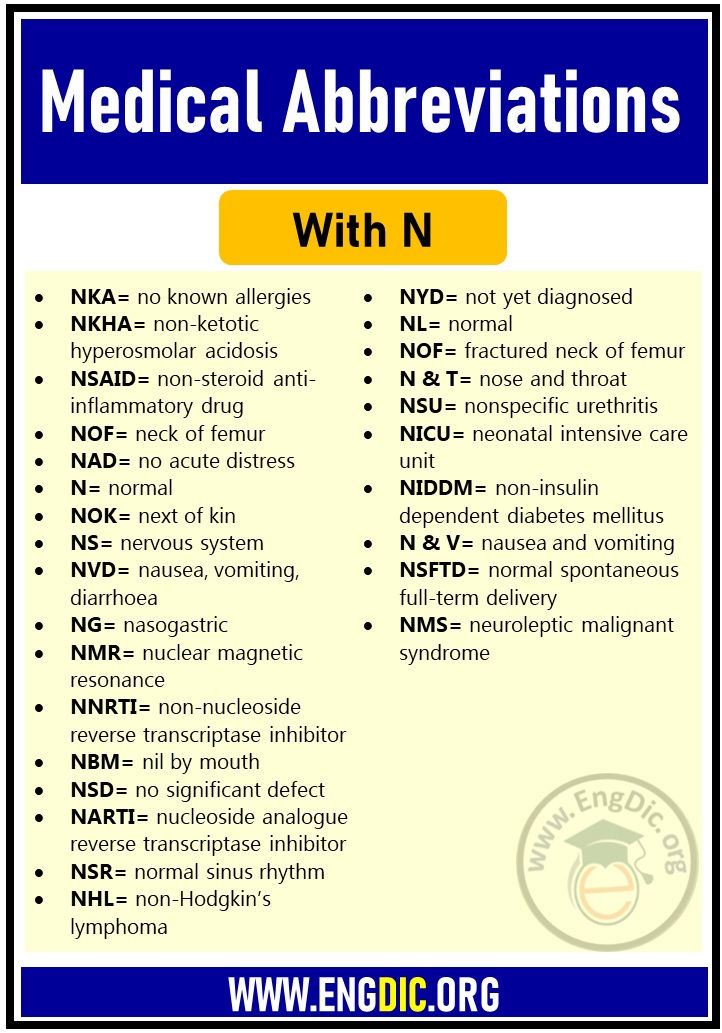
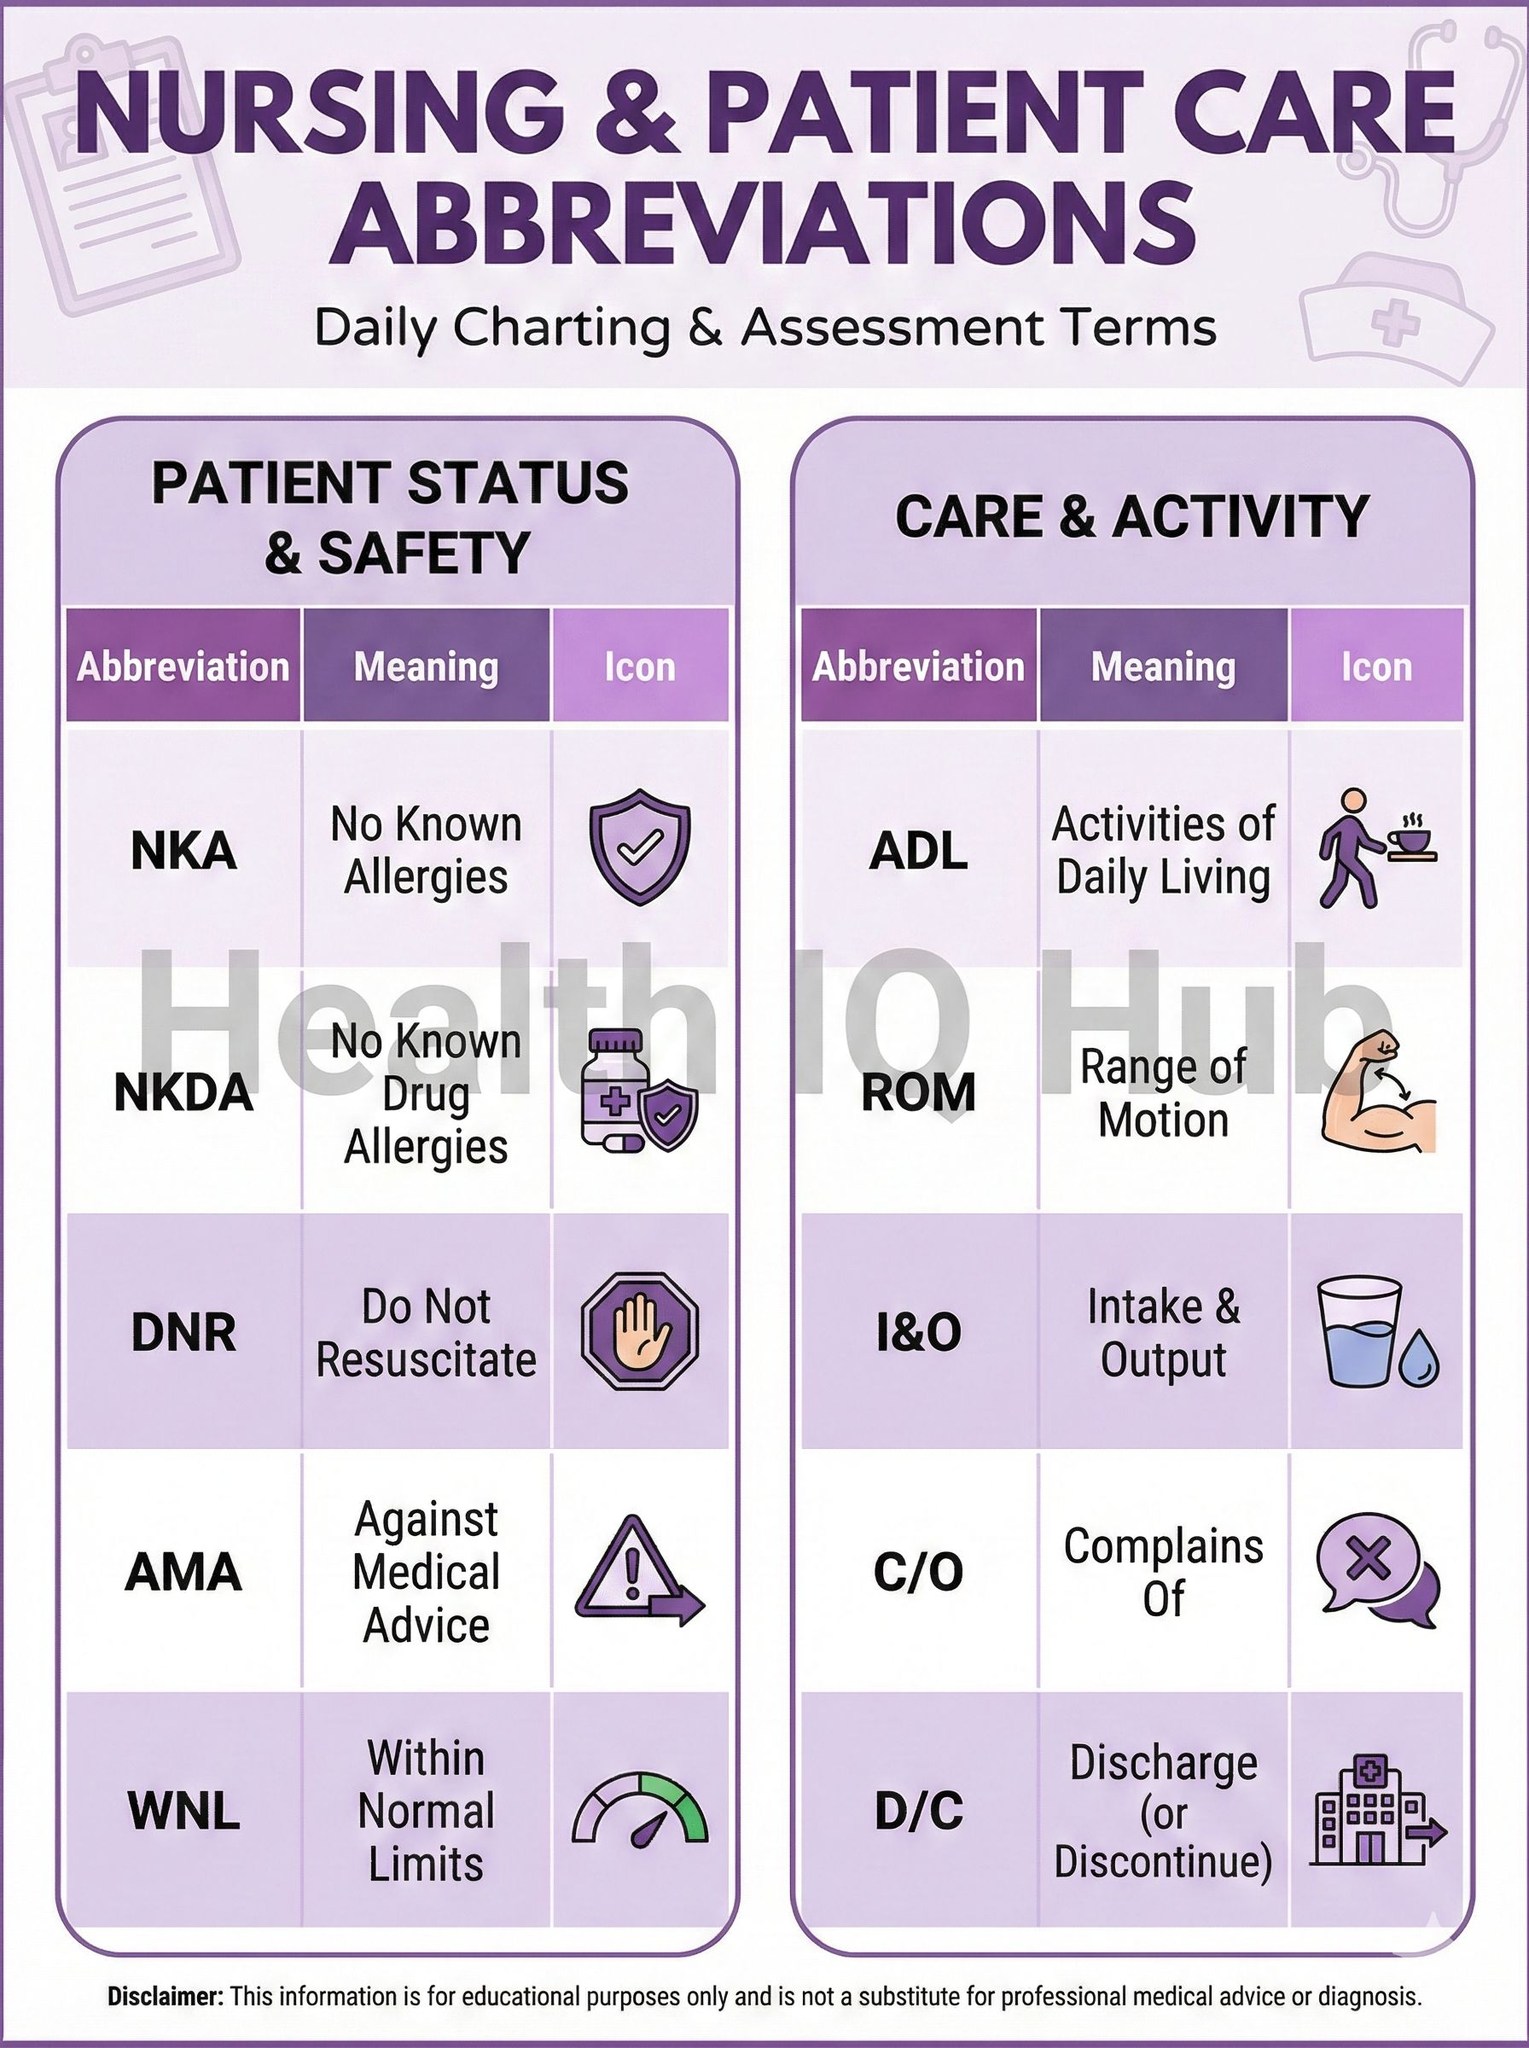
NKA stands for No Known Allergies. You will see it on admission forms, discharge summaries, medication orders, and pre-operative checklists. It is one of the most common abbreviations in clinical documentation, and understanding it properly matters more than you might expect. I spent years working on a busy med-surg floor where we wrote NKA on every new admission. The chart review software at the time did not auto-populate allergy fields consistently, so nurses and providers would handwrite it during intakes. I learned early that NKA does not mean the patient has no allergies. It means we do not currently know of any documented allergic reactions. That distinction is not semantic trivia. It is the difference between safe prescribing and adverse events.
The Nka Medical Abbreviation Decoded What Healthcare Professionals Really Mean When They Write It
When a clinician writes NKA, they are making a specific documentation statement: no allergy has been recorded in the available medical history at the time of entry. It is not a diagnosis. It is not a guarantee. It is a placeholder for negative allergy history as far as current records go. Here is how it actually functions in practice. A patient arrives for surgery. The anesthesiologist reviews the chart, sees NKA, and selects a neuromuscular blocking agent without checking a detailed allergy inventory. Six hours later the patient develops hypotension and urticaria. The post-op incident report traces it to a previously undocumented shellfish allergy that the patient forgot to mention during triage. The NKA notation was technically accurate based on available information, but clinically insufficient. This is why I started requiring a verbal allergy confirmation during every admission assessment after that event. It added roughly ninety seconds per patient intake and caught about three undocumented allergies per month on our unit.
Where NKA Appears and What It Signals
You will encounter this abbreviation in several clinical contexts, each with slightly different implications depending on who wrote it and when. Admission notes typically include NKA as part of the standard social or past medical history section. In those cases, the notation usually reflects a conversation with the patient or their family. The accuracy depends entirely on how thoroughly the admitting provider asks about allergies. Some protocols require asking about medications, foods, latex, and environmental triggers. Others only document medication allergies because those are considered highest risk for immediate clinical decisions. Pre-operative charts often carry NKA because the anesthesia team needs rapid allergy clearance before induction. Surgical teams rely on this notation to choose antibiotics, antiseptics, and dressings. A latex-sensitive patient marked NKA can face serious intraoperative complications if the standard supply kit includes latex gloves or catheters. I recall a case where a patient listed NKA on paper but had a latex allergy documented in an outside hospital system that had not transferred. We nearly used latex barriers during a laparoscopic procedure until the circulating nurse cross-referenced the external records manually. That saved us from a potential anaphylactic event. The workaround was simple: never trust a single NKA notation without verifying against at least one other source when surgery is planned.
Get the Full Details
Medication administration records sometimes show NKA next to the provider order. This serves as a reminder to check before dispensing, especially for high-alert medications like penicillin-class antibiotics, NSAIDs, and contrast dyes. Pharmacy verification workflows often treat NKA as insufficient for certain drug classes unless corroborated by an allergy score or screening tool.
Common Mistakes People Make With NKA
Beginners in clinical documentation often misunderstand what NKA actually represents. The most frequent error is assuming it equals zero allergy risk. It does not. NKA simply indicates no known documented reaction. A patient can still have an undiagnosed or undisclosed allergy, and those situations cause most adverse drug events in hospital settings. Another pitfall involves confusing NKA with NKDA. Both abbreviations appear in clinical notes, and while many facilities treat them interchangeably, some institutions use NKDA to mean No Known Drug Allergies specifically, which is narrower than NKA. If you are writing orders or interpreting charts, verify which convention your facility uses. Mixing them up can create documentation gaps during handoffs. There is also the issue of abbreviation compliance. The Joint Commission and ISMP maintain lists of abbreviations that should be avoided in clinical writing because they are prone to misinterpretation. NKA itself is generally accepted, but some organizations flag it because sloppy handwriting can make NKA look like NKA something else or NA. In electronic health record systems this concern disappears since the field is standardized. In paper-based settings, I learned to write it out fully whenever documenting a critical allergy status change. It takes three extra seconds and prevents ambiguity during midnight shifts when someone is reading a faded note under fluorescent lights.
How to Document NKA Correctly
Proper documentation goes beyond writing three letters on a form. Here is what I found effective over time. First, always specify the source of the NKA notation. Did the patient report it? A family member? Previous records? An outside facility? Adding a brief qualifier like NKA per patient interview or NKA per prior records makes the entry clinically useful rather than decorative. Second, document the date and the person who verified the allergy status. An NKA written six months ago during a routine physical may no longer reflect current reality. Allergies can develop at any time, and new sensitizations are particularly common in hospitalized patients exposed to multiple medications and devices.
Third, when uncertainty exists, write NKA with a note to confirm rather than leaving it blank or assuming safety. In one instance I managed, a patient came in with NKA from a previous admission four years earlier. A skin prick test during that stay revealed a penicillin allergy the patient had never reported. Updating the allergy list immediately changed the antibiotic selection and avoided a rash that would have extended the hospital stay by two to three days. Early verification saves more than time.
Limitations and When NKA Should Not Be Trusted
NKA has real limitations that clinicians need to accept frankly. It is only as reliable as the information available at the moment of documentation. Patients with cognitive impairment, language barriers, or developmental disabilities may be unable to report allergies accurately. In those cases NKA is essentially meaningless unless a caregiver or guardian provides history. Assuming safety in those scenarios is risky. Emergency department settings present another problem. Triage documentation often prioritizes chief complaint over comprehensive history taking. An NKA entered during a fast-paced ED intake may not reflect a thorough review. I have seen it repeatedly. The notation is correct in the narrow sense but clinically inadequate for the full scope of care the patient will eventually receive. For patients with complex medication regimens or multiple comorbidities, NKA should always be followed by active allergy surveillance throughout the care episode. This means reassessing at each transition of care, updating the record when new reactions occur, and communicating the current allergy status clearly to every provider involved. Relying on a single NKA entry across an entire admission chain is a fragile practice.
If you need a more reliable alternative to NKA notation, some institutions use allergy bands combined with electronic alert systems. Others have adopted standardized allergy assessment tools that require providers to rate allergy confidence on a scale before accepting NKA as sufficient documentation. These systems add administrative steps but significantly reduce missed allergies during care transitions. The trade-off is real. They take additional time during intake, and staff turnover can undermine consistent adoption. Still, they represent a meaningful improvement over relying on a three-letter abbreviation alone. The bottom line is straightforward. NKA is a useful clinical shorthand, but it is not a clinical conclusion. Read it carefully, verify it when it matters, and document with enough context that the next person reading the chart understands exactly what the notation was based on. That habit alone prevents most of the problems I encountered throughout my career.