
What Actually Happens When You Get Motion Sick
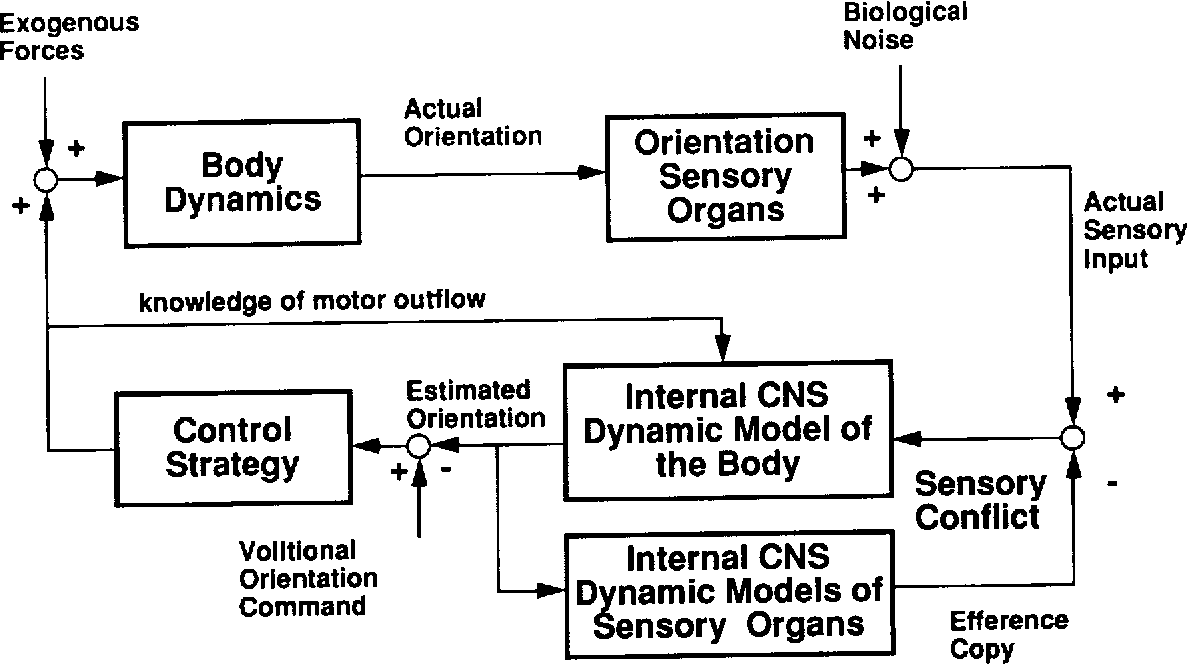
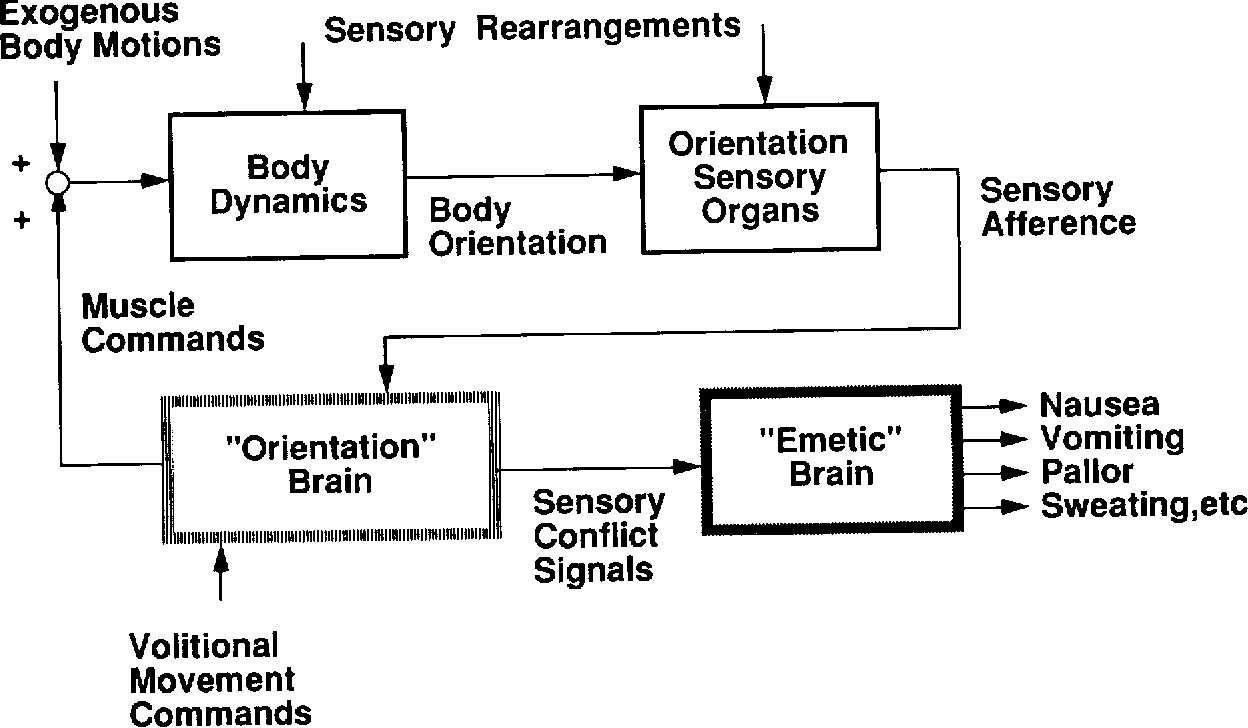
The short version is that your brain thinks you're dying. Your vestibular system, which lives in the inner ear and consists of the semicircular canals plus the otolith organs, sends signals about head movement and linear acceleration directly to the brainstem. When those signals conflict with what your eyes are reporting, the mismatch triggers an autonomic response that includes nausea, cold sweat, and salivation. This isn't some mild discomfort. It's a full physiological cascade. The nucleus tractus solitarius acts as the main convergence point for vestibular, visual, and proprioceptive inputs. When the firing rates from the vestibular nuclei don't match the predicted visual flow field, the area postrema gets activated and you feel sick. The area postrema is the chemoreceptor trigger zone. It sits outside the blood-brain barrier and monitors the blood for toxins, which is why the brain sometimes interprets sensory conflict as poisoning. That's the evolutionary theory anyway. The conflict detection system was likely designed to detect neurotoxins, and motion sickness is essentially a false positive on that detection system.
The Neuroscience Of Motion Sickness How Your Brains Conflict Detection System Causes Carsickness Sea Legs And Space Chil
It is the same mechanism across all environments. The vestibular system doesn't care whether you're in a car, on a boat, or floating in a spacecraft. It only cares whether the sensory inputs are coherent. In a car your eyes tell your brain you're stationary because you're looking at the dashboard or your phone. Your semicircular canals detect the turns and accelerations. The mismatch produces carsickness within minutes for sensitive individuals. On a boat your vestibular system registers pitch, roll, and heave at frequencies between 0.05 and 0.5 Hz. Your eyes may not register the full amplitude of the motion, especially if you're below deck, and the result is seasickness. In microgravity the otolith organs stop detecting linear acceleration because there is no gravity vector to reference. Astronauts experience Space Adaptation Syndrome for the first three days because the brain receives confusing gravity-referenced signals from the gut and proprioceptors while the vestibular system reports null. About 70 percent of astronauts go through this. I spent a few years working in a vestibular lab running simulator studies. The most annoying finding wasn't the data collection itself. It was watching people degrade in real time. A subject would sit in a motion platform doing a standard pitch-rotation protocol and start fine. Around minute twelve their breathing would change. By minute eighteen they'd lose color in the face and need to remove the headset. We had one participant who could handle 0.3 Hz rotational motion without issue but became symptomatic the moment we introduced a 0.08 Hz heave component. The low-frequency vertical oscillation was the trigger. She told me it felt like her stomach was being pulled downward repeatedly. That specific frequency range is known to be particularly destabilizing because it falls right in the resonance band of the human vestibulospinal reflex.
Why Your Brain Can't Just Get Over It
The conflict detection system doesn't have a simple on-switch. You can't will yourself past it because it involves the brainstem and the autonomic nervous system, which operate below conscious control. What does work is reducing the magnitude of the sensory mismatch. The most reliable method is providing a visual reference that moves consistently with your vestibular input. In a car that means looking at the horizon. In a plane that means watching the wings or the runway lights. It sounds obvious but most people do the opposite. They look down at their phone or read a book, which eliminates the visual reference and makes the conflict worse. Here's something most people don't understand. The mismatch isn't just about what you see versus what you feel. It's also about what your brain predicts. Predictive coding models show that the brain constantly generates predictions about sensory input. When the actual input deviates significantly from the prediction, the error signal triggers the nausea response. This is why novelty matters. A route you drive every day won't make you sick even if it has sharp turns. The brain has built up accurate predictions for that specific motion profile. The first time you take a ferry crossing is almost universally worse than the third or fourth time because your brain hasn't yet learned the predictability pattern of that particular motion environment.
Get the Full Details
What Actually Helps And What Doesn't
Ginger has moderate evidence behind it. A few studies show it reduces nausea severity by about 30 to 40 percent compared to placebo. It works through 5-HT3 receptor antagonism in the gut, which is the same pathway that antiemetics like ondansetron target, just less potently. Taking 1 gram of dried ginger powder about thirty minutes before travel is the typical effective dose. It's not a cure. It reduces symptom intensity. Scopolamine patches are the clinical gold standard. A transdermal patch delivering 1 mg over seventy-two hours blocks muscarinic acetylcholine receptors in the vestibular nuclei. It prevents the signal cascade before it starts. The downside is dry mouth, blurry vision, and drowsiness. Some people experience urinary retention too. It requires a prescription in most countries and needs to be applied at least four hours before travel to be effective. If you apply it after symptoms have already started, it won't help much. Meclizine and dimenhydrinate are over-the-counter antihistamines that cross the blood-brain barrier and block H1 receptors in the vestibular system. They reduce symptoms but cause significant drowsiness. You shouldn't drive after taking them. I've seen people try to power through the sedation and end up making dangerous decisions because their reaction time drops by roughly a third. That's not a minor effect.
Acupressure wristbands exist. The evidence is mixed. Some studies show a small benefit for motion sickness specifically, while others show no difference from placebo. The pressure point is P6 on the inner wrist. If you want to try them, they're cheap and have no side effects. Worst case you waste five dollars. Best case you get some relief.
The Habituation Problem
Repeated exposure does lead to habituation. The brain learns to suppress the conflicting signals over time. This is why sailors who spend weeks at sea stop feeling sick. The problem is that habituation is motion-specific and environment-specific. Someone who habituates to boat motion doesn't necessarily habituate to car motion or flight turbulence. The neural adaptation is tied to the specific sensory conflict pattern. You're training a specific vestibular-visual integration pathway. It doesn't transfer well to different motion profiles. There's also the issue of aftereffects. After you habituate to one type of motion and then stop, the adapted state doesn't carry over permanently. Re-exposure after months of non-travel can cause a temporary resurgence of symptoms. The habituation decays with disuse. This is particularly relevant for people who travel infrequently. A cruise once a year means you're essentially starting from scratch each time.
Edge Case That Nobody Talks About
Virtual reality induces motion sickness through the same conflict mechanism but on a different timescale. The delay between head movement and visual refresh rate creates a proprioceptive-vestibular mismatch that hits even people who never get carsick in real life. The acceptable latency threshold is around twenty milliseconds. Most modern headsets manage that now. The bigger problem is field of view. Narrow FOV vignettes reduce the peripheral motion cues that your brain uses to resolve conflicts, making the mismatch more severe. I had a colleague who could spend six hours in a full immersion simulator without issues but got nauseous after twenty minutes using a consumer VR headset. The 110-degree FOV versus his previous 200-degree setup was the difference. The wider the field of view, the more your vestibular system can use visual flow to confirm motion signals. Another overlooked factor is respiratory sinus arrhythmia. Shallow breathing during motion sickness actually worsens the symptoms. The autonomic dysfunction that causes nausea also disrupts normal breathing patterns. People start hyperventilating slightly without realizing it. Controlled diaphragmatic breathing at six breaths per minute can reduce the severity by lowering sympathetic nervous system activation. It's a small intervention but it addresses a real physiological component of the response. Genetic factors play a role too. Certain variants in the COMT gene affect dopamine metabolism in the vestibular nuclei and correlate with motion sickness susceptibility. Women report symptoms at higher rates than men, possibly due to hormonal modulation of the vestibular system. Estrogen influences serotonin receptor sensitivity in the area postrema. This is why some women experience worse motion sickness during certain phases of their menstrual cycle. It's not in your head. It's in the receptor chemistry.
Practical Summary
If you're dealing with motion sickness regularly, the most effective approach is a combination. Take scopolamine if you can get a prescription and can tolerate the side effects. Use ginger as a supplement if you want something OTC. Position yourself so you can see the horizon or a stable visual reference. Avoid reading or screen use during movement. Breathe slowly. Habituates through gradual, repeated exposure if the motion is predictable and regular. But if your motion exposure is infrequent and unpredictable, habituation will never fully catch up. The conflict detection system is built to err on the side of caution. It would rather make you sick once than miss a real toxin. That's the fundamental tradeoff your brain is making every time you get carsick on a winding road.


