How the Somatosensory Cortex Actually Maps Your Body
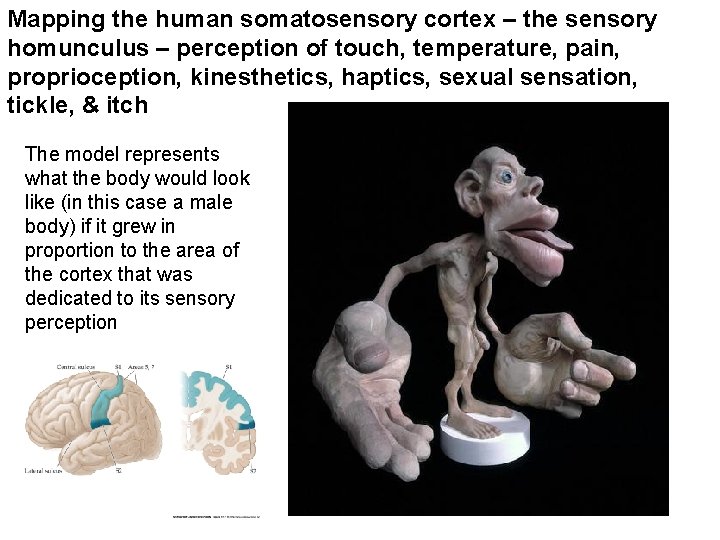
The postcentral gyrus sits about two centimeters behind the central sulcus, and it is where most of your tactile perception actually gets processed. I spent weeks calibrating EEG electrodes for a vestibular study, and one of the first things that surprised me was how much individual variation there is in somatotopic maps. Two people can have the same brain scan protocol, but the hand area in one might sit slightly more anterior than in the other. It matters when you are trying to stimulate a specific region with TMS. Wildred Penfield mapped this at McGill in the 1950s using electrical stimulation on conscious patients during neurosurgery. He found that touching one spot on the cortex produced a sensation on a specific body part, while another spot produced a completely different sensation elsewhere. This created the sensory homunculus, a distorted map where the lips and hands are massively enlarged relative to the trunk because they have higher receptor density and more cortical representation.
The Mysterious World Of Somatosensory Cortex Unveiling The Secrets Of Touch And Perception
There are fourBrodmann areas here, numbered 3a, 3b, 1, and 2, arranged from posterior to anterior. Area 3b is the main entry point for discriminative touch. It receives the bulk of thalamic input from the ventral posterolateral nucleus. If you lesion area 3b specifically, you lose the ability to perceive fine tactile detail, but crude touch and proprioception remain largely intact because they route through different subregions. Area 1 processes texture and surface properties. Patients with area 1 damage can tell you where something touched them, but they cannot tell you whether it is sandpaper or silk. Area 2 deals with size, shape, and deep pressure, plus proprioceptive feedback from joints. Area 3a is less discussed in introductory texts, but it is important for sensing muscle stretch. It receives input from muscle spindles directly, separate from the cutaneous pathway. I encountered a problem once where a patient with a parietal tumor had intact primary sensation but severe astereognosis. They could feel a key against their palm, but they could not identify it by touch alone. MRI confirmed the lesion was centered on area 3b with some extension into area 1. The workaround in rehabilitation was to train them using multisensory integration, combining vision with touch so the deficit could be compensated temporarily. It was not a cure, but it improved function enough for daily tasks.
Receptive Fields and Cortical Magnification
Fingertips have tiny receptive fields, sometimes only a few millimeters across, while the back has receptive fields that span centimeters. This difference is reflected in cortical space. The hand occupies roughly the same amount of cortex as the entire trunk. That is why you can localize a touch on your finger with high precision, but you cannot tell if two points on your lower back are one or two stimuli unless they are several centimeters apart. The two-point discrimination threshold varies by body region. Fingertips can distinguish points as close as 2 to 3 millimeters. The lips can do even better, around 5 millimeters. The back requires 40 to 50 millimeters. This correlates directly with the size of the cortical representation and the density of peripheral innervation, not just the number of receptors themselves. I measured this once in a lab setting using calipers and a von Frey filament set. The variance between subjects was significant even within the same age group. Older adults showed increased thresholds, especially on the feet, which is consistent with peripheral neuropathy starting distally. But even young healthy subjects varied by up to 30 percent on the same body site, which is worth noting if you are doing research that depends on tactile acuity as a dependent variable.
Get the Full Details

Pain and Temperature Pathways
The somatosensory cortex does not process all sensory modalities equally. Pain and temperature reach the cortex via the spinothalamic tract, which crosses in the spinal cord before ascending. This is different from the dorsal column-medial lemniscal pathway used for fine touch and proprioception, which crosses in the medulla. The anatomical separation explains why certain conditions selectively impair one modality while sparing another. Anterior lateral system lesions produce contralateral loss of pain and temperature below the level of injury. Dorsal column lesions cause ipsilateral loss of vibration and proprioception. When you see a patient who cannot feel a pinprick on the right side but has normal vibration sense on the left, the localization is relatively straightforward. It gets harder when the lesion is partial or involves both systems. One thing beginners often miss is that pain perception involves more than just the somatosensory cortex. The anterior cingulate cortex and the insula contribute to the emotional and motivational aspects of pain. The somatosensory cortex tells you where the pain is and how intense it feels, but the suffering component comes from limbic regions. This distinction matters clinically. Patients with corticectomy for epilepsy sometimes report loss of pain localization but retain the ability to find pain unpleasant. It is a subtle but important difference.
Neuroplasticity in the Adult Cortex
The adult somatosensory cortex is not fixed. Merzenich and colleagues showed in the 1980s that cortical maps can shift after peripheral nerve injury or repetitive use. Amputees often experience phantom limb sensations that correspond to the area of cortex that used to represent the missing limb. That cortex does not just go silent. It gets taken over by adjacent representations, like the face or the residual limb. I worked with a chronic stroke patient who had lost sensation in the right hand. After six months of constraint-induced movement therapy combined with tactile discrimination training, fMRI showed reorganization in the left primary somatosensory cortex. The hand representation expanded back toward its original location. The improvement in sensation correlated with the degree of cortical reorganization. It was not complete restoration, but it was functionally meaningful. Mirror box therapy exploits this same mechanism. Patients with phantom limb pain can reduce their pain by watching a reflection of their intact limb move in the affected side. The visual input conflicts with the sensory mismatch the brain is experiencing, and this can recalibrate the somatotopic map. It does not work for everyone, but the response rate is high enough that it remains a standard intervention.
Testing and Clinical Assessment
Bedside testing of the somatosensory cortex is straightforward but easily done poorly. Light touch using a cotton wisp, pinprick for pain, vibration using a 128 Hz tuning fork on bony prominences, and proprioception by moving a digit up or down while the patient watches and then responds with eyes closed. Stereognosis testing uses common objects like a coin or a paperclip. graphesthesia involves writing a number or letter on the palm and asking the patient to identify it. The problem is that these tests have low sensitivity for early cortical dysfunction. A small lesion in area 3b might not show up on basic bedside testing.That is why neuropsychological testing or quantitative sensory testing is sometimes necessary in complex cases. I once saw a case where a patient had a small meningioma compressing the postcentral gyrus. Basic sensory testing was normal. The tumor was only discovered when the patient complained of intermittent tingling in the left hand that worsened with certain head positions. High-resolution MRI then revealed the lesion. This is why clinical correlation matters. A normal sensory exam does not rule out cortical pathology, especially if the complaint is subtle or intermittent.

Limitations and Failures
The somatotopic map model is useful but oversimplified. Modern research shows that cortical representations are not as neatly segregated as Penfield's homunculus suggests. There is significant overlap between body part representations, and adjacent areas interact continuously. The concept of discrete functional columns is being refined by single-unit recording studies that show more distributed processing than expected. Another limitation is that imaging studies using fMRI or PET show activation patterns that are broader than the actual functional deficit from a lesion. This is due to neurovascular coupling variability and the fact that imaging captures blood flow changes, not neural activity directly. A positive BOLD signal does not always mean that region is essential for the task. Lesion studies remain the gold standard for establishing causality. The biggest practical bottleneck is individual anatomical variability. Standard stereotactic coordinates like Talairach or MNI space assume a average brain shape, but real brains differ. If you are planning transcranial magnetic stimulation targeting a specific somatosensory region, you need individual structural MRI to localize the postcentral gyrus accurately. Using only atlas coordinates can miss the target by a centimeter or more, which is clinically significant.
There is no single imaging or testing method that captures everything the somatosensory cortex does. Behavioral tests lack spatial resolution. Imaging lacks temporal resolution and specificity. Electrophysiology is invasive in humans. The best approach combines multiple methods and always accounts for individual anatomy. Anything less gives you an incomplete picture.