
What The Dorsal Spine Actually Is
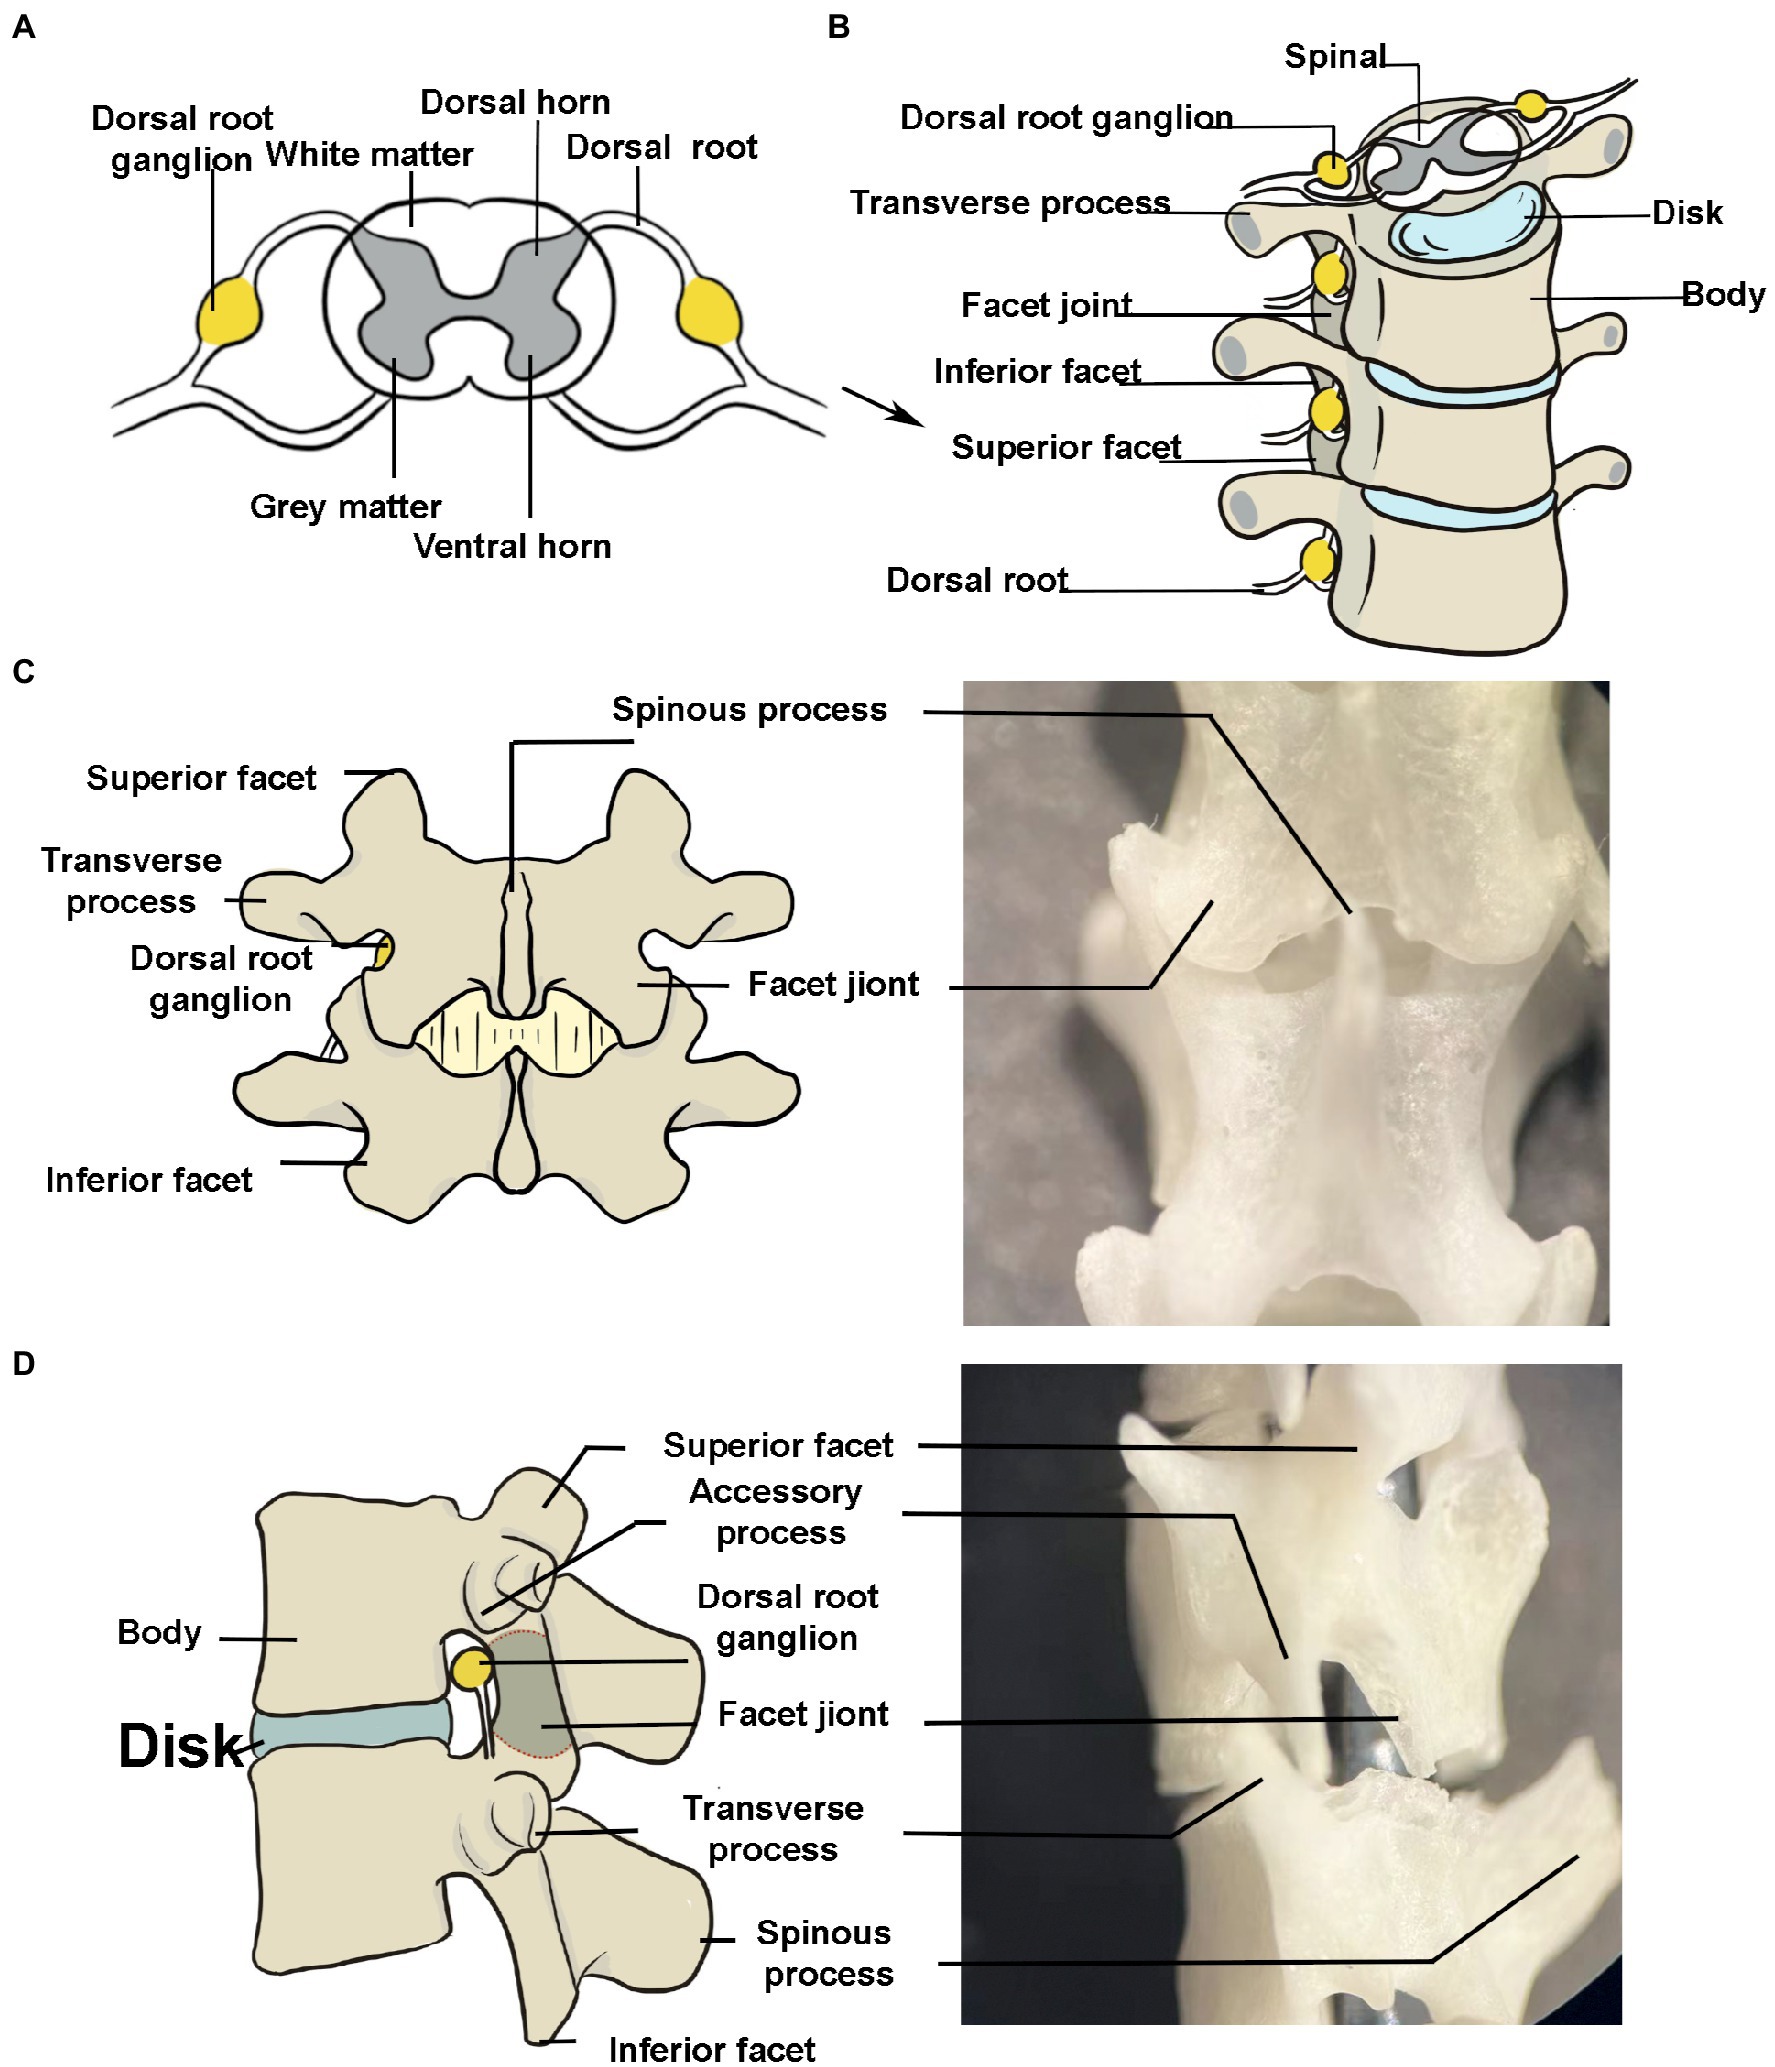
The dorsal spine refers to the thoracic region of the vertebral column. It spans from T1 through T12, sits between the cervical spine above and the lumbar spine below, and is the only section where the vertebrae articulate with the rib cage. That makes it structurally different from every other spinal segment. People search for The Mysterious World Of Dorsal Medical Definition Unlocking The Secrets Of The Dorsal Spine because medical textbooks often treat the thoracic spine as an afterthought compared to the cervical and lumbar regions, but it carries real clinical weight. The thoracic vertebrae have a few features you need to actually know if you are reading imaging or working a patient. Each body is heart-shaped and wider transverse than mediolaterally. The costal facets on the lateral surfaces articulate with rib heads. The transverse processes have small facets at their tips for the tubercles of the ribs in the lower thoracic levels. The spinous processes are long and angle sharply downward, which matters when you are doing a midline approach for a thoracic epidural or a needle biopsy. At T9 and above, the spinous processes sit at roughly the same horizontal level as their corresponding vertebral body. Below T9, they sit progressively lower. That anatomical relationship is why counting spinous processes by palpation gets unreliable past the mid-thoracic region. I spent a lot of time learning this the hard way during spine surgery fellowships. You think you are at T10 because the palpable process looks like it should be T10, but the actual vertebral body is three levels lower. I learned to confirm with intraoperative fluoro instead of trusting my fingers every time.
Why The Dorsal Spine Is Clinically Important
The thoracic spine has the smallest spinal canal relative to the size of the cord among all regions. A 6mm disc herniation in C5 might cause minor radiculopathy. The same 6mm herniation at T8 can cause complete myelopathy because there is almost no reserve space. That disproportion is the single most important concept to understand about this region. The blood supply is another area where people get tripped up. The thoracic cord relies heavily on the artery of Adamkiewicz, which arises from a left-sided radicular artery in about 75 percent of people, usually between T8 and L2. When you are planning a thoracic procedure or an aortic repair, knowing where this artery is likely to be matters more than anything else. I once saw a case where a surgeon did not check preoperative MRA and the patient ended up with a paraplegic deficit because the feeding vessel was sacrificed. The lesson was straightforward: always map the radicular anatomy before cutting.
Common Pathologies and What They Actually Look Like
Thoracic disc herniations are rare, accounting for roughly 1 percent of all disc herniations. When they do occur, they are almost always posterolateral and calcified. The calcification makes them rigid and harder to resorb spontaneously, which is why surgical intervention rates are higher here than in the lumbar spine despite lower incidence. Thoracic outlet syndrome involves structures passing between the anterior and middle scalene muscles, near the first rib. It is not a dorsal spine problem per se, but the cervicothoracic junction is often pulled into the differential. I see this confusion constantly in clinics. The actual dorsal root compression from a T4-T5 disc herniation presents with a band-like thoracic radiculopathy that wraps around the chest wall. Patients describe it as a tight girdle sensation. It gets misdiagnosed as cardiac pain, gallbladder disease, or peptic ulcer symptoms far more often than you would expect. Scoliosis in the thoracic region is another common finding. Degenerative thoracic scoliosis in older adults tends to shift the coronal balance forward and creates a double curve pattern. The main thoracic curve is usually convex to the left, which is the opposite of idiopathic thoracic scoliosis in adolescents. That difference matters when you are writing operative plans and explaining prognosis to patients.
Get the Full Details

Imaging Nuances That Matter
X-rays of the thoracic spine are notoriously difficult to interpret because the ribs overlay the vertebral bodies and the lung fields create low contrast. AP views show rib shadows obscuring the disc spaces. Lateral views are better but require proper positioning to avoid rotation artifacts. I usually recommend CT myelography when MRI is contraindicated and you need to see bony detail alongside nerve root compression. The myelogram fills the subarachnoid space and the CT cuts through the bone, giving you information neither study provides alone. MRI signal characteristics in the thoracic cord differ from the lumbar cord. The normal thoracic cord has less cerebrospinal fluid around it, so motion artifacts from breathing and CSF pulsation are more pronounced. I always scan with respiratory triggering or at least hold instructions, and I repeat sequences if the first pass is blurred. A rushed thoracic MRI misses more lesions than any other region simply because the images are degraded by movement.
Procedural Considerations
Thoracic epidurals are technically demanding. The ligamentum flavum is thickest in the thoracic region, sometimes 4 to 5mm, compared to 2 to 3mm lumbar. The loss of resistance technique requires more force and you can easily overshoot into the epidural space or puncture the dura if you are not paying attention. I use a 25G pencil-point needle and advance in 1mm increments once I am within 5mm of expected ligament depth. It adds time but prevents dural taps that lead to post-dural puncture headaches. Vertebroplasty and kyphoplasty in the thoracic spine carry a higher risk of cement leakage into the spinal canal because the posterior vertebral cortex is thinner and the epidural space is narrower. I limit injection pressure to below 15 PSI and use low viscosity cement mixed with barium at a 2:1 powder to liquid ratio. This gives you enough working time without the cement flowing too fast into unwanted spaces.
Limitations of Conservative Management
Not everything in the dorsal spine responds to physical therapy or epidural injections. Spinal stenosis from degenerative changes in the thoracic region rarely improves with conservative care because the canal is already tight. A facet joint arthropathy that causes 3mm of ligamentum flavum hypertrophy in the lumbar spine might be tolerable. The same amount of hypertrophy in the thoracic spine can reduce the canal diameter by a third. I do not hesitate to refer thoracic myelopathy cases early for surgical decompression. Waiting six months for conservative treatment to work in a thoracic cord compression case is a mistake I have seen repeated too many times. If you are dealing with an acute thoracic fracture from osteoporosis, bracing with a TLSO can help with pain but does not reverse the vertebral collapse. Kyphoplasty offers better short-term pain relief than analgesics alone, but the long-term functional outcomes are similar. The data supports pain reduction, not structural restoration. Be honest with patients about what the procedure can and cannot do.
Practical Takeaways
The thoracic spine is not mysterious. It is just underappreciated in most general training programs. The key facts are the small canal diameter, the variable location of the artery of Adamkiewicz, the downward angulation of spinous processes, and the tendency for pathology here to present with dramatic neurological deficits despite small structural changes. If you remember those four points and verify your level localization with imaging before every intervention, you will avoid most of the common errors. The rest is anatomy and attention to detail.


