Where It Actually Sits
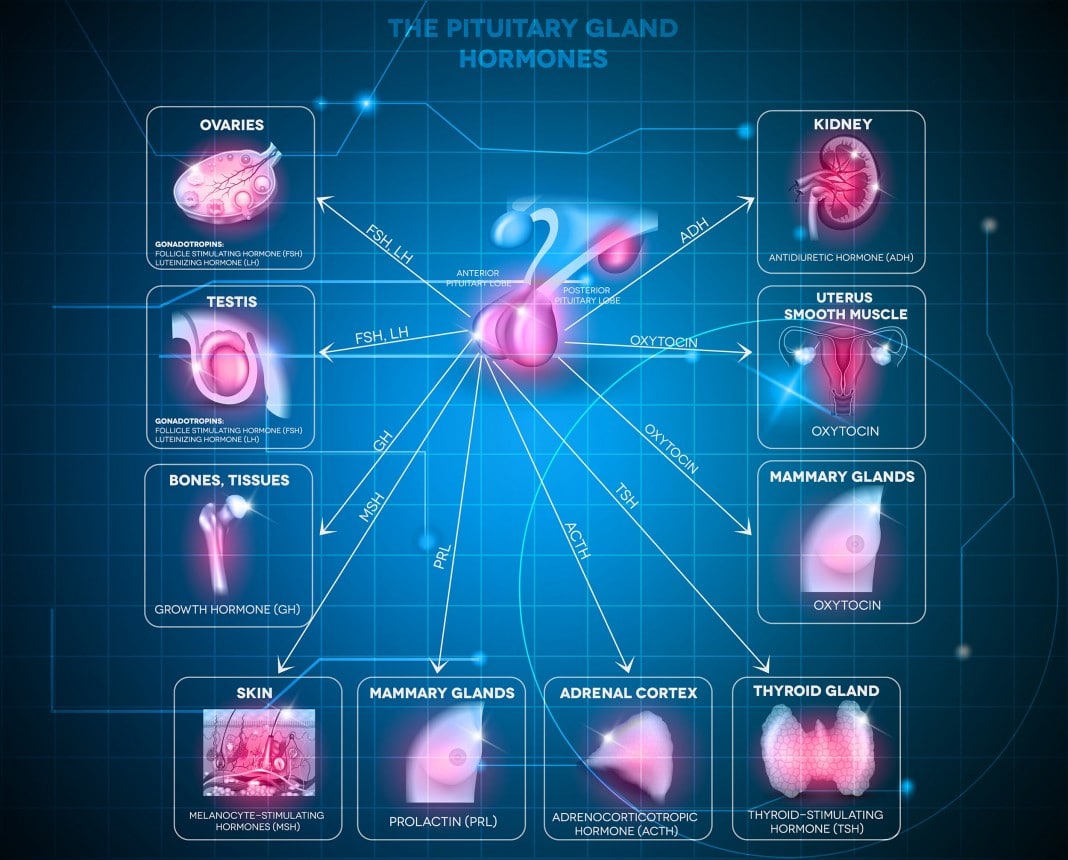
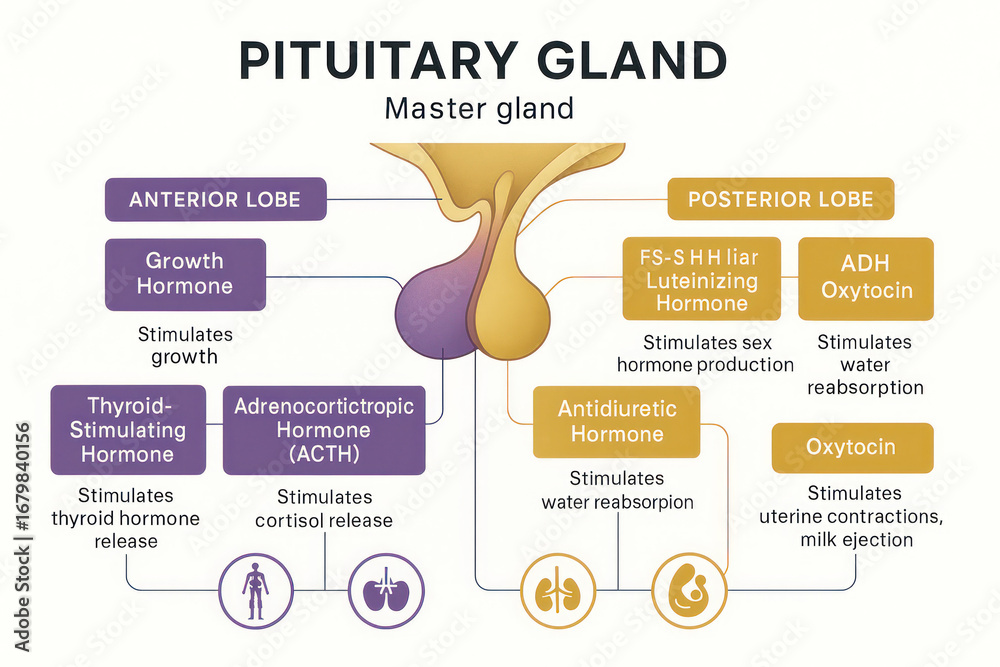
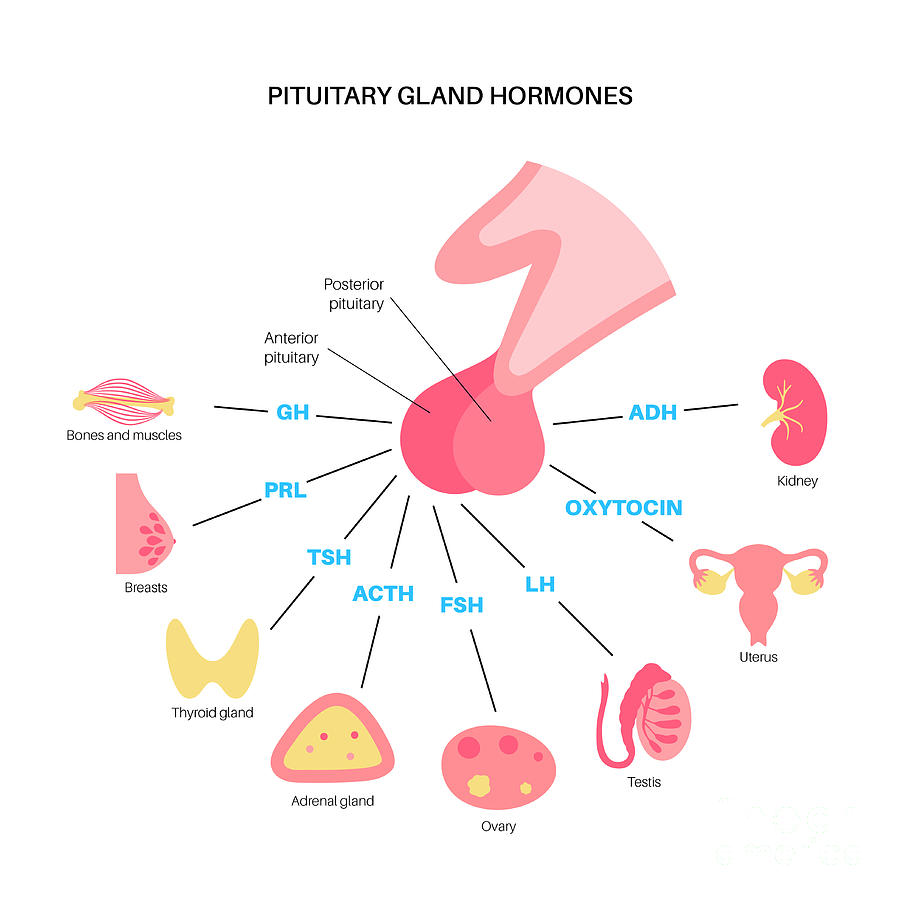
The pituitary gland is about the size of a pea. It rests in a shallow depression of the sphenoid bone called the sella turcica, just behind the bridge of the nose and directly below the hypothalamus. It connects via a stalk, the infundibulum, which carries both neural fibers and blood vessels. That stalk matters more than most people realize. It is the reason treatment for pituitary issues often splits into two completely different camps: surgery through the nose versus medication. You do not get one simple answer here. The nickname makes it sound like a command center, but calling it the master gland is only half true and sometimes the wrong half. The hypothalamus is actually running the show. The pituitary is more like a relay station with its own opinions. Anterior pituitary cells respond to releasing and inhibiting hormones arriving through the hypophyseal portal system. Posterior pituitary tissue is basically modified neural tissue storing oxytocin and vasopressin made upstream in the hypothalamus. So when you see elevated prolactin or altered cortisol patterns, you often trace the problem back to the hypothalamus or to feedback loops that have gone offline, not to the gland itself. The anterior lobe produces six standard hormones, though naming them changes depending on which textbook you open. ACTH drives cortisol from the adrenals. TSH pushes the thyroid. FSH and LH control gonadal function. Prolactin handles lactation. Growth hormone manages somatic growth and metabolism. The posterior lobe stores and releases oxytocin and antidiuretic hormone, also called vasopressin. None of these operate in isolation. They form tight feedback chains, and breaking one link throws off everything downstream.
Most pituitary tumors are adenomas. They are usually benign, slow growing, and discovered incidentally on MRI scans ordered for something else entirely. I have seen patients flagged by headache, visual field cuts, or menstrual irregularity. But many present with nothing obvious until a random lab draw shows something odd, or a clinician notices a subtle pattern in basic metabolic panels. The trouble is that symptoms overlap with far more common conditions. Fatigue and weight changes get attributed to stress. Vision issues get blamed on eye strain. Menstrual changes get written off as PCOS without checking prolactin. Mass effect is the straightforward mechanical problem. A tumor pressing on the optic chiasm causes bitemporal hemianopsia, a classic visual field defect. Compression of normal pituitary tissue causes hypopituitarism, meaning hormone deficiency rather than excess. Hormone hypersecretion is the other side, and it follows a completely different clinical logic.
Testing That Actually Makes Sense
Blood work is the starting point, but timing and conditions matter more than most labs acknowledge. Prolactin rises with stress, needle sticks, and sleep. If you order a prolactin level at 8 AM after someone has been running around all morning, you may chase a phantom elevation. Morning, seated, rested samples reduce noise. For growth hormone, random levels are nearly useless because GH pulses throughout the day. You need stimulation or suppression testing depending on what you suspect. IGT with oral glucose is the standard suppression test for acromegaly. Failure to suppress GH below a certain threshold after a glucose load confirms the diagnosis more reliably than any single random draw. MRI with contrast is the imaging standard. Non-contrast scans miss a lot of microadenomas. A dedicated pituitary protocol with thin cuts through the sella gives you the resolution needed to spot lesions under 10 millimeters. I had a case recently where a patient had classic acromegaly features, elevated IGF-1, and non-suppressible GH, yet the initial MRI reported normal. We repeated the scan with a pituitary-specific protocol and a 3T machine, and a 4-millimeter microadenema appeared. The first radiologist had used a standard brain MRI sequence optimized for stroke detection, not for tiny sellar lesions. This is not rare. It happens because pituitary imaging requires a different setup entirely.
Get the Full Details

Treatment Realities
Surgery is transsphenoidal in the vast majority of cases. The surgeon goes through the nasal cavity, not through the skull. Recovery is surprisingly quick for something that sounds brutal. Most patients are home within a couple of days. The real risks are CSF leak, diabetes insipidus, and permanent hormone deficiency. CSF leaks happen in a meaningful percentage of cases, and they usually require repair before discharge or within the first week. Diabetes insipidus is transient in many patients but becomes permanent in a small subset. Hormone replacement may be lifelong after resection if significant normal tissue was removed. Medication works well for prolactinomas. Cabergoline and bromocriptine shrink tumors and normalize prolactin in the majority of patients. Many of these patients never need surgery. For non-functioning adenomas, surgery is usually the only option, though observation with serial imaging is reasonable for very small asymptomatic lesions. Cushing disease and acromegaly sit in a gray zone. Surgery is first line, but medical therapy with somatostatin analogs, GnRH analogs, or targeted receptor blockers can be bridging treatment or definitive management in patients who are not surgical candidates.
The One Thing Nobody Tells You
Pituitary disorders rarely resolve completely. Even after successful tumor removal, patients need lifelong endocrine follow-up. Adrenal insufficiency can develop months or years later. Hypothyroidism emerges gradually. Gonadal function may not recover. I once managed a patient who was told she was cured after a clean post-op MRI and normal hormone levels on day three. Two years later she presented with severe fatigue, hyponatremia, and an adrenal crisis triggered by a minor infection. She had developed secondary adrenal insufficiency from subtle damage to the corticotroph cells that was not apparent immediately after surgery. The lesson is that normal labs in the acute postoperative period do not equal permanent cure. You need follow-up at six months, twelve months, and then annually, covering at minimum cortisol, thyroid, prolactin, IGF-1, and gonadal axes. Pregnancy also changes the calculus. Prolactinomas can enlarge significantly during gestation because estrogen drives lactotroph hyperplasia. Monitoring visual fields and symptoms is critical, and cabergoline is generally continued through pregnancy in treated patients, though the data on long-term offspring outcomes remains limited. Brachytherapy and external beam radiation are rarely used now but carry a high risk of hypopituitarism over time, often developing within five to ten years after treatment. If radiation is part of your plan, factor in the long-term hormone monitoring burden.
Bottom Line
The pituitary is not a simple on-off switch. It is a hub embedded in complex feedback networks, sitting behind structures that make surgical access tricky and hormonal assessment deceptively difficult. Imaging protocols matter. Lab timing matters. Follow-up matters more than initial treatment success. A single abnormal test is not a diagnosis. A single normal MRI is not a guarantee. You need a systematic approach, and you need patience because the endocrine system does not rush to reveal its problems.