Understanding Pamidronate Dosing in Pediatric Oncology
Pamidronate is a bisphosphonate used to treat bone metastases in children with cancers like osteosarcoma or neuroblastoma. The dosing is calculated based on body surface area, typically 60 mg per square meter of body surface area per cycle, given as an intravenous infusion over several hours. Children receive these infusions on a schedule that varies depending on their clinical status, but most protocols call for monthly cycles. The dosing calculator for pediatric pamidronate exists in a gray area because there is no single FDA-approved pediatric dosing program specifically branded for this medication. What clinicians typically use is either a hospital-developed decision support tool or an off-label calculation spreadsheet. "Pamibaby" appears to be an informal or institutional name for one such dosing reference, but it isn't a widely published or peer-reviewed tool. That's why finding a clean download link online is nearly impossible, and what you'll encounter on various medical resource sites are either outdated spreadsheets, institutional PDFs, or third-party references that may not reflect your hospital's current protocol. Here is how the actual dosing works in practice. You calculate body surface area using the Mosteller formula, which is square root of height in centimeters times weight in kilograms divided by 3600. Once you have the BSA, you multiply by the standard dose of 60 mg per square meter. The result is your total cycle dose. For example, a child who is 95 centimeters tall and weighs 14 kilograms has a BSA of approximately 0.59 square meters, giving a cycle dose of about 35.4 milligrams of pamidronate.
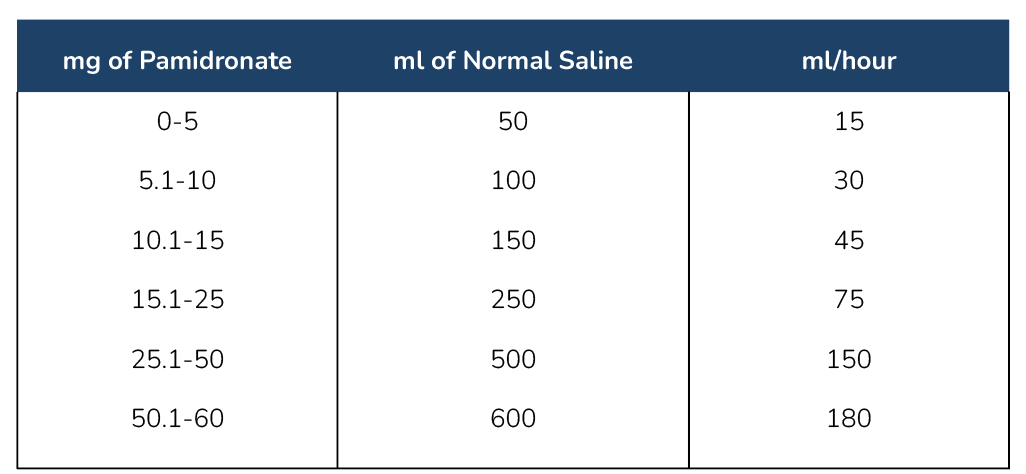
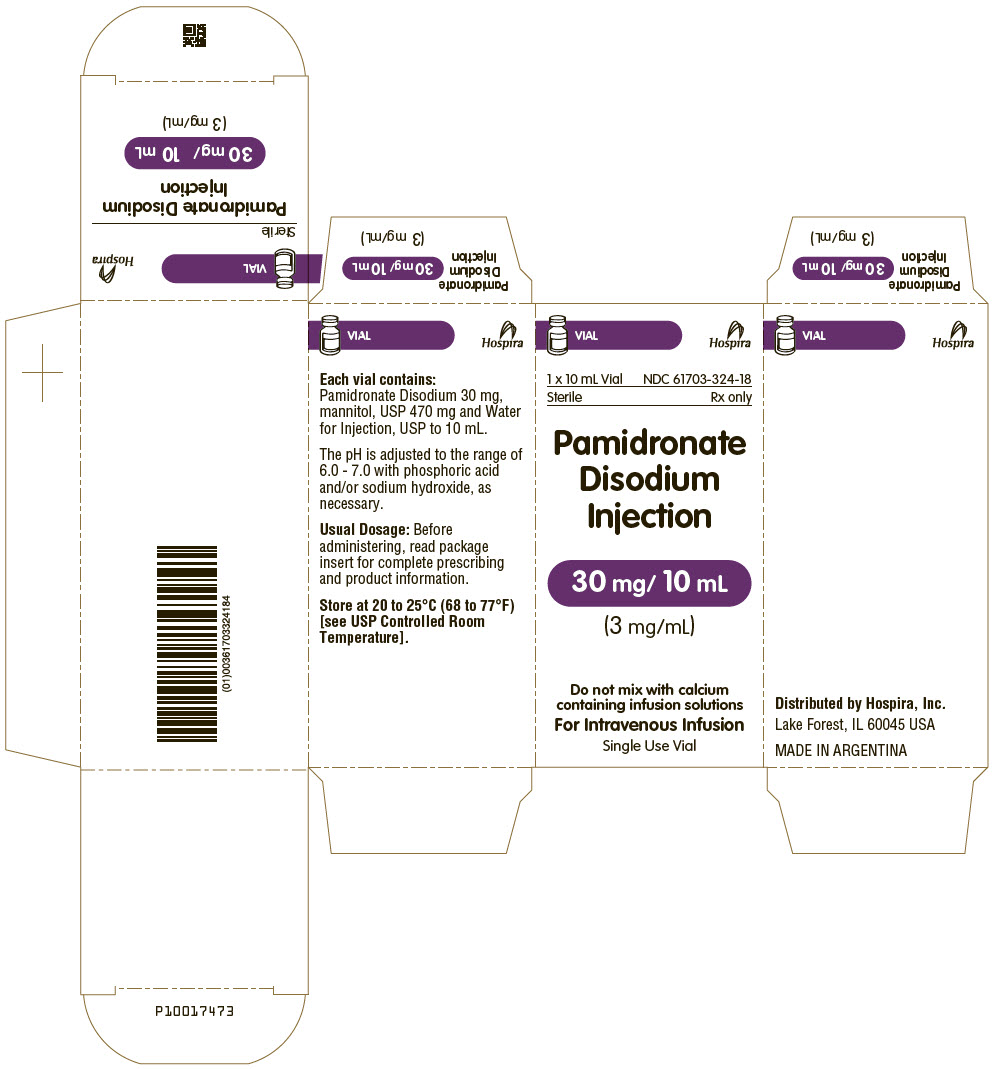
The important nuance most people miss is that the actual prepared infusion volume and concentration depend on the pharmacy compounding the drug. Pamidronate comes as a 30-milligram vial that must be diluted in normal saline or dextrose solution. The infusion rate matters significantly in pediatrics because rapid administration increases the risk of acute phase reactions and hypocalcemia. The standard recommendation is to infuse over at least two to four hours for pediatric patients, sometimes longer depending on the child's hydration status and renal function. I ran into a specific problem last year where a facility was using a cached dosing calculator that had a hardcoded maximum dose cap of 90 milligrams per cycle. A teenager with osteosarcoma who weighed enough to exceed that cap was being underdosed by roughly 15 milligrams per cycle because the tool wouldn't allow the calculated dose to pass through. I had to manually override the safety limit after verifying the BSA calculation and confirming with pharmacy that the higher dose was appropriate for that patient's renal function and hydration status. This happened because the original developer of that tool had built in a ceiling based on adult osteoporosis protocols rather than the oncology pediatric standard, and nobody had updated it in three years. Another counter-intuitive point: pamidronate dosing in children with bone metastases does not follow a simple linear relationship with age or weight alone. Two children with the same weight but different heights will have different BSAs and therefore different doses. More importantly, renal function must be assessed before each cycle. Creatinine clearance calculated using the Schwartz formula for pediatrics should be checked, and doses may need to be held or reduced if clearance falls below certain thresholds. I have seen cases where a child's creatinine cleared up between cycles, allowing a dose to proceed that would otherwise have been delayed, and other cases where dehydration from poor oral intake dropped the clearance enough to warrant a 25 percent dose reduction for that cycle only.
If you are looking for a downloadable dosing reference, your best path is to check your institution's formulary or pharmacy department. Most children's hospitals have an internal clinical decision support module embedded in the electronic health record that handles this automatically. Some institutions share resources through collaborative networks, so if your hospital does not have a dedicated tool, reaching out to a peer children's hospital pharmacy department is a practical way to obtain a working spreadsheet or calculator. External references like the Lexicomp or Micromedex pediatric dosing modules also contain the calculations, though they require an institutional subscription. The real limitation here is that pamidronate in pediatric bone metastasis is always an off-label use. No manufacturer-specific pediatric dosing tool exists for this indication, and any calculator you find online is essentially a user-created approximation. The clinical evidence supporting the 60 mg per square meter dosing comes from retrospective studies and small prospective trials, not a large randomized controlled pediatric trial. This means the dosing range has some flexibility, and institutional protocols vary. Some centers use 45 milligrams per square meter for younger or smaller children, while others stick strictly to the 60 milligram standard across all weights. Neither approach is universally right or wrong, but consistency within your institution matters more than chasing an ideal number. Monitoring during treatment includes checking serum calcium, phosphorus, magnesium, and creatinine before each cycle. Hypocalcemia is the most common adverse metabolic event, and prophylactic calcium and vitamin D supplementation is standard practice in most pediatric oncology protocols. I have also seen bone mineral density scans used to track response over time, though the utility of DEXA in very young children remains somewhat debated in the literature.
Get the Full Details