What We Actually Know About K102
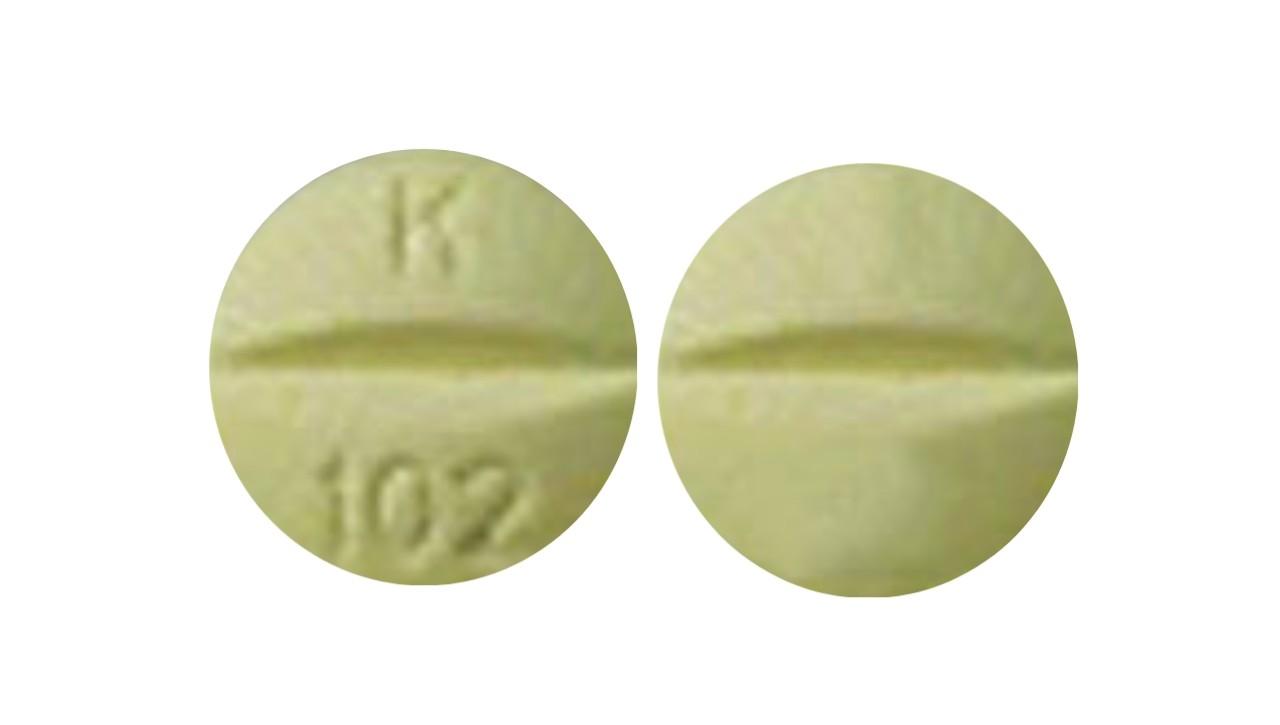
The K102 yellow pill, also called flubromazolam, is a synthetic benzodiazepine built around a modified brominated triazole ring. It landed on underground pharmacy lists somewhere around 2017 and caused a noticeable spike in overdose reports because its potency curve is nowhere near flat. People who work with clinical toxicology or emergency pharmacology usually learn about this compound through case files rather than drug education materials, because standard immunoassay screens don't flag it. The molecular structure gives flubromazolam a very high binding affinity for the GABA-A receptor complex. That translates to roughly ten times the potency of alprazolam by weight. Most standard benzos have a therapeutic window wide enough that accidental dosing mistakes are survivable. With flubromazolam the margin shrinks dramatically. A dose measured incorrectly by just a couple of milligrams can push someone into respiratory depression, especially when other CNS depressants are present. The pill itself is unremarkable on the surface. Yellow, round, imprinted K102 on one side, nothing on the other. What makes it problematic is that the manufacturing origin varies between batches, and there is no regulated pharmaceutical version with consistent dosing. A single pill might contain anywhere from 0.2 mg to over 1 mg of active compound depending on who pressed it and how the powder was distributed through the pellet. That variance alone is enough to turn a supposedly standard dose into something unpredictable.
I have seen lab results where two pills taken from the same batch showed a 3x difference in active concentration between them. The variation was not measurement error. It was uneven mixing during manufacture. Once you understand that mechanical reality, the whole concept of taking a known dose of K102 becomes almost absurd.
How Testing Actually Works In Practice
Standard urine drug panels will come back negative for flubromazolam. The compounds in those tests target common metabolites like oxazepam, temazepam, and nordiazepam. Flubromazolam metabolizes into entirely different byproducts that the antibodies simply do not recognize. If you need confirmation, you have to request GC-MS or LC-MS/MS specifically. That is not always cheap, and not every hospital laboratory runs that panel unless requested. Reagent testing on powdered forms is possible, but the yellow coloring of the pill itself interferes with colorimetric tests. You would need to extract and dissolve a sample first, which introduces its own accuracy problems if you are not doing it carefully. I learned that the hard way watching a colleague ruin several test runs because the pigment carried over and skewed the Marquis and Mecke reactions into false positives that looked like other benzos.
Get the Full Details

What Makes This Compound Different From Other Novel Benzodiazepines
Flubromazolam has an unusually long half-life for its class. Estimates range between 30 and 50 hours, sometimes longer depending on individual metabolism. That means it accumulates with repeated use. The sedative effects do not simply wear off after a day. People often report next-day cognitive impairment that they attribute to poor sleep rather than residual drug effect. Another detail most people miss is the context of co-ingestion. A significant number of reported adverse events involve combined use with opioids or alcohol. The pharmacodynamic interaction here is multiplicative, not additive. The respiratory depression risk jumps substantially because both substances depress the brainstem drive through overlapping mechanisms. Fentanyl exposure complicates identification even further because standard test strips detect fentanyl analogs now, but flubromazolam will not show up on those strips at all.
Why Medical Literature Stays Surprisingly Thin
There is almost no peer-reviewed clinical research on flubromazolam in humans. What exists comes from toxicology case reports, forensic pathology journals, and a handful of animal studies that mostly document receptor binding characteristics. That gap exists because the compound was never developed as an approved medication. It entered circulation through unregulated channels, and regulatory bodies responded by scheduling it rather than funding studies. In the United States, flubromazolam ended up classified as a Schedule I controlled substance under the Federal Analogue Act enforcement actions. Several individual states also listed it explicitly. That legal status makes it difficult for clinicians to encounter it openly, and researchers face institutional hurdles when publishing data that could be construed as promoting use.
What Actually Happens When Someone Overdoses
The clinical presentation follows a benzo overdose pattern but intensified. Severe sedation, slurred speech, ataxia, and progressively depressed respiration. The dangerous part is that reversal agents exist. Flumazenil can reverse benzodiazepine effects, but using it with flubromazolam carries a specific risk of precipitating seizures, especially in someone who has been using the compound regularly. That seizure threshold drop is a well-documented concern with all benzodiazepines, but it becomes more relevant when the compound is this potent and the dosing history is unknown. Supportive care remains the primary treatment pathway in most emergency departments. Airway management, monitoring, and time. Flumazenil is reserved for situations where the benefits clearly outweigh the seizure risk, and the patient profile has to be evaluated individually.

How This Compares To Other Emerging Synthetic Benzos
Brivazolam and flualprazolam sit in the same general potency space, but flubromazolam tends to produce stronger dissociative and sedative effects at lower milligram doses. Etizolam, another common substitute, is weaker and shorter-acting, which makes it feel different even though the receptor target is identical. The community sometimes confuses these compounds because they all belong to the thienodiazepine or triazolobenzodiazepine families. They are not interchangeable dosing-wise, and assuming they are leads directly to dosing errors. If you are encountering this compound in any context, the practical reality is that you cannot reliably verify purity or dose without laboratory equipment. Urine screens will not help you. Reagent strips are inconsistent with colored tablets. Blood tests exist but only show presence, not accurate concentration without specialized analytical methods. The compound has no approved medical use in most jurisdictions. Any encounter with it falls outside regulated prescribing pathways. That absence of oversight is the core reason the pill looks deceptively ordinary while carrying disproportionate risk compared to pharmaceutical-grade benzodiazepines with established dosing standards.



