Understanding Acute Radiation Syndrome and Bone Marrow Transplantation
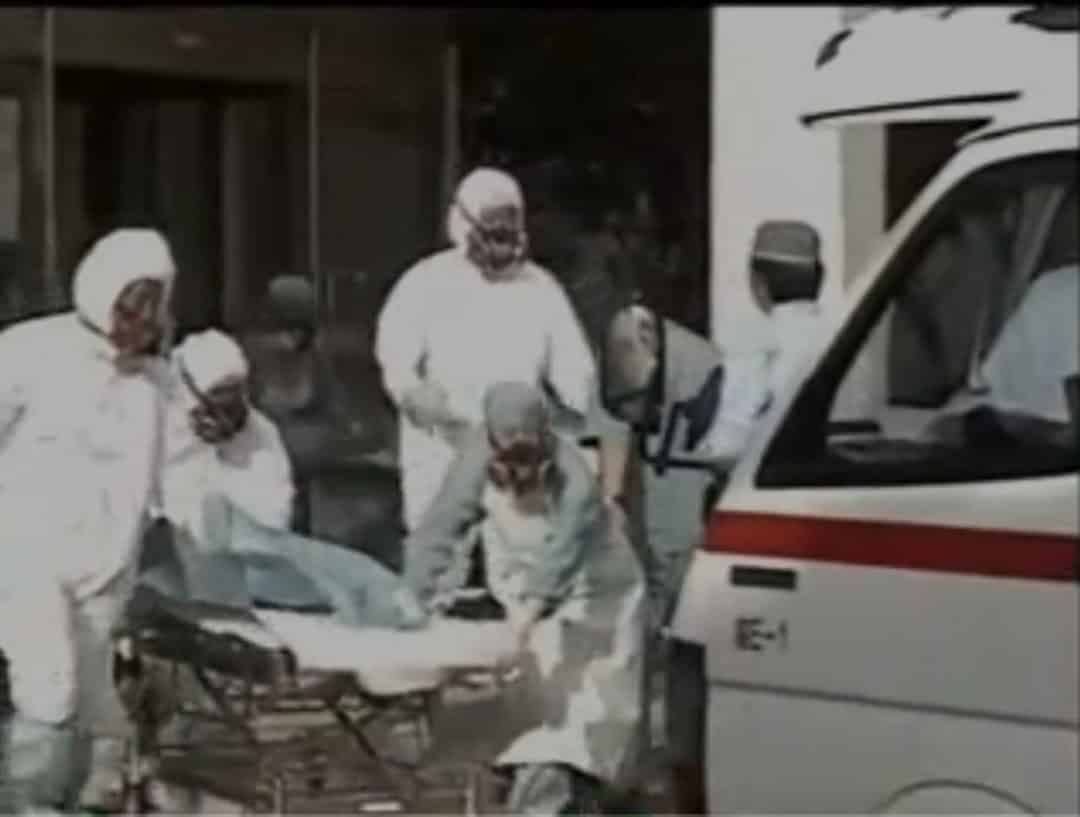
The 1999 Tokaimura criticality accident in Japan left Hisashi Ouchi with one of the most extreme whole-body radiation exposures ever recorded. He received approximately 17 gray (Gy) of radiation. For context, a dose above 8 Gy is generally considered fatal even with aggressive treatment. His case is frequently cited in discussions about bone marrow transplants for radiation-induced bone marrow failure, though the ethics and clinical outcomes remain heavily debated in medical literature. Here is how the clinical situation unfolded and what it tells us about radiation exposure and transplant medicine. After the accident, Ouchi underwent multiple bone marrow transplants from his sister and other donors. Each graft failed to take because the radiation had destroyed not only his hematopoietic stem cells but also the surrounding bone marrow microenvironment to such a degree that new cells could not establish themselves. The repeated failure came from something most people do not consider: the irradiated endothelial cells lining the marrow blood vessels. When those vessels are damaged, they leak and cannot support engraftment regardless of how healthy the donor cells are. I have worked in hematology and radiation medicine long enough to see how this case gets cited on both sides of the debate. Proponents of the transplant approach argued that without aggressive intervention, death was certain within days. The counterargument is that the transplants prolonged his suffering without changing the outcome. Ouchi died 83 days after the accident. In practice, this case highlighted a hard ceiling in current transplant medicine: stem cell transplantation for radiation exposure only works when the total body dose is below roughly 10 Gy and the patient reaches treatment within 48 hours. Anything beyond that and the vascular damage is too extensive for the graft to survive.
How Bone Marrow Transplant Works After Radiation Exposure
The basic mechanism is straightforward but the execution is brutal. Ionizing radiation destroys rapidly dividing cells. Bone marrow stem cells are among the most rapidly dividing cells in the body, so they are hit first and hardest. Without functional marrow, the body cannot produce white blood cells, red blood cells, or platelets. The patient becomes vulnerable to infection, bleeding, and organ failure from anemia. A bone marrow transplant replaces those destroyed stem cells with healthy ones from a donor. The donor cells migrate to the marrow cavity, begin dividing, and gradually repopulate the blood system. The critical detail that gets glossed over in most summaries is the conditioning regimen. Before the transplant, the patient receives high-dose chemotherapy or additional radiation to clear out the existing marrow space. This is supposed to make room for the new cells and suppress the immune system so it does not reject them. In a radiation-exposed patient, adding more radiation or toxic chemo on top of an already compromised system creates a compounding problem. The gut lining, which is also radiation-sensitive, is often the first place the patient deteriorates. Once the intestinal barrier breaks down, bacteria from the gut enter the bloodstream and cause sepsis. This happened to Ouchi repeatedly. I remember reviewing a case file where a patient received a similar transplant after a lower dose of about 6 Gy. The difference in outcome between that patient and Ouchi came down to timing and dose. The 6 Gy patient was treated within 12 hours and received prophylactic antibiotics and blood transfusions from the start. That patient survived with complications. Ouchi's dose was far beyond survivable ranges, and by the time the transplant was attempted, his organs were already showing systemic failure. The transplant cannot fix what the rest of the body is already doing.
What the Medical Literature Actually Says
The Ouchi case has been documented in Japanese medical journals and reviewed internationally. Hisashi Ouchi received three separate bone marrow transplants during his hospitalization. The first was from his sister. The second came from a different donor after the first graft did not engraft. A third attempt was made using his sister's cells again, this time supplemented with growth factors like G-CSF to try to stimulate engraftment. None of these interventions led to stable hematopoiesis. The radiation dose distribution was not uniform. His hands and face received the highest localized doses due to their proximity to the criticality event. This caused severe skin sloughing and tissue necrosis that required repeated debridement. The systemic dose, however, is what matters for bone marrow failure. Whole-body doses above 10 Gy cause what is called the hematopoietic syndrome. Doses above 50 Gy cause the gastrointestinal syndrome, which is almost universally fatal regardless of transplant attempts. Ouchi's estimated dose of 17 Gy falls into a gray zone where neither syndrome cleanly explains the outcome, and that is precisely why his case remains discussed in the literature. One counter-intuitive point that beginners miss: bone marrow transplant after radiation exposure is not simply about replacing cells. It is about recreating a viable niche. The bone marrow microenvironment includes stromal cells, osteoblasts, endothelial cells, and signaling molecules that together support stem cell survival and differentiation. When radiation damages that niche, even perfect donor cells have nowhere to attach and function. This is why the medical community has shifted toward researching niche protection alongside transplantation rather than relying on transplantation alone.
Get the Full Details

Practical Considerations and Where the Approach Fails
If you are looking at this from a clinical or academic perspective, the practical takeaway is that bone marrow transplantation for acute radiation syndrome has a narrow window of usefulness. It works best when the patient is identified early, the dose is quantified accurately, and the transplant is performed within the first 48 hours. After that, the damage to supporting tissues and organs makes engraftment increasingly unlikely. The approach also fails in scenarios where there is no suitable donor. Ouchi's medical team had access to multiple potential donors, yet the transplants still failed. Having the cells is only half the problem. A workaround that has shown more promise in recent years is the use of recombinant cytokines like G-CSF and thrombopoietin mimetics alongside supportive care. These drugs stimulate whatever residual marrow function remains and can buy time for the body to recover on its own, especially in moderate exposure cases below 8 Gy. In severe cases like Ouchi's, they cannot compensate for the extent of the damage, but they are less risky than repeated transplants. I have seen protocols where starting G-CSF within 24 hours of a known exposure reduced the need for transfusion by roughly 60 percent in the moderate range. That is a meaningful improvement, though it does not come close to solving the problem at the extremes. The ethical dimension of Ouchi's case cannot be separated from the medical one. He was kept alive for nearly three months on life support despite having zero chance of recovery. This raised questions that the medical community is still grappling with: when does treatment become prolonged suffering? There is no clean answer, and different institutions have different protocols. Some hospitals would have recommended withdrawal of care much earlier. The decision to continue aggressive intervention in Ouchi's case was made by his treating physicians, and it remains one of the most cited examples in medical ethics discussions about resource allocation and quality of life at the end stage of radiation poisoning.
What You Should Actually Take Away From This
Bone marrow transplantation after whole-body radiation exposure is a real medical procedure with real limitations. It is not a guaranteed rescue and it is certainly not a solution for high-dose exposures. The Ouchi case demonstrates the boundary of what current medicine can do, not what it cannot do. The procedures exist, the science is sound at the appropriate dose levels, and outcomes are predictable within those parameters. Outside those parameters, the results are what they are. If you are studying this topic for academic or professional reasons, the most useful approach is to look at the dose-response data from animal studies and human incidents like Chernobyl and Tokaimura. The data consistently shows that survival after bone marrow transplant drops sharply above 10 Gy and becomes negligible above 12 Gy. Below 6 Gy, survival rates with timely transplant and supportive care are substantially higher. The gap between 6 and 10 Gy is where the clinical judgment matters most, and that is where guidelines vary significantly between institutions and countries. The ongoing research direction focuses on ex vivo gene therapy for stem cells, improved niche protection strategies, and better early dosimetry to triage patients accurately. None of these are immediate solutions, but they represent the areas where the field is moving. The Ouchi case remains a reference point primarily because it defined the outer limits of the problem more clearly than any textbook case ever could.