Simple Cuboidal Epithelium: What It Actually Does and Why It Matters
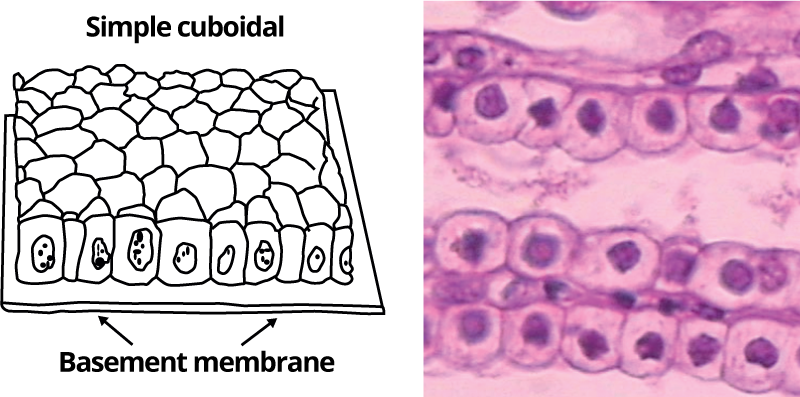
Simple cuboidal epithelium is one of the most common tissue types you'll encounter in any histology or physiology context. It's a single layer of cube-shaped cells, roughly as wide as they are tall. You'll find it lining kidney tubules, the surface of the ovary, the ducts of small glands, and the thyroid follicles. That's the textbook answer. The practical reality is a bit messier. When you're studying transport mechanisms across this tissue, the interesting part isn't just that the cells exist — it's how their geometry and organelle distribution dictate what moves in and out. The apical membrane typically has microvilli in secretory or absorptive variants, which increases surface area for transport. The basolateral membrane often shows infoldings, especially in kidney proximal tubule cells, where you're dealing with massive amounts of ion pumping via Na+/K+ ATPase. Those pumps sit on the basolateral side, not the apical side, and that polarity is non-negotiable for proper function.The Miraculous Simple Cuboidal Epithelium Unlocking The Secrets Of Biological Transport
If you want to understand biological transport through this tissue type, start with the kidney proximal convoluted tubule. It's the textbook example for a reason. Here's what actually happens at the level of the cell membrane, without the simplification most textbooks apply: Sodium enters the cell from the tubular lumen through apical co-transporters — SGLT2 for glucose, various amino acid transporters, and NBCe1 for bicarbonate. These are all secondary active transport processes powered by the sodium gradient. The Na+/K+ ATPase on the basolateral side keeps intracellular sodium low, which drives the whole cascade. Glucose and amino acids then exit across the basolateral membrane via facilitated diffusion through GLUT transporters. That's transepithelial transport in its most straightforward form. But here's where it gets complicated. In my experience teaching this and dealing with lab work, the common pitfall is assuming all simple cuboidal epithelium functions the same way. It doesn't. The thyroid follicular cells and the renal tubule cells both have simple cuboidal morphology, but their transport priorities are completely different. Thyroid cells are focused on iodide uptake via NIS (sodium-iodide symporter) and organification of iodine onto thyroglobulin. Renal tubule cells are focused on reabsorption of water, ions, and nutrients. Same shape, very different job.
I once spent two weeks troubleshooting why an in vitro transport assay on isolated thyroid follicles wasn't showing expected iodide uptake. The issue wasn't the protocol. It was that the follicles had been sitting in culture too long and the cells had dedifferentiated — they started losing their cuboidal shape and adopting a more flattened appearance, which disrupted the polarized expression of NIS. The workaround was straightforward once I figured it out: shorten the culture window to under 48 hours and use Matrigel-coated membranes to maintain polarity. You can't fix dedifferentiated cells. You have to prevent it.
The Mechanisms That Actually Drive Transport
Let me break down the transport mechanisms you need to know, because there are nuances that basic courses skip over. Passive transport across simple cuboidal epithelium happens through paracellular and transcellular routes. The paracellular route goes between cells, through tight junctions. The permeability of those junctions varies significantly by tissue. Kidney proximal tubule tight junctions are relatively "leaky" — they allow significant paracellular movement of water and solutes. That's why about 65% of sodium reabsorption in the proximal tubule is passive and paracellular, driven by solvent drag and electrochemical gradients. Ducts of exocrine glands, on the other hand, have tighter junctions and rely more on transcellular transport. Active transport is where the real work happens. Primary active transport is straightforward — Na+/K+ ATPase, H+ ATPase in certain contexts, Ca2+ ATPase. Secondary active transport is where things get interesting. Symporters and antiporters dominate here. The SGLT family, the Na+/Ca2+ exchanger, the Na+/H+ exchanger (NHE3 in the kidney) — these are all critical for understanding what this tissue does.
Get the Full Details
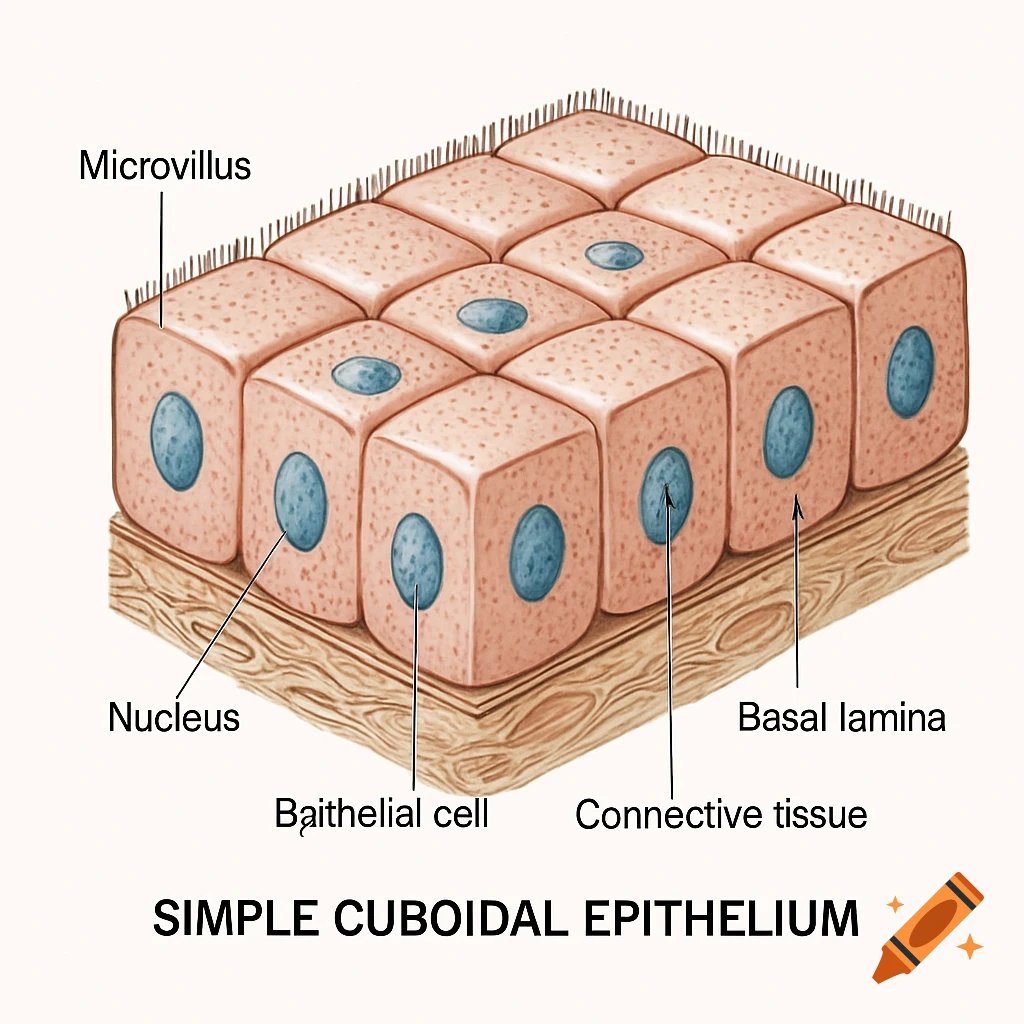
One counter-intuitive point that beginners consistently miss: the thickness of the epithelium isn't the primary determinant of transport rate. It's the number and density of transporters in the membrane. A single layer of cuboidal cells can move massive quantities of substance if the transporter expression is high enough. Proximal tubule cells have an enormous density of Na+/K+ ATPase pumps on their basolateral membranes — up to 10^9 pumps per cell. That's what allows them to reabsorb roughly 180 liters of filtrate per day in a human kidney. The cube shape itself is almost incidental to that capacity.
Practical Considerations When Working With This Tissue
If you're doing experimental work — whether that's histology, electrophysiology, or molecular biology — here are the things that actually matter: Fixation matters more than people realize. For immunohistochemistry targeting membrane transporters, over-fixation with formalin can mask epitopes to the point where your antibody doesn't bind. I've seen people spend days troubleshooting weak staining only to find the antigen retrieval step was insufficient. Citrate buffer at pH 6.0, 10 minutes at high heat, usually does the trick for most transporter antigens. But some, like certain SGLT isoforms, are more finicky. You need to validate your protocol with a known positive control tissue. Isolation of intact simple cuboidal epithelium is harder than it sounds. Enzymatic digestion with collagenase works, but the output is often a mixed population. You'll get some cuboidal cells, but also fragmented cells, cells that have lost polarity, and contaminating stromal elements. If you need pure populations, fluorescence-activated cell sorting using marker-specific antibodies is the way to go. CD10 is a reasonable marker for proximal tubule cells. Not perfect, but workable.
For electrophysiology measurements — short-circuit current experiments, for instance — you need intact epithelial sheets with preserved tight junctions. The Ussing chamber setup is standard, but tissue preparation is critical. Any mechanical damage to the epithelial surface during dissection will introduce noise and artifact. I've found that keeping the tissue in cold PBS with 0.1% BSA during dissection and working quickly (under 20 minutes from excision to mounting) gives the most reliable readings. Temperature also matters. Most transporters have Q10 values around 2-3, meaning their activity roughly doubles with every 10°C increase. Room temperature measurements will underestimate in vivo rates significantly.
Where This Model Breaks Down
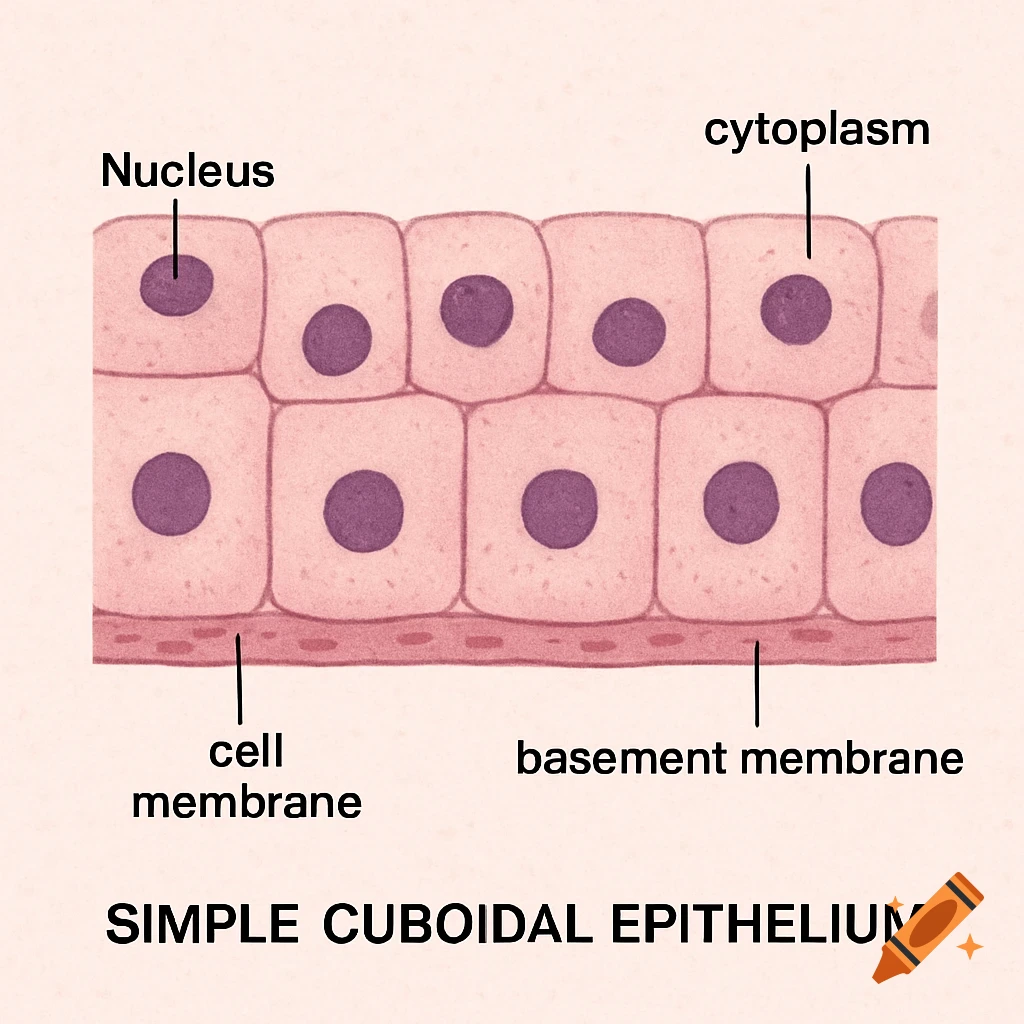
I should be clear about the limitations, because the literature often presents simple cuboidal epithelium as a clean, well-understood system. It's not. First, the cuboidal classification itself is somewhat arbitrary. Many cells classified as simple cuboidal are actually low columnar or vary in shape depending on their functional state. The ovarian surface epithelium, for example, can appear cuboidal when flat but become more columnar when actively secreting. Calling it uniformly "cuboidal" obscures important functional differences. Second, in vitro models rarely replicate the in vivo complexity. Cell lines like LLC-PK1 (derived from porcine proximal tubule) are widely used, but they drift genetically over passages and lose key transport expressions. Primary cell cultures dedifferentiate quickly. Organoid models are improving but still don't fully capture the native architecture or the hemodynamic forces present in living tissue.
Third, species differences are significant. Rat proximal tubule transport differs from human in ways that matter for drug metabolism and toxicity prediction. SGLT2 expression levels, transporter kinetics, and even the dominant isoforms can vary. If you're translating findings from animal models to human physiology, don't assume equivalence without checking the specific parameter you care about. Finally, the biggest blind spot in most research: the role of the glycocalyx. The carbohydrate-rich layer coating the apical surface of these cells is increasingly recognized as functionally important for transport — it creates a diffusion barrier, traps enzymes, and mediates cell signaling. Most transport studies ignore it entirely. If you're measuring apical transporter activity in vitro without accounting for glycocalyx integrity, your results may not reflect physiological reality. The take-home is that simple cuboidal epithelium is a useful model for understanding biological transport, but it's a simplified model. The cells are more dynamic, more variable, and more complex than the name suggests. Treat it that way and you'll get better data.