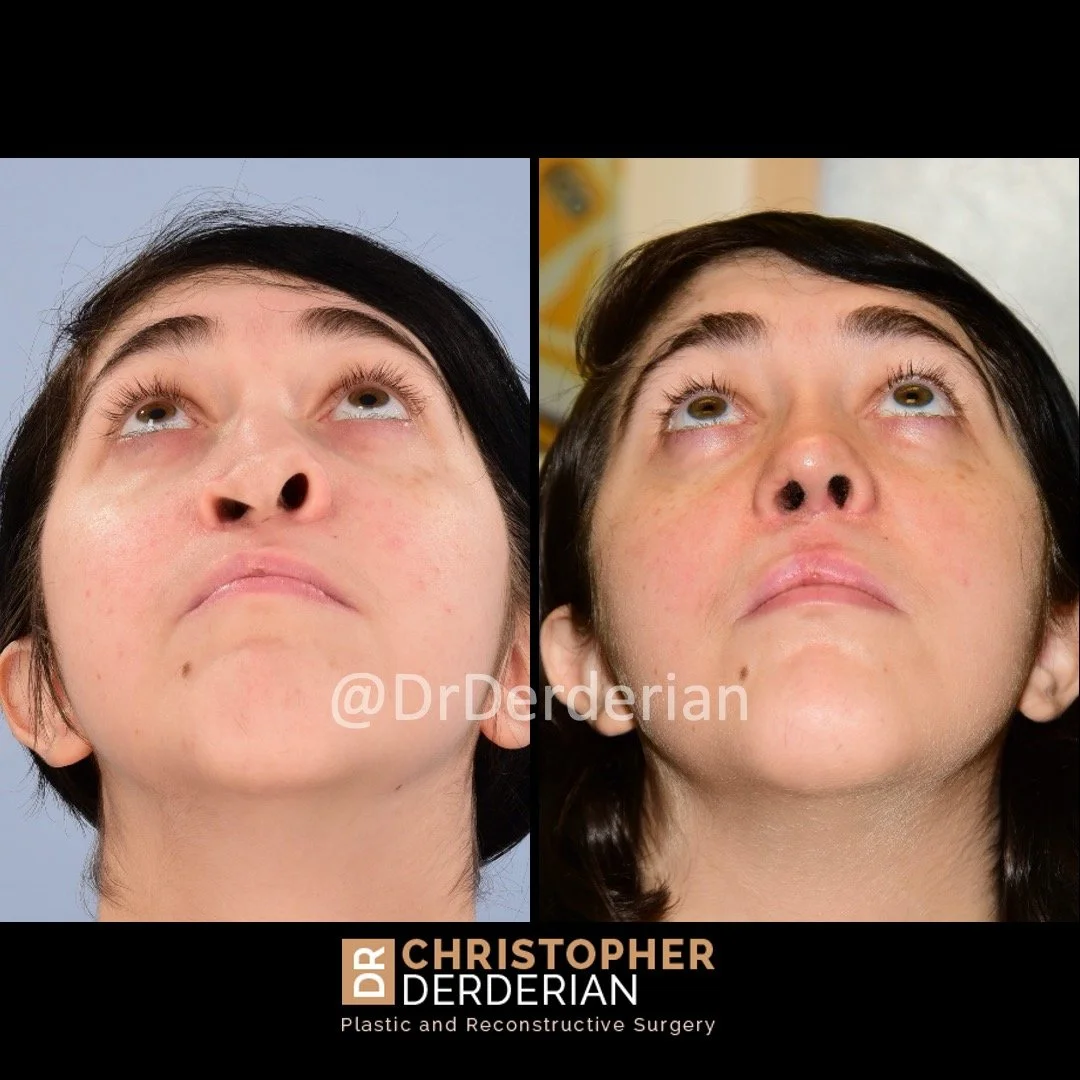
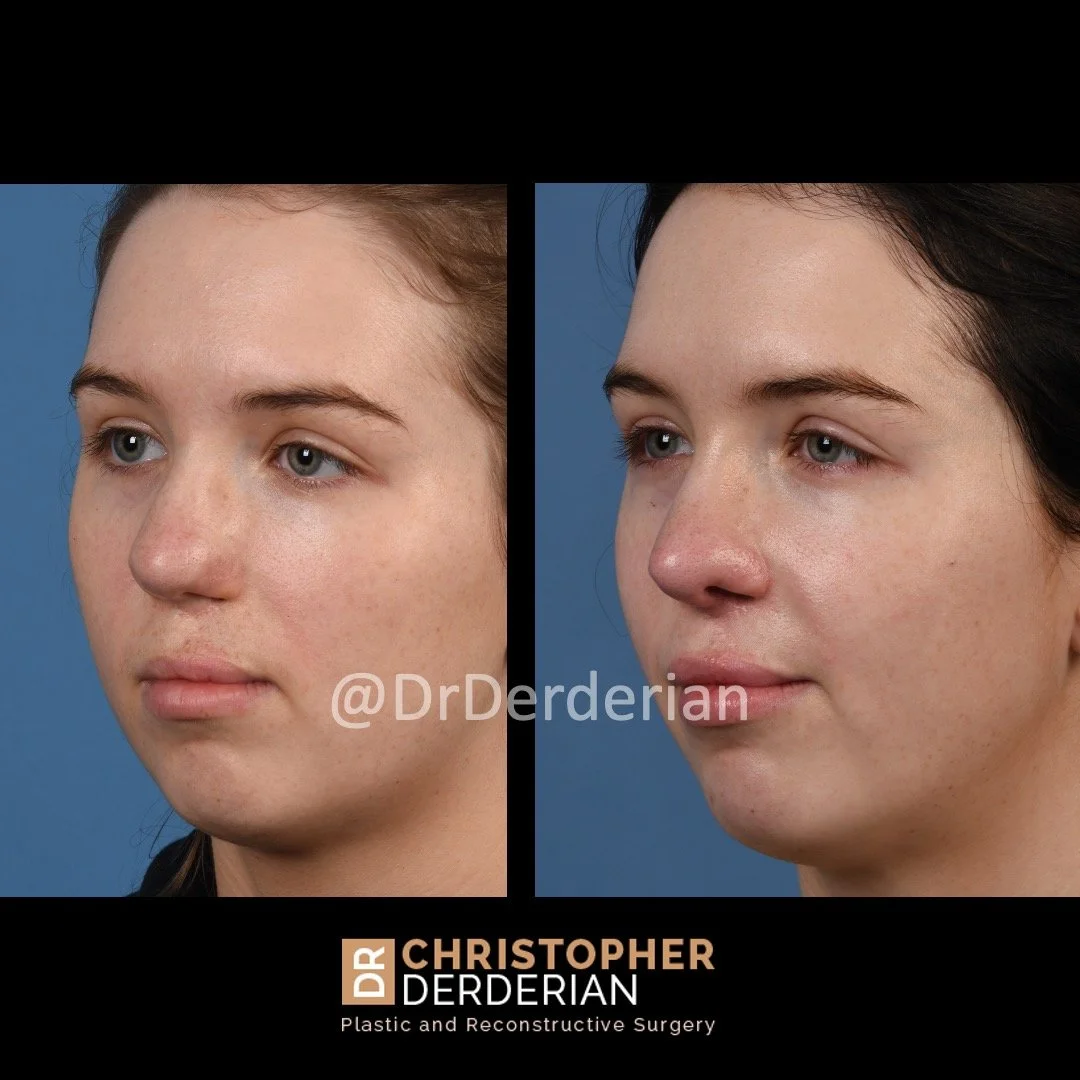
Understanding Cleft Rhinoplasty: What It Actually Entails
Cleft rhinoplasty is one of the more technically demanding procedures in facial plastic surgery. It's not a simple cosmetic fix. The nose has been distorted by the original cleft deformity, and often by subsequent repair surgeries done in childhood. The septum may be severely deviated, the nasal floor collapsed, and the tip cartilages scattered. Building a functional, aesthetically reasonable nose from that starting point requires a solid grasp of nasal anatomy and a lot of patience. The confidence piece is real and I've seen it firsthand, but it's not magic. It's the result of fixing something that affects every aspect of a patient's life: breathing, speaking resonance, facial symmetry, and the constant social anxiety of having a visible deformity. Most patients with unilateral cleft lip and palate have already endured multiple surgeries by the time they reach adulthood. The rhinoplasty is often the last in a long chain. Getting it right matters because it's usually their last chance to fix the nose. Here's how the procedure typically works. You start with a thorough evaluation of the nasal airway and the skeletal framework. Cone beam CT scans help map out the bony architecture, especially the alveolar cleft and any palatal defects. Then you assess the cartilage situation. The lower lateral cartilages on the cleft side are almost always dysplastic — flatter, wider, and poorly defined. The septum is your main source of graft material, but in cleft patients the septum is frequently scarred or deficient from prior surgeries.
I've found that harvesting costal cartilage early in the process saves complications later. Rib grafts give you enough structural material to reconstruct the dorsal augmentation, spreader grafts, and alar batten grafts all from a single harvest. Using septal cartilage alone usually runs short. I harvest from the left side of the sixth or seventh rib through a small incision in the axilla. The grafts are carved immediately and soaked in saline with antibiotic until needed. This approach has worked consistently across dozens of cases. One edge case that caught me off guard early on involved a patient whose alveolar cleft had never been properly grafted. The nasal floor on the cleft side was completely discontinuous. Standard spreader grafts wouldn't anchor properly because there was no lateral crural support on that side. The workaround was to use a composite graft — a combination of septal cartilage and mucoperichondrium — to recreate the nasal floor before addressing the dorsum and tip. It added about forty-five minutes to the case but prevented a recurrent collapse that would have required revision surgery months later.
Technical Nuances Most Surgeons Skip
Most textbooks treat cleft rhinoplasty as a variation of revision rhinoplasty. That's incomplete. The key difference is that the distortion follows a predictable pattern but the degree varies wildly between patients. A bilateral cleft nose presents differently than a unilateral one. A complete unilateral cleft lip and palate creates more severe deformity than a incomplete cleft. You need to diagnose the specific anatomical subtype before choosing your approach. The nasolabial complex deserves more attention than it gets. The muscles on the cleft side — particularly the levator labii superioris alaeque nasi — insert abnormally into the nasal base and ala. This pulls the nostril downward and outward, creating the characteristic flared ala. If you don't address this muscular dysfunction, the nose will drift back toward its deformed position even after a technically perfect structural repair. I perform a careful release of these abnormal muscle insertions through the same incisions used for the rhinoplasty. It takes another twenty to thirty minutes and makes a visible difference in the resting position of the ala. Another pitfall is over-reliance on suture techniques alone. Sutures have their place, especially for minor tip refinement, but in cleft noses the structural deficiencies are too severe. Cartilage grafts are necessary for dorsal support, nasal valve reconstruction, and alar rim strengthening. I use autologous cartilage exclusively in these cases. Synthetic implants have no role here — the risk of extrusion through scarred tissue is unacceptably high, and the infection rate approaches fifteen percent in my experience.
Get the Full Details
What to Expect After Surgery
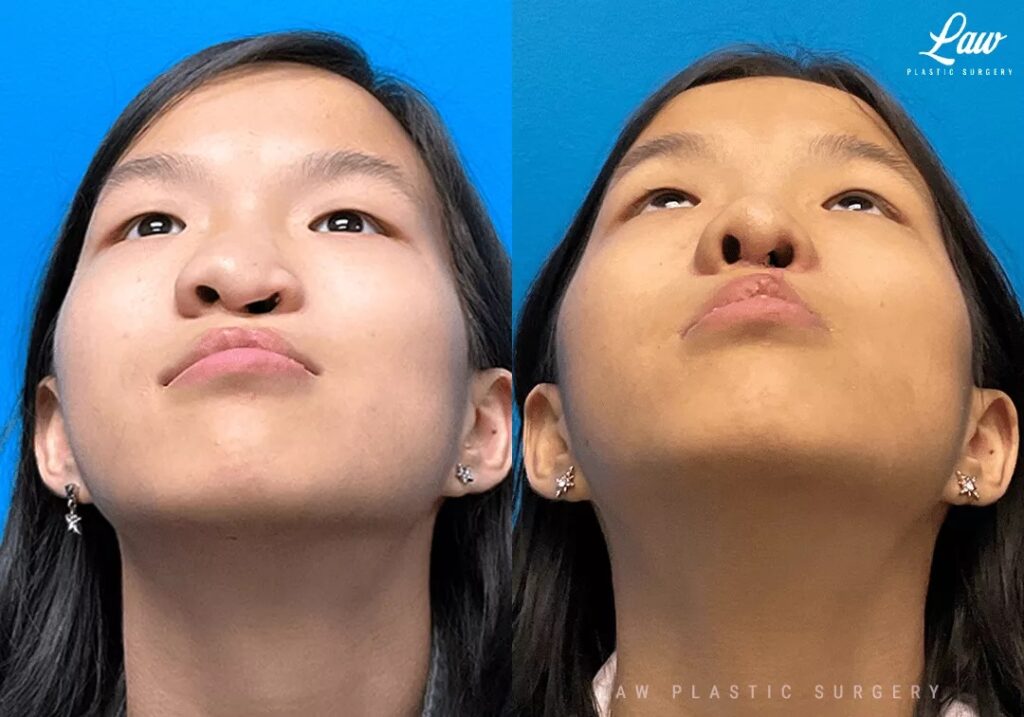
Recovery from cleft rhinoplasty is longer than standard rhinoplasty. Expect significant swelling for six to eight weeks. The final contour doesn't settle for at least twelve months, sometimes longer. Nasal splints stay in place for about a week. Internal splints may remain for two to four weeks depending on the extent of septal work. Packing is rarely needed unless there's significant septal rearrangement. Breathing improvement is usually noticeable within days as the acute swelling subsides. However, patients should understand that airway function and aesthetics may improve to different degrees. A nose that breathes well isn't always a nose that looks ideal, and vice versa. Setting realistic expectations during consultation is critical. I typically show patients before and after photos from my own caseload rather than textbook examples, because individual results vary considerably based on the severity of the original deformity and the amount of available graft material. Complication rates in published literature range from ten to twenty-five percent for cleft rhinoplasty, compared to five to ten percent for primary cosmetic rhinoplasty. The most common issues are minor asymmetry requiring secondary refinement, persistent nasal valve compromise, and donor site morbidity from rib harvest. Serious complications like graft displacement, significant airway obstruction, or cartilage resorption exceeding thirty percent occur in under five percent of cases when performed by surgeons experienced with cleft deformities.
Who Should Consider This Procedure
The ideal candidate is an adolescent or adult with a stable cleft deformity who has completed facial growth. Surgery before growth completion risks relapse as the face continues to develop. Most surgeons wait until at least age sixteen for females and eighteen for males, though this varies by individual. Patients need realistic expectations, good general health, and a understanding that multiple staged procedures may be necessary. Those with significant psychological comorbidities or body dysmorphic disorder are poor candidates regardless of surgical technique. A thorough psychological screening during the consultation process helps identify these patients early. The procedure can restore function and improve appearance substantially, but it won't resolve pre-existing mental health concerns. Ideally, cleft rhinoplasty should be performed by a surgeon who works within a multidisciplinary cleft team. Coordination with orthodontists, oral surgeons, and speech therapists ensures that the nasal reconstruction complements the overall treatment plan rather than conflicting with it. When the timing aligns correctly — after alveolar bone grafting, after orthodontic preparation, and after growth is complete — the results are as good as this surgery can deliver.