Understanding Medulla Oblongata Localization in Clinical and Research Settings
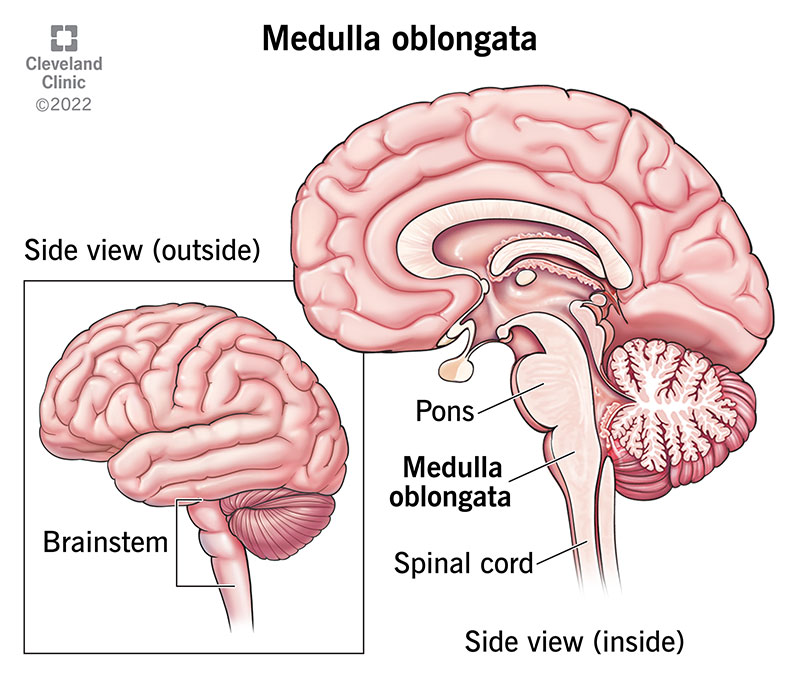
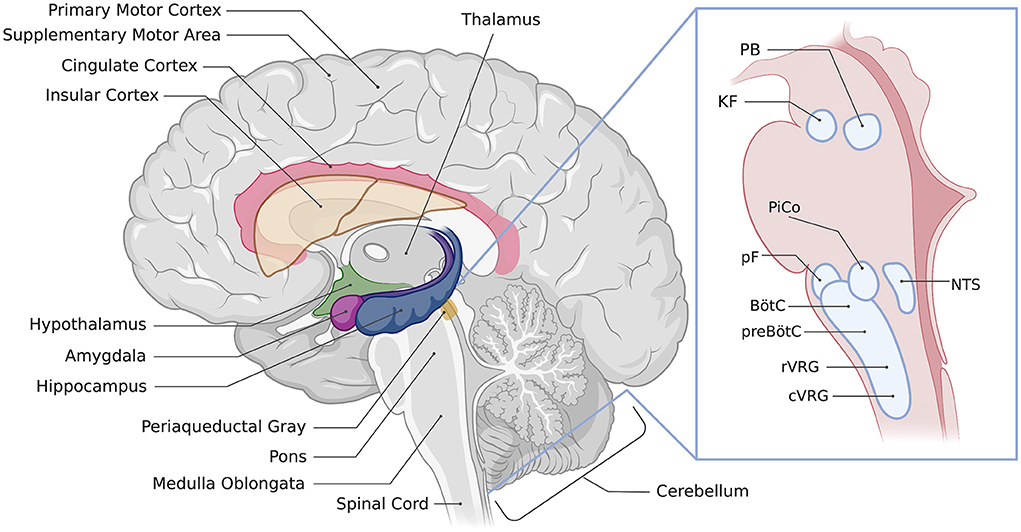
Mapping the medulla's precise boundaries is something most people encounter when they're either dissecting cadavers or interpreting high-resolution MRI sequences for surgical planning. It sits at the base of the brainstem, continuous with the cervical spinal cord inferiorly and merging into the pons superiorly. But "continuous" and "merging" are loose terms that don't help much when you're trying to identify the obex on a scan or locate the pyramidal decussation during a posterior fossa procedure. I spent about six months working through a series of brainstem specimens for a neurosurgery residency project, and let me tell you—the textbook drawings are clean, but real tissue doesn't always cooperate. You'll find the medulla roughly where the foramen magnum meets the clivus, but individual anatomy varies. The anterior surface bears the median fissure with the pyramids flanking it, while the posterior surface shows the gracile and cuneate tubercles. Simple enough until you're dealing with a patient who has a Chiari malformation, and suddenly your landmarks shift. That happened to me twice. We had to rely on bony anatomy instead—identifying the level of the foramen magnum and tracing upward about 2 centimeters to find the obex, which marks the transition between the fourth ventricle and the central canal.
The Medulla Location Mapping The Brainstems Vital Control Center
The medulla houses nuclei and tracts that you can't live without. Respiratory rhythm generation, cardiovascular regulation, swallowing, gag reflex—all of it converges here. The dorsal column nuclei (gracilis and cuneatus) relay proprioceptive information. The vestibular nuclei connect to the cerebellum and eye muscles. The nucleus ambiguus controls phonation and swallowing. If you're doing any kind of posterior fossa surgery, even a small resection near the floor of the fourth ventricle can knock out one of these and leave someone with dysphagia or autonomic instability. Here's the part most beginners miss: the medulla isn't a uniform block. It's organized into four functional columns along the rostrocaudal axis, and the internal architecture changes dramatically from the lower to upper portions. The lower medulla is essentially an extension of the spinal cord—same basic layout, just bulkier. The upper medulla starts incorporating structures like the inferior olivary nucleus, which is that characteristic olive-shaped bulge on the lateral surface. Between those two levels, you've got the pyramidal decussation, where about 85% of the corticospinal fibers cross. That's why a unilateral lesion above the decussation causes contralateral motor deficits, and below it causes ipsilateral ones. Get this wrong during surgical planning, and you'll be surprised by unexpected symptoms. When I'm mapping the medulla on MRI, I look for three consistent landmarks. First, the medullary pyramids on the ventral surface—they're those paired longitudinal ridges. Second, the obex posteriorly, where the fourth ventricle narrows into the central canal. Third, the inferior cerebellar peduncles laterally, which connect to the cerebellum. On T2-weighted sequences, the pyramids show up as relatively hypointense bands against the surrounding tissue. The medial lemniscus sits just dorsal to the pyramids, and the spinal trigeminal tract occupies the lateral margin. If you're doing diffusion tensor imaging, you can actually trace the corticospinal tracts through the pyramids, which helps confirm whether they're intact before you proceed with anything invasive.
Clinically, isolated medullary lesions are rare because the area is so compact. Most medullary syndromes occur as part of broader brainstem or cervical cord pathology. Lateral medullary syndrome (Wallenberg) is the classic presentation—contralateral body sensory loss, ipsilateral face sensory loss, Horner syndrome, dysphagia, vertigo, ataxia. But even that requires understanding which vascular territories supply different parts of the medulla. The anterior spinal artery feeds the medial portion, including the pyramids and medial lemniscus. The vertebral arteries or PICA supply the lateral medulla. A thrombosis in one versus the other produces completely different clinical pictures. One thing I wish more people understood: the medulla's control over autonomic functions means lesions here can be deceptively dangerous. Someone might look fine neurologically except for a mild gait imbalance, but their blood pressure variability or respiratory patterns could be profoundly affected. I saw a case where a small vascular malformation in the ventrolateral medulla presented only as episodic syncope for months before anyone connected it to the brainstem. By the time we imaged it, the patient had already suffered two near-fatal falls. Don't underestimate the medulla because it's "just the lower brainstem." It's not. It's the gatekeeper between your conscious nervous system and everything that runs automatically. If you're learning this for anatomical study, start with axial slices at the level of the lower medulla and work your way up. Label the pyramids, the decussation, the gracile and cuneate tubercles, then add the olivary complex as you move superiorly. The cerebellar tonsils sit just dorsal to the medulla, which is relevant if you're studying Chiari malformations or posterior fossa masses. The key is recognizing that the medulla doesn't end abruptly—it tapers into the spinal cord, and that transition zone is where clinical localization gets tricky. You need to correlate imaging findings with the actual vertebral levels, which is why I always cross-reference with CT myelography or at least a good bony landmark scan.
Get the Full Details
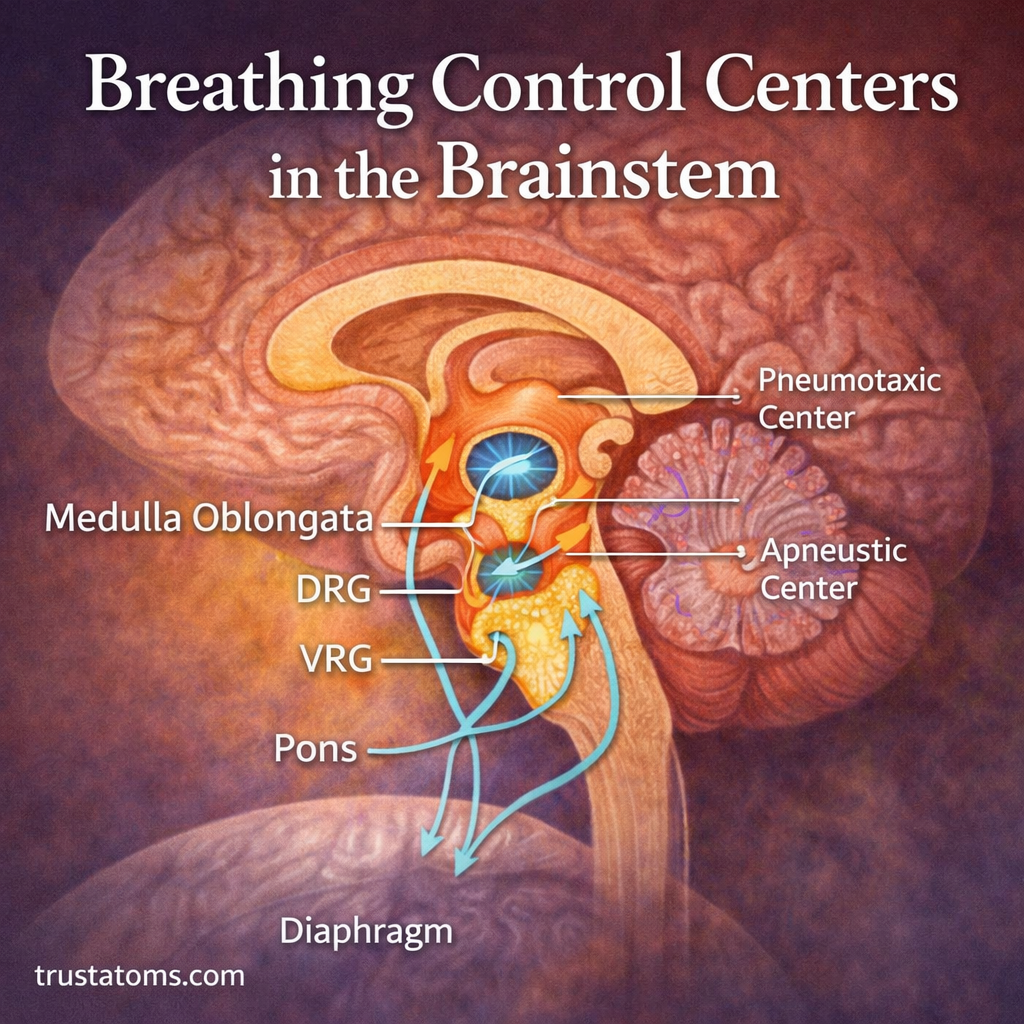
For research purposes, the medulla's topographic organization is well mapped, but the functional heterogeneity within each nucleus is still being refined. Single-unit recordings in animal models have shown subnuclei within the nucleus ambiguus that preferentially control different muscular targets—laryngeal versus pharyngeal versus cardiac branches. That kind of precision matters if you're developing neuromodulation therapies for dysphagia or cardiorespiratory disorders. The medulla isn't just a relay station. It's an integrative center, and its output extends way beyond what most textbooks emphasize. I keep this simple: when you're working with the medulla, respect the anatomy, understand the vascular supply, and don't assume that a small lesion is a benign one. The structure is compact, the functions are vital, and the clinical consequences of injury are immediate and often permanent. That's not dramatic language—that's just what the tissue does.